

AF Form 4380 at a glance
What it is: AIRFORCE SPECIAL NEEDS SCREENER (Completed by all Sponsors with Family Members)
Who signs: Sign and date the form at Sponsor's Signature Date.
The Air Force makes an effort to ensure specialized medical and educational services are available for all military family members. In order to help the Air Force do this, the Air Force needs to know if any special medical and/or educational needs exist for your family members. You are required to complete this form as part of your relocation processing, if you have family members, whether they are living with you or not.
AUTHORITY: 10 U.S.C. 55. 10 U.S.C. 8013 and E.O. 9397 (SSN) as amended. PURPOSE(S): Used to document, plan, and coordinate the health care of family members during relocation; determine eligibility and suitability for benefits for various programs; and compile statistical data. ROUTINE USE: Used to accumulate information for determining family member special needs.
A filled-in AF Form 4380 example: a sponsor answers No to every question

How to fill out AF Form 4380, box by box
Sponsor's Name, Current Unit and Projected Departure Date
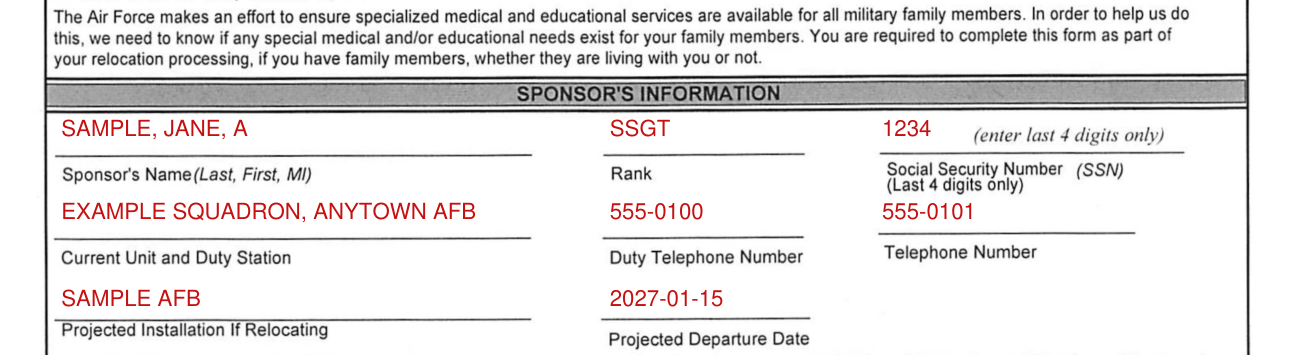
Sponsor's Name (Last, First, Ml) Rank Social Security Number (SSN) (Last 4 digits only) (enter last 4 digits only)
Enter the Current Unit and Duty Station, the Duty Telephone Number and the Telephone Number.
Enter the Projected Installation If Relocating and the Projected Departure Date.
Sponsor's Family Information and question 1

SPONSOR'S FAMILY INFORMATION Please read and answer all questions. Indicate (X) the appropriate box. Thank you. Yes □ No □
1. Are your currently enrolled in any Service's Exceptional Family Member Program (EFMP)? If yes, stop here.
Questions 2 to 9

2. Do any of your children receive Special Education Services?
3. Do any of your children receive Early Intervention Services?
4. Do any of your family members receive speech therapy, occupational therapy, physical therapy, or counseling services?
5. Has any dependent member of your family been hospitalized for the same condition more than once?
6. Has any dependent member of your family been seen by a medical provider or mental health provider for the same condition more than once times in the last year?
7. Do any of your family members have a chronic medical condition that requires at least annual evaluation or follow-up by a specialist, other than a PCM (such as cardiology, internist, psychology, neurology,
8. Do any of your dependent family members have reactive airway disease or asthma?
9. Do any of your family members require specialized equipment or modified housing?
If YES to any questions numbered 2 - 8, please contact the Exceptional Family Member Program (EFMP-M) Office at the Military Treatment Facility for assistance prior to pursuing any further relocation actions.
Sponsor's Signature Date

"I certify that this information is complete and accurate to the best of my knowledge. I understand that insufficient and/or inaccurate information may affect family member travel at government expense. I understand that making a knowing and willful false official statement can be punishable by fine or imprisonment. (See U.S. Code, Title 18, Section 1001; Title 10, Section 907; Article 107 UCMJ)."
Sign and date the form at Sponsor's Signature Date.
More rules for AF Form 4380
DISCLOSURE: Voluntary; however, failure to provide SSN or other requested information may delay screening of family member's suitability for relocation at government expense or delay issuance of PCS orders.
TO: Special Needs Coordinator and Air Force Personnel Center (AFPC) FROM: Air Force Family Member Special Needs Identification Screener
Sources
[1] AF Form 4380 (20150806), Air Force Special Needs Screener, U.S. Air Force (the Official source link on this page).
