

Form 211 at a glance
What it is: Form 211 is the Alabama Medicaid Agency's Application for Medicare Savings Programs.
Who signs: Sign the application: the Signature of Applicant or Representative and the Signature of Applicant's Spouse or Representative, each with the Date.
This is NOT an application for full Medicaid.
What to bring and attach to Form 211
Send verification of the gross amount (before taxes) of your monthly income.
A copy of most recent check stub or other verification must be provided.
A filled-in Form 211 example: a widow fills out the applicant page

How to fill out Form 211, box by box
1 APPLICANT
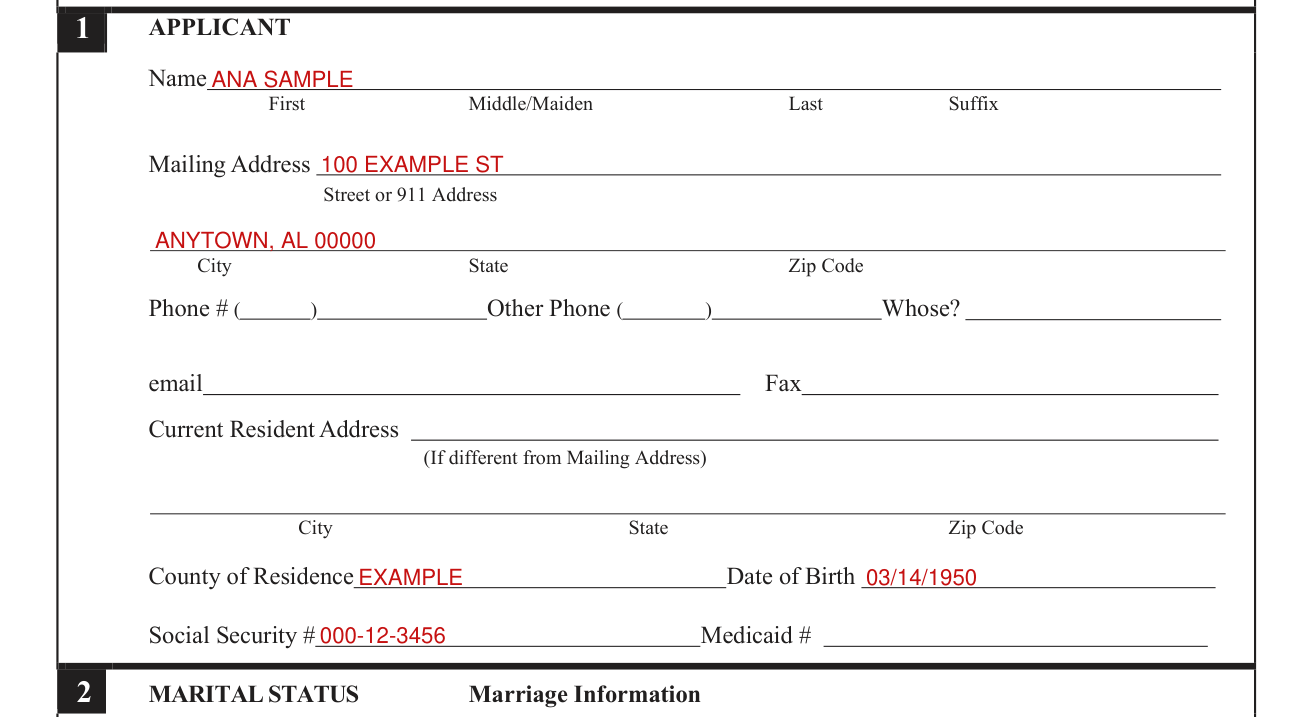
On Form 211 Application for Medicare Savings Programs 3-2023, please print clearly using dark ink.
Enter your Name: First, Middle/Maiden, Last, Suffix.
Under Mailing Address, enter the Street or 911 Address, then the City, State and Zip Code.
Enter your Phone #, Other Phone and Whose?, then your email and Fax.
Enter the Current Resident Address (If different from Mailing Address), then the City, State and Zip Code.
Enter your County of Residence, Date of Birth, Social Security # and Medicaid #.
2 MARITAL STATUS
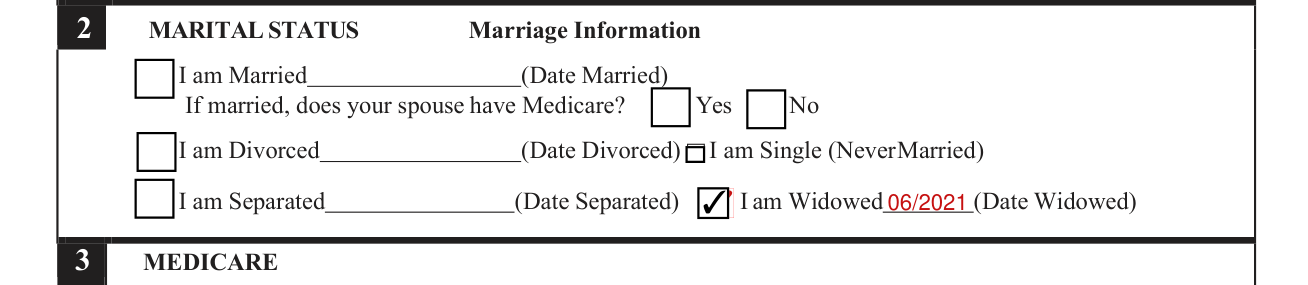
Under Marriage Information, mark I am Married (Date Married) and, if married, mark Yes or No for does your spouse have Medicare?; or mark I am Divorced (Date Divorced), I am Single (Never Married), I am Separated (Date Separated) or I am Widowed (Date Widowed).
3 MEDICARE

Mark Yes or No for Do you have Medicare Part A (Hospital) Coverage?, then enter the Name on Medicare card and the Medicare #.
4 RACE
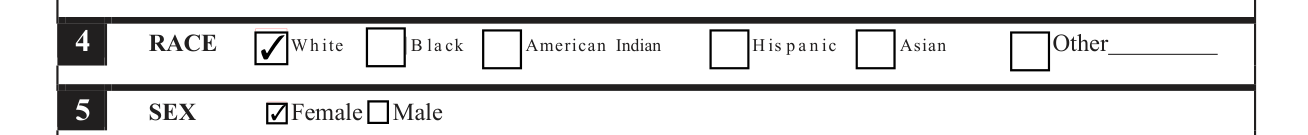
Mark White, Black, American Indian, Hispanic, Asian or Other.
5 SEX

Mark Female or Male.
6 FAMILY SIZE
Enter the Applicant's Name and SS #. Under FAMILY SIZE, list names of anyone living in your home with their Name, Age and Relationship.
7 SPONSOR

If the applicant is unable to complete the application or provide additional information, the Medicaid sponsor should be the person most familiar with the financial situation of the applicant. Please complete the Appointment of Representative form on Page 6 of this application.
Enter the Relationship to Applicant, Name, Home Phone, Address, Work Phone, Cell Phone, City State Zip, email and FAX.
8 SPOUSE INFORMATION
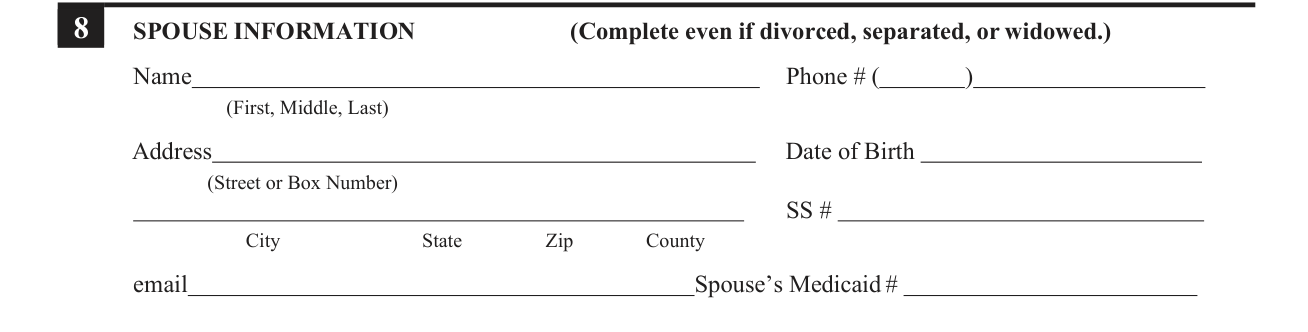
Complete SPOUSE INFORMATION even if divorced, separated, or widowed.
Enter the spouse's Name (First, Middle, Last), Phone #, Address (Street or Box Number), Date of Birth, SS #, City, State, Zip, County, email and Spouse's Medicaid #.
9 FORMER SPOUSE INFORMATION
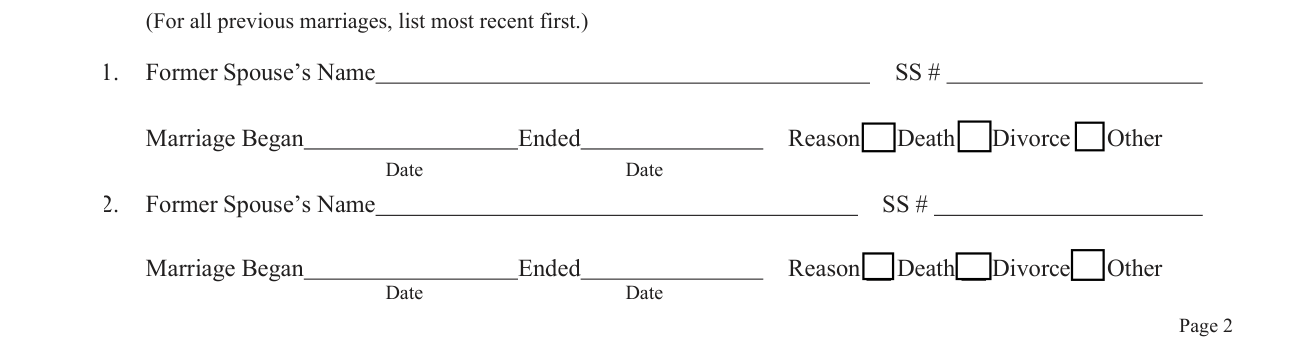
FORMER SPOUSE INFORMATION must be completed if you are widowed or divorced. For all previous marriages, list most recent first.
For each former spouse, enter the Former Spouse's Name, SS #, the Date Marriage Began and the Date Ended, and mark the Reason: Death, Divorce or Other.
10 VETERAN'S STATUS
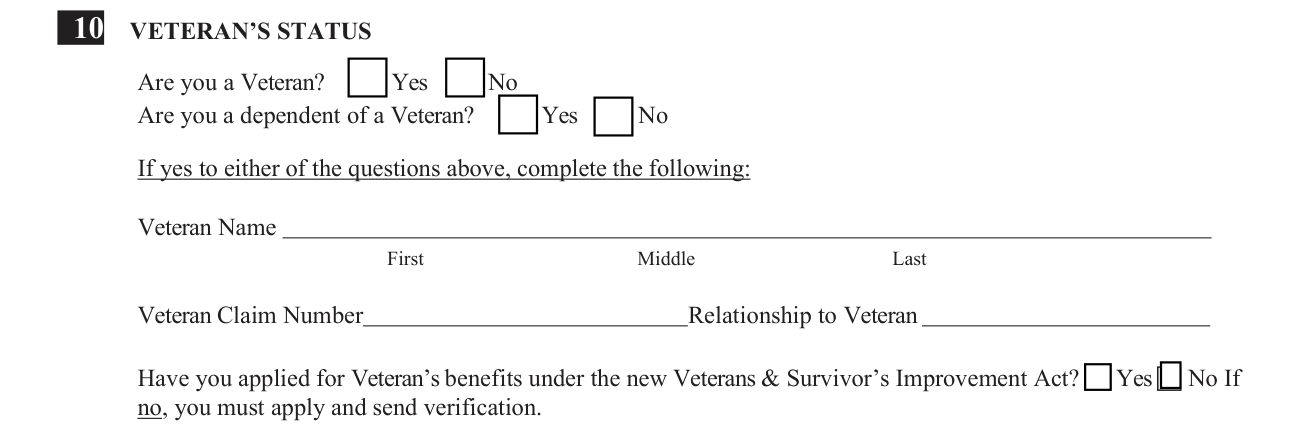
Under 10 VETERAN'S STATUS, mark Yes or No for Are you a Veteran? and for Are you a dependent of a Veteran?; if yes to either of these questions, complete the following: the Veteran Name (First, Middle, Last), Veteran Claim Number and Relationship to Veteran.
Mark Yes or No for Have you applied for Veteran's benefits under the new Veterans & Survivor's Improvement Act? If no, you must apply and send verification.
11 RESIDENCY INFORMATION

Under 11 RESIDENCY INFORMATION, mark Yes or No for Are you a United States Citizen? and for Are you a lawfully admitted alien?, then enter Where were you born? with City, County, State and Country.
Mark Yes or No for Do you live in Alabama and plan to stay?; mark English, Spanish or Other for What language do you usually speak?; mark Yes or No for Do you or a family member speak English? and for Have you ever applied for or received SSI?
If yes, were you terminated from SSI? When? Enter the Month/Year.
12 OTHER INSURANCE
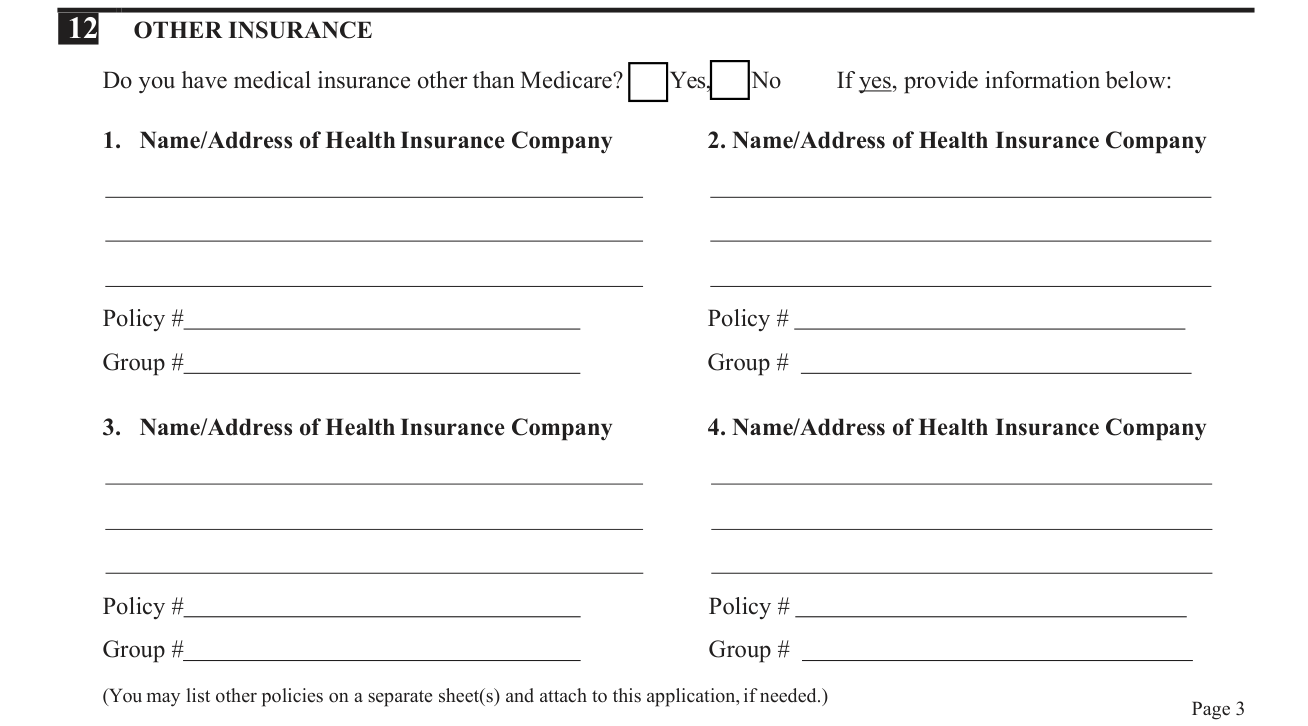
Mark Yes or No for Do you have medical insurance other than Medicare? If yes, provide information: for each of 1. to 4., the Name/Address of Health Insurance Company, Policy # and Group #.
You may list other policies on a separate sheet(s) and attach to this application, if needed.
13 GROSS INCOME
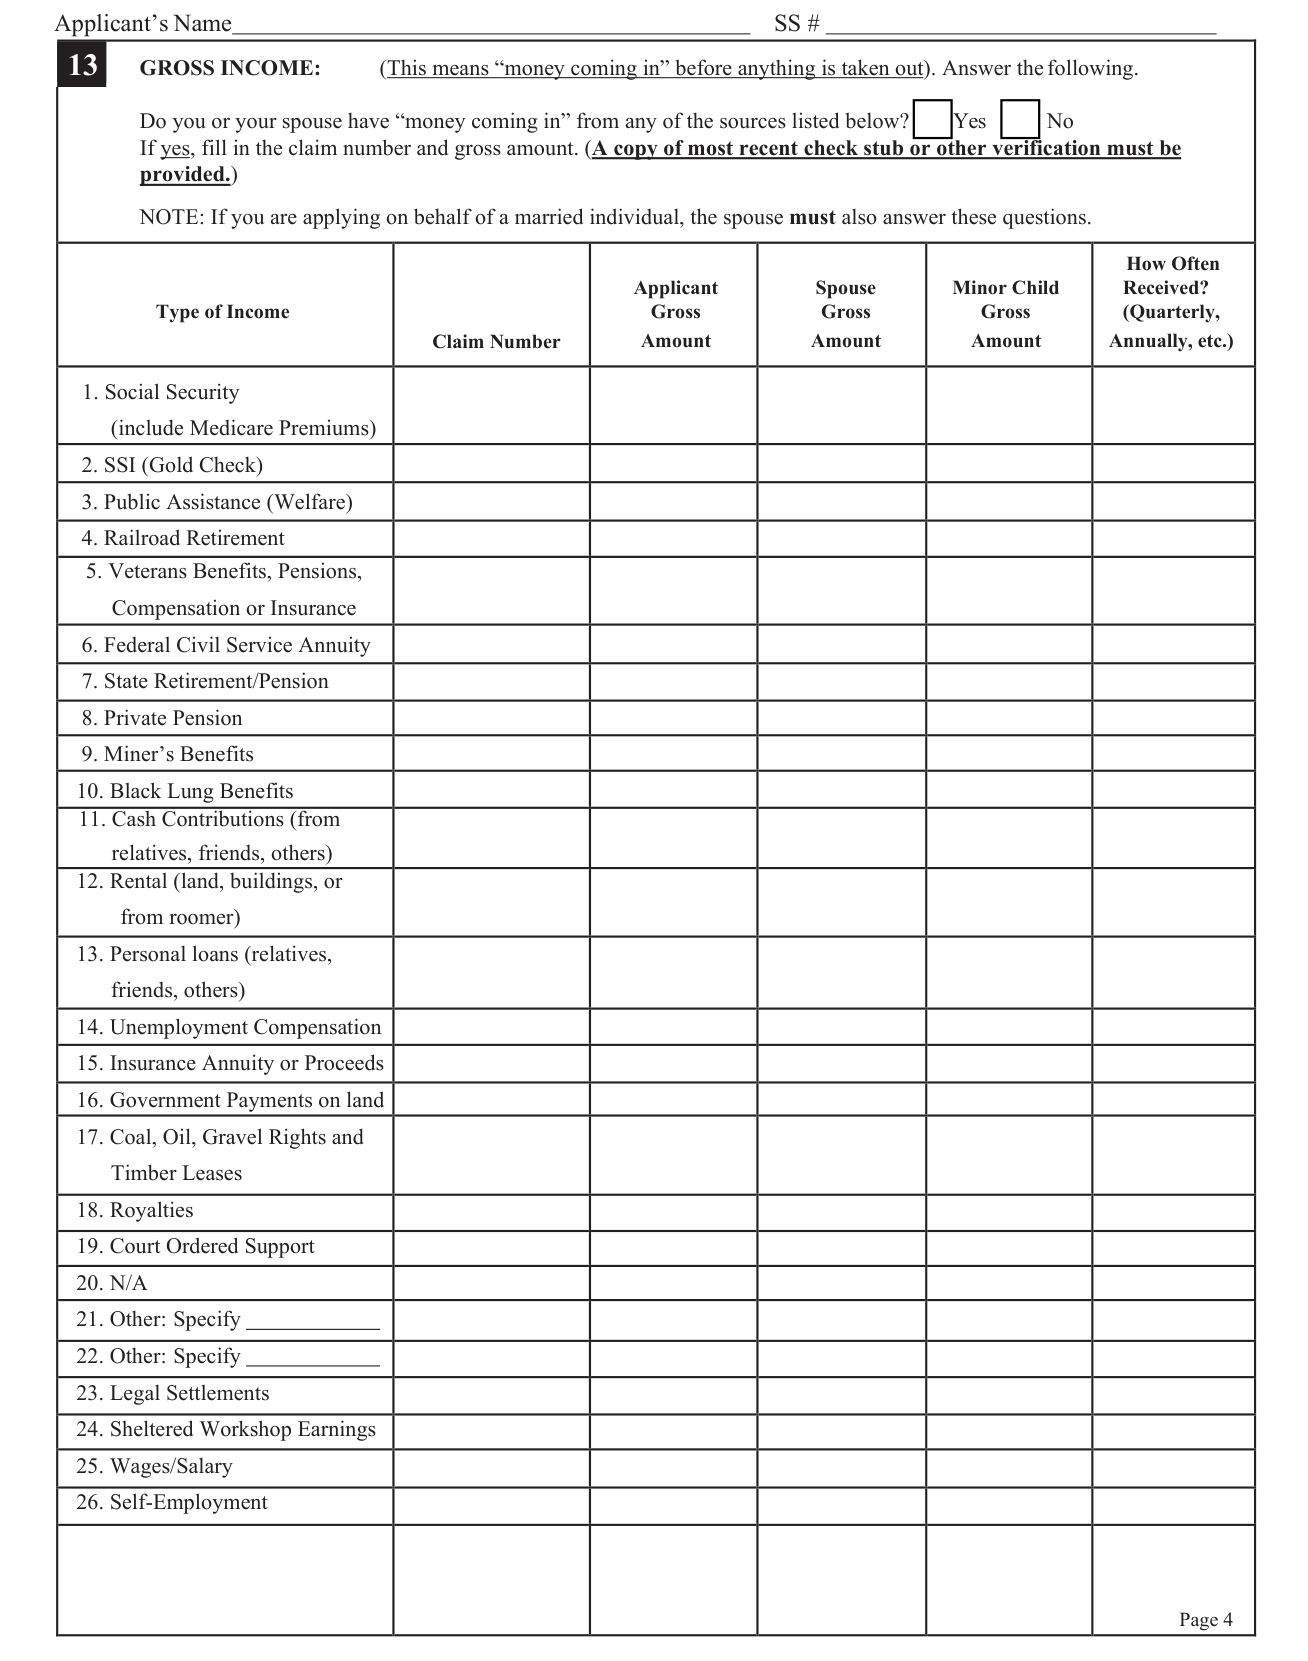
Under 13 GROSS INCOME, mark Yes or No for Do you or your spouse have “money coming in” from any of the sources listed under Type of Income? If yes, fill in the claim number and gross amount: enter the Claim Number, Applicant Gross Amount, Spouse Gross Amount, Minor Child Gross Amount and How Often Received? (Quarterly, Annually, etc.)
If you are applying on behalf of a married individual, the spouse must also answer these questions.
Release of Information, Responsibilities and Signature of Applicant or Representative

Under RELEASE OF INFORMATION, by signing, you authorize and give consent for the Alabama Medicaid Agency to obtain information from any source for the purpose of determining eligibility for Medicaid benefits.
Under AFFIRMATION AND AGREEMENT, you give permission to the Alabama Medicaid Agency to use your Social Security number to get information about your resources and income from banks, financial institutions, employers, and other county, state, and federal agencies, and/or to see if you qualify for assistance or to see if you have insurance. If you are approved for Medicaid, you assign all insurance and medical support benefits to Medicaid. Under RESPONSIBILITIES, notify the Medicaid District Office within ten (10 days), if there is a change in your address, living arrangements, family size, income or resources.
Anyone who makes or causes to be made a false statement, representation or omission of a material fact in an application or for use in determining eligibility for Medicaid commits a crime punishable under Federal or State Law or both. Affirm under penalty of perjury that all information you give in this document or in support of it is true.
Any application found to contain material misstatements or omissions will be denied.
Sign Signature of Applicant or Representative and enter the Date.
Sign Signature of Applicant's Spouse or Representative and enter the Date.
Renewal of coverage in future years
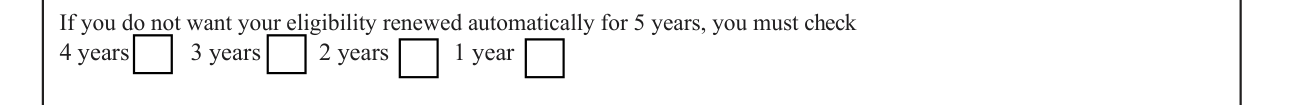
Agree to allow Medicaid to use income data, including information from tax returns. Medicaid will send you a notice, let you make any changes and you can opt out at any time.
Mark Yes, renew my eligibility automatically for the next five years without completing a renewal.
If you do not want your eligibility renewed automatically for 5 years, you must check 4 years, 3 years, 2 years or 1 year.
APPOINTMENT OF REPRESENTATIVE

Under APPOINTMENT OF REPRESENTATIVE, enter the Sponsor's Name after I hereby appoint, fill in Done this the day of , 20 , then sign the Signature of Medicaid Claimant and enter the Social Security Number and the WITNESSES. If claimant cannot sign his/her name but can make a mark, this is acceptable if witnessed by two adults. If claimant has a legally appointed guardian, conservator or someone with durable power of attorney who will represent him/her for Medicaid purposes, claimant's signature on this form is not required. The representative signs under ACCEPTANCE OF APPOINTMENT only and attaches to this form a copy of evidence of legal authority to act on claimant's behalf (Letter of Conservatorship/Guardianship or Durable Power of Attorney).
ACCEPTANCE OF APPOINTMENT

Under ACCEPTANCE OF APPOINTMENT, the representative enters My relationship (Attorney, relative, etc.), fills in Done this the day of , 20 , signs the Signature of Sponsor/Representative and enters the Address, City, State, Zip, Telephone Number and the WITNESSES.
More rules for Form 211
Read this application carefully and follow all instructions given throughout the form. Answer each question completely and accurately.
Common questions about Form 211
What is form 211 for?
Form 211 is the Alabama Medicaid Agency's Application for Medicare Savings Programs. These programs cover Medicare premiums and deductibles. Medicaid will not pay for any excluded drugs under Medicare Part D.
Where do I file it?
Send the application to Medicaid either by email or U.S. Postal Service mail. Email: apply@medicaid.alabama.gov, or Mail: to the District Office serving your county.
Is there a penalty?
Federal and state laws provide both criminal and civil penalties for false statements or material omissions in an application for Medicaid benefits or payments. Any person who, with intent to defraud or deceive, makes a false statement, representation or omission of a material fact in any claim or application for medical benefits from the Medicaid agency, knowing the same to be false, shall be guilty of a felony and upon conviction shall be fined not more than $10,000.00 or imprisoned for not less than one nor more than five years, or both (checked November 2, 2026).
Sources
[1] Form 211 (Revised 3/9/23), Application for Medicare Savings Programs, Alabama Medicaid Agency (the Official source link on this page).
