

BCBSM Subrogation Unit Questionnaire at a glance
What it is: This is the BCBSM Subrogation Unit Questionnaire. Fax the completed form to 877-257-2012.
Where and when to file: Office of the General Counsel Subrogation Department, 232 S. Capitol Ave., L09A, Lansing, Michigan 48933-1504, (517) 325-4658, FAX No. (877) 257-2012, E-mail: SubrogationUnit@bcbsm.com.
A filled-in BCBSM Subrogation Unit Questionnaire example: a client reports a car crash
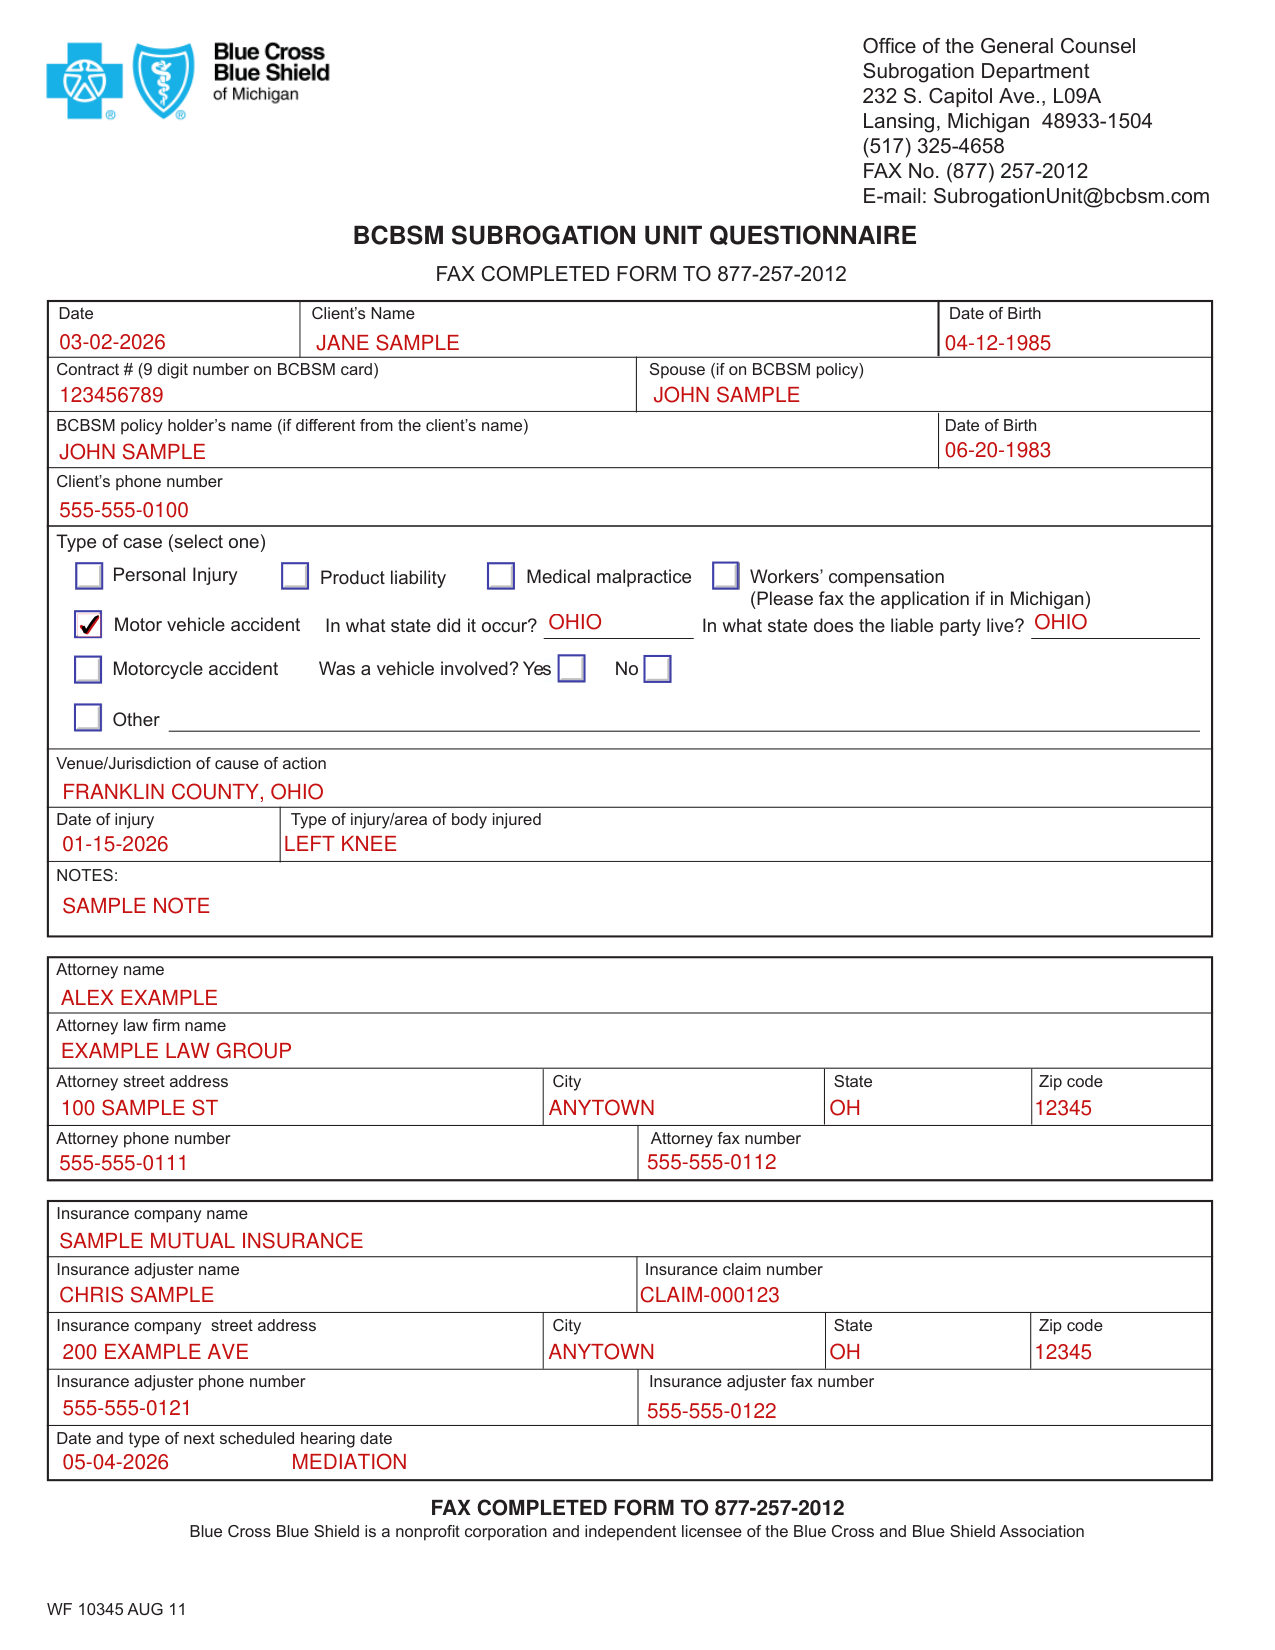
How to fill out BCBSM Subrogation Unit Questionnaire, box by box
Client and policy holder
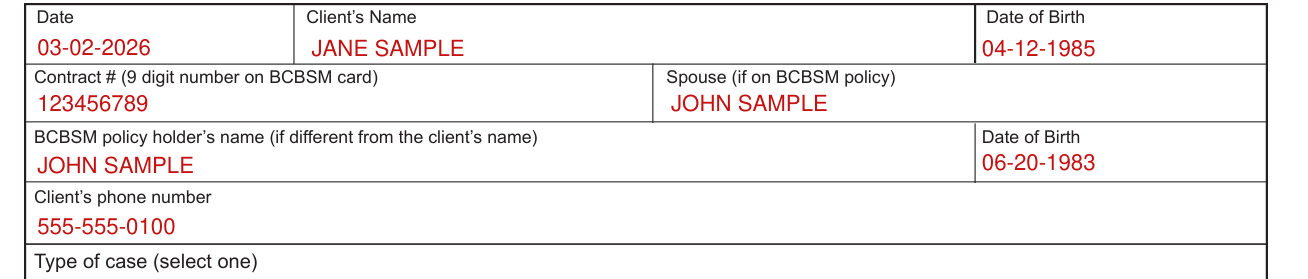
Enter the Date, the Client's Name and the Date of Birth. Enter the Contract # (9 digit number on BCBSM card) and the Spouse (if on BCBSM policy). Enter the BCBSM policy holder's name (if different from the client's name) and the Date of Birth, then the Client's phone number.
Type of case (select one)

For Type of case (select one): Personal Injury, Product liability, Medical malpractice, Workers' compensation (Please fax the application if in Michigan), Motor vehicle accident, Motorcycle accident or Other.
For Motor vehicle accident, enter the state for: In what state did it occur? In what state does the liable party live? For Motorcycle accident, mark Yes or No to: Was a vehicle involved?
Venue and injury

Enter the Venue/Jurisdiction of cause of action, the Date of injury and the Type of injury/area of body injured, with any NOTES.
Attorney
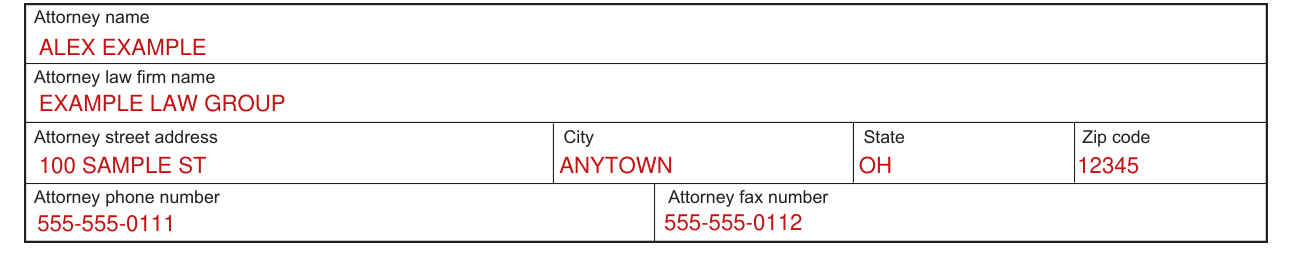
Enter the Attorney name, Attorney law firm name, Attorney street address, City, State, Zip code, Attorney phone number and Attorney fax number.
Insurance company and adjuster

Enter the Insurance company name, Insurance adjuster name, Insurance claim number, Insurance company street address, City, State, Zip code, Insurance adjuster phone number and Insurance adjuster fax number.
Next scheduled hearing

Enter the Date and type of next scheduled hearing date.
Sources
[1] BCBSM Subrogation Unit Questionnaire (WF 10345 AUG 11), Blue Cross Blue Shield of Michigan (the Official source link on this page).
