

Form 07I-61 at a glance
What it is: Form 07I-61 is the Medical Board of California Consumer Complaint Form.
Where and when to file: Enforcement Program, 2005 Evergreen Street, Suite 1200, Sacramento, CA 95815-5401, mbc.ca.gov.
You must fill out a separate complaint form for each physician or other healthcare provider or unlicensed provider you wish to file a complaint against.
A filled-in Form 07I-61 example: a complaint about a physician's treatment

How to fill out Form 07I-61, box by box
COMPLAINT REGISTERED AGAINST and Subject Information
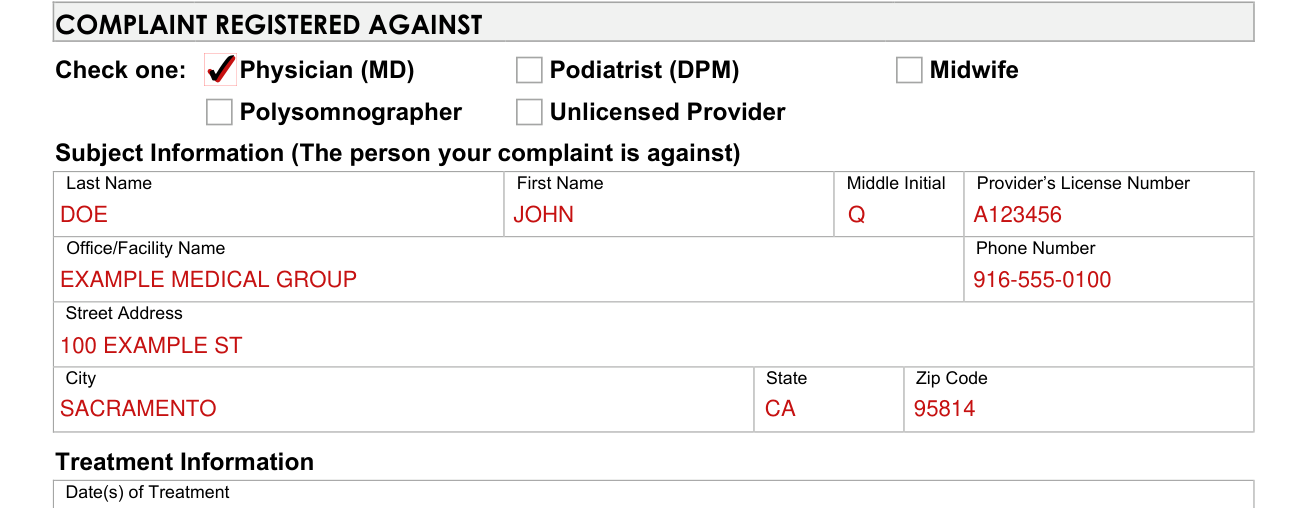
Fill in the full name, address, telephone number, and license number (if known) of the person your complaint is against. This information must also be included in the corresponding section of the Authorization for Release of Information form. The Medical Board only handles complaints against the listed individuals on the second page, and complaints about unlicensed practice.
Under COMPLAINT REGISTERED AGAINST, check one: Physician (MD), Podiatrist (DPM), Midwife, Polysomnographer or Unlicensed Provider.
Under Subject Information (The person your complaint is against), fill in Last Name, First Name, Middle Initial and Provider's License Number.
Fill in the Office/Facility Name, Phone Number, Street Address, City, State and Zip Code.
Treatment Information
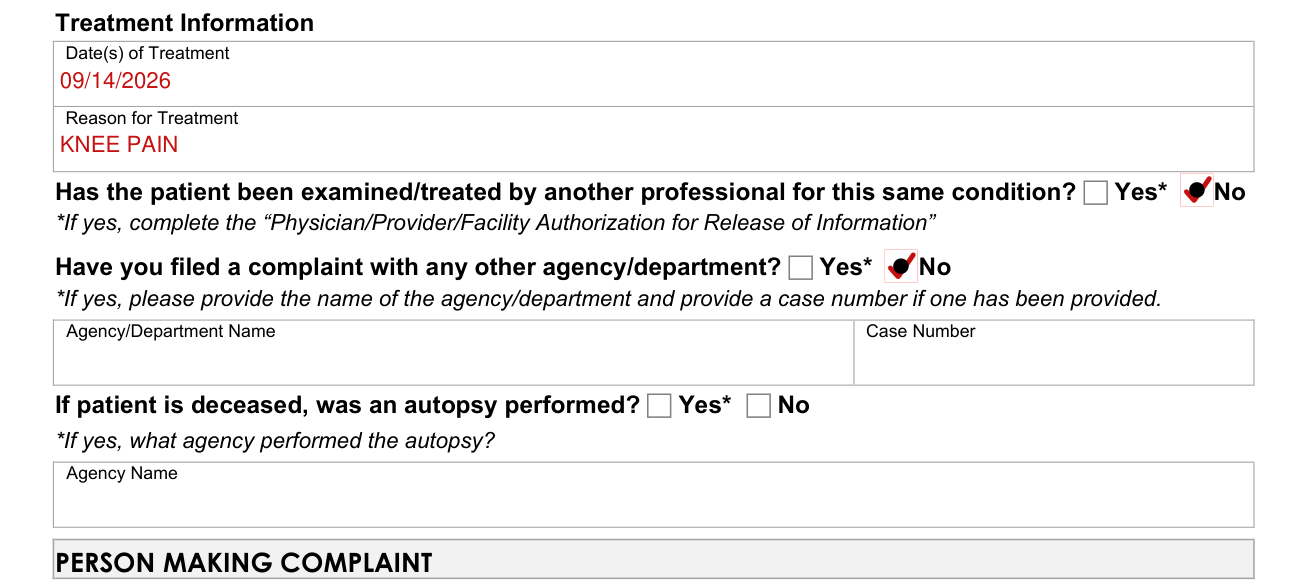
Under Treatment Information, fill in Date(s) of Treatment and Reason for Treatment.
Has the patient been examined/treated by another professional for this same condition? Mark Yes or No. If yes, complete the “Physician/Provider/Facility Authorization for Release of Information”.
If you were treated by another provider or received treatment at a health facility related to your complaint, complete one of the following medical release forms in their entirety: “Physician/Provider/Facility Authorization for Release of Information”.
Should care and treatment have been rendered at a Kaiser facility please fill out the enclosed Kaiser form and check if it's a “northern” or “southern” facility.
Have you filed a complaint with any other agency/department? Mark Yes or No. If yes, please provide the name of the agency/department and provide a case number if one has been provided.
If patient is deceased, was an autopsy performed? Mark Yes or No. If yes, write the agency that performed the autopsy under Agency Name.
If the patient is deceased, the person signing the release form(s) must be the patient's representative as demonstrated on a durable power of attorney, death certificate, or an executor of will/estate document. Please include a copy of supportive documentation, including the autopsy report or Coroner/Medical Examiner's report if applicable.
Person making complaint and patient information
Except for the name of the person your complaint is against, all information requested is voluntary, but failure to provide this information may delay or prevent the investigation of your complaint. The information on the complaint form will be used in part to determine whether a violation of law has occurred. If a violation is substantiated, the information may be transmitted to other governmental agencies, including, but not limited to, the Attorney General's Office.
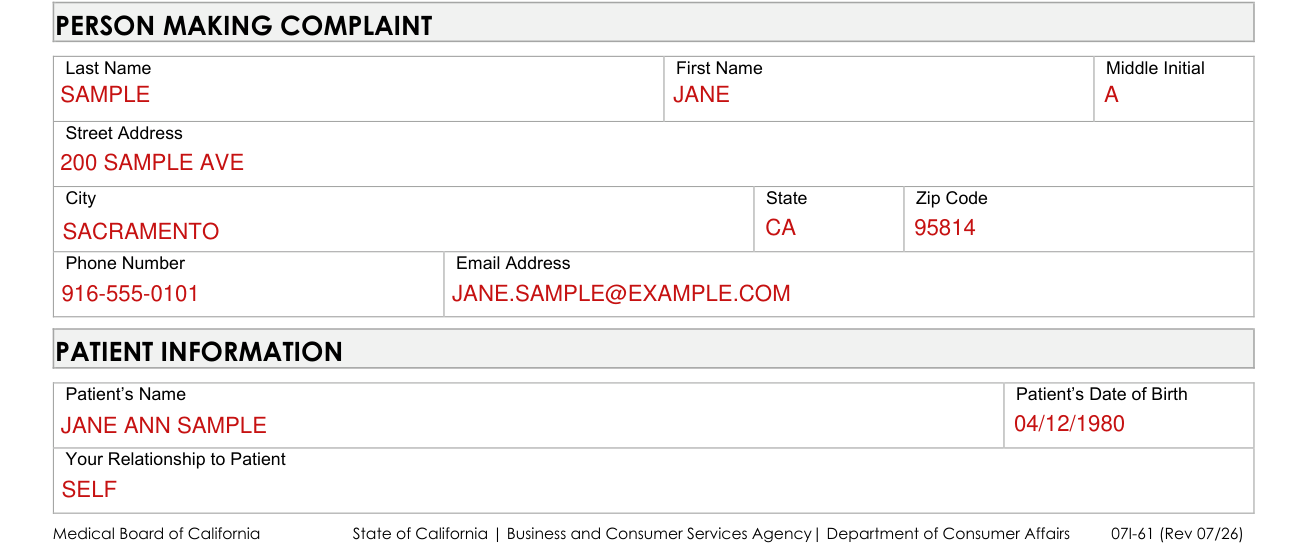
Under PERSON MAKING COMPLAINT, fill in Last Name, First Name, Middle Initial, Street Address, City, State, Zip Code, Phone Number and Email Address.
Under PATIENT INFORMATION, fill in the Patient's Name, the Patient's Date of Birth and Your Relationship to Patient.
Nature of complaint

Under NATURE OF COMPLAINT, check all that apply: Quality of Care (Misdiagnosis, treatment/medication causing side effects, surgical complications, negligent care, etc.); Office Practice (Failure to sign death certificate, failure to provide records, misleading advertising, double billing, billing for services not rendered); Inappropriate Prescribing; Provider Impairment (Under the influence of drugs or alcohol, mental or physical impairment); Sexual Misconduct; Unlicensed Activity (Aiding and abetting unlicensed practice, unlicensed provider); Other.
Details of complaint and signature date

Under DETAILS OF COMPLAINT, state your complaint in chronological order and in detail. Attach additional pages if necessary. In addition, please include dates of treatment and list all relevant treating providers specific to your complaint.
It is important that you be specific regarding any allegations of substandard care. Providing a comprehensive narrative of your complaint allows for a more expeditious review process.
Authorization for Release of Information for the Subject of the Complaint, record types and patient
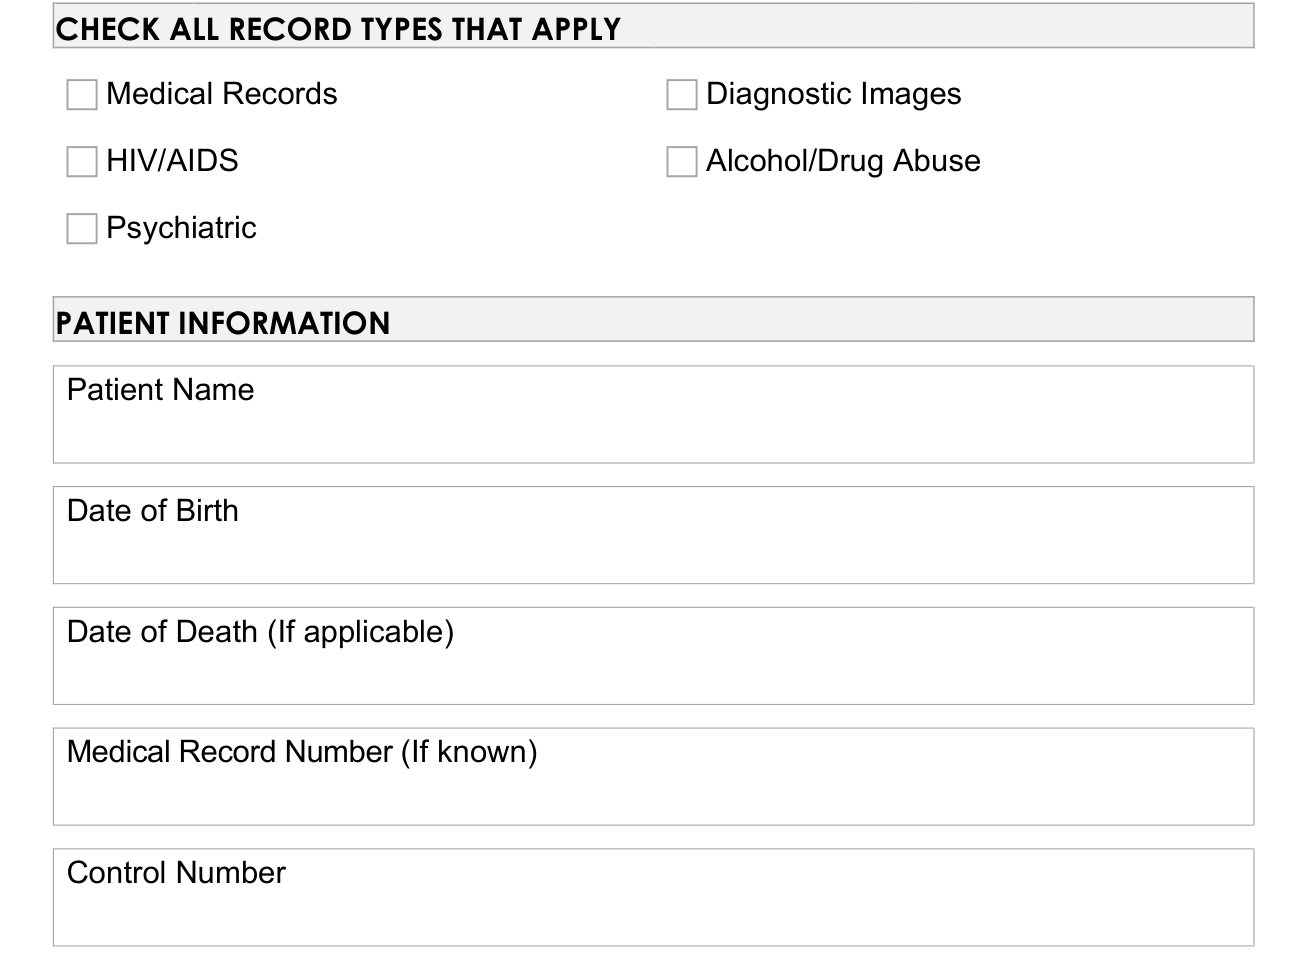
Complete the “Authorization for Release of Information for the Subject of the Complaint” (Subject is the physician or other healthcare provider you are complaining about). This form is necessary to obtain information from the physician your complaint is about.
Under Check all record types that apply, check Medical Records, Diagnostic Images, HIV/AIDS, Alcohol/Drug Abuse or Psychiatric.
Under PATIENT INFORMATION, fill in Patient Name, Date of Birth, Date of Death (If applicable), Medical Record Number (If known) and Control Number.
Patient Name, Physician/Provider and Patient Signature

Fill in the Patient Name and, after I, the undersigned hereby authorize, the Physician/Provider, Street Address, City, State, Zip Code, Phone Number and Treatment Date(s).
Add the Patient Signature and Date - OR - the Patient Representative Name, Relationship to Patient, Patient Representative Signature and Date.
This authorization shall remain valid for three years from the date of signature.
Failure by a physician, podiatrist, or healthcare provider to provide the requested records within 15 days, or a healthcare facility within 30 days, of receipt of this request and authorization may constitute a violation of Section 2225.5 of the Medical Practice Act and may result in further action by the Board.
More rules for Form 07I-61
Attach a copy of any supporting documents you may have in your possession pertaining to your specific complaint; documents may include patient records, photographs, audio or video recordings, correspondence, billing statements, proof of payments, autopsy/toxicology report, police report, court documents, etc.
Common questions about Form 07I-61
Who signs it?
Sign and date the complaint form.
Where do I file it?
Enforcement Program, 2005 Evergreen Street, Suite 1200, Sacramento, CA 95815-5401, mbc.ca.gov.
When is this form not the right one?
The Board does not have jurisdiction over billing/fee disputes, general business practices (contracts, office policies, appointment times/duration, etc.) or personal conflicts, unless the behavior in question interferes with the safe delivery of health care. Please contact your insurance company or your physician's or other healthcare provider's office to resolve disputes outside of the Board's jurisdiction. The Board cannot award any kind of financial compensation.
Sources
[1] Form 07I-61 (Rev 07/26), Medical Board of California (the Official source link on this page).
