

CalHR 754 at a glance
What it is: CalHR 754 is the Certification of Health Care Provider for Employee's Serious Health Condition, State of California, for the Family and Medical Leave Act (FMLA) and the California Family Rights Act (CFRA).
Who signs: The Health Care Provider Signature verifies that the information provided is true and accurate.
What to bring and attach to CalHR 754
Attach a copy of the employee's job description and the essential job functions of the employee's position.
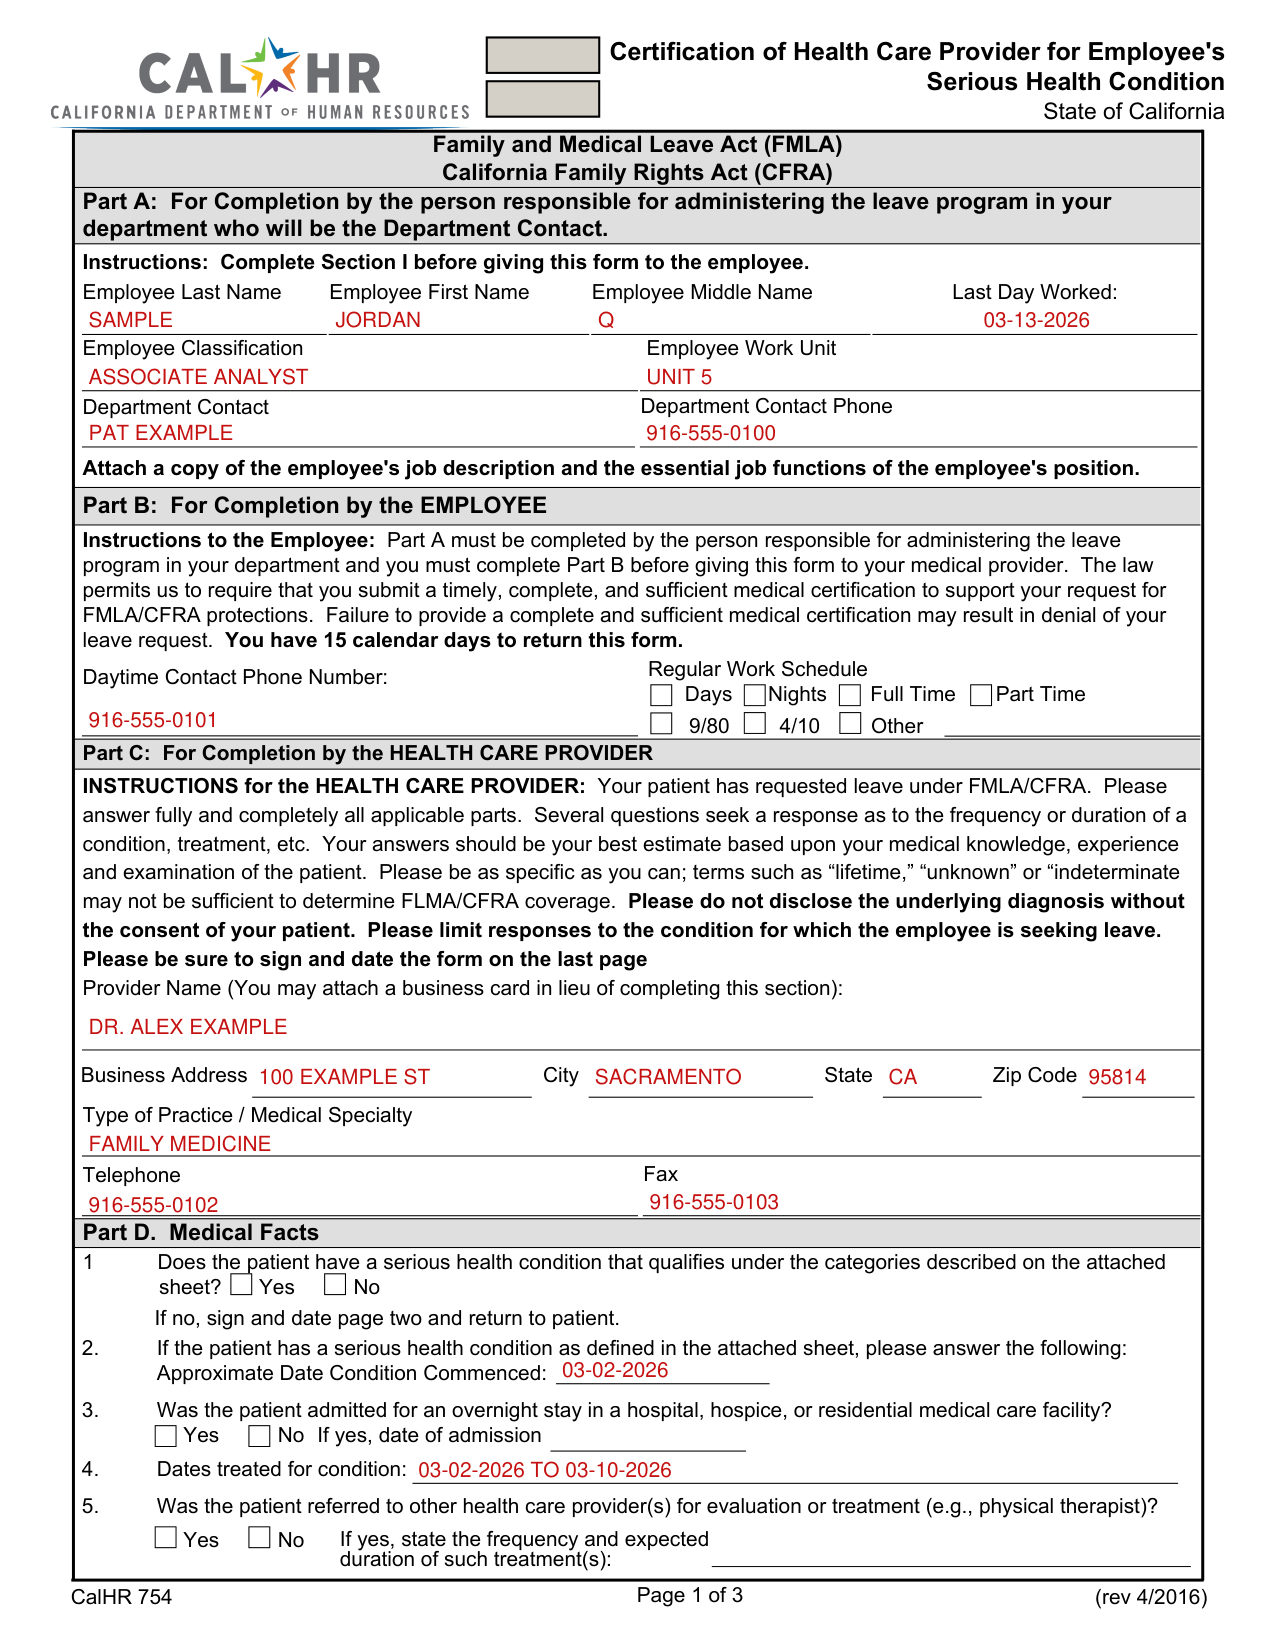
A filled-in CalHR 754 example: page one of CalHR 754
How to fill out CalHR 754, box by box
Part A: For Completion by the person responsible for administering the leave program

Part A: For Completion by the person responsible for administering the leave program in your department who will be the Department Contact. Complete Section I before giving this form to the employee. Enter Employee Last Name, Employee First Name, Employee Middle Name, Last Day Worked, Employee Classification, Employee Work Unit, Department Contact and Department Contact Phone.
Part B: For Completion by the EMPLOYEE

Part A must be completed by the person responsible for administering the leave program in your department and you must complete Part B before giving this form to your medical provider. You have 15 calendar days to return this form. Failure to provide a complete and sufficient medical certification may result in denial of your leave request.
Regular Work Schedule: Nights Days Part Time Full Time Other 4/10 9/80.
Part C: For Completion by the HEALTH CARE PROVIDER

Provider Name: you may attach a business card in lieu of completing this section. Do not disclose the underlying diagnosis without the consent of your patient. Limit responses to the condition for which the employee is seeking leave. Terms such as lifetime, unknown or indeterminate may not be sufficient to determine FLMA/CFRA coverage. Your answers should be your best estimate based upon your medical knowledge, experience and examination of the patient. Please be sure to sign and date the form on the last page.
Part D. Medical Facts

Part D. Medical Facts. Does the patient have a serious health condition that qualifies under the categories described on the attached sheet? If no, sign and date page two and return to patient.
If the patient has a serious health condition as defined in the attached sheet, please answer the following: Approximate Date Condition Commenced.
Was the patient admitted for an overnight stay in a hospital, hospice, or residential medical care facility? Yes or No. If yes, date of admission.
Dates treated for condition.
Was the patient referred to other health care provider(s) for evaluation or treatment (e.g., physical therapist)? No or Yes. If yes, state the frequency and expected duration of such treatment(s).
Job functions and modified duty
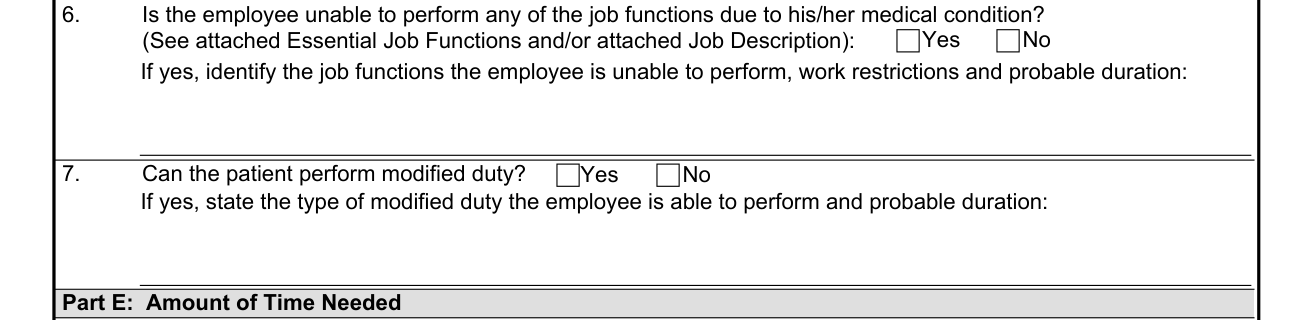
Is the employee unable to perform any of the job functions due to his/her medical condition? (See attached Essential Job Functions and/or attached Job Description) If yes, identify the job functions the employee is unable to perform, work restrictions and probable duration.
Can the patient perform modified duty? No or Yes. If yes, state the type of modified duty the employee is able to perform and probable duration.
Part E: Amount of Time Needed
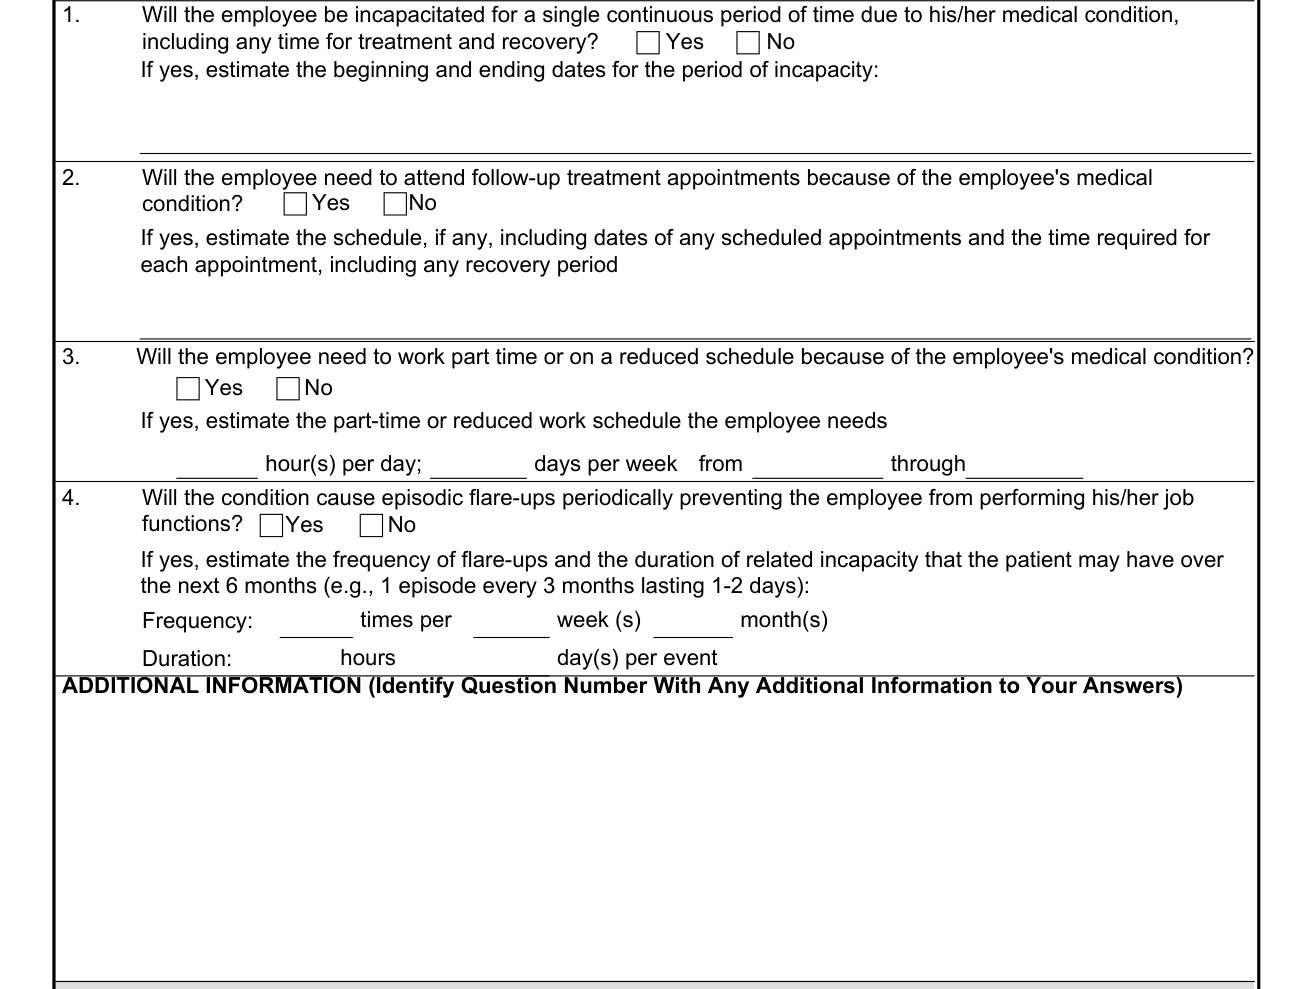
Part E: Amount of Time Needed. Will the employee be incapacitated for a single continuous period of time due to his/her medical condition, including any time for treatment and recovery? Yes or No. If yes, estimate the beginning and ending dates for the period of incapacity.
Will the employee need to attend follow-up treatment appointments because of the employee's medical condition? Yes or No. If yes, estimate the schedule, if any, including dates of any scheduled appointments and the time required for each appointment, including any recovery period.
Will the employee need to work part time or on a reduced schedule because of the employee's medical condition? Yes or No. If yes, estimate the part-time or reduced work schedule the employee needs: enter from, through, days per week and hour(s) per day.
Will the condition cause episodic flare-ups periodically preventing the employee from performing his/her job functions? Yes or No. If yes, estimate the frequency of flare-ups and the duration of related incapacity that the patient may have over the next 6 months (e.g., 1 episode every 3 months lasting 1-2 days). Frequency: times per month(s) or week(s). Duration: day(s) per event or hours.
Additional Information and Printed Name of Health Care Provider

Identify Question Number With Any Additional Information to Your Answers. Enter the Printed Name of Health Care Provider, sign on Health Care Provider Signature and enter the Date.
More rules for CalHR 754
It is mandatory to furnish all information requested on this form. Failure to provide the mandatory information may result in a delay in processing your request.
Sources
[1] CalHR 754 (rev 4/2016), Certification of Health Care Provider for Employee's Serious Health Condition, State of California (the Official source link on this page).