

SOC 450 at a glance
What it is: The Voluntary Services Certification is a form of the State of California Health and Human Services Agency, California Department of Social Services.
Who signs: The provider signs on the Provider Signature line and enters the Date. The Social Service Worker signs on the Social Service Worker Signature line and enters the Date.
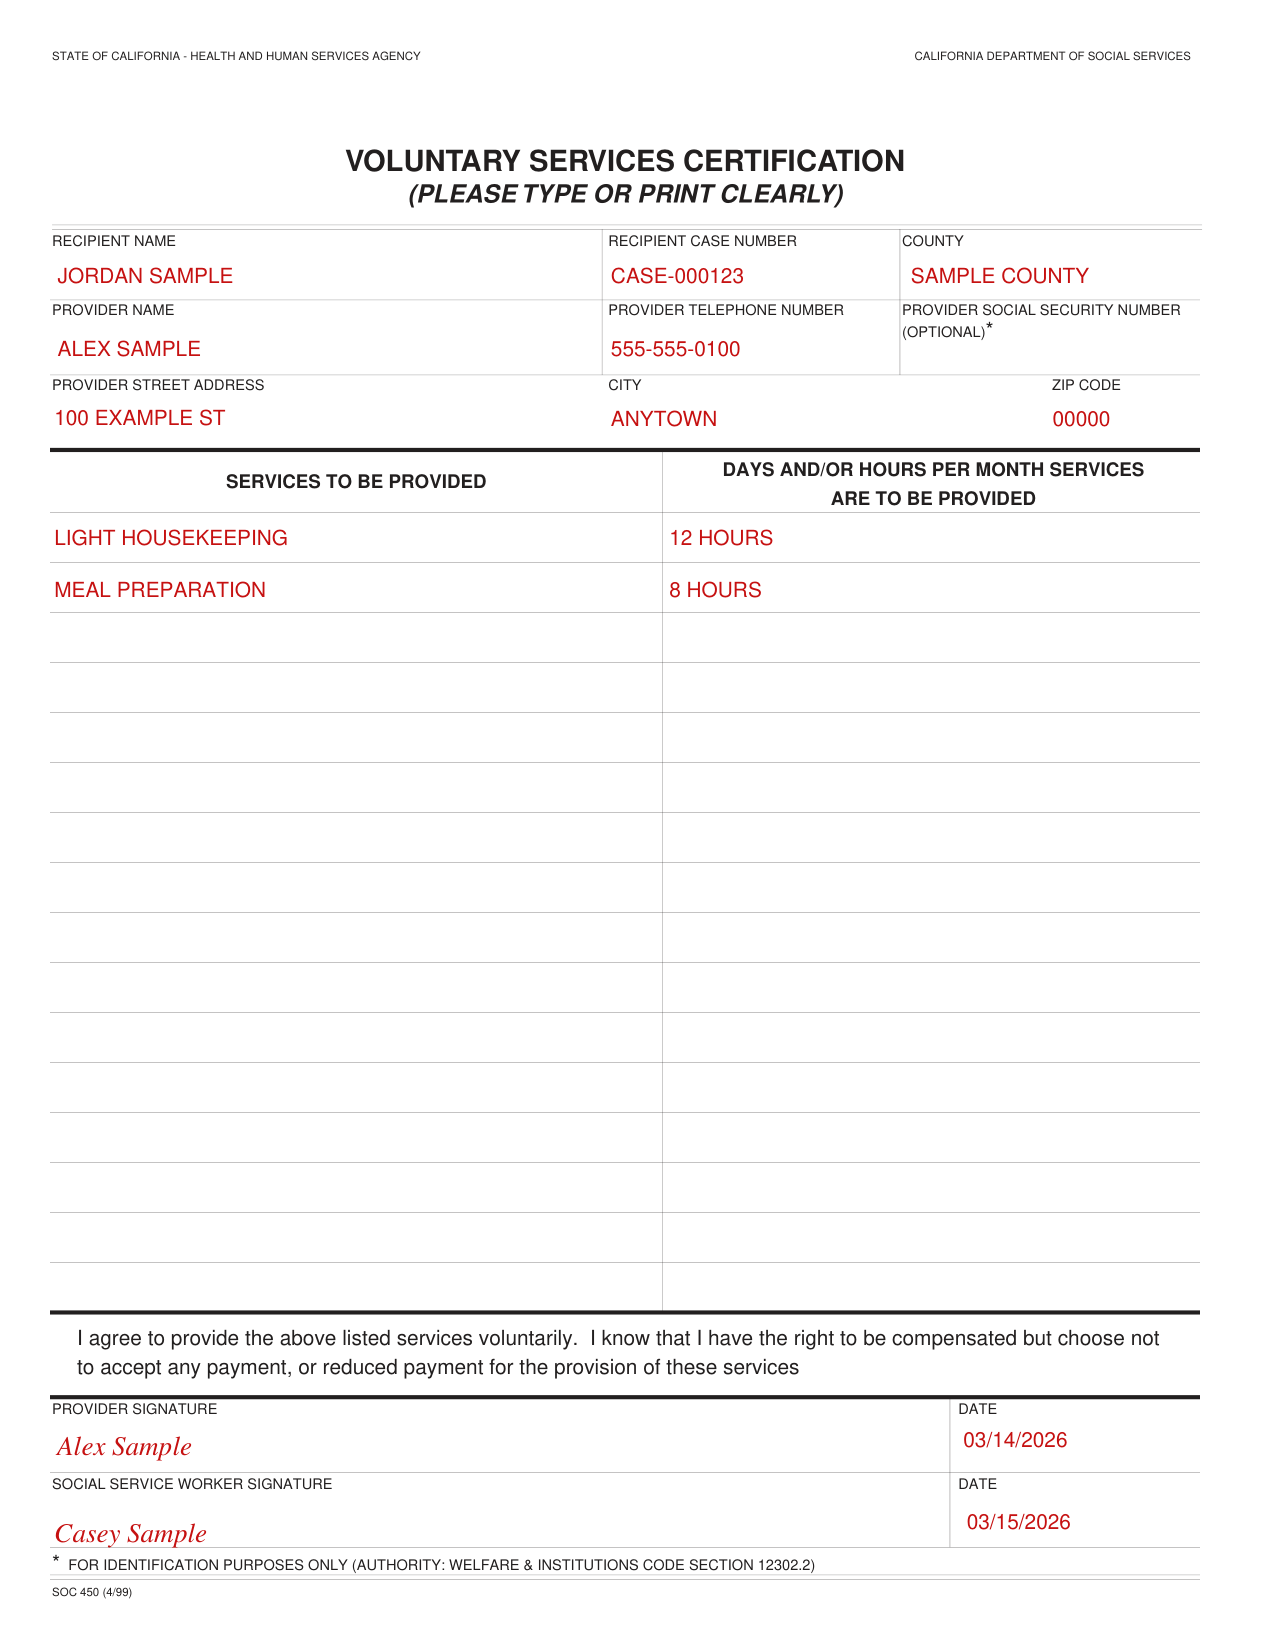
A filled-in SOC 450 example: a provider volunteers 20 hours a month
How to fill out SOC 450, box by box
Recipient Name, Recipient Case Number and County

Please type or print clearly.
Enter the Recipient Name, Recipient Case Number and County.
Provider Name, Provider Telephone Number and Provider Social Security Number

Enter the Provider Name and Provider Telephone Number.
The Provider Social Security Number is optional, for identification purposes only (authority: Welfare & Institutions Code Section 12302.2).
Provider Street Address, City and Zip Code

Enter the Provider Street Address, City and Zip Code.
Services to Be Provided and Days and/or Hours per Month
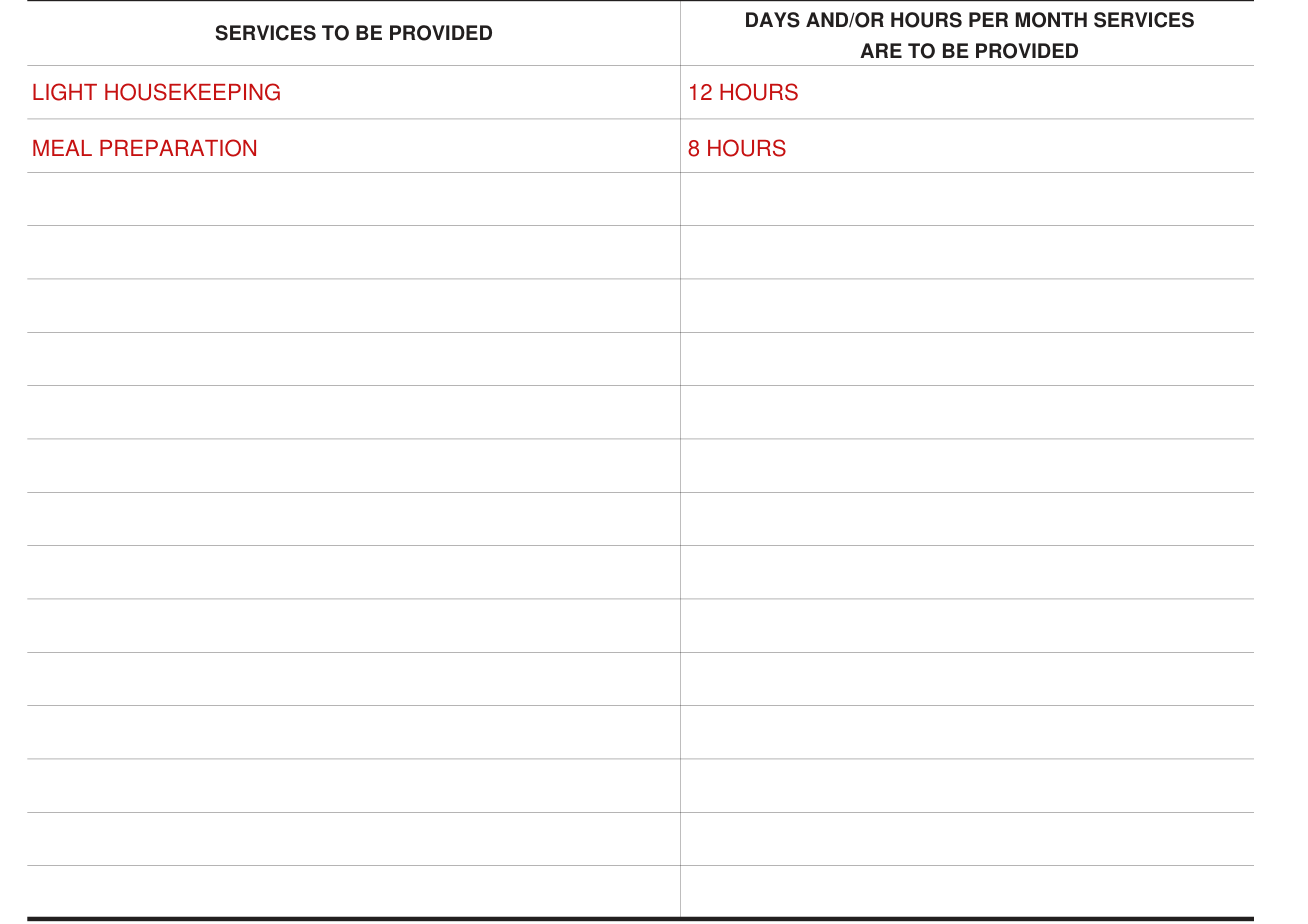
Under Services to be Provided, enter the services, and next to each, enter the Days and/or Hours per Month Services Are to Be Provided.
Provider Signature and Social Service Worker Signature

The provider agrees to provide the services listed under Services to Be Provided voluntarily and knows of the right to be compensated but chooses not to accept any payment, or reduced payment for the provision of these services.
The provider signs on the Provider Signature line and enters the Date.
The Social Service Worker signs on the Social Service Worker Signature line and enters the Date.
Sources
[1] Form SOC 450 (4/99), Voluntary Services Certification, California Department of Social Services (the Official source link on this page).