


California Form SOC 295 at a glance
What it is: SOC 295 is the Application for In-Home Supportive Services of the California Department of Social Services.
Who signs: Signature of Applicant and, only if applicable, Signature of Applicant's Representative.
A filled-in California Form SOC 295 example: Maria Sample applies for IHSS

How to fill out California Form SOC 295, box by box
Date of Application and Case Number

Enter the Date of Application and the Case Number (if known).
Section 1 - Personal Information
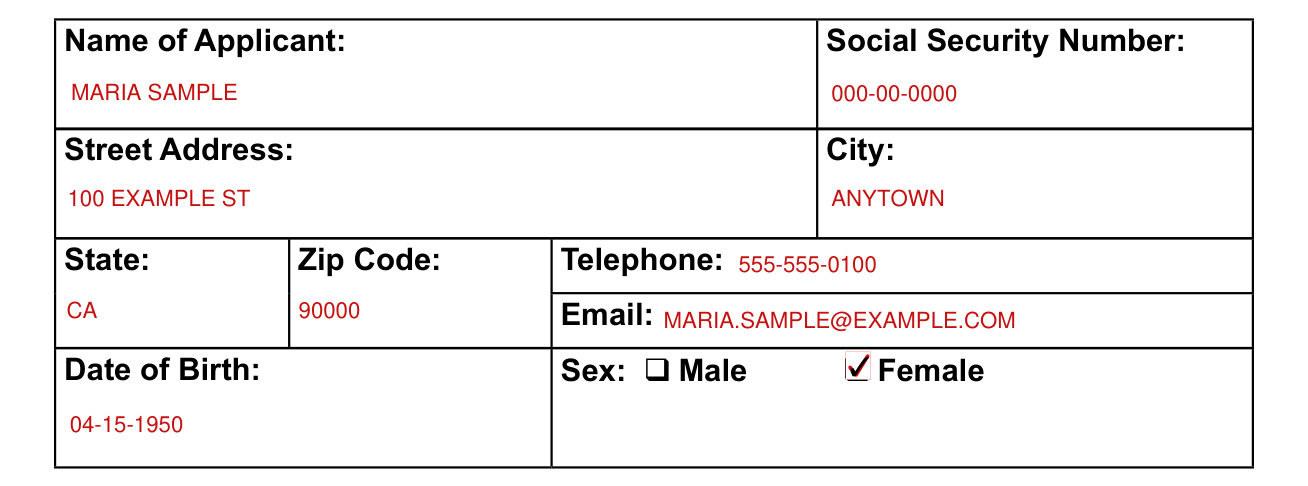
Retain your copy of your completed application. Regarding your Social Security Number, it is mandatory that you provide your Social Security Number(s) as required in 42 USC 405, or that you apply for a Social Security Number(s) with the Social Security Administration. This information will be used in eligibility determination and coordinating information with other public agencies.
Enter the Name of Applicant and the Social Security Number.
Enter the Street Address, City, State, Zip Code, Telephone and Email.
Enter the Date of Birth, then check Male or Female for Sex.
Section 2 - Sexual Orientation and Gender Identity (Optional)

Providing responses in Section 2 is optional and confidential. Any information you provide in this section will not be used in your eligibility determination.
Check the box that best describes your current gender identity: Female, Male, Transgender: male to female, Transgender: female to male, Non-Binary (neither male nor female), Another gender identity or Decline to state.
If your situation is different
Sex on your original birth certificate and sexual orientation
Check Female or Male for What sex was listed on your original birth certificate?
How do you describe your sexual orientation? Select one answer: Straight/heterosexual, Gay or lesbian, Bisexual, Queer, Another sexual orientation, Unknown or Decline to state.
Section 3 - Veteran Information
Check Yes or No for Are you a Veteran?
Check Yes or No for Are you a Spouse/Child of a Veteran? If YES, give Veteran name and Claim Number.
Section 4 - SSI/SSP Information
Check Yes or No for Do you receive SSI/SSP benefits? If yes, check your type of living arrangement: Independent Living, Board and Care or Home of Another. Enter the Services being requested.
Section 5 - Past IHSS Information
Check Yes or No for Have you received In-Home Supportive Services (IHSS) in the past? If Yes, enter the Date and county where service was last received, the Total Monthly Hours and the Name Used (if different).
Section 6 - Household Information
Under List Household Members, enter the Name of Spouse with the Birthdate and Social Security Number.
For each other household member, enter the Name, check Parent, Child, Other Relative or Non-Relative, and enter the Birthdate and Social Security Number.
Section 7 - Ethnic and Language Information
The law requires that information on ethnic origin and primary language be collected. If you do not complete this section, social service staff will make a determination. The information will not affect your eligibility for service.
For A. My Ethnic Origin is, please choose one; see Page 8 for a list of Ethnicities and Codes.
For B1. What language do you prefer to read? please choose one. For B2. What language do you prefer to speak? please choose one from the list of Languages and Codes on Page 8.
Ethnic Codes: A. White. B. Hispanic. C. Black. D. Other Asian or Pacific Islander. E. American Indian or Alaskan Native. F. Filipino. G. Chinese. H. Cambodian. I. Japanese. J. Korean. K. Samoan. L. Asian Indian. M. Hawaiian. N. Guamanian. O. Laotian. P. Vietnamese. Q. Other. R. Mixed Ethnicity.
Language Codes: 1. American Sign Language (AMISLAN or ASL). 2. Spanish - NOA will be issued in Spanish. 3. Cantonese. 4. Japanese. 5. Korean. 6. Tagalog. 7. Other non-English. 8. English. 9. Spanish - NOA will be issued in English. 10. Other Sign Language. 11. Mandarin. 12. Other Chinese Languages. 13. Cambodian. 14. Armenian. 15. Ilacano. 16. Mien. 17. Hmong. 18. Lao. 19. Turkish. 20. Hebrew. 21. French. 22. Polish. 23. Russian. 24. Portuguese. 25. Italian. 26. Arabic. 27. Samoan. 28. Thai. 29. Farsi. 30. Vietnamese.
Section 8 - Communication Accommodations
To accommodate blind or visually-impaired applicants, IHSS information is available in alternative formats. Please indicate which format you would prefer, if applicable. Providing information in this section will not affect your eligibility for services.
Check Yes or No for I am Blind and Yes or No for I am Visually Impaired.
If yes, please choose one of the following for each of the three types of Department of Social Services (DSS) documents listed. For Notices of Action and for IHSS Required forms: No accommodation is needed, Braille Documents (I am Blind), 18 point font documents (I am Visually Impaired), Audio CD, Data CD or County Support. If County Support, describe requested support.
For Timesheets: No accommodation is needed, Telephonic System (4 Digit RAN: ), 18 point font documents (I am Visually Impaired), County Support or Electronic Timesheet System (ETS). Applicants and providers must first register at https://www.etimesheets.ihss.ca.gov. For County Support, describe requested support (including blind-only services if you are Visually Impaired).
Section 9 - Affirmation
You affirm that the information is true to the best of your knowledge and belief. You agree to cooperate fully if verification of the statements is required in the future.
As the employer of your IHSS provider(s) you are responsible for: 1. Hiring, training, supervising, scheduling and, when necessary, firing your provider(s). 2. Ensuring the total hours reported by all providers who work for you do not exceed your IHSS authorized hours each month. 3. Referring any individual you want to hire to the County IHSS office to complete the provider eligibility process. 4. Notifying the County IHSS office within 10 days when you hire or fire a provider.
Payment for services by the IHSS program
1. In order for any individual to be paid by the IHSS program, they must be approved as an IHSS eligible provider.
2. If you choose to have an individual work for you who has not yet been approved as an eligible IHSS provider, you will be responsible for paying him/her if he/she is not approved.
3. The IHSS program will not pay for any services provided to you until your application for services is approved and then will only pay for those services that are authorized for you to receive by the IHSS Program.
4. You will be responsible for paying for any services you receive that are not included in your IHSS authorization.
5. You will be responsible for paying your Share-of-Cost (SOC) and informing your individual provider(s) of that SOC.
Visits to your home
As a part of your eligibility for IHSS, to promote program integrity and quality assurance, you may be subject to (un)announced visits to your home and you or your provider(s) may receive letters identifying program requirement concerns from the State Department of Health Care Services (DHCS), California Department of Social Services (CDSS) and/or the County in which you receive services.
Medi-Cal fraud
If it is found that IHSS services are not required or not being properly provided, you and/or your provider may be subject to a Medi-Cal fraud investigation.
If fraud is substantiated, you and/or your provider will be prosecuted for Medi-Cal fraud.
To report suspected fraud or abuse in the provision or receipt of IHSS services, please call the fraud hotline at 1-800-822-6222 or email at stopmedicalfraud@dhcs.ca.gov.
Section 10 - Signature(s)
Sign the Signature of Applicant line and enter the Date.
Sign the Signature of Applicant's Representative (only if applicable) line and enter the Date.
Enter the Representative's Relationship to Applicant (only if applicable), the Representative's Telephone Number (only if applicable) and the Representative's Address (only if applicable).
Common questions about California Form SOC 295
What is SOC 295 form?
SOC 295 is the Application for In-Home Supportive Services of the California Department of Social Services. All sections of this form must be completed. Information provided is subject to verification.
Sources
[1] SOC 295 (9/18), Application for In-Home Supportive Services, California Department of Social Services (the Official source link on this page).