

California Participating Practitioner Application Addendum B at a glance
What it is: This California Participating Practitioner Application Addendum B Professional Liability Action Explained is submitted to this Healthcare Organization.
Who signs: Sign on the APPLICANT SIGNATURE line (Stamp is Not Acceptable), and enter the PRINTED NAME and the DATE.
A filled-in California Participating Practitioner Application Addendum B example: a practitioner reports one settled lawsuit

How to fill out California Participating Practitioner Application Addendum B, box by box
Each lawsuit or arbitration, or no claims to report

Please complete this form for each pending, settled or otherwise conclude professional liability lawsuit or arbitration filed and served against you, in which you were named a party in the past seven (7) years, whether the lawsuit or arbitration is pending, settled or otherwise concluded, and whether or not any payment was made on your behalf by any insurer, company, hospital or other entity. All questions must be answered completely in order to avoid delay in expediting your application. If there is more than one professional liability lawsuit or arbitration action, please photocopy this Addendum B prior to completing, and complete a separate form for each lawsuit.
Check here if there are no pending/settled claims to report, and sign to attest.
I. Practioner Identifying Information

Under I. Practioner Identifying Information, enter your Last Name, First Name and Middle.
II. Case Information
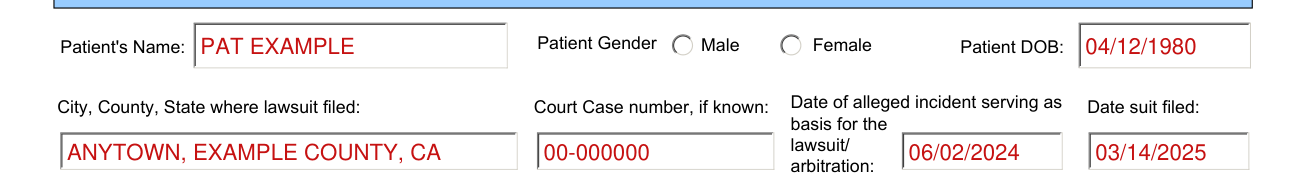
Enter the Patient's Name, mark the Patient Gender Male or Female, and enter the Patient DOB.
Enter the City, County, State where the lawsuit was filed, the Court Case number, if known, the Date suit was filed and the Date of the alleged incident serving as basis for the lawsuit/ arbitration.
Location of incident and Relationship to patient
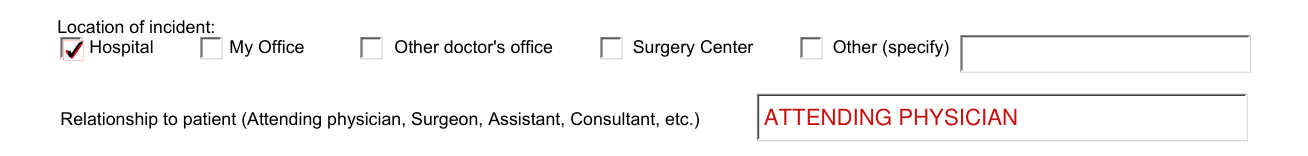
For the Location of incident, mark Hospital, My Office, Other doctor's office, Surgery Center or Other (specify).
Enter your Relationship to patient (Attending physician, Surgeon, Assistant, Consultant, etc.).
Allegation and insurance coverage
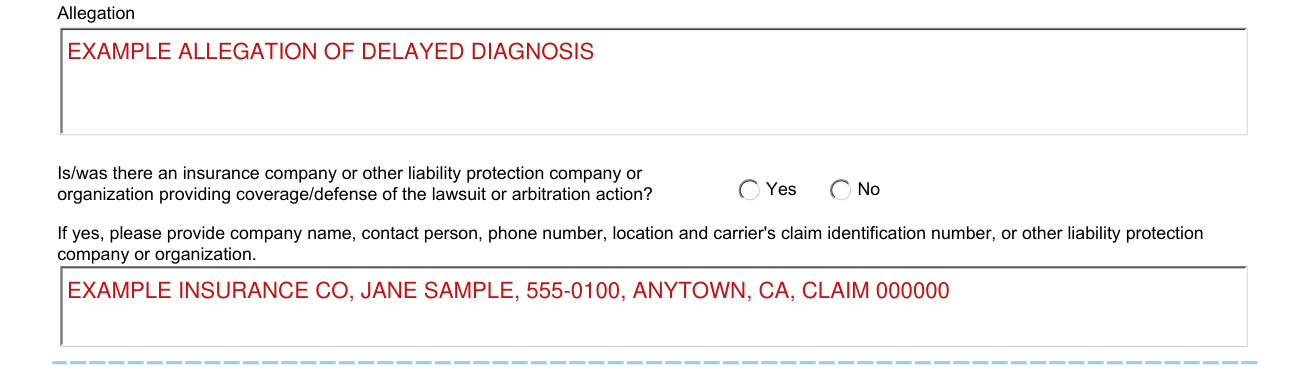
Enter the Allegation in its box. Mark Yes or No: Is/was there an insurance company or other liability protection company or organization providing coverage/defense of the lawsuit or arbitration action? If yes, provide company name, contact person, phone number, location and carrier's claim identification number, or other liability protection company or organization.
Name, Fax Number and Telephone Number

If you would like your attorney contacted, enter the attorney(s) name(s) and phone number(s) in Name, Fax Number and Telephone Number. Please fax this document to your attorney, as this will serve as your authorization.
III. Status of Lawsuit/Arbitration (check one)

Check one under III. Status of Lawsuit/Arbitration: Lawsuit/arbitration still ongoing, unresolved; Judgment rendered and payment was made on my behalf, with the Amount paid on my behalf; Judgment rendered and I was found not liable; Lawsuit/arbitration settled and payment made on my behalf, with the Amount paid on my behalf; or Lawsuit/arbitration settled/dismissed, no judgment rendered, no payment made on my behalf.
SUMMARY, certification and APPLICANT SIGNATURE
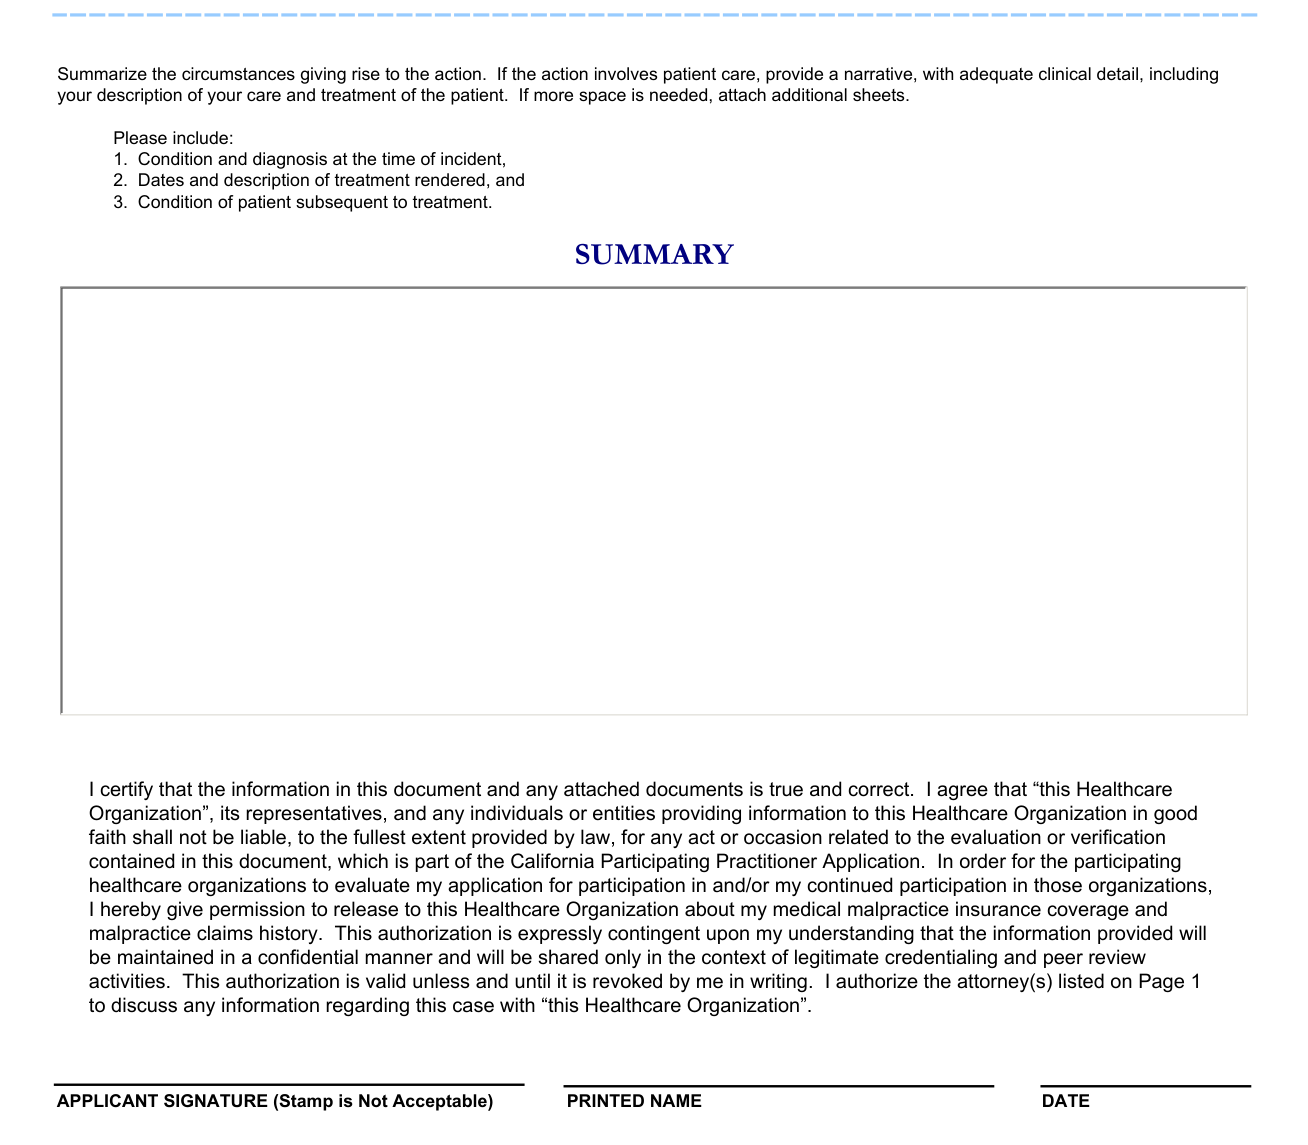
Summarize the circumstances giving rise to the action.
If the action involves patient care, provide a narrative, with adequate clinical detail, including your description of your care and treatment of the patient.
If more space is needed, attach additional sheets. Please include: 1. Condition and diagnosis at the time of incident, 2. Dates and description of treatment rendered, and 3. Condition of patient subsequent to treatment.
By signing you certify that the information in this document and any attached documents is true and correct.
By signing you give permission to release to this Healthcare Organization your medical malpractice insurance coverage and malpractice claims history, so that the participating healthcare organizations can evaluate your application for participation and/or your continued participation in those organizations.
This authorization is valid unless and until you revoke it in writing.
By signing you also authorize the attorney(s) listed on Page 1 to discuss any information regarding this case with “this Healthcare Organization”.
Sign on the APPLICANT SIGNATURE line (Stamp is Not Acceptable), and enter the PRINTED NAME and the DATE.
Sources
[1] California Participating Practitioner Application, Addendum B Professional Liability Action Explained (Version 1.2012) (the Official source link on this page).