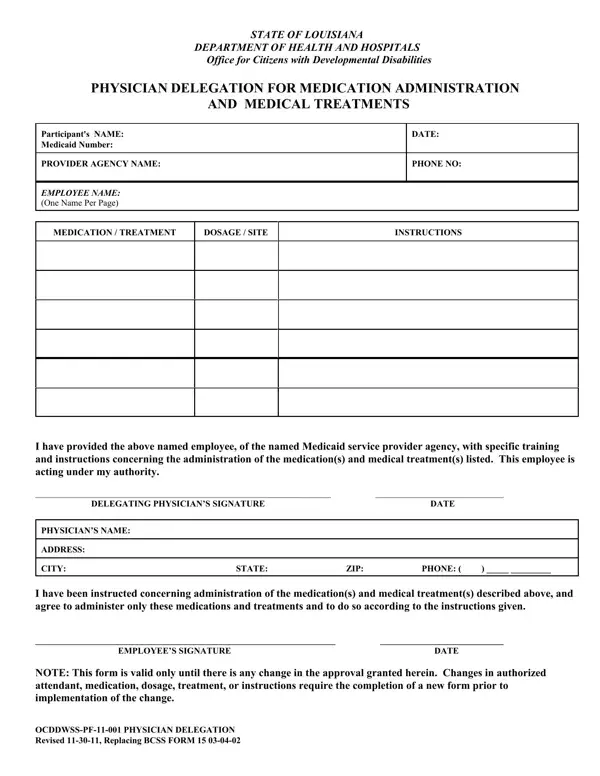
Physician Delegation Form PDF Details

In the realm of healthcare and medicine, the dynamics of treatment extend beyond hospital rooms and into various settings where constant medical oversight is not always feasible. The Physician Delegation Form, as issued by the State of Louisiana's Department of Health and Hospitals, Office for Citizens with Developmental Disabilities, bridges this gap by authorizing non-physician personnel to administer medication and carry out medical treatments under a physician's supervision. This document not only specifies the participant's name and Medicaid number but also names the provider agency and its employee designated to perform these tasks. It meticulously outlines the type, dosage, and site of medication or treatment, ensuring that delegated individuals are directly instructed by the delegating physician. With spaces for both the physician's and the employee's signatures, it underscores a mutual agreement and understanding of the responsibilities handed over. Significantly, this form is contingent on the precision of its contents—any change in treatment, medication, or personnel necessitates a new form, emphasizing the form's pivotal role in safeguarding patient care through clear, regulated delegation.

QuestionAnswer
Form NamePhysician Delegation Form
Form Length1 page
Fillable?Yes
Fillable fields36
Avg. time to fill out15 sec
Other namesocddwss pf 11 001 physician delegation, nurse delegation form for colostomy louisiana, louisiana physician delegation, louisiana delegation administration

How to Fill Out Physician Delegation for Medication Administration and Medical Treatments (OCDDWSS-PF-11-001)

Physician Delegation for Medication Administration and Medical Treatments (OCDDWSS-PF-11-001) at a glance

What it is: State of Louisiana Department of Health and Hospitals, Office for Citizens with Developmental Disabilities: Physician Delegation for Medication Administration and Medical Treatments.

Who signs: The delegating physician signs in DELEGATING PHYSICIAN'S SIGNATURE and enters the DATE. The employee signs in EMPLOYEE'S SIGNATURE and enters the DATE.

A filled-in Physician Delegation for Medication Administration and Medical Treatments (OCDDWSS-PF-11-001) example: a physician delegates two medications
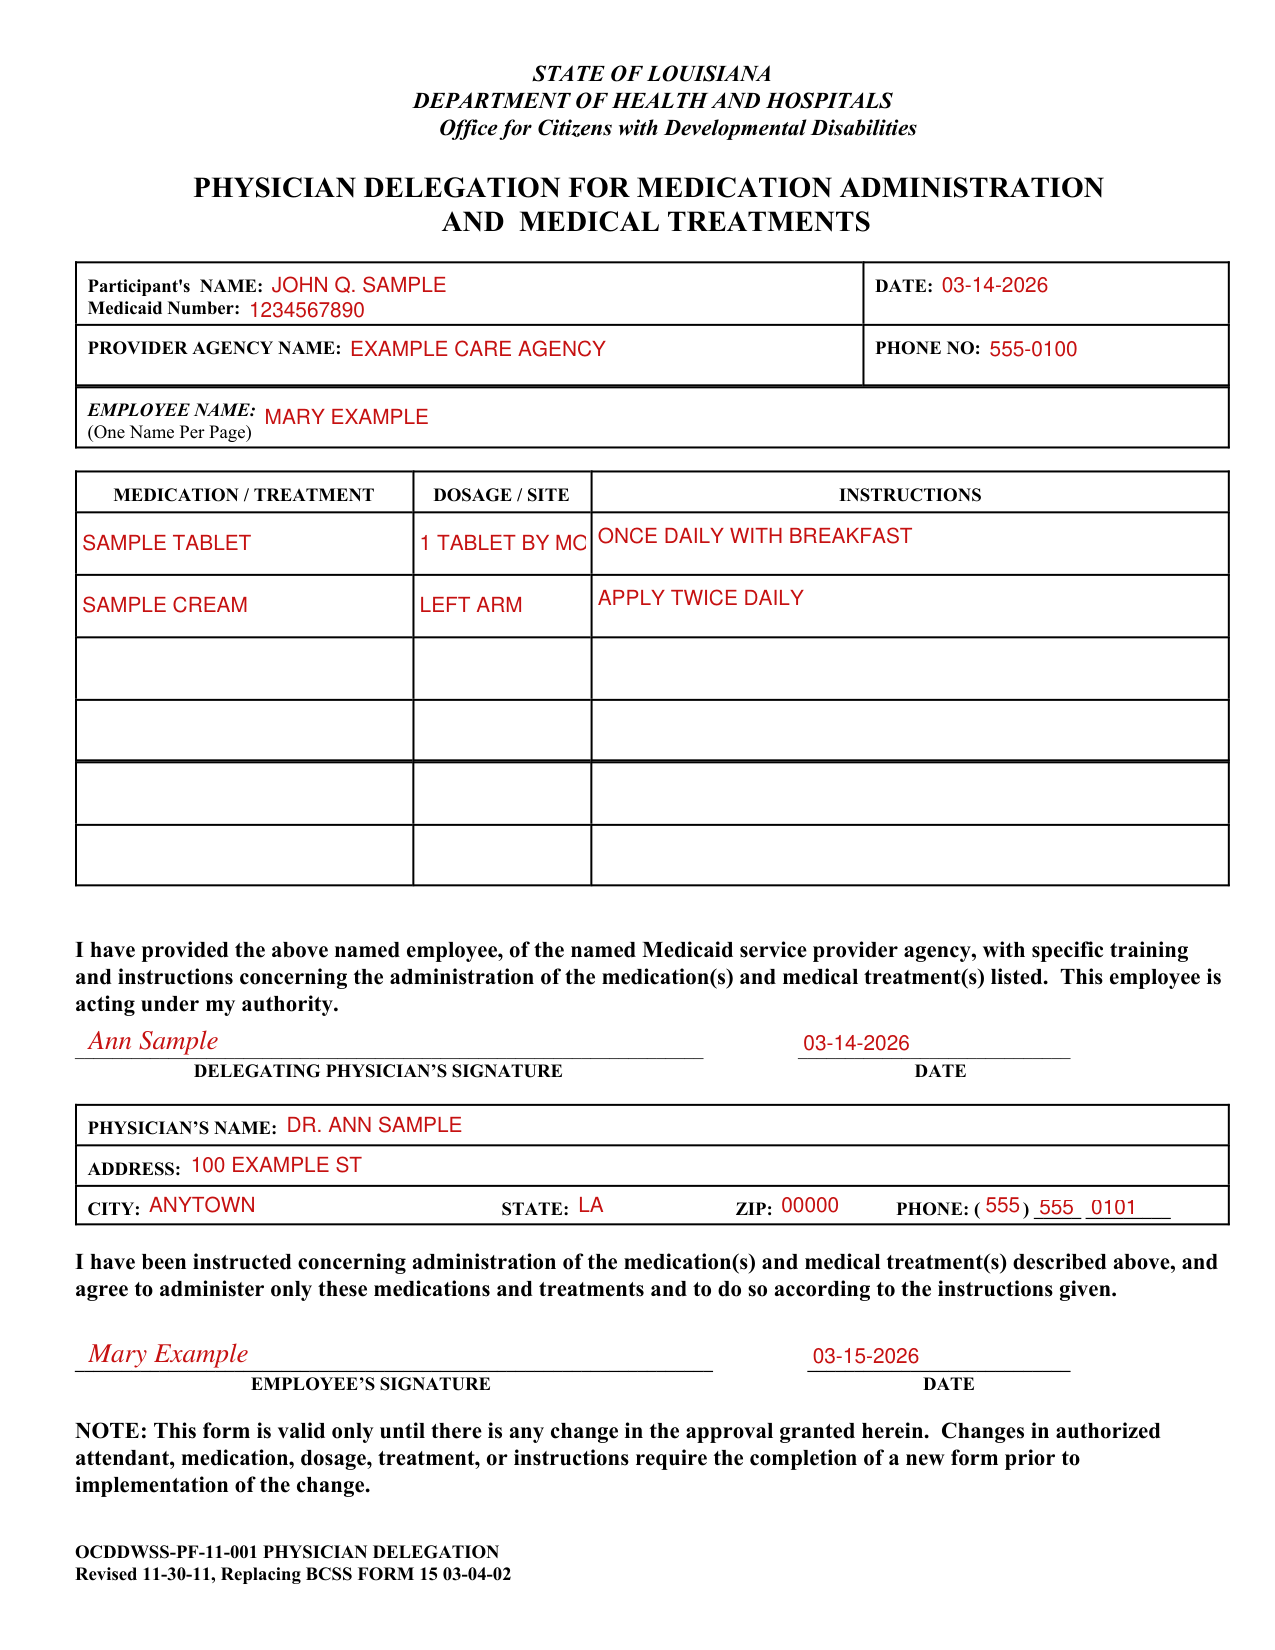
Physician Delegation for Medication Administration and Medical Treatments (OCDDWSS-PF-11-001) example filled out, example: a physician delegates two medications
Dr. Ann Sample completes the physician delegation form for one employee. Two medications are listed, so rows 3 to 6 of the medication and treatment list stay empty. The picture shows the filled page, and none of its entries is real.

How to fill out Physician Delegation for Medication Administration and Medical Treatments (OCDDWSS-PF-11-001), box by box

Participant, provider agency and employee

Physician Delegation for Medication Administration and Medical Treatments (OCDDWSS-PF-11-001) example filled out, participant, provider agency and employee

Enter the Participant's NAME, the Medicaid Number and the DATE.

Enter the PROVIDER AGENCY NAME and the PHONE NO.

Enter the EMPLOYEE NAME (One Name Per Page).

Medication and treatment list
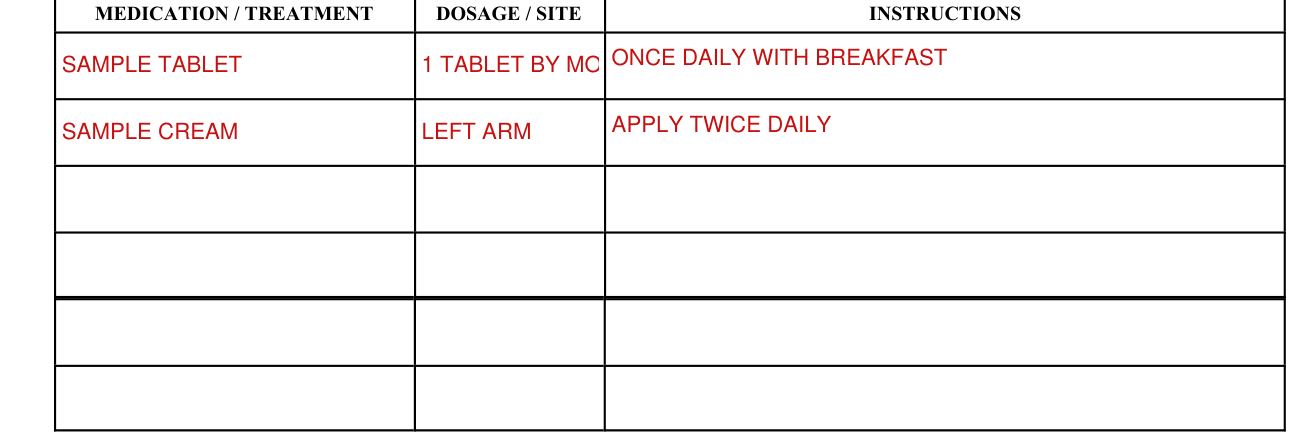
Physician Delegation for Medication Administration and Medical Treatments (OCDDWSS-PF-11-001) example filled out, medication and treatment list

Under MEDICATION / TREATMENT, DOSAGE / SITE and INSTRUCTIONS, list each medication or treatment.

Delegating physician
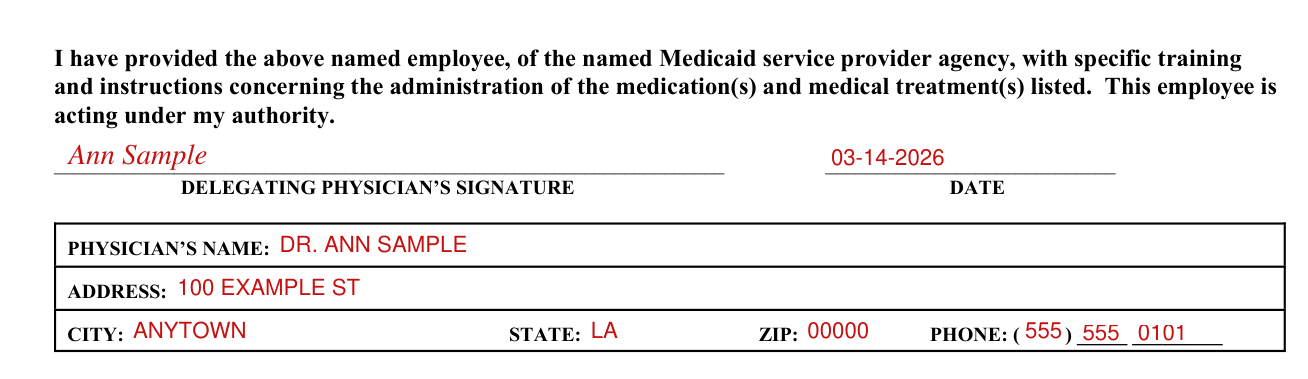
Physician Delegation for Medication Administration and Medical Treatments (OCDDWSS-PF-11-001) example filled out, delegating physician

I have provided the named employee, of the named Medicaid service provider agency, with specific training and instructions concerning the administration of the medication(s) and medical treatment(s) listed. This employee is acting under my authority.

The delegating physician signs in DELEGATING PHYSICIAN'S SIGNATURE and enters the DATE.

Enter the PHYSICIAN'S NAME, the ADDRESS, and the CITY, STATE, ZIP and PHONE.

Employee

Physician Delegation for Medication Administration and Medical Treatments (OCDDWSS-PF-11-001) example filled out, employee

I have been instructed concerning administration of the medication(s) and medical treatment(s) described, and agree to administer only these medications and treatments and to do so according to the instructions given.

The employee signs in EMPLOYEE'S SIGNATURE and enters the DATE.

More rules for Physician Delegation for Medication Administration and Medical Treatments (OCDDWSS-PF-11-001)

This form is valid only until there is any change in the approval granted herein. Changes in authorized attendant, medication, dosage, treatment, or instructions require the completion of a new form prior to implementation of the change.

Sources

[1] Form OCDDWSS-PF-11-001, Physician Delegation, State of Louisiana Department of Health and Hospitals (the Official source link on this page).