

CAPF 160 at a glance
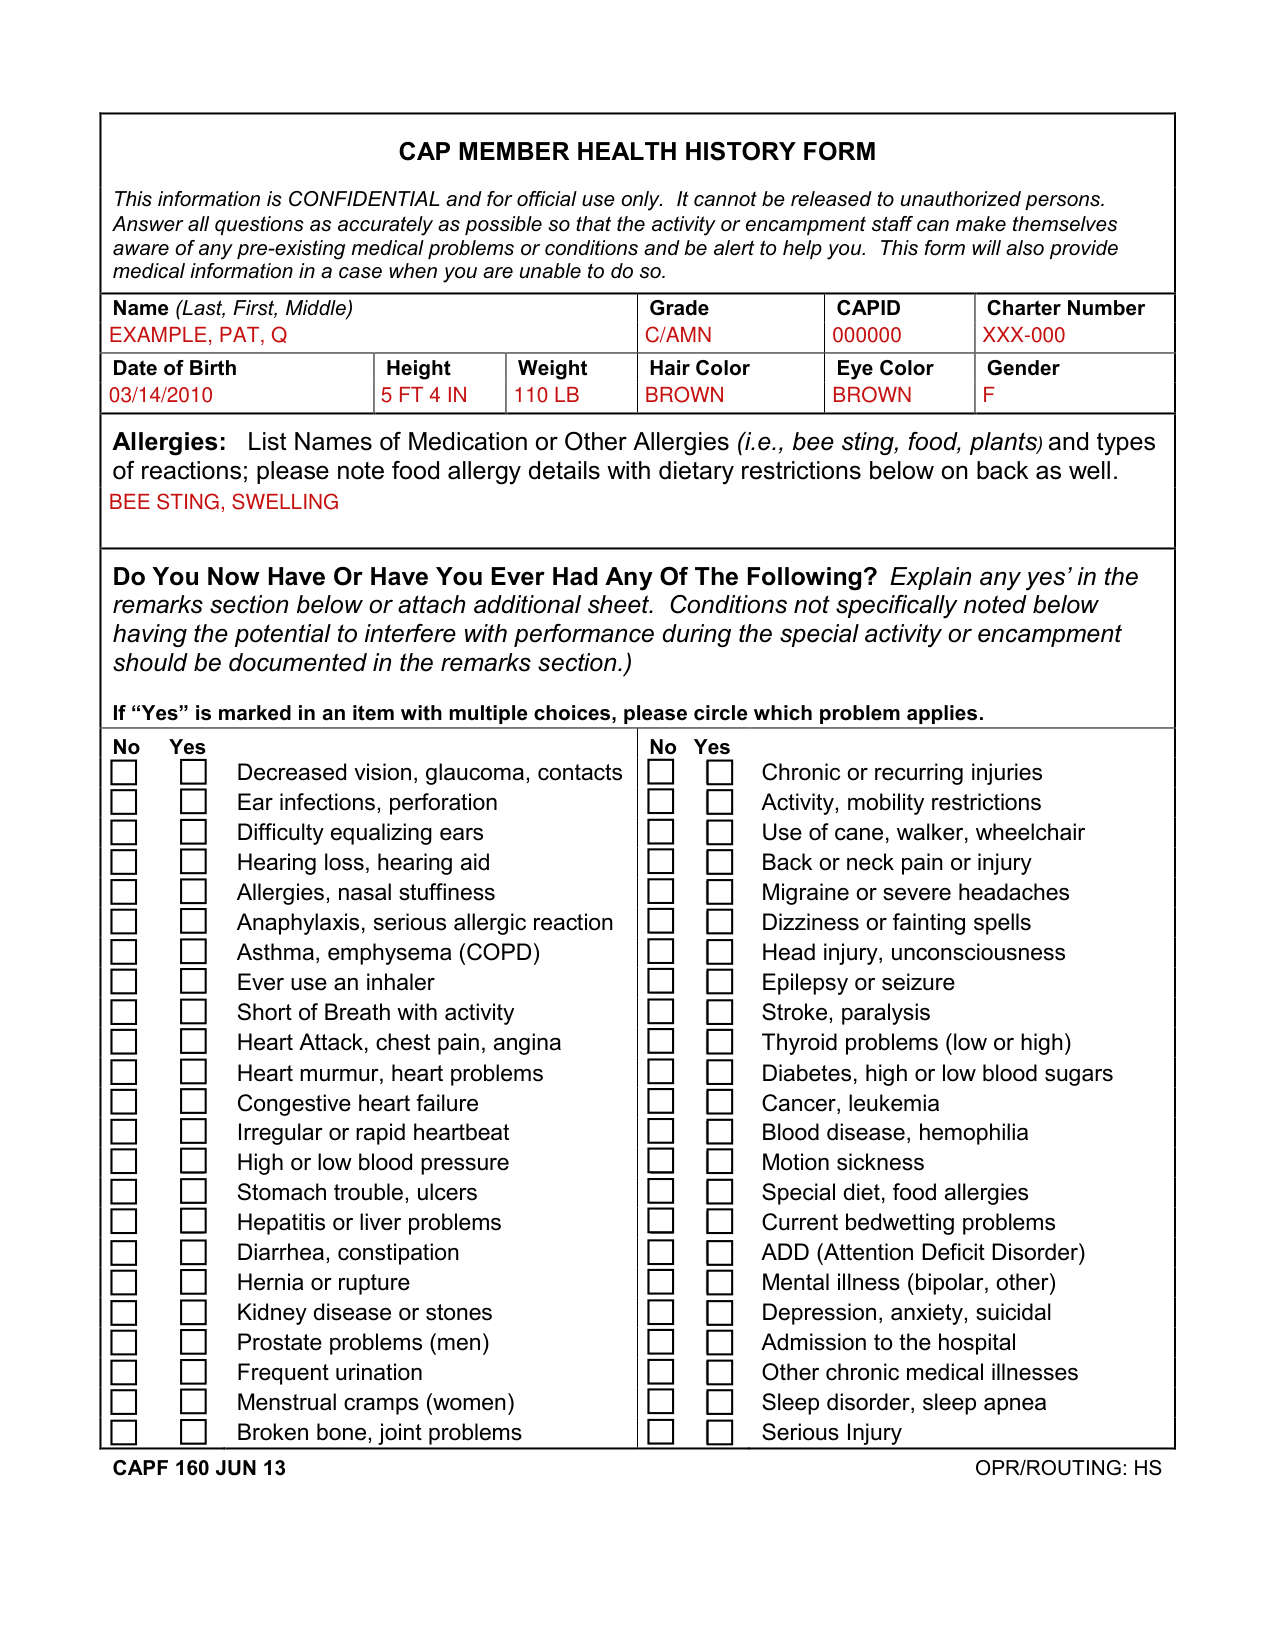
What it is: CAPF 160 JUN 13 is the CAP MEMBER HEALTH HISTORY FORM.
Who signs: Under Consent for Minor Cadet Participation, Medications, Treatment, the parent or guardian signs on the SIGNATURE OF PARENT/GUARDIAN line and fills in the DATE.
A filled-in CAPF 160 example: a cadet lists asthma and one allergy
How to fill out CAPF 160, box by box
Name, Grade, CAPID, Charter Number and Date of Birth
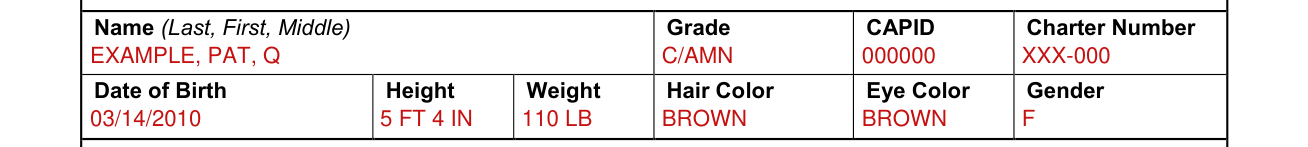
Enter Name (Last, First, Middle), Grade, CAPID, Charter Number, Date of Birth, Height, Weight, Hair Color, Eye Color and Gender.
Allergies

“Allergies: List Names of Medication or Other Allergies (i.e., bee sting, food, plants) and types of reactions; please note food allergy details with dietary restrictions below on back as well.”
Do You Now Have Or Have You Ever Had Any Of The Following?
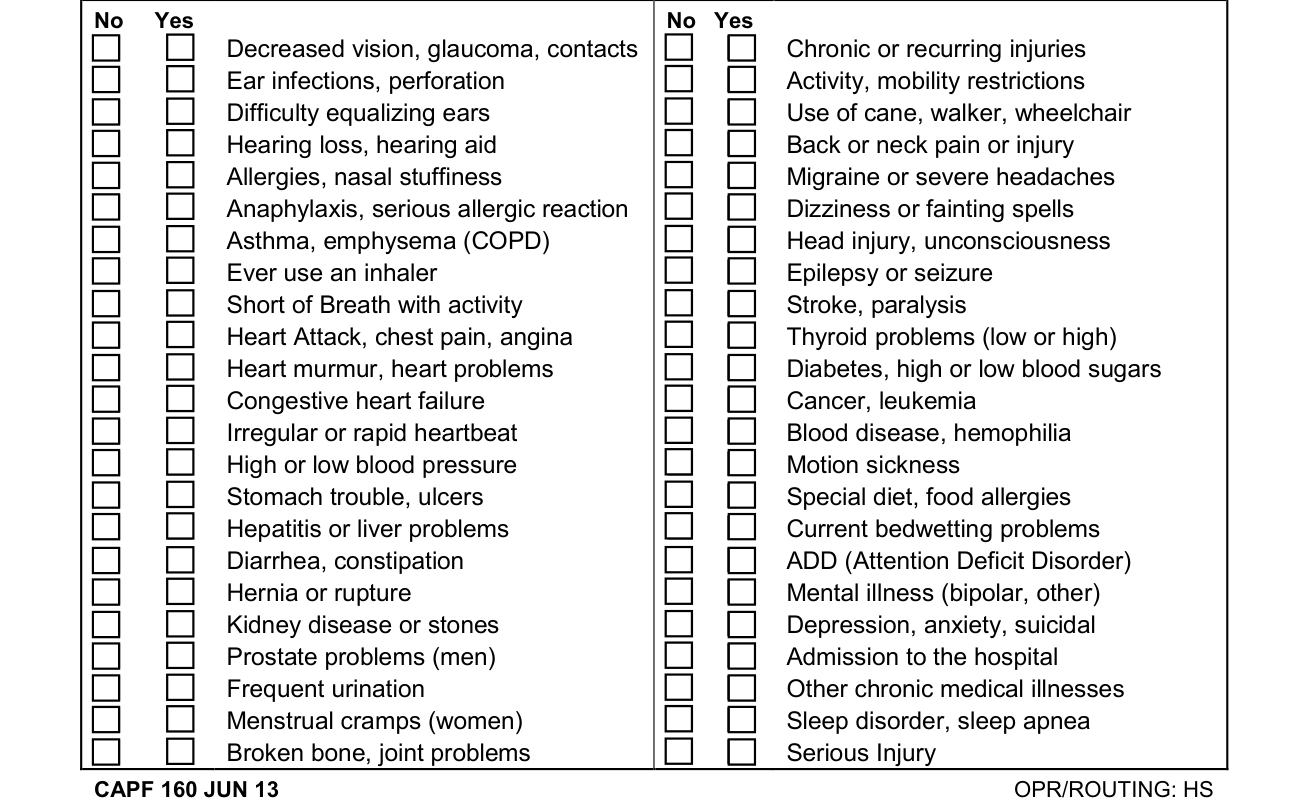
Do You Now Have Or Have You Ever Had Any Of The Following? Explain any yes' in the remarks section or attach additional sheet. Conditions not specifically noted having the potential to interfere with performance during the special activity or encampment should be documented in the remarks section. If “Yes” is marked in an item with multiple choices, please circle which problem applies.
Mark No or Yes.
Dietary Restrictions or Limitations

Under Dietary Restrictions or Limitations, list any dietary restrictions like food allergies, diabetes, gluten-free, vegetarian diets, etc.
Past Surgical History

Under Past Surgical History, list all surgeries including tonsils, ear tubes, appendix, gall bladder, hernia, hysterectomy, heart, heart catheterization, bone and joint and all other surgeries.
Tetanus Booster, Hepatitis Vaccine and the other vaccines

For Tetanus Booster, Hepatitis Vaccine, Pneumonia Vaccine, Varicella Immunization/chickenpox and Influenza Vaccine, fill in Date: or mark No.
Medication Information
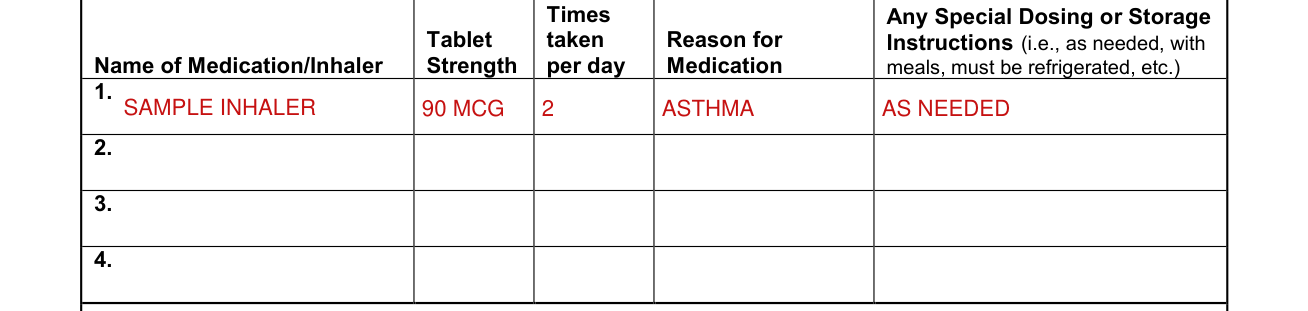
Under Medication Information, include supplements, over-the-counter medicines, herbals, creams, etc., or write “None”.
On each line, 1., 2., 3. and 4., enter the Name of Medication/Inhaler, Tablet Strength, Times taken per day, Reason for Medication and any Special Dosing or Storage Instructions (i.e., as needed, with meals, must be refrigerated, etc.).
Social History and Remarks
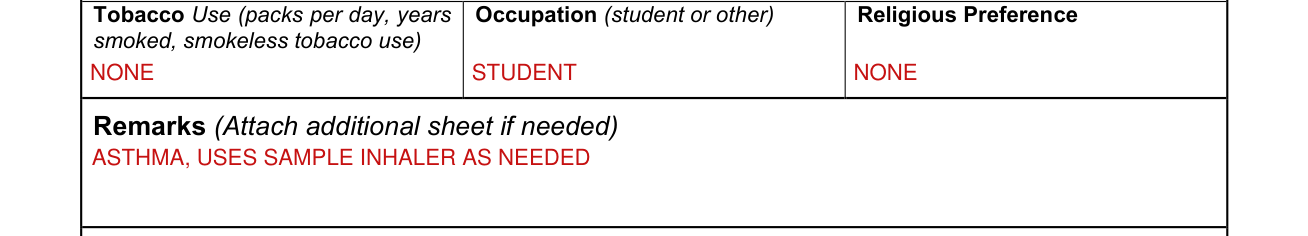
Under Social History, enter Tobacco Use (packs per day, years smoked, smokeless tobacco use), Occupation (student or other) and Religious Preference.
Write in Remarks (Attach additional sheet if needed).
Consent for Minor Cadet Participation, Medications, Treatment

Under Consent for Minor Cadet Participation, Medications, Treatment: I give permission for full participation in CAP programs, subject to any limitations noted herein.
My signature evidences my consent for my child/ward to possess and self-administer the prescription medications listed in Medication Information (Cross out if permission is denied). I understand that there are legal limitations imposed on CAP senior members with regard to the involuntary administration of medications to my child/ward.
In case of emergency, I understand every effort will be made to contact me. In the event I cannot be reached, I hereby give my permission to the licensed health-care practitioner selected by the adult leader in charge to secure proper treatment, including hospitalization, anesthesia, surgery, or injections of medication for my child.
Medical providers are authorized to disclose to the adult in charge exam/test results and treatment provided.
More rules for CAPF 160
This information is CONFIDENTIAL and for official use only. It cannot be released to unauthorized persons. Answer all questions as accurately as possible so that the activity or encampment staff can make themselves aware of any pre-existing medical problems or conditions and be alert to help you. This form will also provide medical information in a case when you are unable to do so.
Sources
[1] CAPF 160, CAP Member Health History Form, Civil Air Patrol (the Official source link on this page).
