

Form 470-4694 at a glance
What it is: Form 470-4694 (Rev. 1/10) is the Case Management Comprehensive Assessment.
Who signs: The Assessor signs on Signature and fills in the Date. Under Home- and Community-Based Services (HCBS), where the consumer may choose (1) Home- and Community-Based Services or (2) Medical Institutional Services, the Consumer or Guardian or Durable Power of Attorney for Health Care signs the Signature of Consumer or Guardian or Durable Power of Attorney for Health Care line and fills in the Date.
A filled-in Form 470-4694 example: an initial assessment for a waiver applicant

How to fill out Form 470-4694, box by box
Section A: Consumer Information
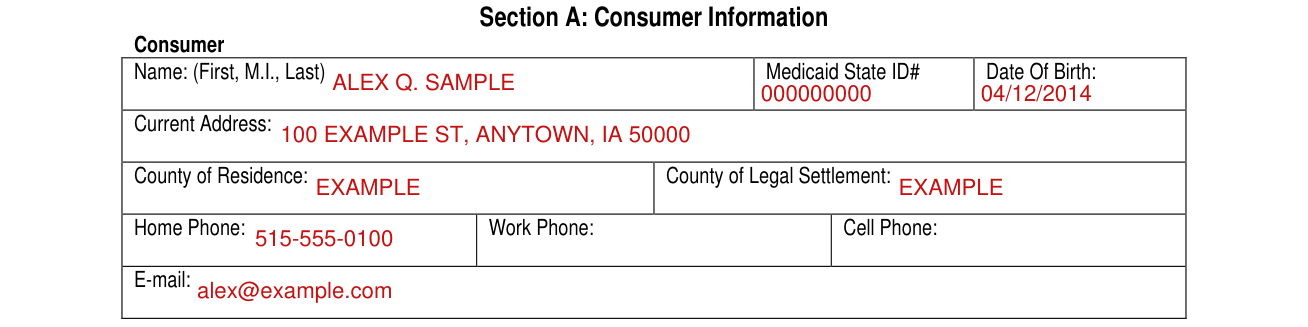
Under Section A: Consumer Information, enter the Consumer Name (First, M.I., Last), Medicaid State ID#, Date Of Birth, Current Address, County of Residence, County of Legal Settlement, Home Phone, Work Phone, Cell Phone and E-mail.
Assessor

Enter the Assessor Name, Title, Agency, Address, Phone and E-Mail, then the Signature and Date.
Type of Assessment

Under Type of Assessment, mark Initial, Annual, Special, Demographic Change Only or Discharge. For Demographic Change Only, fill in the Date; for Discharge, fill in the Discharge Date and the Reason.
Basis of Case Management Eligibility

Under Basis of Case Management Eligibility, mark CMI, MR, DD, BI Waiver, Elderly Waiver, CMH Waiver, Habilitation or MFP.
Complete the Verification of HCBS Waiver Consumer Choice section for consumers applying for HCBS Brain Injury Waiver, Children's Mental Health Waiver, Intellectual Disability Waiver.
Home- and Community-Based Services (HCBS)

Under Home- and Community-Based Services (HCBS), the consumer is advised that they may choose (1) Home- and Community-Based Services or (2) Medical Institutional Services; mark I choose: HCBS or Medical Institutional Services, then sign the Signature of Consumer or Guardian or Durable Power of Attorney for Health Care line and fill in the Date.
More rules for Form 470-4694
For consumers applying for or receiving HCBS Intellectual Disability Waiver, list the most current IQ score, or if the IQ isn't listed, give the consumer's level of functioning within the range of mental retardation (mild, moderate, severe, profound).
For consumers applying for or receiving HCBS Brain Injury Waiver, fill in the Diagnosis and the Date Injury Occurred.
Comment on any risk factors marked as "Yes" and address the issue in the Crisis Intervention Plan.
Complete B15 only if the consumer is taking medications.
At B19, if a consumer doesn't have an item but needs it, mark the "Needs" box.
Under Complete This Section For Adults (Age 18 and Over), mark Veteran Yes or No and fill in the Marital Status.
Complete Section H: Vocational for consumers age 14 or older.
Sources
[1] Form 470-4694 (Rev. 1/10), Case Management Comprehensive Assessment, Iowa Department of Health and Human Services (the Official source link on this page).
