
CDCR 7385 at a glance
What it is: CDCR 7385 is the State of California Authorization for Release of Protected Health Information from California Correctional Health Care Services.
Who signs: Under 9. SIGNATURES, the Patient/Agent signs at Signature of Patient/Agent.
What to bring and attach to CDCR 7385
If you are the Agent, you must attach documentation of your authority to act on behalf of the patient.
A filled-in CDCR 7385 example: a patient releases her own records
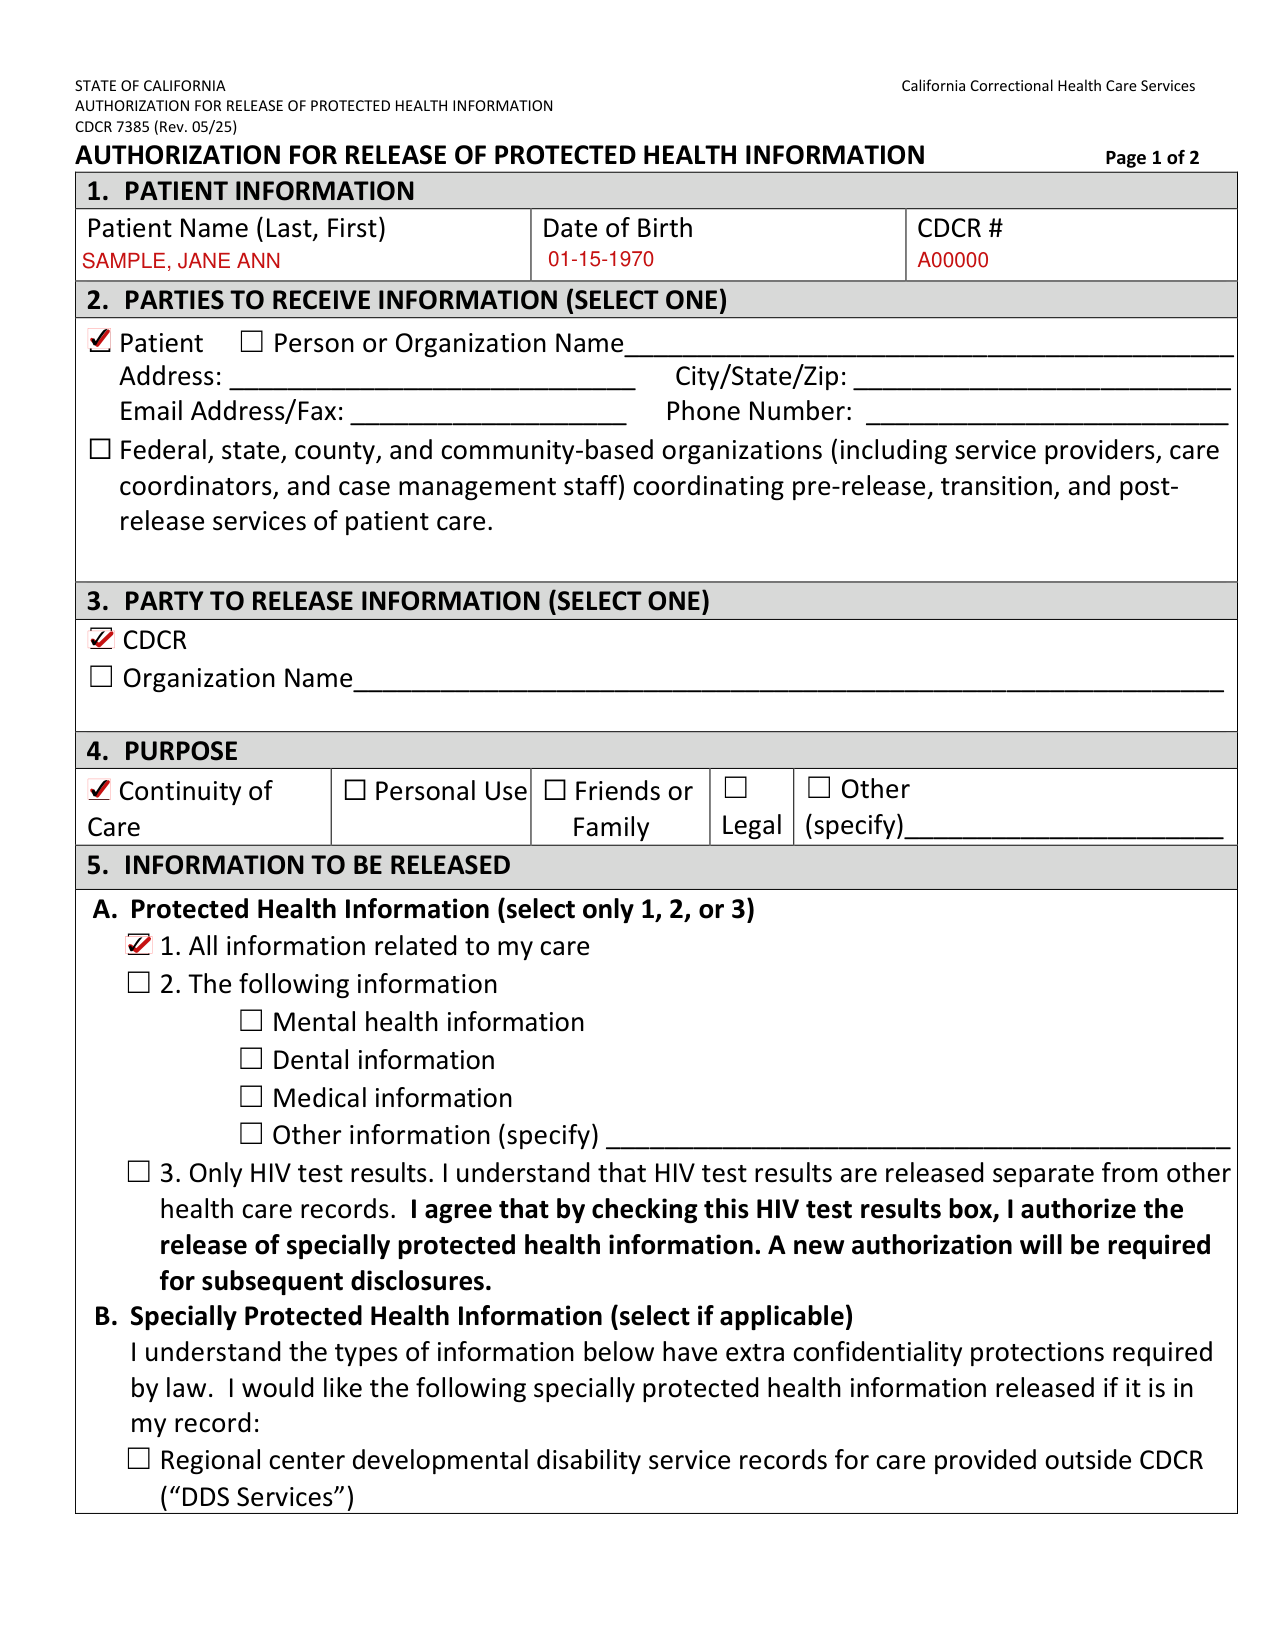
How to fill out CDCR 7385, box by box
1. Patient information

Under 1. PATIENT INFORMATION, enter the Patient Name (Last, First), the Date of Birth and the CDCR #.
2. Parties to receive information
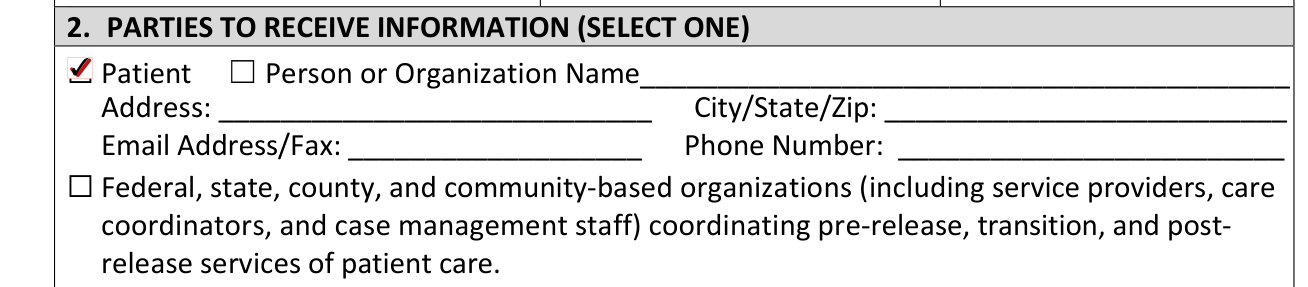
Under 2. PARTIES TO RECEIVE INFORMATION, select one: Patient; Person or Organization, with Name, Address, City/State/Zip, Email Address/Fax and Phone Number; or Federal, state, county, and community-based organizations.
Federal, state, county, and community-based organizations (including service providers, care coordinators, and case management staff) coordinating pre-release, transition, and post-release services of patient care.
3. Party to release information

Under 3. PARTY TO RELEASE INFORMATION, select one: CDCR, or Organization with the Organization Name.
4. Purpose

Under 4. PURPOSE: Continuity of Care, Personal Use, Friends or Family, Legal, or Other (specify).
5A. Protected health information

Under A. Protected Health Information, select only 1, 2, or 3: 1. All information related to my care; 2. The following information; or 3. Only HIV test results.
With 2. The following information, select Mental health information, Dental information, Medical information, or Other information (specify).
3. Only HIV test results: I understand that HIV test results are released separate from other health care records. I agree that by checking this HIV test results box, I authorize the release of specially protected health information. A new authorization will be required for subsequent disclosures.
5B. Specially protected health information
B. Specially Protected Health Information (select if applicable): I understand the types of information in B have extra confidentiality protections required by law. I would like the following specially protected health information released if it is in the record:
Regional center developmental disability service records for care provided outside CDCR (“DDS Services”).
Substance use treatment service records for care provided outside CDCR, including any services provided by a Narcotic Treatment Program (“Part 2 Program Services”).
5C. Dates of service

C. Dates of Service (select one), before 6: All dates of service, or Only dates of service from (insert dates).
6. Method of release of information

Under METHOD OF RELEASE OF INFORMATION (SELECT ALL THAT APPLY): Written or electronic records (e.g., facsimile, mail, CD) or Verbal or written correspondence (Note: This option is not available to patients who have paroled or discharged from CDCR.)
7. Expiration date

Under 7. EXPIRATION DATE, select one: This authorization shall remain in effect until revoked by the patient; This authorization expires one year from the date signed at 9. SIGNATURES; or This authorization expires on the following date.
I may revoke this authorization at any time by providing written notification to California Correctional Health Care Services, Health Information Management Services. If I revoke this authorization, my revocation will be effective upon receipt but will have no impact on uses or disclosures made while my authorization was valid.
9. Signatures
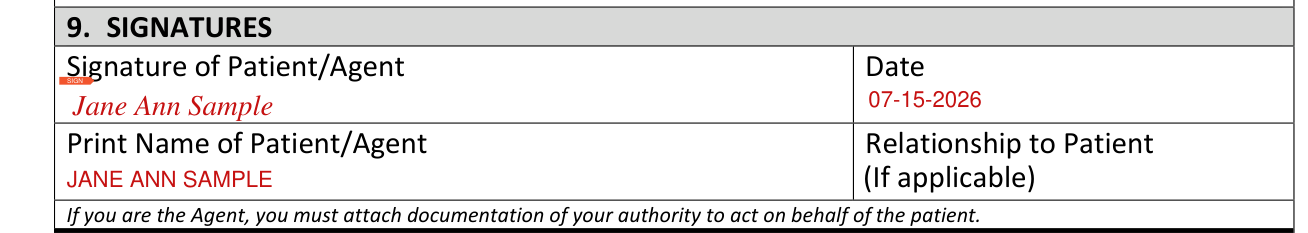
Under 9. SIGNATURES, enter the Date, the Print Name of Patient/Agent and the Relationship to Patient (If applicable).
More rules for CDCR 7385
Under 8. RIGHTS, I understand: I may refuse to sign this authorization; refusal will not affect my ability to obtain treatment.
I may request a copy of this signed form.
Information disclosed pursuant to this authorization may be subject to redisclosure by recipient and may no longer be subject to federal and state privacy law protection. Even if I do not authorize a release of health information, CDCR may share my confidential information for treatment, payment, and health care operations and other purposes required or permitted by law.
Sources
[1] CDCR 7385 (Rev. 05/25), Authorization for Release of Protected Health Information, California Correctional Health Care Services (the Official source link on this page).