

VA Form 10-7959a at a glance
What it is: VA Form 10-7959a is the CHAMPVA claim form.
Who signs: This form is to be completed by the patient, sponsor or guardian (it is NOT to be used for provider submitted claims). SIGN and enter the Date (MM/DD/YYYY). If certification is signed by a person other than the patient, complete that person's Signature, Last Name, First Name, MI and Relationship to Patient.
A filled-in VA Form 10-7959a example: a patient files a claim with employer insurance
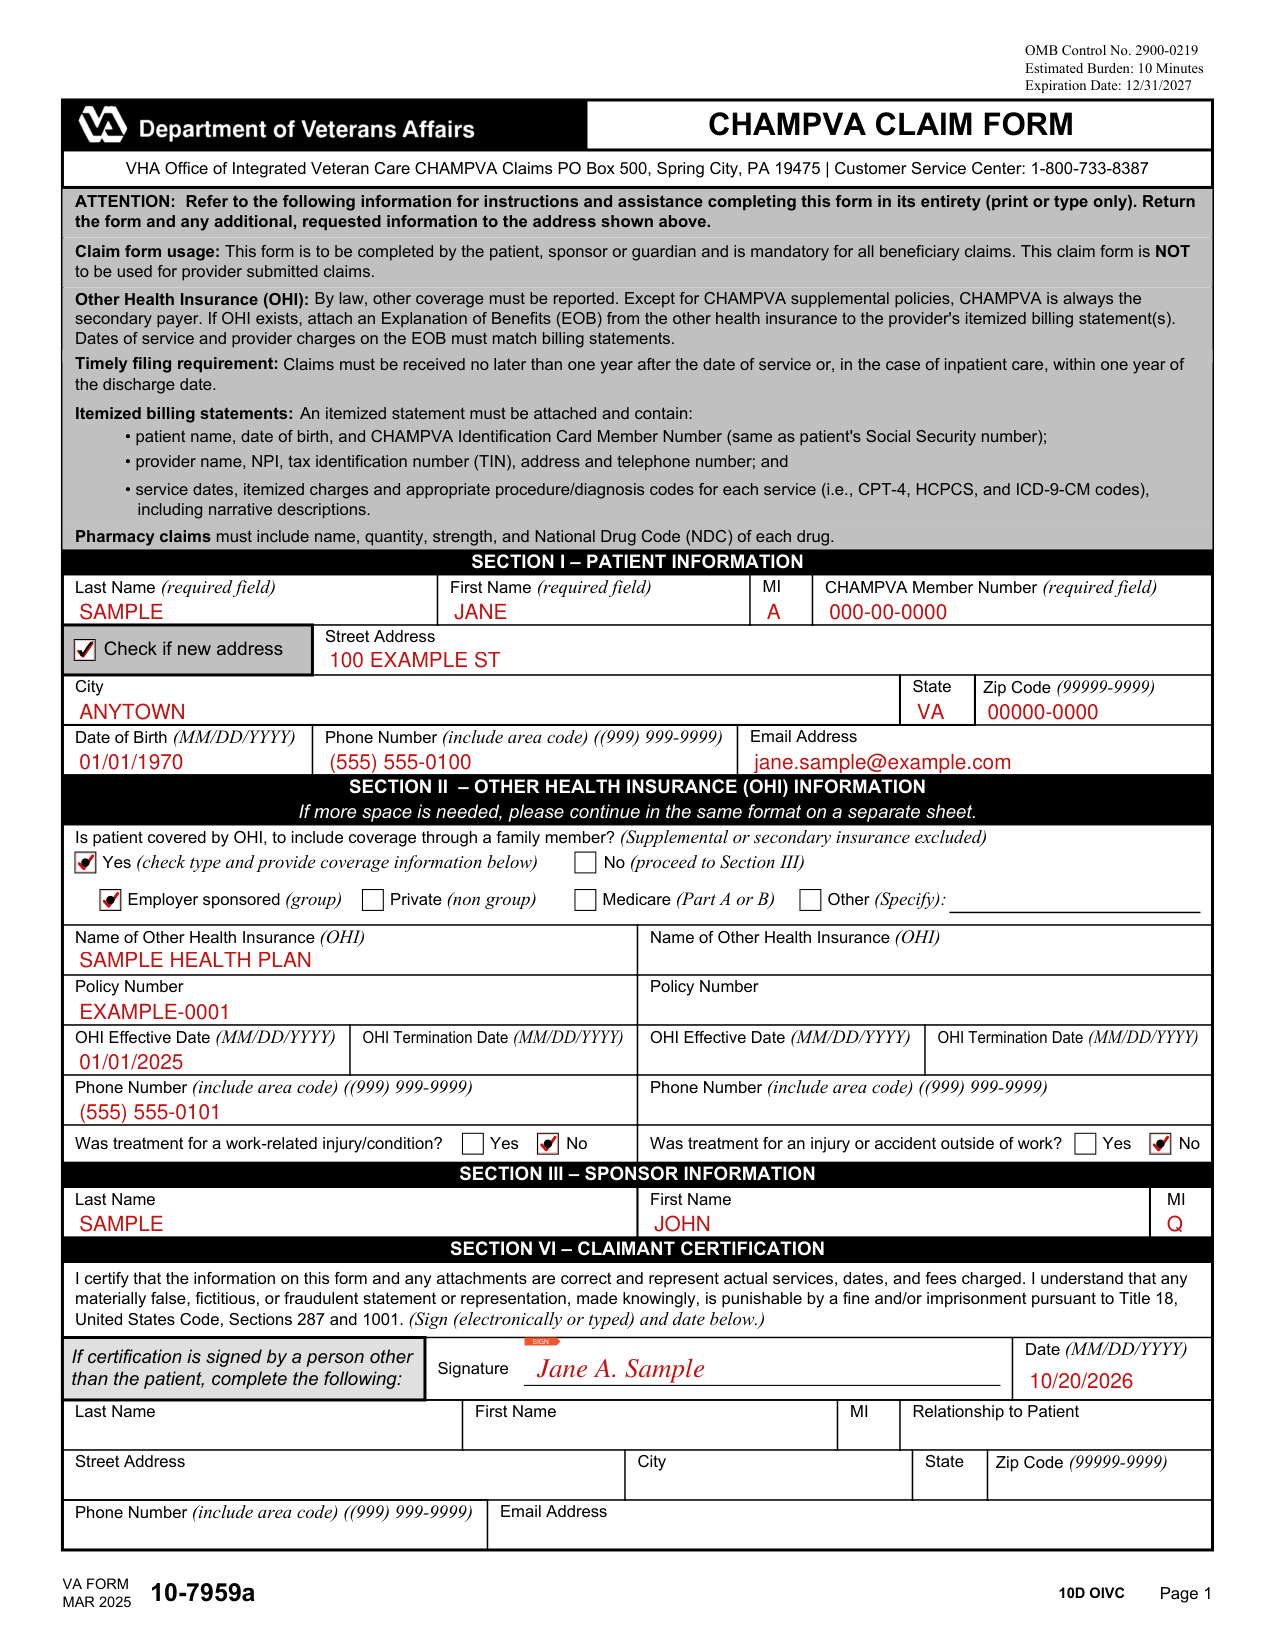
How to fill out VA Form 10-7959a, box by box
Section I, Patient Information
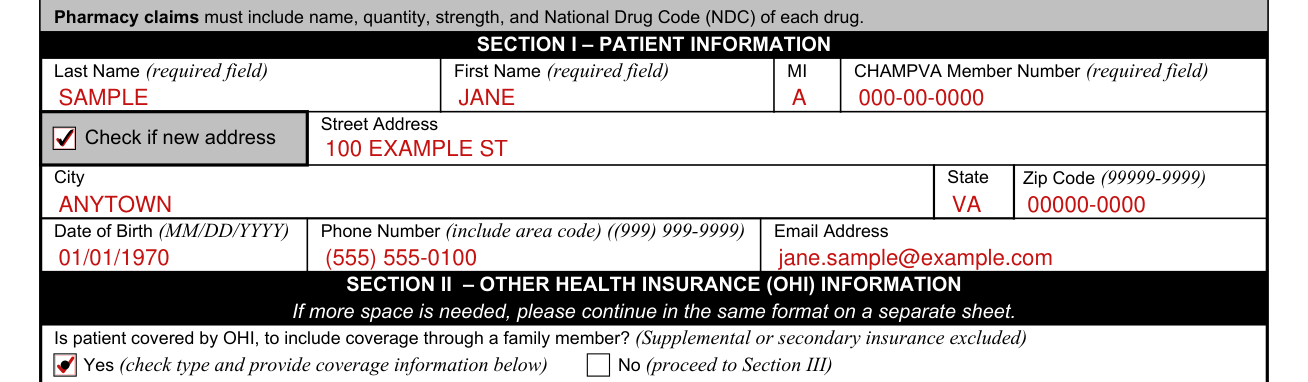
Enter Last Name, First Name, MI and CHAMPVA Member Number; Last Name, First Name and CHAMPVA Member Number are required fields.
The CHAMPVA Identification Card Member Number is the same as the patient's Social Security number.
Mark Check if new address if the address is new, then enter the Street Address, City, State and Zip Code (99999-9999).
Enter the Date of Birth (MM/DD/YYYY), the Phone Number (include area code) ((999) 999-9999) and the Email Address.
Section II, Other Health Insurance (OHI) Information
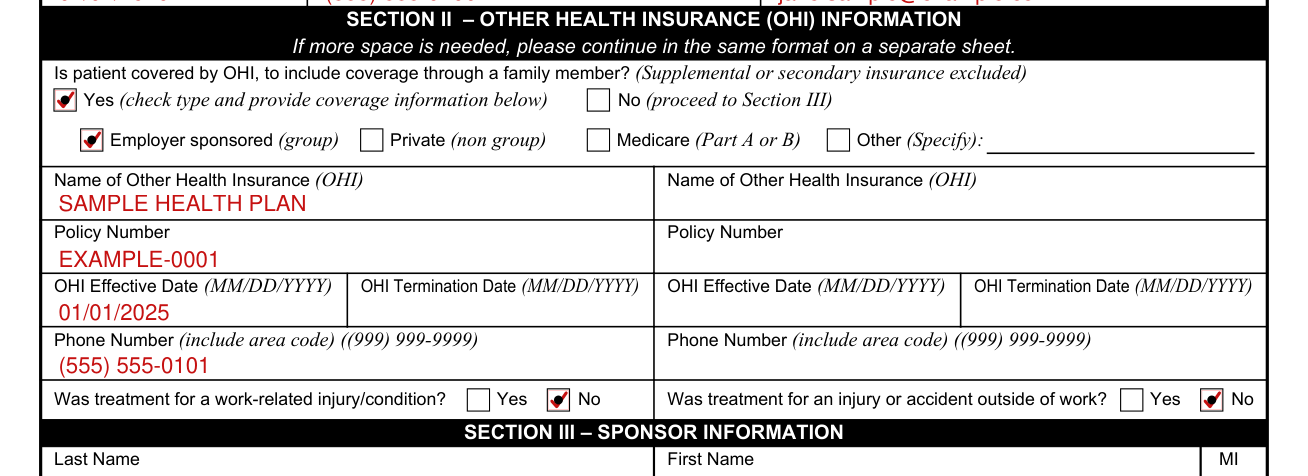
Is patient covered by OHI, to include coverage through a family member? (Supplemental or secondary insurance excluded) Mark Yes (check type and provide coverage information in Section II): Employer sponsored (group), Private (non group), Medicare (Part A or B) or Other (Specify); or mark No (proceed to Section III).
Enter the Name of Other Health Insurance (OHI), Policy Number, OHI Effective Date (MM/DD/YYYY), OHI Termination Date (MM/DD/YYYY) and Phone Number (include area code) ((999) 999-9999).
If more space is needed, please continue in the same format on a separate sheet.
Other Health Insurance (OHI): By law, other coverage must be reported. Except for CHAMPVA supplemental policies, CHAMPVA is always the secondary payer. If OHI exists, attach an Explanation of Benefits (EOB) from the other health insurance to the provider's itemized billing statement(s). Dates of service and provider charges on the EOB must match billing statements.
Mark Yes or No for Was treatment for a work-related injury/condition? and for Was treatment for an injury or accident outside of work?
Section III, Sponsor Information
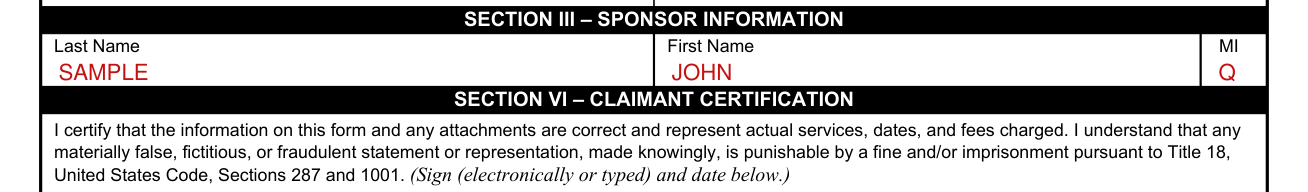
Enter the sponsor Last Name, First Name and MI.
Section VI, Claimant Certification
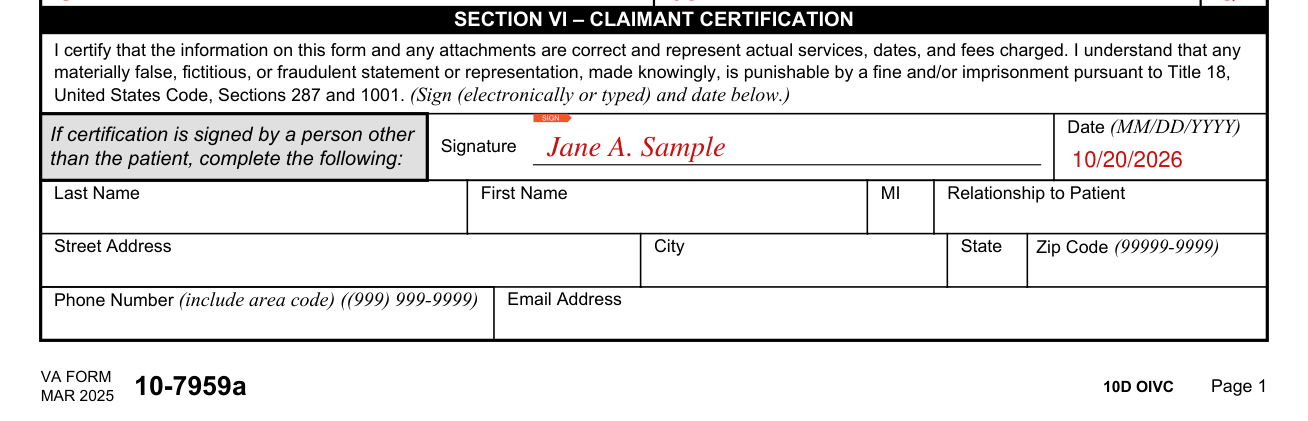
SECTION VI - CLAIMANT CERTIFICATION: By signing you certify that the information on this form and any attachments are correct and represent actual services, dates, and fees charged. You understand that any materially false, fictitious, or fraudulent statement or representation, made knowingly, is punishable by a fine and/or imprisonment pursuant to Title 18, United States Code, Sections 287 and 1001. (Sign (electronically or typed) and date in Section VI.)
SIGN and enter the Date (MM/DD/YYYY).
If certification is signed by a person other than the patient, complete the following: Signature
Last Name, First Name, MI, Relationship to Patient, Street Address, City, State, Zip Code (99999-9999), Phone Number (include area code) ((999) 999-9999) and Email Address.
If certification is signed by a person other than the patient, that person also signs on the Signature line.
More rules for VA Form 10-7959a
Termination of marriage by divorce or annulment to the qualifying sponsor ends CHAMPVA eligibility as of midnight on the effective date of the dissolution of marriage.
Changes in status should be reported immediately to CHAMPVA, ATTN: VHA Office of Integrated Veteran Care CHAMPVA Eligibility PO Box 137 Spring City, PA 19475 or call 1-800-733-8387.
Questions about completing this form may be addressed by calling the CHAMPVA Help Line at 1-800-733-8387.
Before you go
An itemized statement must be attached and contain: patient name, date of birth, and CHAMPVA Identification Card Member Number (same as patient's Social Security number); provider name, NPI, tax identification number (TIN), address and telephone number; and service dates, itemized charges and appropriate procedure/diagnosis codes for each service (i.e., CPT-4, HCPCS, and ICD-9-CM codes), including narrative descriptions.
Pharmacy claims must include name, quantity, strength, and National Drug Code (NDC) of each drug.
Common questions about VA Form 10-7959a
Is there a deadline?
Claims must be received no later than one year after the date of service or, in the case of inpatient care, within one year of the discharge date.
Where do I file it?
Print or type only. Return the form and any additional, requested information to VHA Office of Integrated Veteran Care CHAMPVA Claims, PO Box 500, Spring City, PA 19475.
When is this form not the right one?
This form is to be completed by the patient, sponsor or guardian and is mandatory for all beneficiary claims. This claim form is NOT to be used for provider submitted claims.
Sources
[1] VA Form 10-7959a (MAR 2025), CHAMPVA Claim Form, Department of Veterans Affairs (the Official source link on this page).
