

Claim Form (Group Policy 285630) at a glance
What it is: Claim Form, Group Policy 285630, to be completed by the insured member.
Who signs: The member signs (Signature of member) the authorization for direct payment of benefits and enters the Date. "I certify the information on this form is complete and accurate." Signature of patient or member Date.
To be completed by insured member. All items must be answered in full before your claim can be processed.
A filled-in Claim Form (Group Policy 285630) example: a member files a claim for a sickness

How to fill out Claim Form (Group Policy 285630), box by box
New address

Check here if new address since last submission. Date relocated.
Member's name, mailing address and enrollment
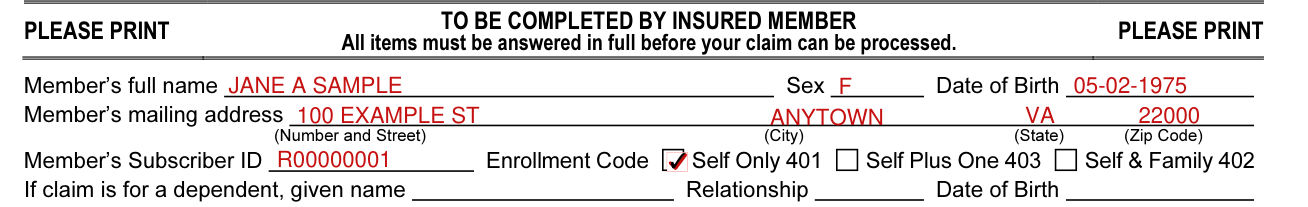
Enter the Member's full name, Sex, Date of Birth and Member's mailing address (Number and Street) (City) (State) (Zip Code).
Enter the Member's Subscriber ID and the Enrollment Code: Self Only 401, Self Plus One 403 or Self & Family 402.
Claim for a dependent
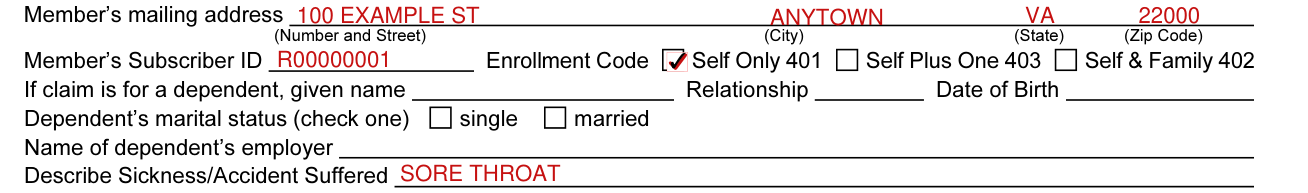
If claim is for a dependent, enter given name, Relationship, Date of Birth, Dependent's marital status (check one) single or married, and Name of dependent's employer.
Sickness or accident suffered
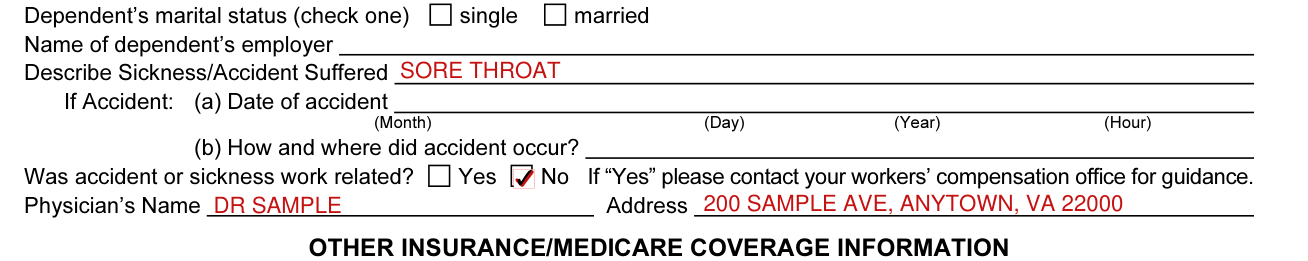
Describe Sickness/Accident Suffered. If Accident: (a) Date of accident (Month) (Day) (Year) (Hour); (b) How and where did accident occur?
Was accident or sickness work related? Yes or No. If “Yes” please contact your workers' compensation office for guidance.
Physician

Enter the Physician's Name and Address.
Other insurance coverage

This question must be answered and the form signed before claim can be processed.
(a) Are you or any member of your family covered under any health plan other than FOREIGN SERVICE BENEFIT PLAN? Yes or No.
(b) If answer is “Yes”, complete the following: Person in whose name the other plan is issued, Name of all dependents covered under the other plan, Name of Insurance Company or Plan, Effective Date, Address of Claims Office, Is this insurance through active employment?, Employment Effective Date, Policy or Contract Number, Is Plan Family or Self only coverage? (Check appropriate block).
(c) Is this other plan issued under a Group or Individual contract? (Check appropriate block).
Medicare coverage
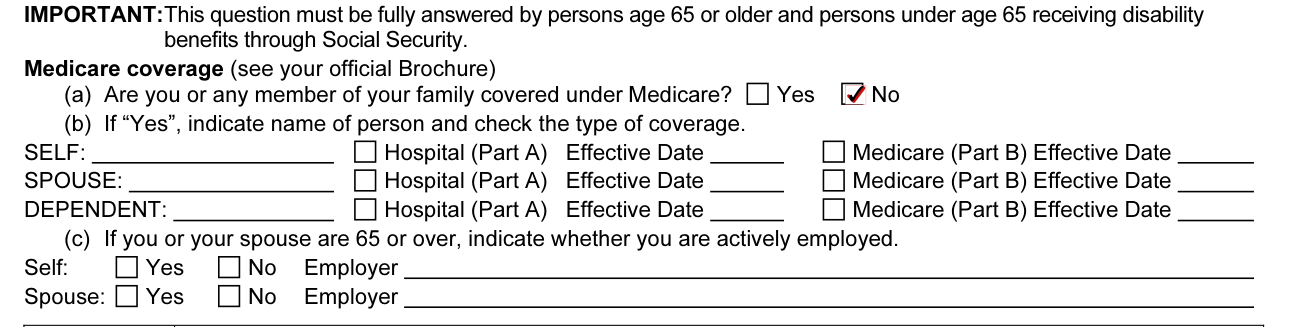
This question must be fully answered by persons age 65 or older and persons under age 65 receiving disability benefits through Social Security. (a) Are you or any member of your family covered under Medicare? Yes or No. (b) If “Yes”, indicate name of person and check the type of coverage. SELF, SPOUSE and DEPENDENT each have: Hospital (Part A) Effective Date, Medicare (Part B) Effective Date. (c) If you or your spouse are 65 or over, indicate whether you are actively employed. Self: Yes or No, Employer. Spouse: Yes or No, Employer.
Authorization for direct payment of benefits
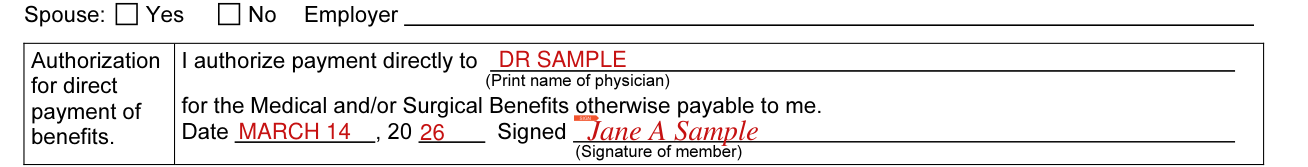
Authorization for direct payment of benefits. I authorize payment directly to (Print name of physician) for the Medical and/or Surgical Benefits otherwise payable to me.
The member signs (Signature of member) the authorization for direct payment of benefits and enters the Date.
Certification

"I certify the information on this form is complete and accurate." Signature of patient or member Date.
Forward completed claim form

Forward the completed claim form to: Foreign Service Benefit Plan, 1620 L Street, NW, Suite 800, Washington, DC 20036-5629. Phone: (202) 833-4910.
Have you answered every question? Have you dated and signed this form?
Common questions about Claim Form (Group Policy 285630)
Is there a penalty?
Any intentional false statement in this application or willful misrepresentation relative thereto is a violation of the law punishable by a fine of not more than $10,000, or imprisonment of not more than five years, or both (checked November 10, 2026).
Sources
[1] Claim Form, Group Policy 285630 (GC-16435 (12-17)), Foreign Service Benefit Plan (the served file; no issuer file found) (the Official source link on this page).
