

Form CH205 at a glance
What it is: The CH205 is the Child & Adolescent Health Examination Form of the Department of Education Health and the Department of Health and Mental Hygiene.
Please Print Clearly. The parent or guardian completes the part marked TO BE COMPLETED BY THE PARENT OR GUARDIAN.
The health care practitioner completes the part marked TO BE COMPLETED BY THE HEALTH CARE PRACTITIONER.
A filled-in Form CH205 example: a healthy five-year-old's exam
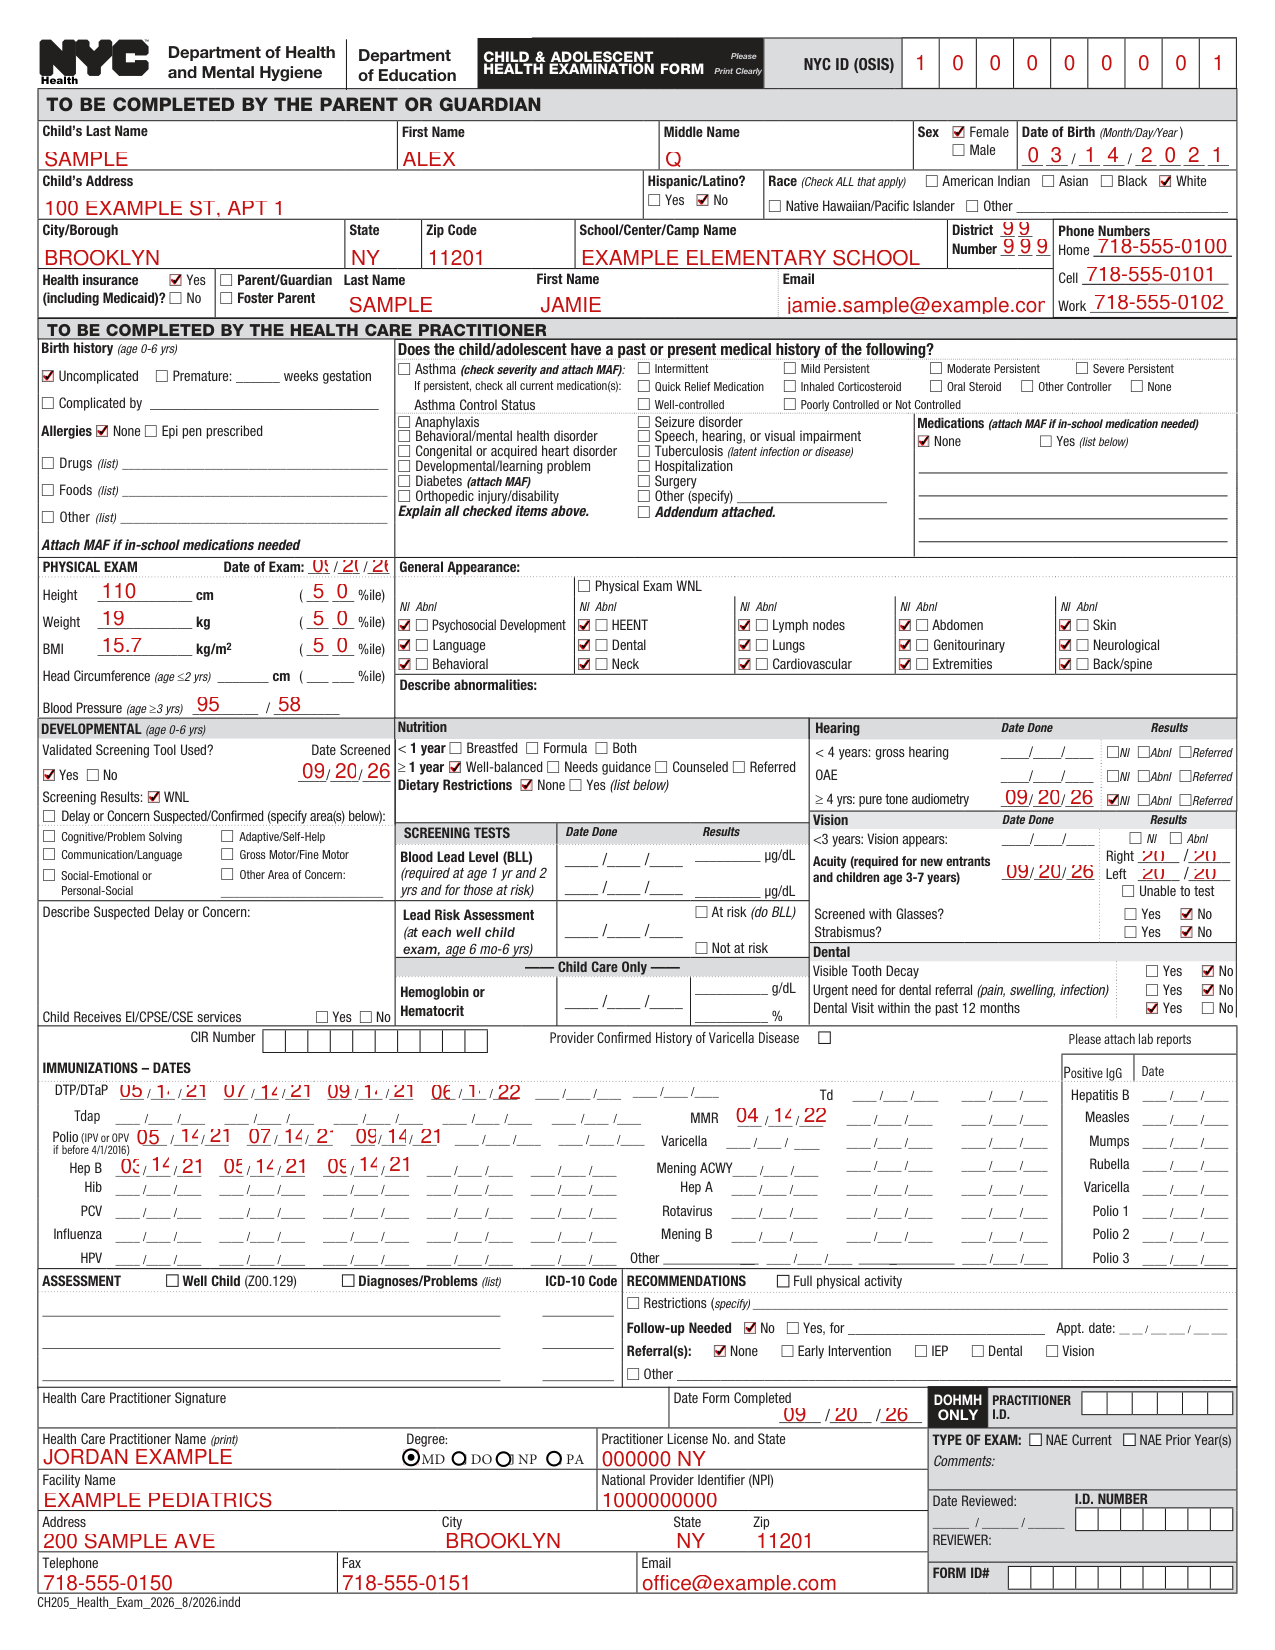
How to fill out Form CH205, box by box
Tap a group of boxes to open it, and a picture to see it full size.
NYC ID (OSIS), name, Sex and Date of Birth
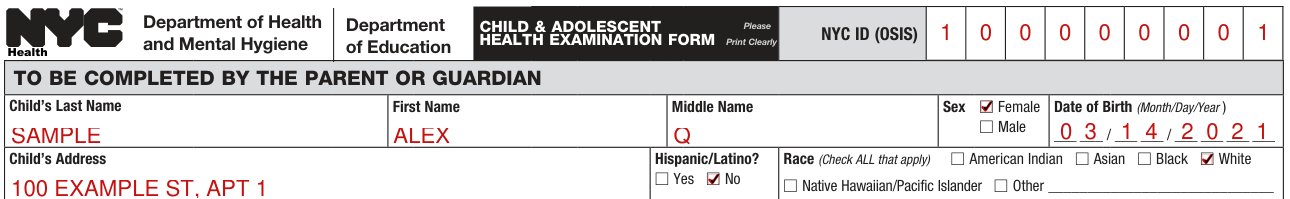
Enter the NYC ID (OSIS), the Child's Last Name, First Name and Middle Name, and mark Sex Female or Male.
Enter the Date of Birth as Month/Day/Year.
Child's Address, Hispanic/Latino?, Race and School/Center/Camp Name

Enter the Child's Address, then City/Borough, State and Zip Code. Mark Hispanic/Latino? Yes or No.
Under Race (Check ALL that apply), mark American Indian, Asian, Black, White, Native Hawaiian/Pacific Islander or Other, and write the other race on the line.
Enter the School/Center/Camp Name, the District and the Number.
Health insurance, Parent/Guardian and Phone Numbers

For Health insurance (including Medicaid)?, mark Yes or No.
Mark Parent/Guardian or Foster Parent, then enter the Last Name, First Name and Email.
Enter the Phone Numbers: Home, Cell and Work.
Birth history, medical history, Medications and Allergies

For Birth history (age 0-6 yrs), mark Uncomplicated, Premature or Complicated by, and write the weeks gestation or what it was complicated by on the line.
For Asthma, check the severity and attach MAF: Intermittent, Mild Persistent, Moderate Persistent or Severe Persistent. If persistent, check all current medication(s): Quick Relief Medication, Inhaled Corticosteroid, Oral Steroid, Other Controller or None. For Asthma Control Status, check Well-controlled or Poorly Controlled or Not Controlled.
Check each of the following that the child/adolescent has as a past or present medical history: Anaphylaxis, Seizure disorder, Behavioral/mental health disorder, Speech, hearing, or visual impairment, Congenital or acquired heart disorder, Tuberculosis (latent infection or disease), Developmental/learning problem, Hospitalization, Diabetes (attach MAF), Surgery, Orthopedic injury/disability or Other (specify). Explain all checked items. Mark Addendum attached.
For Medications (attach MAF if in-school medication needed), mark None or Yes (list below).
For Allergies, mark None, Epi pen prescribed or Drugs (list). Attach MAF if in-school medications needed.
PHYSICAL EXAM, Height, Weight and BMI
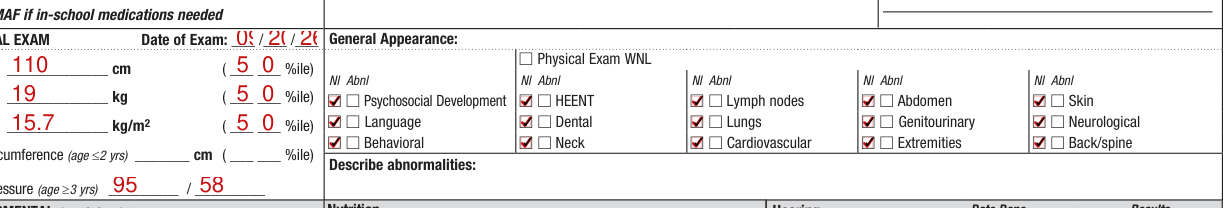
Enter the Date of Exam, Height in cm, Weight in kg and BMI in kg/m2, each with its %ile.
Enter Head Circumference (age ≤2 yrs) in cm with its %ile, and Blood Pressure (age ≥3 yrs) in the two boxes.
Mark Physical Exam WNL. Mark Nl or Abnl for each of Psychosocial Development, HEENT, Abdomen, Skin, Language, Dental, Lungs, Genitourinary, Neurological, Behavioral, Neck, Cardiovascular, Extremities and Back/spine. Describe abnormalities.
DEVELOPMENTAL (age 0-6 yrs)
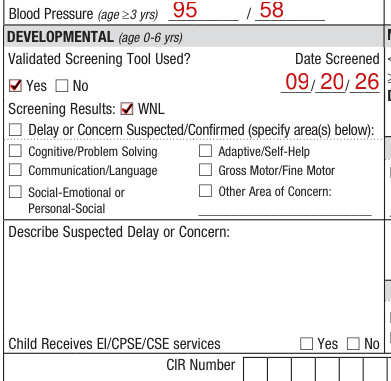
For DEVELOPMENTAL (age 0-6 yrs): mark Validated Screening Tool Used? Yes or No and enter the Date Screened; for Screening Results, mark WNL or Delay or Concern Suspected/Confirmed (specify area(s) below), and Describe Suspected Delay or Concern.
Nutrition and Dietary Restrictions

For Nutrition < 1 year, mark Breastfed, Formula or Both. For Nutrition ≥ 1 year, mark Well-balanced, Needs guidance, Counseled or Referred. For Dietary Restrictions, mark None or Yes (list below).
Hearing, Vision and Dental
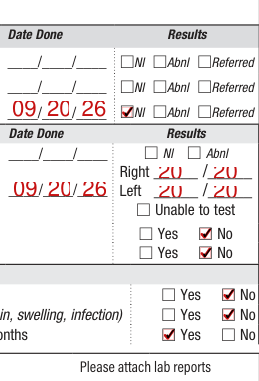
Hearing has a line for < 4 years: gross hearing, a line for OAE and a line for ≥ 4 yrs: pure tone audiometry. Each line has a Date Done and Results to mark.
For Vision, enter the Date Done and the Results. For <3 years: Vision appears, mark Nl or Abnl. For Acuity (required for new entrants and children age 3-7 years), enter Right and Left in the boxes, two for each, and mark Unable to test where it applies. Mark Screened with Glasses? Yes or No, and Strabismus? Yes or No.
For Dental, mark Visible Tooth Decay Yes or No, Urgent need for dental referral (pain, swelling, infection) Yes or No, and Dental Visit within the past 12 months Yes or No.
Blood Lead Level, Lead Risk Assessment and Hemoglobin or Hematocrit
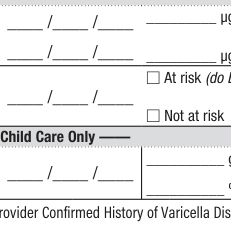
Under SCREENING TESTS, for Blood Lead Level (BLL) (required at age 1 yr and 2 yrs and for those at risk), enter the Date Done and the Results in µg/dL.
For Lead Risk Assessment (at each well child exam, age 6 mo-6 yrs), enter the Date Done and mark At risk (do BLL) or Not at risk.
Child Care Only: for Hemoglobin or Hematocrit, enter the Date Done, the Results in g/dL and the Results in %.
IMMUNIZATIONS - DATES, Positive IgG Date and CIR Number
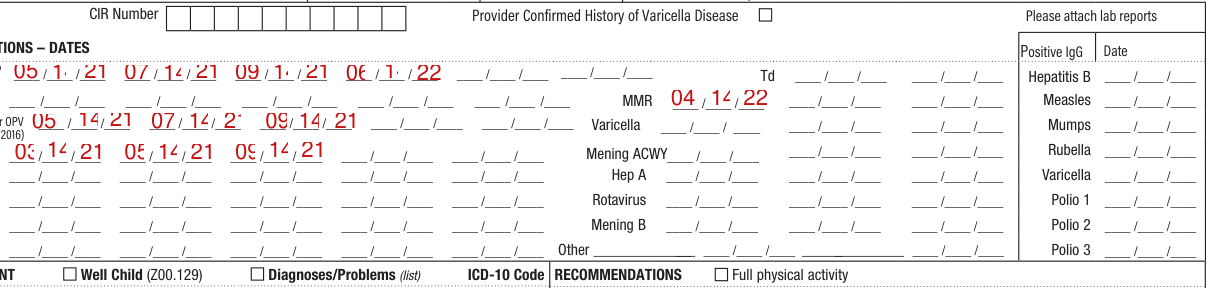
Under IMMUNIZATIONS - DATES, enter each date in its three boxes for DTP/DTaP, Td, Tdap, MMR, Polio (IPV or OPV if before 4/1/2016), Varicella, Hep B, Mening ACWY, Hib, Hep A, PCV, Rotavirus, Influenza, Mening B, HPV and Other.
For Positive IgG Date, enter the date for Hepatitis B, Measles, Mumps, Rubella, Varicella, Polio 1, Polio 2 and Polio 3.
Enter the CIR Number and mark Provider Confirmed History of Varicella Disease. Please attach lab reports.
ASSESSMENT and RECOMMENDATIONS

Under ASSESSMENT, mark Well Child (Z00.129), or list Diagnoses/Problems with the ICD-10 Code.
Under RECOMMENDATIONS, mark Full physical activity, or mark Restrictions and specify them on the line.
For Follow-up Needed, mark No, or mark Yes and write what it is for on the line, then enter the Appt. date.
For Referral(s), mark None, Early Intervention, IEP, Dental, Vision or Other, and write the other referral on the line.
Health Care Practitioner Signature, name and Degree

The health care practitioner signs the Health Care Practitioner Signature line and enters the Date Form Completed.
Enter the Health Care Practitioner Name (print), mark the Degree MD, DO, NP or PA, and enter the Practitioner License No. and State, the Facility Name, the National Provider Identifier (NPI), the Address, City, State and Zip, and the Telephone, Fax and Email.
More rules for Form CH205
Mark Child Receives EI/CPSE/CSE services Yes or No.
Sources
[1] Form CH205, Child & Adolescent Health Examination Form, New York City Department of Education and Department of Health and Mental Hygiene (the Official source link on this page).
