

Personal Training Client Health History Form at a glance
What it is: The Personal Training Client Health History Form is a Client Information and Release Form; to assist in the development of a rewarding physical fitness program, it needs honest and accurate responses.
Who signs: Consent for minors is required prior to first session. Take a moment to carefully read the information and sign where indicated: SIGN, Signature and Date.
A filled-in Personal Training Client Health History Form example: a new client fills out page 1

How to fill out Personal Training Client Health History Form, box by box
Name, Birth Date, Address, E-mail and Employer
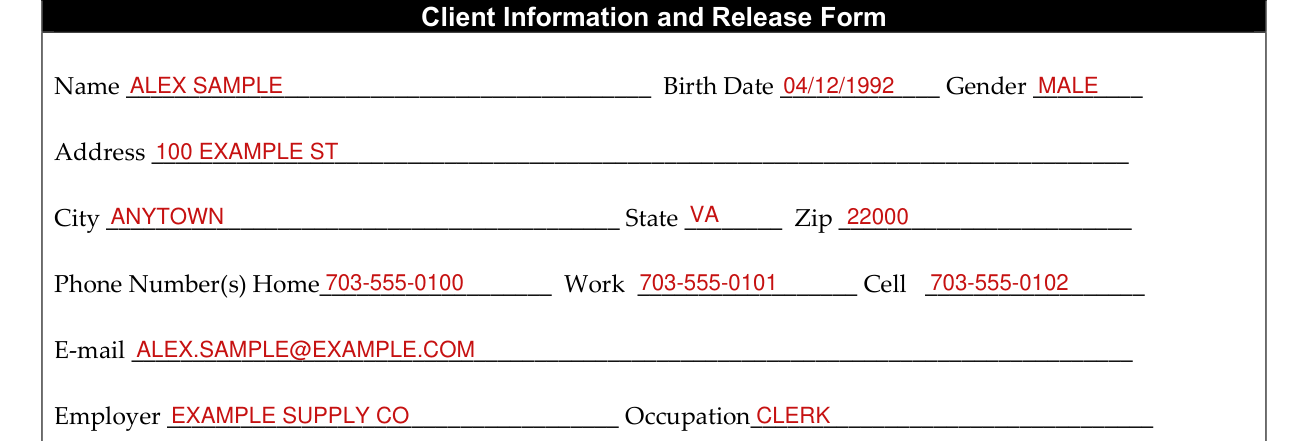
Answer each question by printing the necessary information; your answers will be kept confidential. Fill in Name, Birth Date and Gender.
Fill in Address, City, State and Zip, then Phone Number(s) Home, Work and Cell.
Fill in E-mail, Employer and Occupation.
In case of emergency, please notify
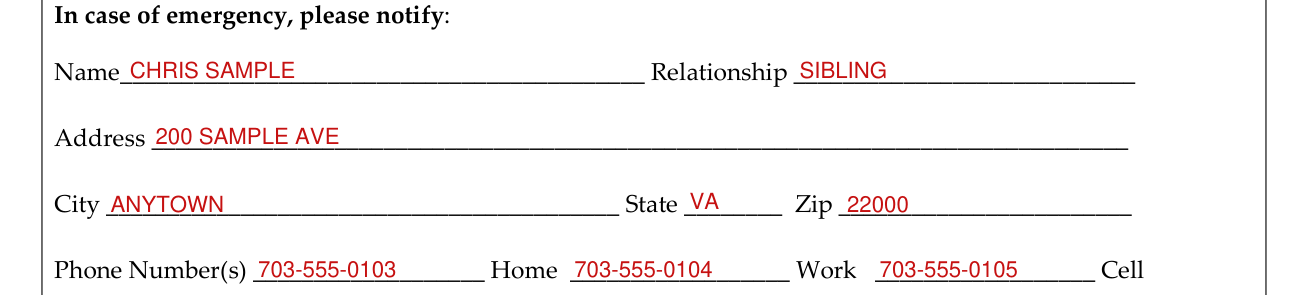
In case of emergency, please notify: fill in Name, Relationship, Address, City, State and Zip, then Phone Number(s) Home, Work and Cell.
General Medical History & Information
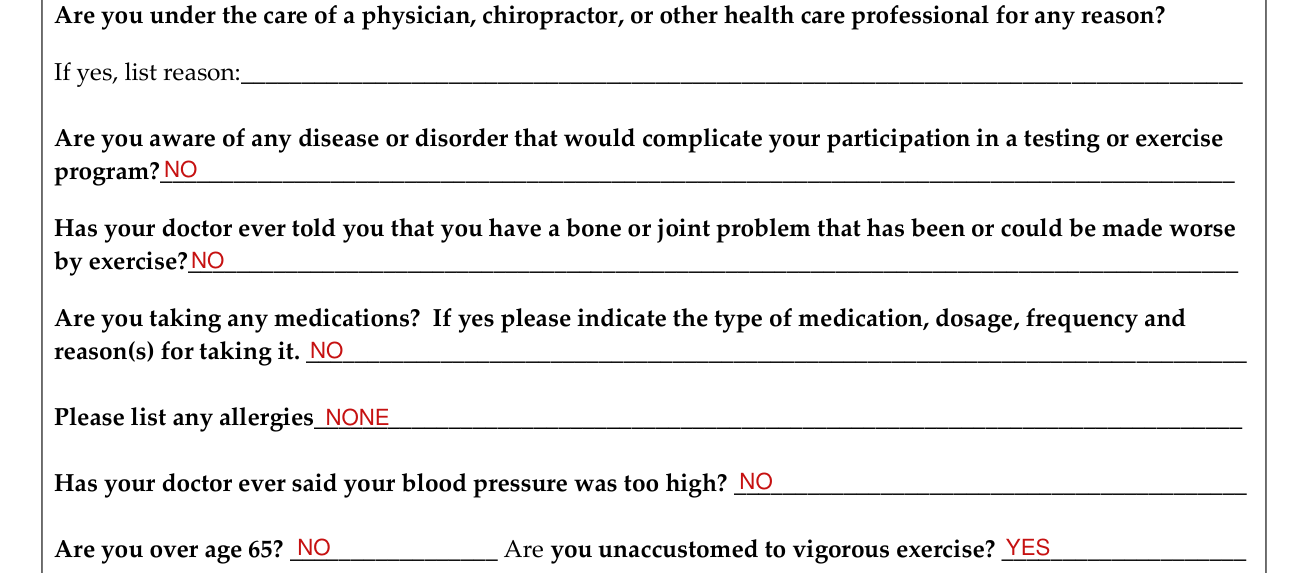
Are you under the care of a physician, chiropractor, or other health care professional for any reason? If yes, list reason.
Are you aware of any disease or disorder that would complicate your participation in a testing or exercise program?
Has your doctor ever told you that you have a bone or joint problem that has been or could be made worse by exercise?
Are you taking any medications? If yes please indicate the type of medication, dosage, frequency and reason(s) for taking it.
Please list any allergies. Has your doctor ever said your blood pressure was too high?
Are you over age 65? Are you unaccustomed to vigorous exercise?
Is there any reason not mentioned here why you should not follow a regular exercise program?

Is there any reason not mentioned here why you should not follow a regular exercise program? If so, please explain.
Please describe any past or current musculoskeletal conditions
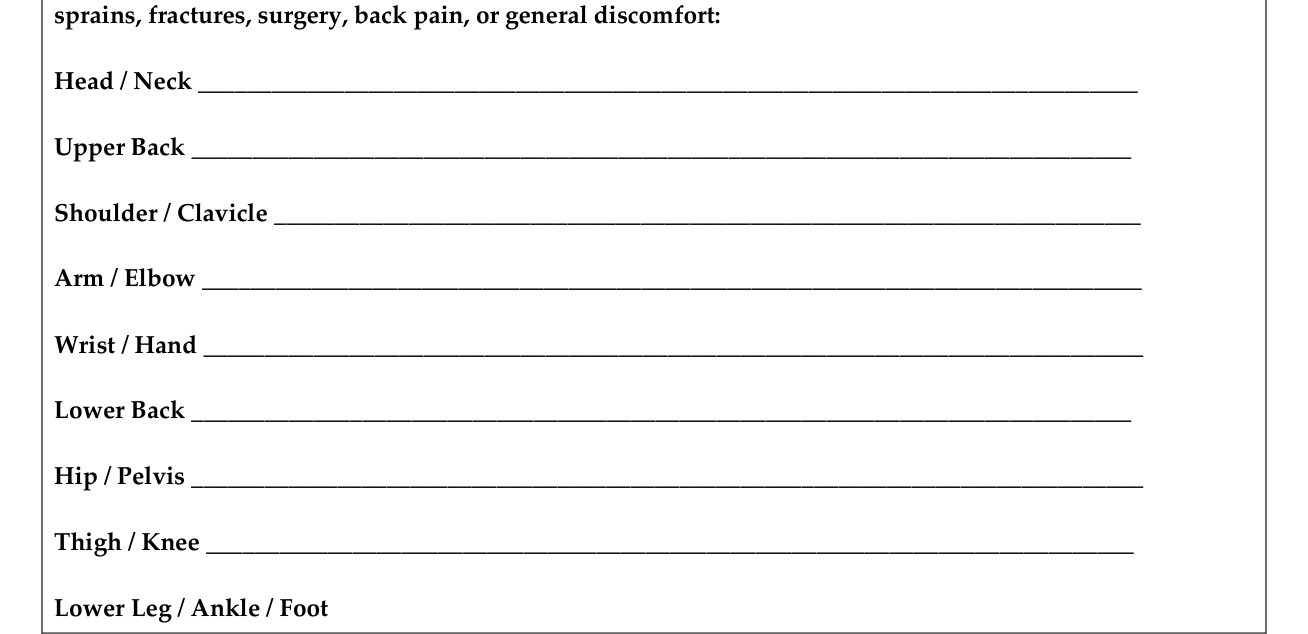
Please describe any past or current musculoskeletal conditions you have incurred such as muscle pulls, sprains, fractures, surgery, back pain, or general discomfort: Head / Neck, Upper Back, Shoulder / Clavicle, Arm / Elbow, Wrist / Hand, Lower Back, Hip / Pelvis, Thigh / Knee, Lower Leg / Ankle / Foot. Please circle any areas of pain, injury, tension, or restriction of movement.
Have you recently experienced any chest pain

Have you recently experienced any chest pain associated with either exercise or stress? If so, please explain.
Do you have a family history of any of the following conditions?

Family history: Heart Disease, Heart Attack, Hypertension, Gout, Abnormal EKG, Asthma, High Cholesterol, Angina, Diabetes, Other heart conditions. Do you have a family history of any of these conditions?
Family history, smoking, nutritional plan, caffeine and weight
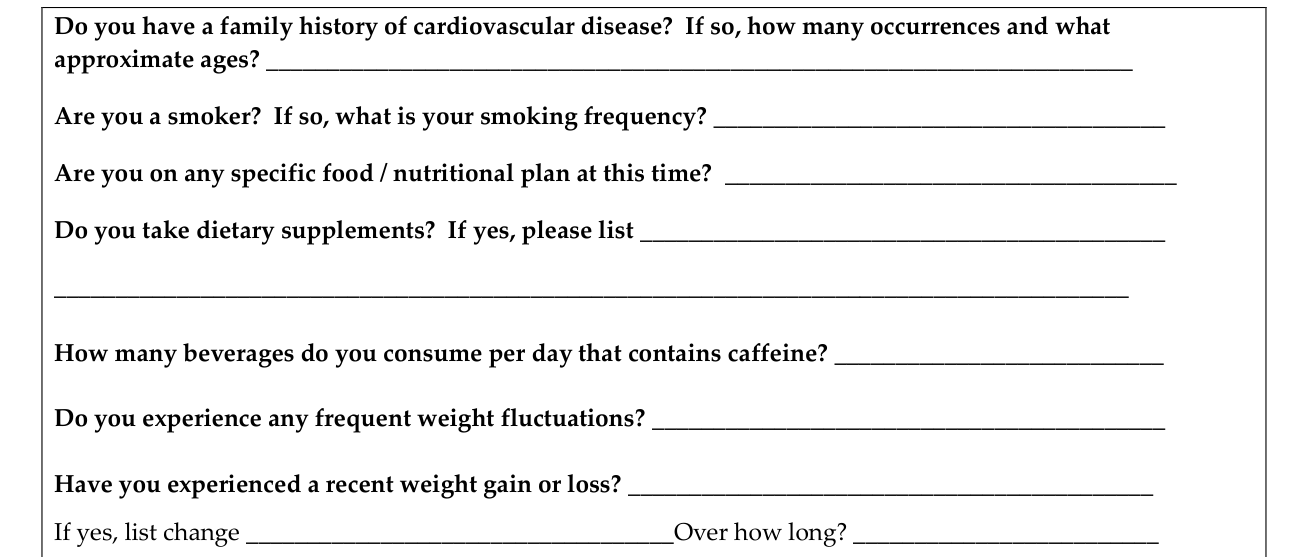
Do you have a family history of cardiovascular disease? If so, how many occurrences and what approximate ages?
Are you a smoker? If so, what is your smoking frequency?
Are you on any specific food / nutritional plan at this time? Do you take dietary supplements? If yes, please list.
How many beverages do you consume per day that contains caffeine?
Do you experience any frequent weight fluctuations? Have you experienced a recent weight gain or loss? If yes, list change. Over how long?
Signature, Date and Signature of Guardian

Take a moment to carefully read the information and sign where indicated: SIGN, Signature and Date.
By signing you affirm that you have read and fully understand the statements, have stated all your known medical conditions and answered all questions honestly, and agree to keep the personal trainer updated as to any changes in your medical profile, and understand that there shall not be liability on the personal trainer's part should you forget to do so.
SIGN: Signature of Guardian and Date, Printed name of Guardian, and Phone number the Guardian can be reached in case of emergency.
Current Exercise Information

Please explain your current exercise regimen including all strength training, cardiovascular training or other sporting activities that you perform. Day of the Week / Activity / Length of Time.
What are your goals?
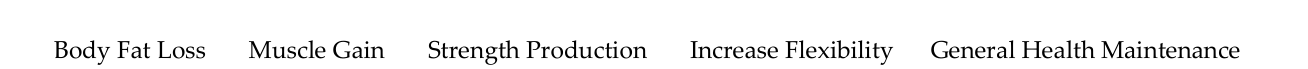
What are your goals? Circle those that apply: Body Fat Loss, Muscle Gain, Strength Production, Increase Flexibility, General Health Maintenance.
How active are you and/or what is your exercise lifestyle like?
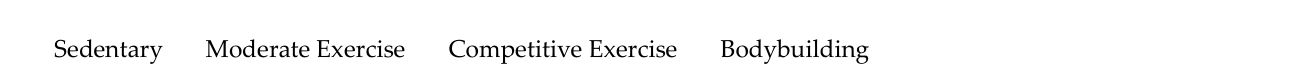
How active are you and/or what is your exercise lifestyle like? Circle those that apply: Sedentary, Moderate Exercise, Competitive Exercise, Bodybuilding.
Does your job require you to be
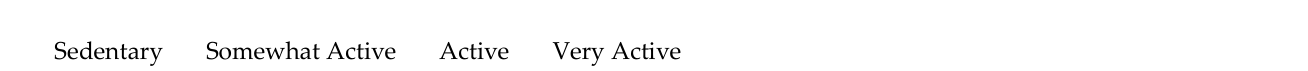
Does your job require you to be: Sedentary, Somewhat Active, Active, Very Active? Circle those that apply.
Please answer yes or no to the following questions

Please answer yes or no to the following questions: Is it hard for you to gain weight? Can you eat a lot and still not gain weight? Do you gain or lose weight according to your fluctuations in activity and food consumption? Is it hard for you to lose weight? Do you gain weight if you're not careful about food intake?
Current Nutritional Consumption

Please list the foods, beverages, supplements etc that you take on the average day. Time / Qty / Food-Beverage-Supplement.
Food Likes / Dislikes / Restrictions

Please list the foods you prefer to eat. Please list the foods you DO NOT prefer to eat. Please list any foods that you must restrict for any reason i.e. medical etc. Have you ever been told to follow a specific nutritional plan in the past? If so, please indicate the reason and the type of plan and who had provided it for you.
SIGN, Signature and Date

SIGN: Signature and Date.
More rules for Personal Training Client Health History Form
Your answers to these questions will be discussed with you prior to your session.
Sources
[1] Personal Training Client Health History Form (the served file; no issuer file found) (the Official source link on this page).
