


Form CMS-700 at a glance
What it is: Form CMS-700 is the Plan of Treatment for Outpatient Rehabilitation (complete for initial claims only) of the Centers for Medicare & Medicaid Services.
Who signs: Enter the signature (or name) and the professional designation of the professional establishing the plan of treatment. If the form CMS-700 is used for certification, the physician enters his/her signature.
A filled-in Form CMS-700 example: a therapist completes the plan of treatment
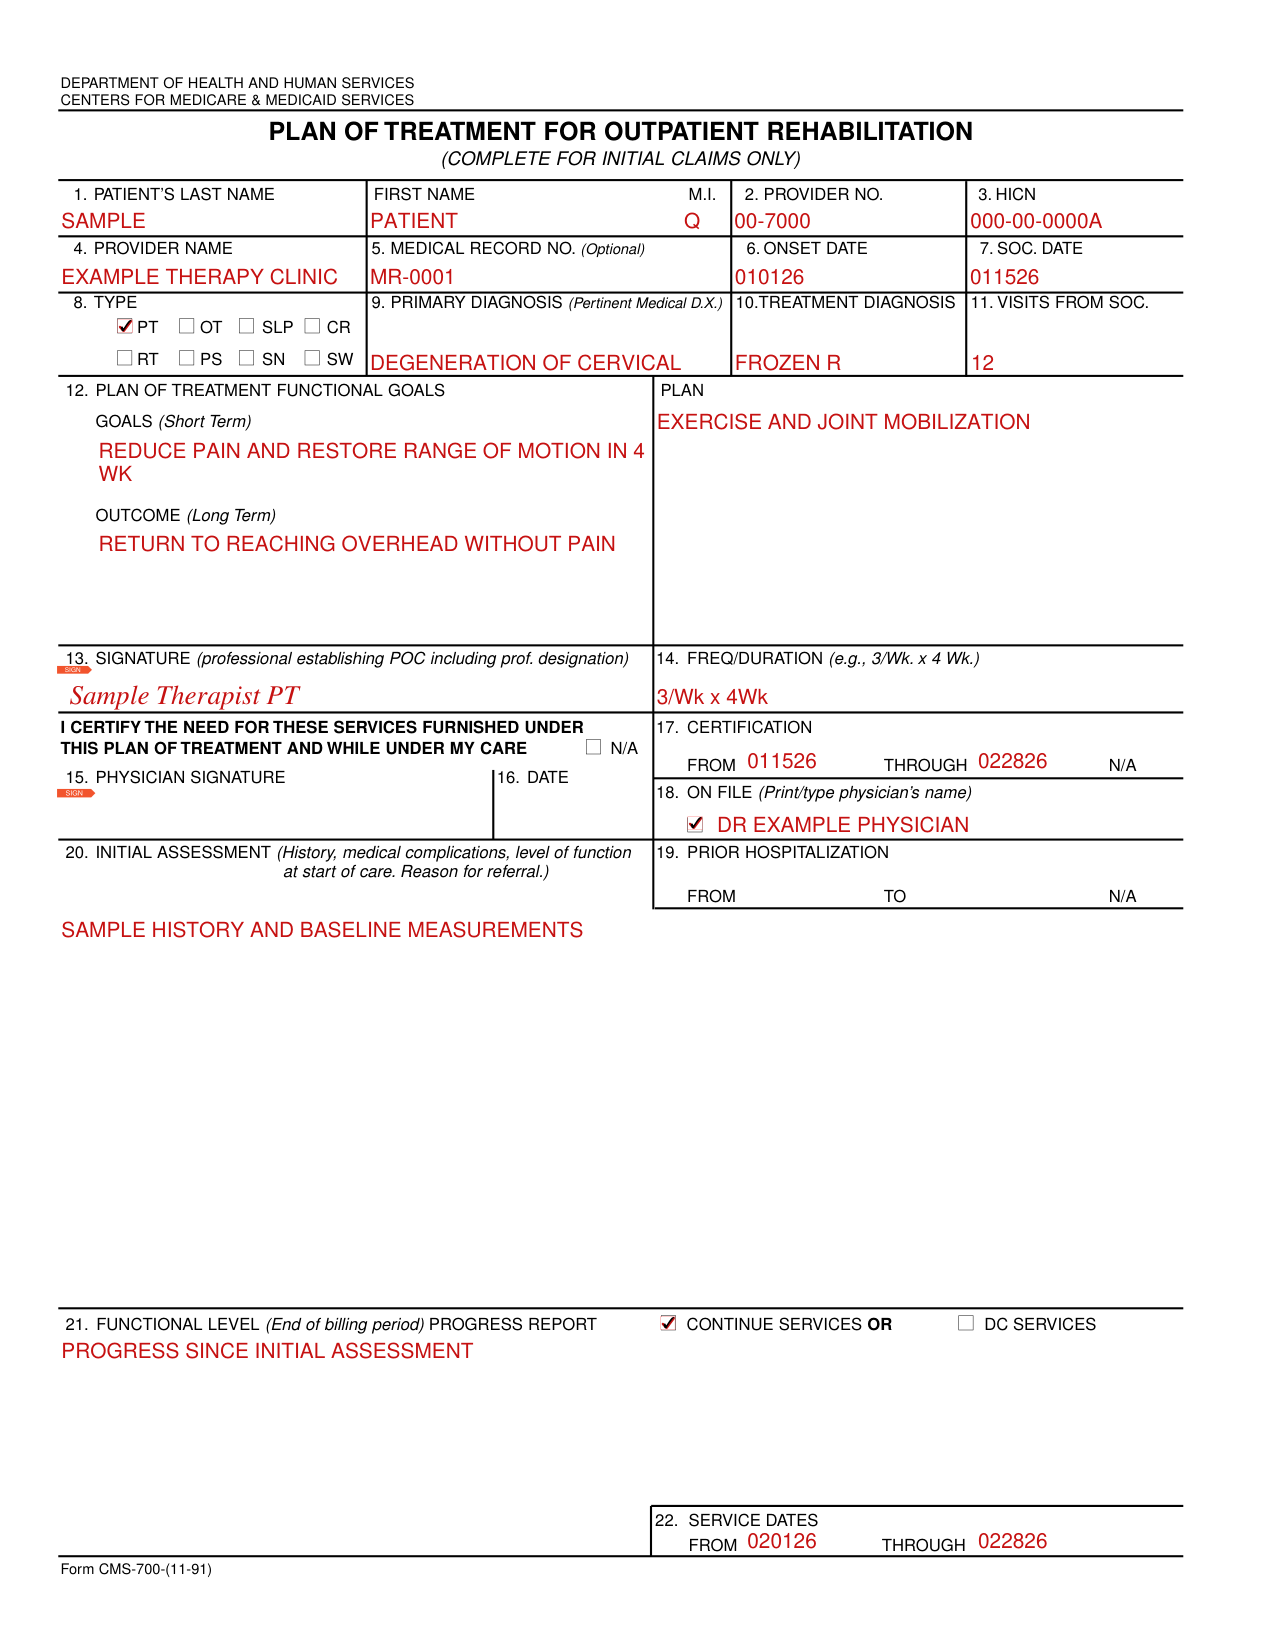
How to fill out Form CMS-700, box by box
Patient and provider
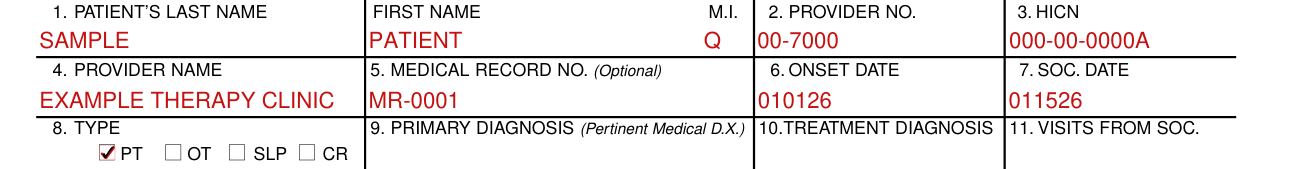
Enter the patient's last name, first name and middle initial as shown on the health insurance Medicare card.
Enter the number issued by Medicare to the billing provider (i.e., 00-7000).
Enter the patient's health insurance number as shown on the health insurance Medicare card, certification award, utilization notice, temporary eligibility notice, or as reported by SSO.
Enter the name of the Medicare billing provider.
Medical Record No. is optional: enter the patient's medical/ clinical record number used by the billing provider.
Onset and start of care dates

Enter the date of onset for the patient's primary medical diagnosis, if it is a new diagnosis, or the date of the most recent exacerbation of a previous diagnosis. If the exact date is not known enter 01 for the day (i.e., 120191).
SOC (start of care) Date: enter the date services began at the billing provider (the date of the first Medicare billable visit which remains the same on subsequent claims until discharge or denial corresponds to occurrence code 35 for PT, 44 for OT, 45 for SLP and 46 for CR on the UB-92).
Type, diagnosis and visits

8. TYPE 9. PRIMARY DIAGNOSIS (Pertinent Medical D.X.) 10.TREATMENT DIAGNOSIS 11. VISITS FROM SOC. PT OT SLP CR RT PS SN SW
Check the type therapy billed; i.e., physical therapy (PT), occupational therapy (OT), speech-language pathology (SLP), cardiac rehabilitation (CR), respiratory therapy (RT), psychological services (PS), skilled nursing services (SN), or social services (SW).
Enter the pertinent written medical diagnosis resulting in the therapy disorder and relating to 50% or more of effort in the plan of treatment.
Enter the written treatment diagnosis for which services are rendered. If the same as the primary DX enter SAME.
Enter the cumulative total visits (sessions) completed since services were started at the billing provider for the diagnosis treated, through the last visit on this bill.
Plan of treatment and functional goals
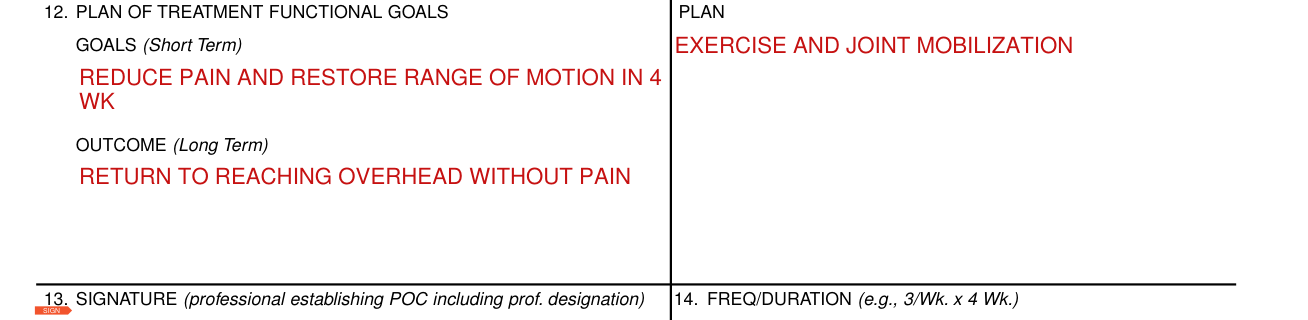
Enter brief current plan of treatment goals for the patient for this billing period.
Enter the major short-term goals to reach overall long-term outcome. Enter the major plan of treatment to reach stated goals and outcome.
Estimate time-frames to reach goals, when possible.
Signature and frequency of treatment
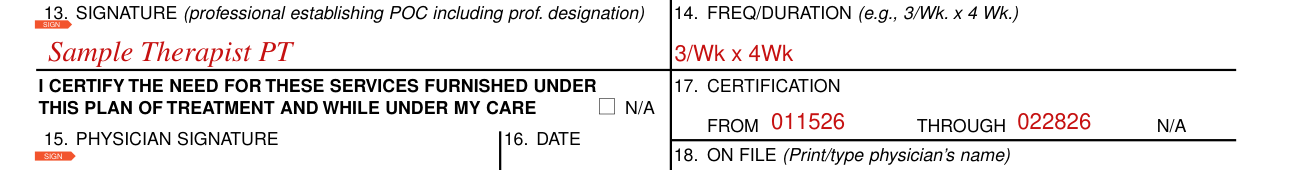
Enter the signature (or name) and the professional designation of the professional establishing the plan of treatment.
Enter the current frequency and duration of your treatment; e.g., 3 times per week for 4 weeks is entered 3/Wk x 4Wk.
Physician certification
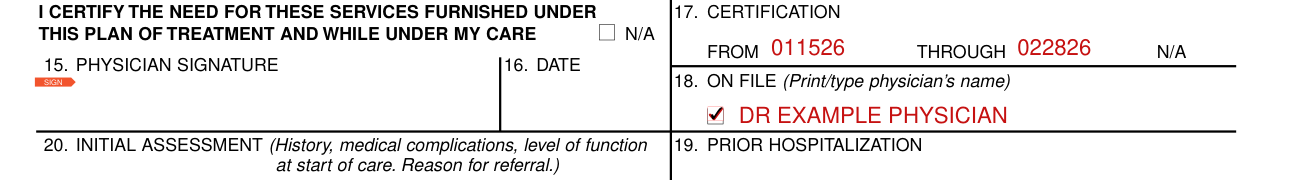
If the form CMS-700 is used for certification, the physician enters his/her signature.
If certification is required and the form is not being used for certification, check the ON FILE box in item 18.
If the certification is not required for the type service rendered, check the N/A box.
Enter the date of the physician's signature only if the form is used for certification.
Enter the inclusive dates of the certification, even if the ON FILE box is checked in item 18. Check the N/A box if certification is not required.
Enter the typed/printed name of the physician who certified the plan of treatment that is on file at the billing provider.
If certification is not required for the type of service checked in item 8, type/print the name of the physician who referred or ordered the service, but do not check the ON FILE box.
Prior hospitalization and initial assessment
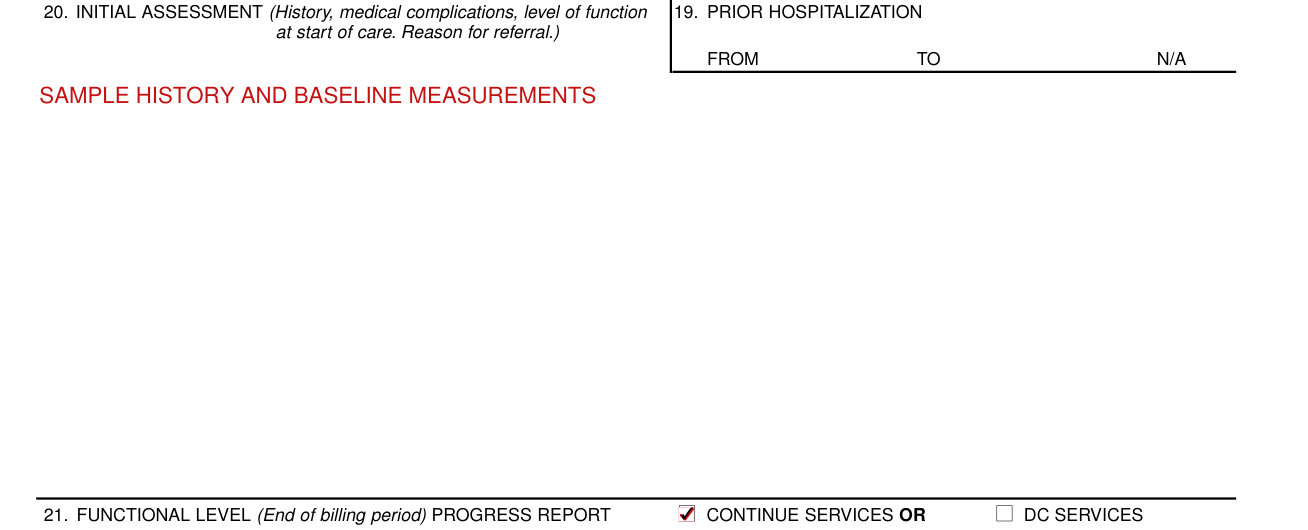
Enter the inclusive dates of recent hospitalization (1st to DC day) pertinent to the patient's current plan of treatment. Enter N/A if the hospital stay does not relate to the rehabilitation being rendered.
Enter only current relevant history from records or patient interview.
Enter the major functional limitations stated, if possible, in objective measurable terms.
Include only relevant surgical procedures, prior hospitalization and/or therapy for the same condition. Include only pertinent baseline tests and measurements from which to judge future progress or lack of progress.
Functional level and service dates
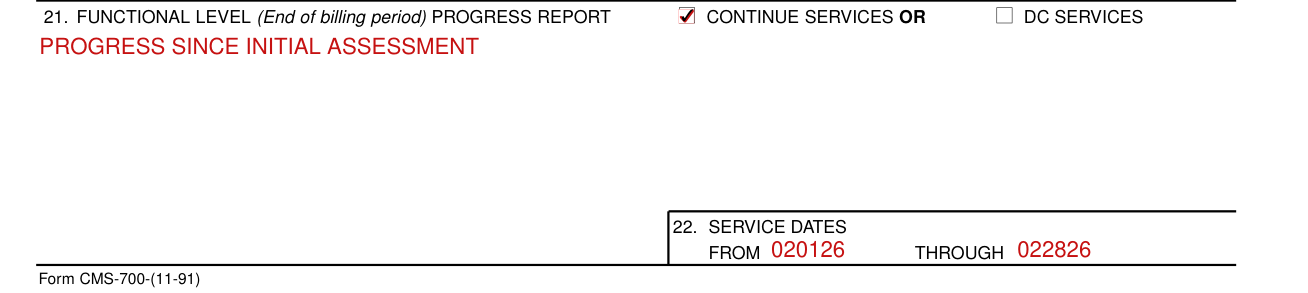
21. FUNCTIONAL LEVEL (End of billing period) PROGRESS REPORT CONTINUE SERVICES OR DC SERVICES
Enter the pertinent progress made and functional levels obtained at the end of the billing period compared to levels shown on initial assessment.
Use objective terminology. Date progress when function can be consistently performed.
When only a few visits have been made, enter a note indicating the training/treatment rendered and the patient's response if there is no change in function.
Enter the From and Through dates which represent this billing period (should be monthly).
DO NOT use 00 in the date. Example: 01 08 91 for January 8, 1991.
Sources
[1] Form CMS-700 (11-91), Plan of Treatment for Outpatient Rehabilitation, Centers for Medicare & Medicaid Services (the Official source link on this page).