
How to Fill Out Form CMS-95

Form CMS-95 at a glance

What it is: CMS-95 is the Illinois Department of Central Management Services Physician's Statement Authorization for Disability Leave and Return to Work.

Who signs: The Attending Physician signs on the Attending Physician Signature line and fills in Degree and Date.

To employees: you are responsible for having this form completed and returned to the appropriate person within your agency within the time limits established by your agency.

Your failure to comply may result in termination of your disability leave.

A filled-in Form CMS-95 example: a physician completes the statement for a state employee

Form CMS-95 example filled out, example: a physician completes the statement for a state employee
A physician completes the Physician's Statement for a state employee's disability leave. The patient was last examined on March 2, 2026 and cannot yet do any occupation. The picture shows the completed form, and none of its entries is real. The patient is seen weekly, with the first visit on February 10, 2026 and the last on March 2, 2026, so Weekly is ticked and Monthly and Other stay empty in 2. DATES OF TREATMENT. Treatment will improve function, so Yes is ticked and specified in 3. TREATMENT. The patient was hospital confined from February 12 through February 16, 2026, has Improved and is House Confined now. Standing and Lifting are the limitations, so the other boxes and the Other (Please specify) line stay empty in 5. LIMITATION. The patient is in Class 5, so the Remarks line stays empty in 6. PHYSICAL IMPAIRMENT. The patient is temporarily totally disabled, so nothing goes in (b) of 7. EXTENT OF DISABILITY because the answer to (a) is Yes, and nothing goes in (e) because the answer to (d) is No. The patient is expected to resume work about April 15, 2026. The physician has no remark to add, so 8. REMARKS stays empty, and the physician signs on March 2, 2026.

How to fill out Form CMS-95, box by box

Name of Patient (full), Present Address and Employed by State of Illinois
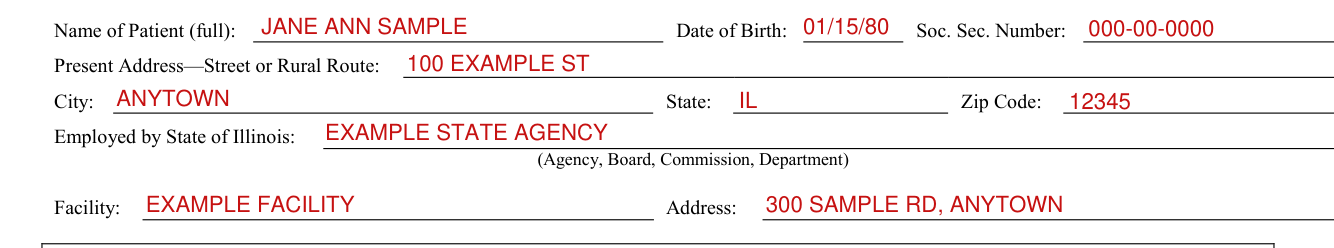
Form CMS-95 example filled out, name of Patient (full), Present Address and Employed by State of Illinois

Enter the Name of Patient (full), Date of Birth and Soc. Sec. Number.

Enter the Present Address-Street or Rural Route.

Enter the City, State and Zip Code.

Enter the (Agency, Board, Commission, Department) under Employed by State of Illinois.

Enter the Facility and the Address.

1. DIAGNOSIS (including any complications)
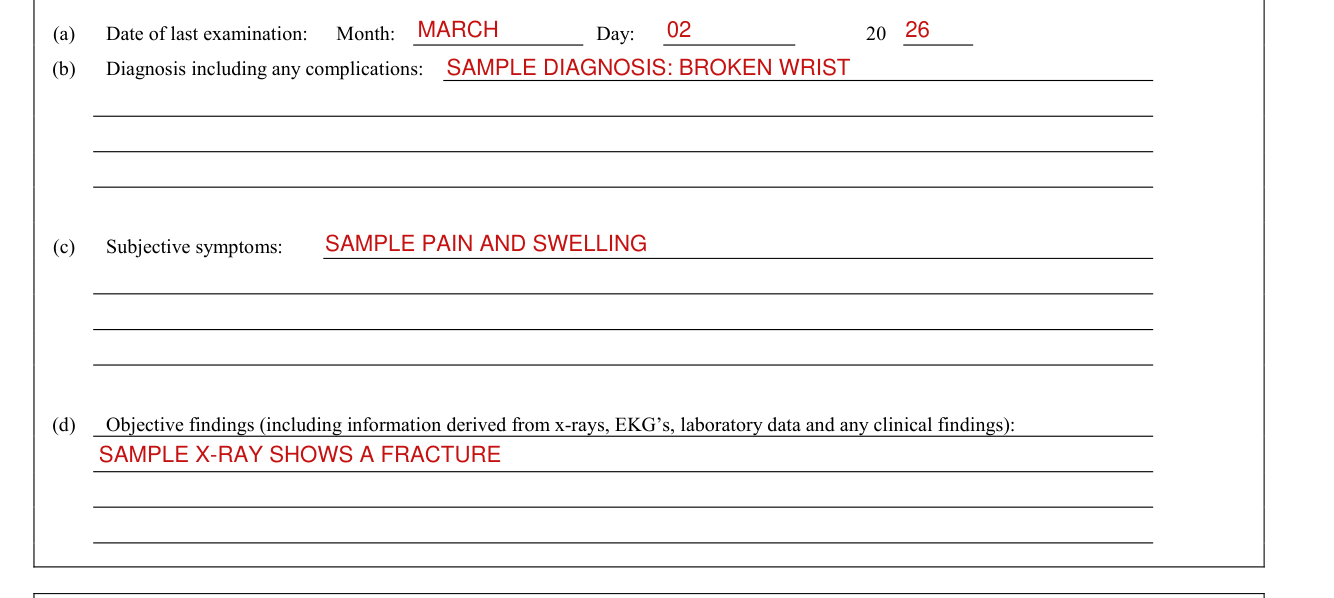
Form CMS-95 example filled out, 1. DIAGNOSIS (including any complications)

In (a), fill in the Date of last examination: Month, Day and 20.

In (b), enter the Diagnosis including any complications.

In (c), enter the Subjective symptoms.

In (d), enter the Objective findings (including information derived from x-rays, EKG's, laboratory data and any clinical findings).

2. DATES OF TREATMENT
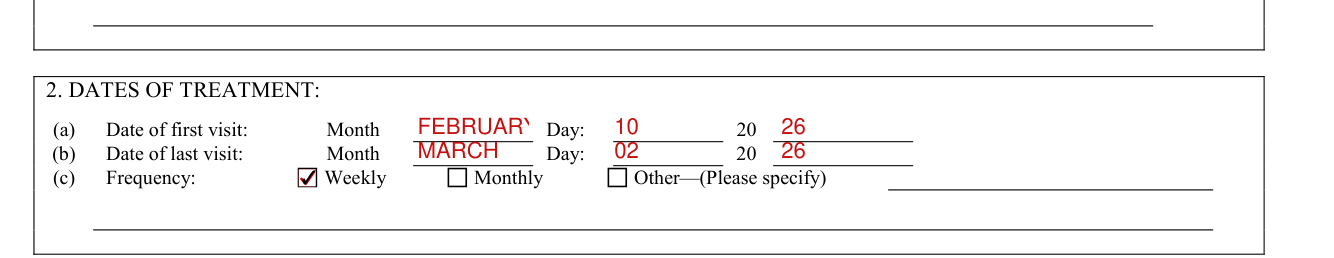
Form CMS-95 example filled out, 2. DATES OF TREATMENT

In (a), fill in the Date of first visit: Month Day 20, and in (b) the Date of last visit: Month Day 20.

In (c), mark the Frequency: Weekly, Monthly or Other-(Please specify).

3. TREATMENT
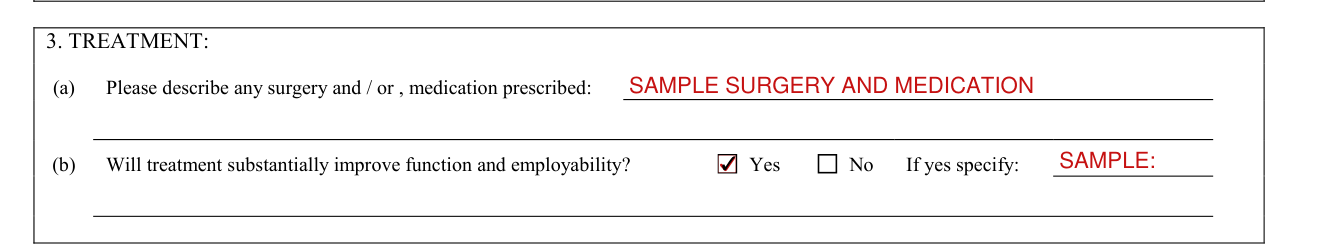
Form CMS-95 example filled out, 3. TREATMENT

In (a), describe any surgery and / or medication prescribed.

In (b), mark Yes or No for: Will treatment substantially improve function and employability? If yes, specify.

4. PROGRESS: The patient has, The patient is

Form CMS-95 example filled out, 4. PROGRESS: The patient has, The patient is

Check the appropriate box provided under 4. PROGRESS.

In (a), check what The patient has: Recovered, Improved, Remained Unchanged or Retrogressed.

In (b), check what The patient is: Ambulatory, House Confined or Bed Confined.

Has the patient been hospital confined because of current condition?

Form CMS-95 example filled out, has the patient been hospital confined because of current condition?

In (c), mark Yes or No for: Has the patient been hospital confined because of current condition?

If yes, give name and address of hospital and fill in Confined from: Month Day 20 Through Month Day 20.

5. LIMITATION

Form CMS-95 example filled out, 5. LIMITATION

5. LIMITATION: If there is a limitation, check the appropriate box and describe: Standing, Climbing, Bending, Use of Hands, Stooping, Lifting, Psychological or Other (Please specify).

6. PHYSICAL IMPAIRMENT

Form CMS-95 example filled out, 6. PHYSICAL IMPAIRMENT

Check a box under 6. PHYSICAL IMPAIRMENT (*As defined in Federal Dictionary of Occupational Titles).

Class 1: No limitation of functional capacity; capable of heavy work * No restrictions (0-10%).

Class 2: Medium manual activity * (15%-30%).

Class 3: Slight limitation of functional capacity; capable of light work* (35%-55%).

Class 4: Moderate limitation of functional capacity; capable of clerical / administrative (sedentary*) activity (60%-70%).

Class 5: Severe limitation of functional capacity; incapable of minimal (sedentary*) activity (75%-100%).

7. EXTENT OF DISABILITY
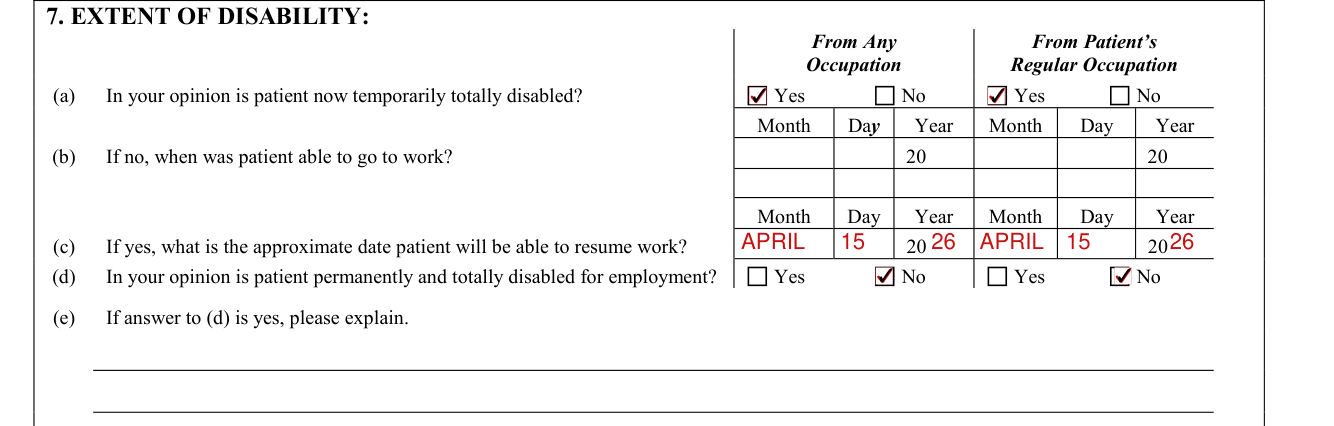
Form CMS-95 example filled out, 7. EXTENT OF DISABILITY

In (a) and (d), mark Yes or No From Any Occupation and From Patient's Regular Occupation: (a) In your opinion is patient now temporarily totally disabled? (d) In your opinion is patient permanently and totally disabled for employment?

In (b), If no, when was patient able to go to work? In (c), If yes, what is the approximate date patient will be able to resume work? Fill in Month, Day and Year From Any Occupation and From Patient's Regular Occupation.

If answer to (d) is yes, please explain.

8. REMARKS

Form CMS-95 example filled out, 8. REMARKS

Under 8. REMARKS, enter any remarks.

Attending Physician Signature and Information
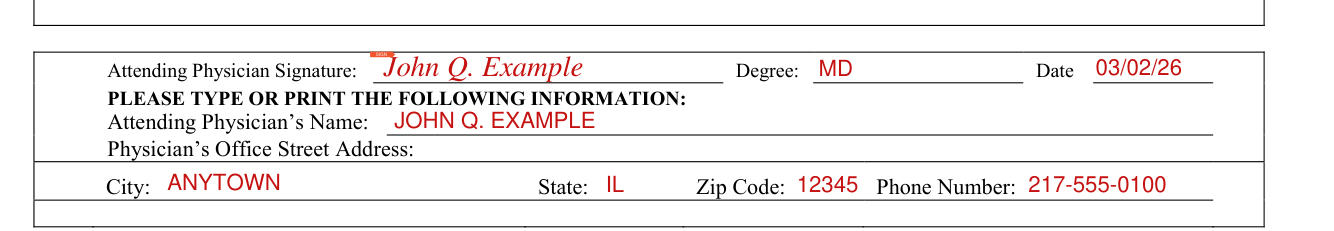
Form CMS-95 example filled out, attending Physician Signature and Information

Type or print the Attending Physician's Name, Physician's Office Street Address, City, State, Zip Code and Phone Number.

More rules for Form CMS-95

Comprehensive medical information is required in order to evaluate the employee's claim for a disability leave of absence or subsequent return to work.

This state agency is requesting disclosure of information that is necessary to accomplish the statutory purpose as outlined under 20 ILCS 415/8c(2). Disclosure of this information is VOLUNTARY.

Sources

[1] Form CMS-95 (6/00), Illinois Department of Central Management Services (the Official source link on this page).

CMS 95 Form PDF Details

The CMS 95 form is the official physician's statement required by the Illinois Department of Central Management Services. This document records an employee's medical condition during a disability leave of absence. Physicians, state employees, and HR administrators all use it to coordinate the leave approval process.

What the CMS 95 form covers

The form collects medical and administrative information across five main areas.

Diagnosis and treatment. The attending physician records the diagnosis, the dates of treatment, and how often the patient receives care. They also list any surgical procedures and state whether current treatment will change the patient's ability to perform work duties.

Patient progress. The physician checks boxes to show whether the patient has recovered, improved, stayed the same, or declined. The form also asks whether the patient is ambulatory, house-confined, or bed-confined, and whether the patient was hospitalized during the period covered.

Physical impairment class. This form uses a five-class rating system. Class I indicates slight limitation of functional capacity. Class V indicates severe limitation that prevents any productive work. The physician selects the class that best fits the patient's current condition and adds remarks as needed.

Extent of disability. This section records whether the patient is disabled from their regular occupation or from any occupation at all. The physician also provides an estimated date when the patient may be able to return to work, if applicable.

Physician certification. The attending physician prints their name, enters their professional degree, signs the form, and records the date of completion. Documents submitted without a physician signature will not be accepted for processing.

Who needs to file the CMS 95 form

Illinois state employees who apply for disability leave must have their attending physician complete this document. The employer then submits it to the Illinois Department of Central Management Services as part of the leave approval package. Late or incomplete forms can delay disability benefit payments, so confirm submission deadlines with your HR department before sending.

Depending on your situation, you may also need a FMLA leave form for federally protected medical leave or a leave of absence request form to formally document the absence with your employer. Once your physician clears you to return, a return-to-work release form may also be required to complete the process.

QuestionAnswer
Form Name CMS 95 Form
Form Type Physician's Statement
Issued By Illinois Department of Central Management Services
Purpose Disability leave documentation for Illinois state employees
Who Files Attending physician, on behalf of the employee
Form Length 2 pages
Fillable? No
Fillable fields 0
Avg. time to fill out 30 sec
Other names il cms 95, illinois authorization work, illinois cms 95 form, state of illinois handicapped form