


DA Form 3947 at a glance
What it is: DA Form 3947 is the Medical Evaluation Board proceedings form, for use under AR 635-40.
Who signs: Service Member, box 17: enter the typed name, grade (17. a), the signature (17. b), the date (17. c, YYYYMMDD). Each provider signs in 13. b, 14. b or 15. b, under the typed name, grade and specialty of provider. The approval authority signs in 25. b, under the typed name, grade and title of approval authority, and dates it in 25. c.
The form is used to document the proceedings of a Medical Evaluation Board (MEB).
By direction of the appointing authority, the board convened to evaluate the Service Member identified.
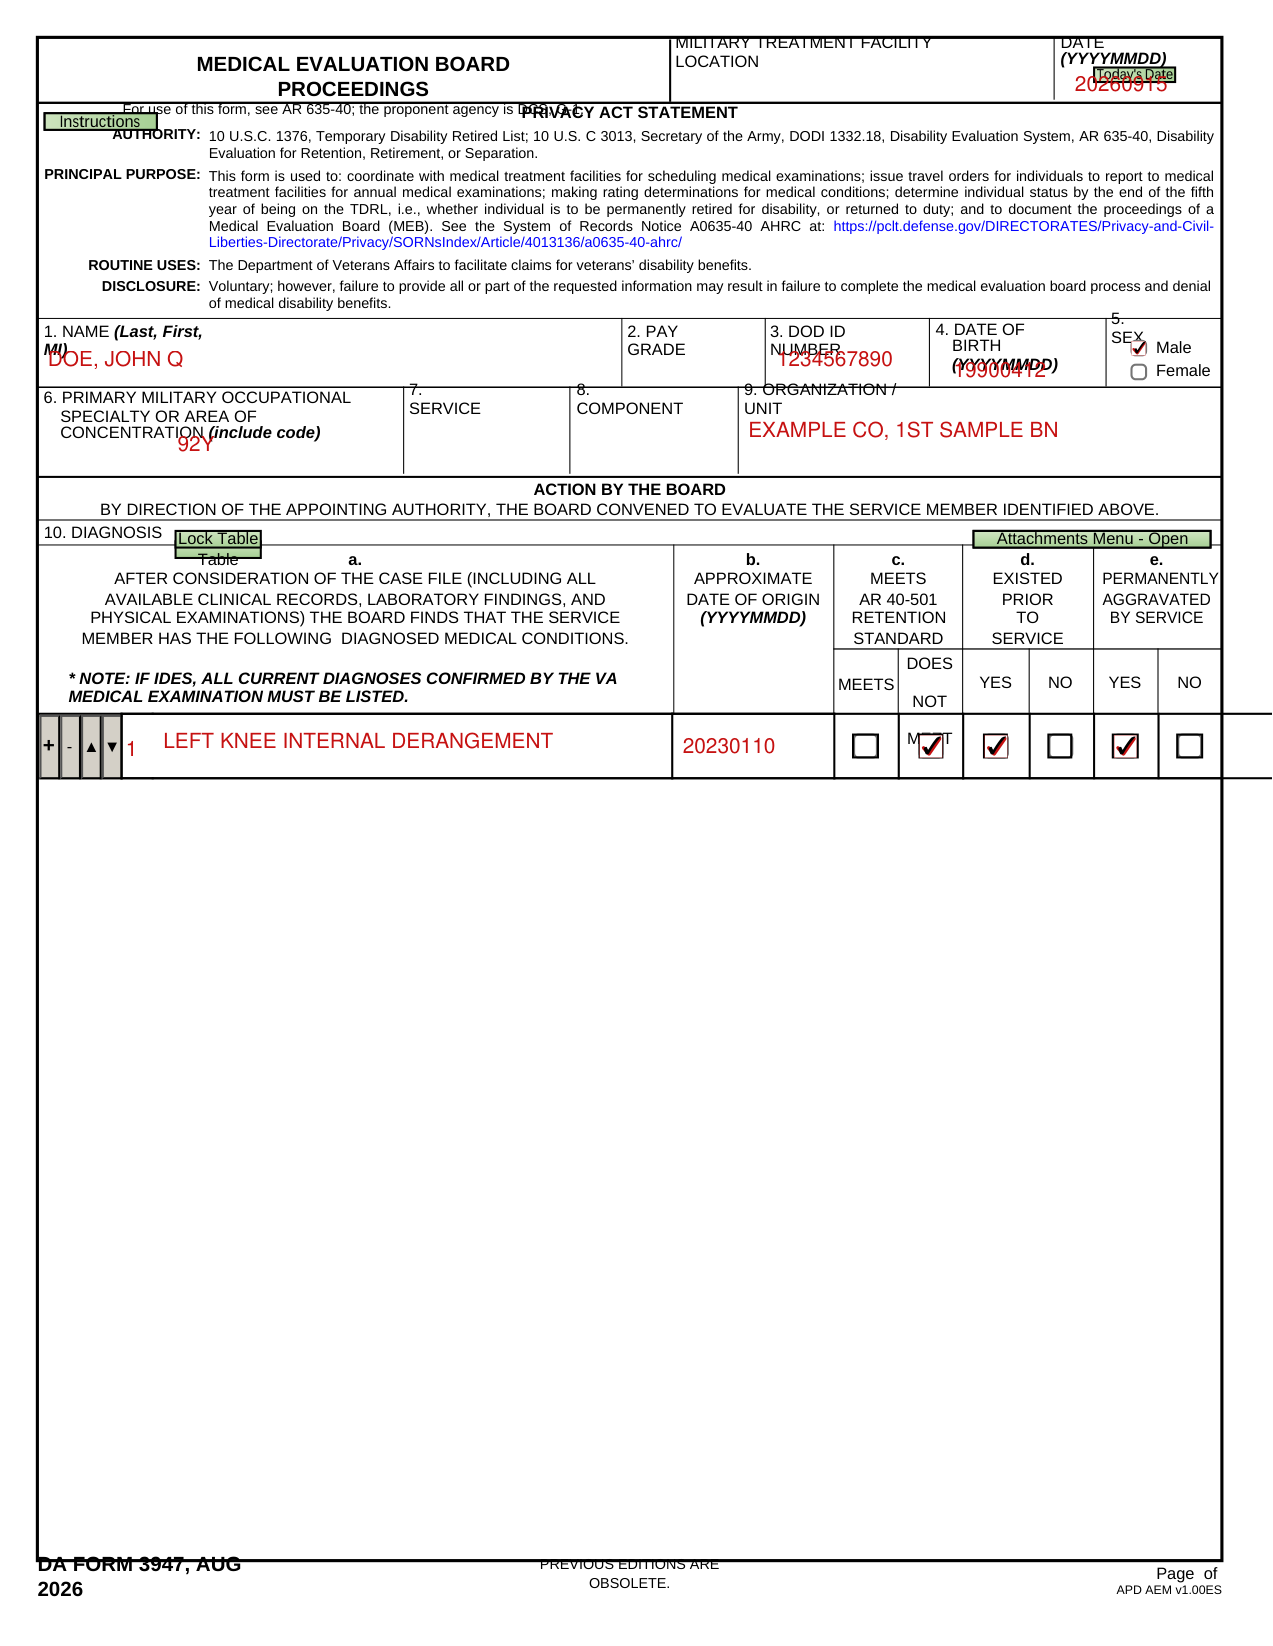
A filled-in DA Form 3947 example: a board lists one soldier's condition
How to fill out DA Form 3947, box by box
Date, facility and boxes 1 to 9
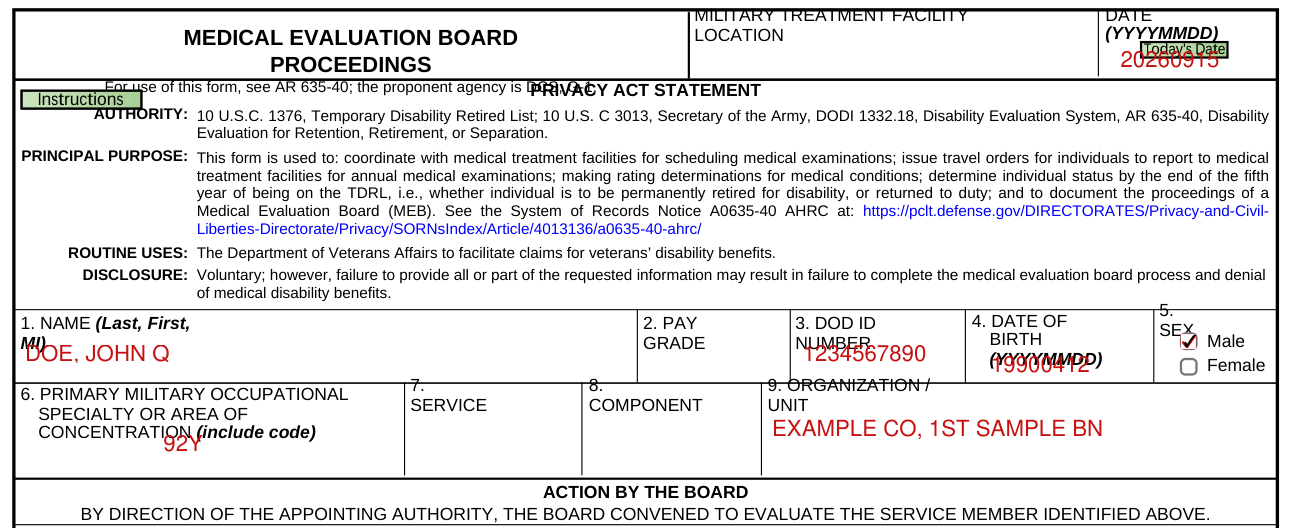
Enter today's date (YYYYMMDD) and the military treatment facility location at the top.
In box 1, enter the name as Last, First, MI.
Enter the DOD ID number in box 3 and the pay grade in box 2.
In box 4, enter the date of birth as YYYYMMDD.
In box 5, mark Male or Female.
In box 6, enter the primary military occupational specialty or area of concentration (include code).
Boxes 7, 8 and 9: service, component, organization / unit.
Box 10, the diagnosis

In box 10 a, list the diagnosed medical conditions the board finds the service member has.
If IDES, all current diagnoses confirmed by the VA medical examination must be listed.
In b, enter the approximate date of origin (YYYYMMDD).
In c, meets AR 40-501 retention standard: mark Meets or Does Not Meet.
In d, mark yes or no for existed prior to service.
In e, mark yes or no for permanently aggravated by service.
Boxes 11 and 12, the board
In box 11a, if no single diagnosis falls below medical retention standards, do any of the conditions listed in box 10 collectively cause the Soldier to fall below medical retention standards, per AR 40-501? Mark No or Yes, condition(s) listed in box 11b.
In 11. b, list numbers from block 11 for diagnosed conditions that collectively cause the Soldier to fall below retention standards.
In box 12, the board recommends that the Service Member be: referred to a Physical Evaluation Board, returned to duty, returned to duty with limitations, or referred to the Air Force or Navy reviewing authority.
Boxes 13 to 15, the providers
In boxes 13, 14 and 15, each provider enters the typed name, grade and specialty of provider (a) and the signature (b).
Boxes 16 and 17, Service Member action
Service Member action, 16: I have been informed of the decision made by the Medical Evaluation Board (MEB).
I understand that I have 5 calendar days to make an election on my MEB.
I have been advised to seek legal counseling from the Soldiers' MEB Counsel Office or counsel of my choice at no expense to the government.
I have received a copy of the DA Form 3947 (MEB Proceedings), Narrative Summary (NARSUM), DA Form 3349 (Physical Profile), and DA Form 7652 (Disability Evaluation System Commander's Performance and Functional Statement).
I have been Informed of my right to an Impartial Medical Review (IMR) and opportunity to submit a written rebuttal to the MEB.
In regard to issues relating to fitness for duty and disability compensation, I understand that the Physical Evaluation Board will consider and review only those diagnosed conditions listed on the DA Form 3947.
All documentation of military and civilian medical care in my possession has been provided to the PEBLO for inclusion in this MEB.
Service Member, box 17: enter the typed name, grade (17. a), the signature (17. b), the date (17. c, YYYYMMDD).
Boxes 18 and 19, I concur or do not concur
18. I CONCUR with the board's decision and DO NOT request an Impartial Medical Review (IMR) and DO NOT wish to submit a written rebuttal; or I REQUEST an IMR; or I DO NOT CONCUR with the board's decision and DO NOT request an IMR; or I DO NOT CONCUR with the MEB, and I wish to submit a rebuttal.
I understand that I have 7 calendar days to submit a written rebuttal. Enter the date rebuttal submitted (if applicable) as YYYYMMDD.
In box 19, enter the typed name, grade (19. a), the signature (19. b) and the date (19. c, YYYYMMDD).
Boxes 20 and 21, Impartial Medical Review actions
Impartial Medical Review actions, 20: all medical documentation pertaining to the MEB has been reviewed to ensure the MEB adequately reflects the complete spectrum of injuries and illnesses.
In box 21, enter the typed name and grade of the IMR reviewer (21. a), the date the Service Member was contacted (21. b) and the date IMR was completed (21. c), each date as YYYYMMDD.
Boxes 22 and 23, Service Member review action
Service Member review action, 22: I have discussed the Impartial Medical Review (IMR) findings with my assigned IMR provider. I CONCUR with the board's decision. I DO NOT CONCUR with the board's decision, and I am submitting a rebuttal.
In box 23, enter the typed name, grade (23. a), the signature (23. b), the date (23. c, YYYYMMDD) and the date rebuttal submitted (if applicable).
Boxes 26 and 27, final Service Member review and continuation
Final Service Member review action, 26: I have reviewed the approval authority's final decision and addendum (ifapplicable).
In box 26, enter the typed name, grade (26. a), the signature (26. b) and the date review finalized (26. c, YYYYMMDD).
In box 27, continuation, identify by item number.
More rules for DA Form 3947
Disclosure: voluntary; however, failure to provide all or part of the requested information may result in failure to complete the medical evaluation board process and denial of medical disability benefits.
Sources
[1] DA Form 3947 (AUG 2026), Medical Evaluation Board Proceedings, Department of the Army (the Official source link on this page).