

Form DCH-3877 at a glance
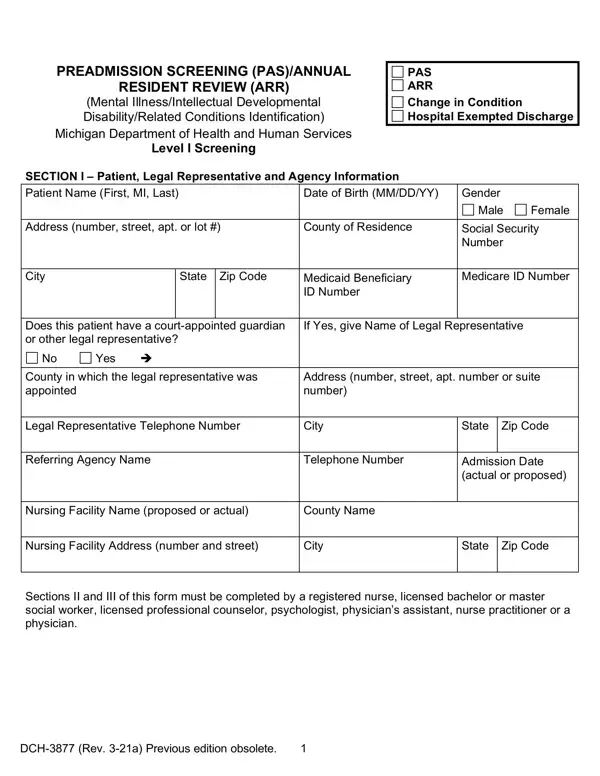
What it is: DCH-3877 is the Preadmission Screening (PAS)/Annual Resident Review (ARR) of the Michigan Department of Health and Human Services.
Who signs: Enter the Clinician Signature, Date, Name (type or print), Degree/License and Telephone Number.
3 Instructions for Completing Level I Screening: This form is used to identify prospective and current nursing facility residents who meet the criteria for possible mental illness or intellectual/developmental disability, or a related condition and who may be in need of mental health services.
Sections 3 and 4 of this form must be completed by a registered nurse, licensed bachelor, or master social worker, licensed professional counselor, psychologist, physician's assistant, nurse practitioner or a physician.
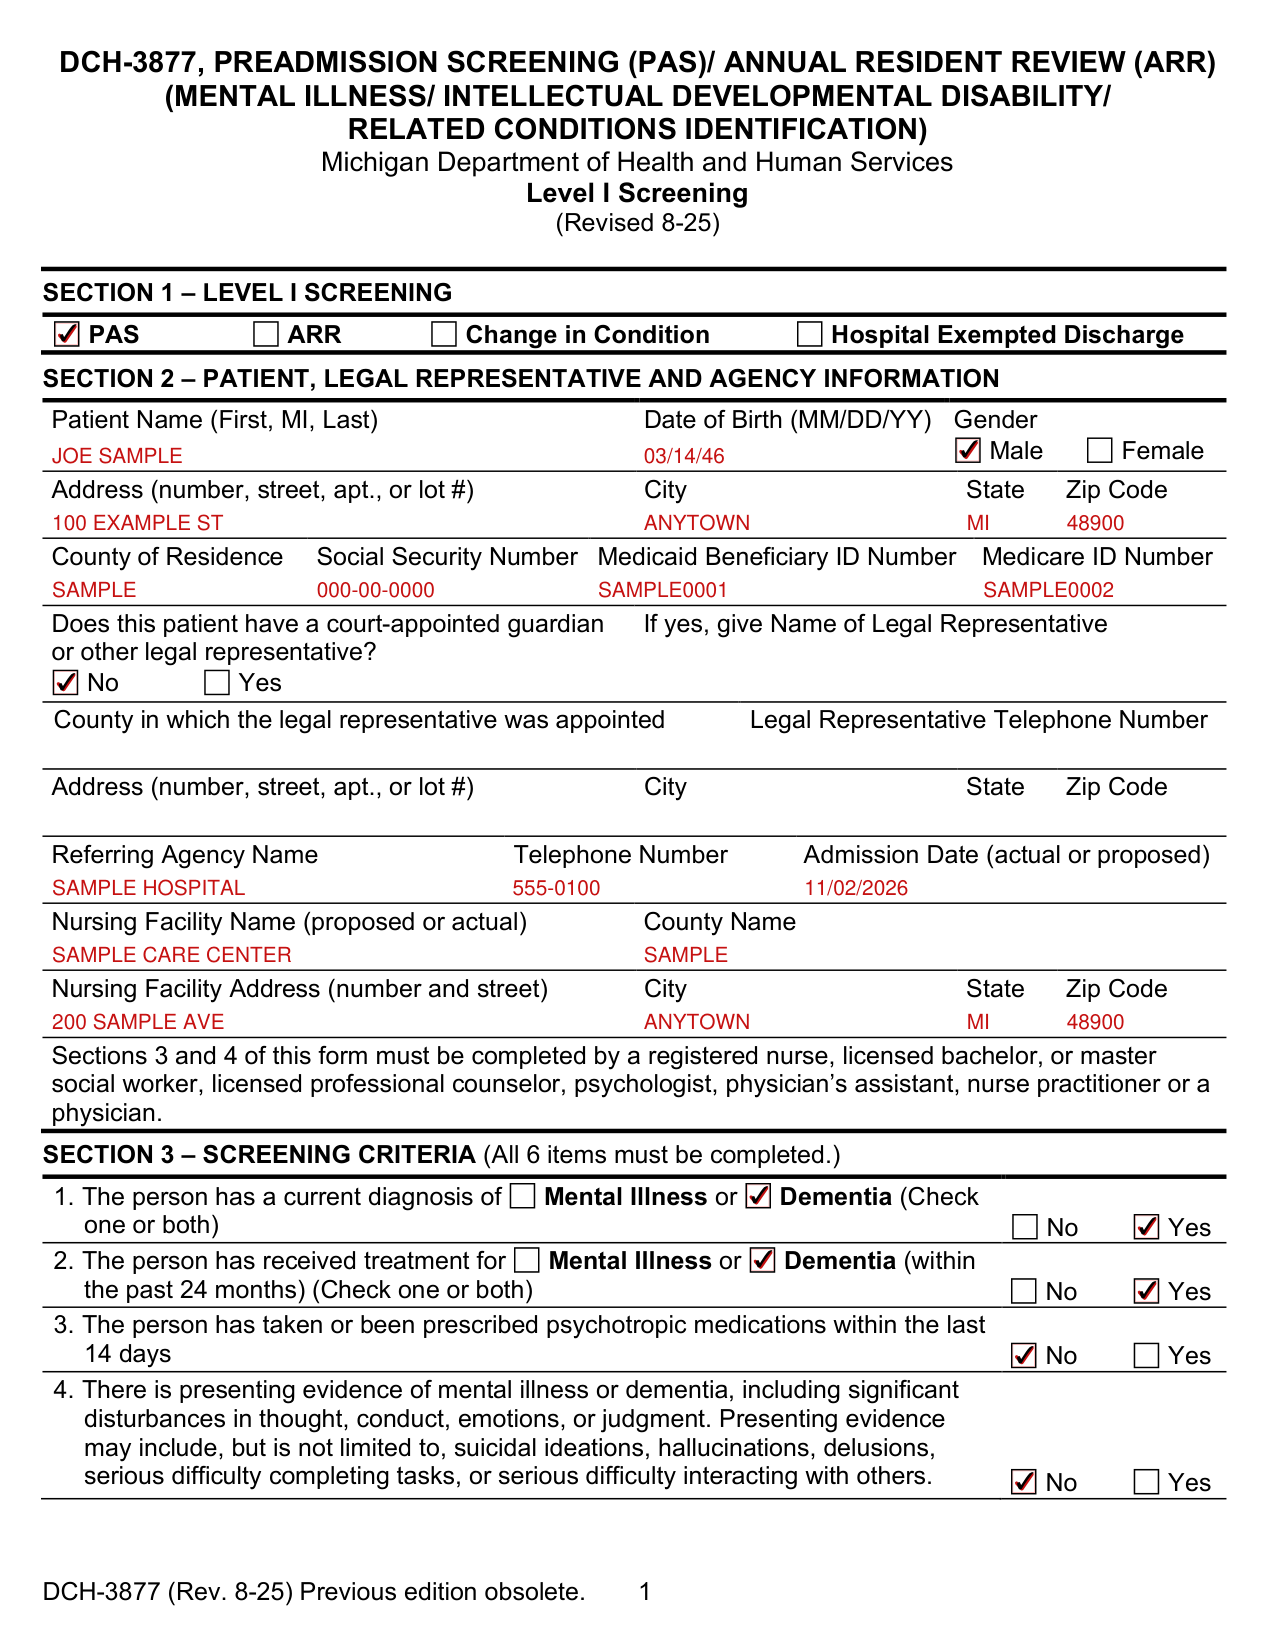
A filled-in Form DCH-3877 example: a nurse screens a patient before admission
How to fill out Form DCH-3877, box by box
Section 1 - Level I Screening
Check the appropriate box in SECTION 1 - LEVEL I SCREENING: PAS, ARR, Change in Condition or Hospital Exempted Discharge.
Annual Resident Review: This form must be completed by the nursing facility annually.
Change in Condition: This form must be completed by the nursing facility when there is a change in the individuals mental health status or needs.
Section 2 - Patient, Legal Representative and Agency Information
In SECTION 2, enter the Patient Name (First, MI, Last), Date of Birth (MM/DD/YY), Gender and Address (number, street, apt., or lot #).
Enter the City, State, Zip Code, County of Residence, Social Security Number, Medicaid Beneficiary ID Number and Medicare ID Number.
Does this patient have a court-appointed guardian or other legal representative? No Yes
If yes, give Name of Legal Representative, County in which the legal representative was appointed and Legal Representative Telephone Number.
Legal Representative Address (number, street, apt., or lot #), City, State and Zip Code.
Enter the Referring Agency Name, Telephone Number and Admission Date (actual or proposed).
Enter the Nursing Facility Name (proposed or actual), County Name, Nursing Facility Address (number and street), City, State and Zip Code.
Section 3 - Screening Criteria
SECTION 3 - SCREENING CRITERIA (All 6 items must be completed.) 1. The person has a current diagnosis of Mental Illness or Dementia (Check one or both)
If you checked Yes to items 1 and/or 2, check the word Mental Illness and/or Dementia.
Current Diagnosis means that a clinician has established a diagnosis of a mental disorder within the past 24 months. Do NOT mark Yes for an individual cited as having a diagnosis "by history" only.
No Yes 2. The person has received treatment for Mental Illness or Dementia (within the past 24 months) (Check one or both)
Receipt of treatment for mental illness or dementia within the past 24 months means any of the following: inpatient psychiatric hospitalization; outpatient services such as psychotherapy, day program, or mental health case management; or referral for psychiatric consultation, evaluation, or prescription of psychopharmacological medications.
3. The person has taken or been prescribed psychotropic medications within the last 14 days
Psychotropic medications are medications that affect how the brain works and causes changes in mood, awareness, thoughts, feelings, or behavior. Examples include antipsychotics, mood stabilizers, stimulants, and sedatives.
4. There is presenting evidence of mental illness or dementia, including significant disturbances in thought, conduct, emotions, or judgment. Presenting evidence may include, but is not limited to, suicidal ideations, hallucinations, delusions, serious difficulty completing tasks, or serious difficulty interacting with others.
5. The person has a diagnosis of an intellectual/developmental disability or a related condition including, but not limited to, epilepsy, autism, or cerebral palsy and this diagnosis manifested before the age of 22.
6. There is presenting evidence of deficits in intellectual functioning or adaptive behavior which suggests that the person may have an intellectual/developmental disability or a related condition. These deficits appear to have manifested before the age of 22.
Explain any yes answers.
The person screened will require a comprehensive Level II OBRA evaluation if any of the Section 3 items are "Yes" UNLESS a physician, nurse practitioner or physician's assistant certifies on form DCH-3878 that the person meets at least one of the exemption criteria, or the CMHSP Coordinator determines a Level II is not needed.
When there are one or more "Yes" answers to items 1 - 6 under SECTION II, complete form DCH-3878, Mental Illness/Intellectual/Developmental Disability/Related Condition Exemption Criteria Certification only if the referring agency is seeking to establish exemption criteria for a dementia, state of coma, or hospital exempted discharge.
Section 4 - Clinician's Statement
SECTION 4 - CLINICIAN'S STATEMENT: I certify to the best of my knowledge that the above information is accurate.
Enter the Clinician Signature, Date, Name (type or print), Degree/License and Telephone Number.
More rules for Form DCH-3877
The nursing facility must retain the original in the patient record and provide a copy to the patient or legal representative.
COMPLETION: Is voluntary, however, if NOT completed, Medicaid will not reimburse the nursing facility.
Common questions about Form DCH-3877
Where do I file it?
Preadmission Screening or Hospital Exempted Discharge: The referral source completing the Level I Screening (DCH-3877) must complete and provide a copy to the proposed nursing facility prior to admission. If any answer to items 1 - 6 in SECTION 3 is "Yes", send ONE copy to the local Community Mental Health Services Program (CMHSP), with a copy of form DCH-3878 if an exemption is requested.
Sources
[1] Form DCH-3877 (Revised 8-25), Preadmission Screening (PAS)/Annual Resident Review (ARR), Michigan Department of Health and Human Services (the Official source link on this page).