

DD Form 2527 at a glance
What it is: The Statement of Personal Injury, Possible Third Party Liability is a Defense Health Agency form.
Where and when to file: Processing of your TRICARE claim will be suspended until you complete and return the form in the attached self-addressed envelope.
A filled-in DD Form 2527 example: a car crash reported by the injured patient

How to fill out DD Form 2527, box by box
Box 1, the sponsor's social security number

Enter the sponsor's social security number in Box 1, and mark one of Army, Navy, Air Force, Coast Guard, USPHS or NOAA.
Box 2, the injured patient
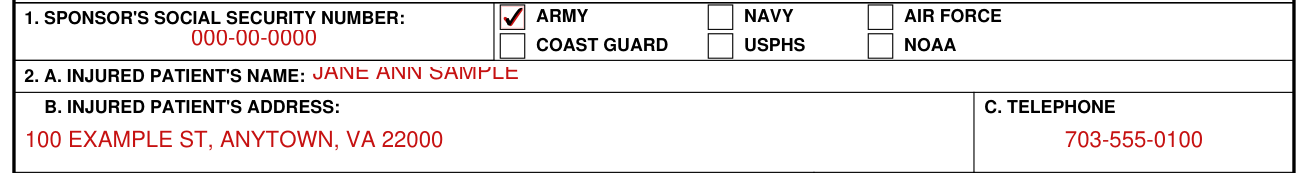
Enter the injured patient's name in Box 2 A, the injured patient's address in B and the telephone in C.
Boxes 3 and 4, when and where

Enter the date of the injury as YYYYMMDD and the approximate time of injury in Box 3.
Enter the locality and state where the injury occurred in Box 4.
Boxes 5 to 13, the type and cause of the injury
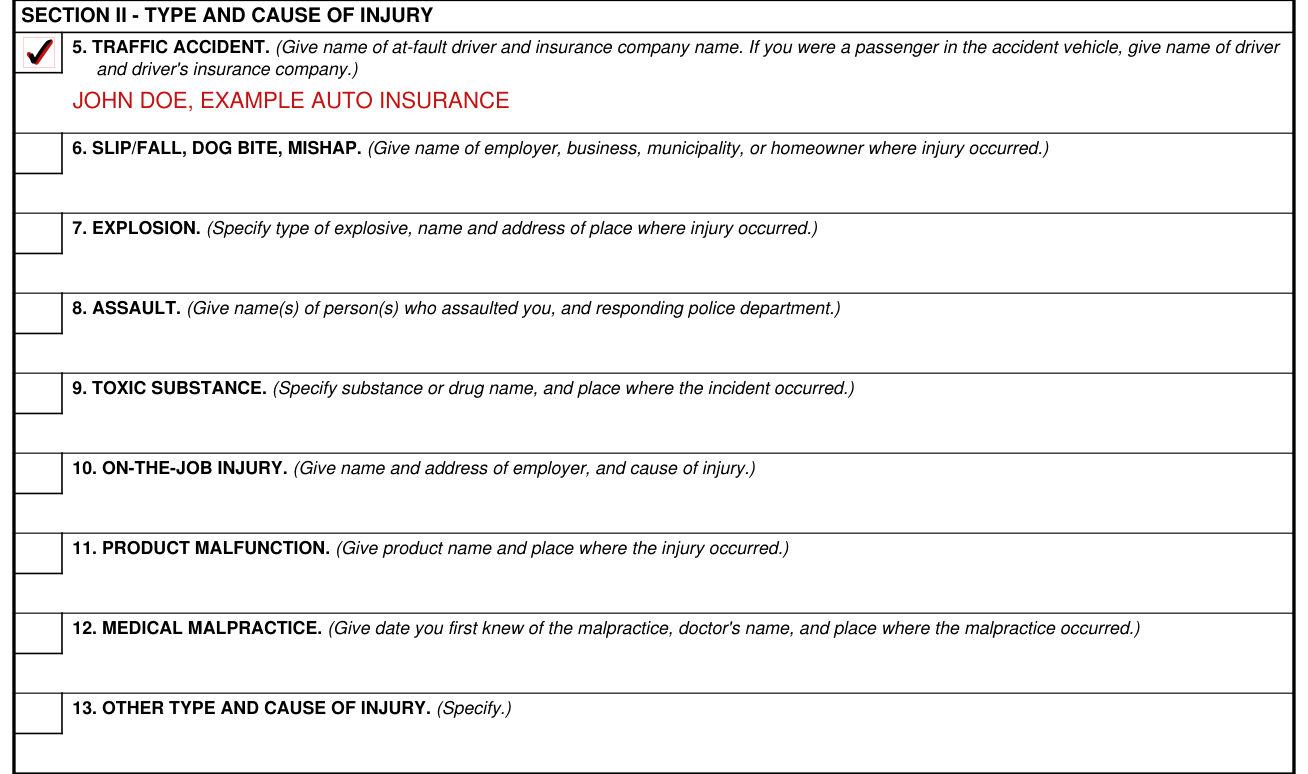
Box 5, traffic accident: give name of at-fault driver and insurance company name. If you were a passenger in the accident vehicle, give name of driver and driver's insurance company.
Box 6, slip/fall, dog bite, mishap: give name of employer, business, municipality, or homeowner where injury occurred.
Box 7, explosion: specify type of explosive, name and address of place where injury occurred.
Box 8, assault: give name(s) of person(s) who assaulted you, and responding police department.
Box 9, toxic substance: specify substance or drug name, and place where the incident occurred.
Box 10, on-the-job injury: give name and address of employer, and cause of injury.
Box 11, product malfunction: give product name and place where the injury occurred.
Box 12, medical malpractice: give date you first knew of the malpractice, doctor's name, and place where the malpractice occurred.
Box 13, other type and cause of injury: specify.
Box 14, the military medical facilities

List the military medical facilities that provided care for this injury, and dates of treatment, in Box 14.
Box 15, the lawyer

Have you hired a lawyer to represent you regarding this injury? Yes or no. Enter the lawyer's name and address in A and the lawyer's telephone number in B.
Box 16, the insurance
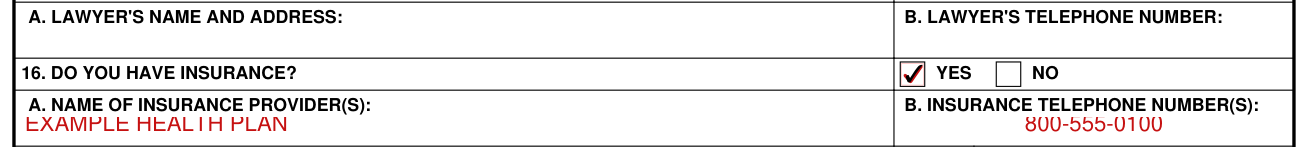
Do you have insurance? Yes or no. Enter the name of the insurance provider(s) in A and the insurance telephone number(s) in B.
Boxes 17 and 18, signing

Enter your signature in Box 17 and the date signed in Box 18 as YYYYMMDD.
Return the completed form within 35 days of the date of the letter
If a preaddressed envelope is not enclosed with the form, return your completed form to either of these locations: (1) the TRICARE processor who sent you the form; or (2) the TRICARE claims processor for the state or country in which you received the medical care. The Health Benefits Advisor at your nearest military installation can provide you with the address.
Payment of your claims has been suspended until more information is received. Your claims, and any related claims that are subsequently received, will be denied if this form is not completed and returned within 35 days from the date of this letter. This information is requested solely for the purpose of processing your TRICARE claim. It has no bearing on any legal action you may pursue as a result of your injury. All questions you may have concerning possible legal actions should be referred to an attorney. Do not execute a release or settle any personal injury claim you may have without notice to a military claims officer.
More rules for DD Form 2527
Disclosure is voluntary. However, failure to provide information may result in a delay processing your claim(s) and/or the denial of your claim(s).
Common questions about DD Form 2527
What is the DD form 2527 used for?
The Statement of Personal Injury, Possible Third Party Liability is a Defense Health Agency form. Fill out the form to permit the United States to recover medical expenses from whoever caused your injury.
Sources
[1] DD Form 2527 (MAR 2020), Statement of Personal Injury - Possible Third Party Liability, Defense Health Agency (the Official source link on this page).
