

Form DE 2501FC at a glance
What it is: Claim for Paid Family Leave (PFL) Care Benefits.
Who signs: Part C may be completed by the claimant if the care recipient is mentally or physically unable to do so. Part C must be signed by the care recipient or the care recipient's authorized representative. Part D: Original Signature of physician/practitioner - RUBBER STAMP IS NOT ACCEPTABLE. Enter the Physician/Practitioner's Phone Number and the Date Signed.
A filled-in Form DE 2501FC example: a daughter claims care benefits for her father
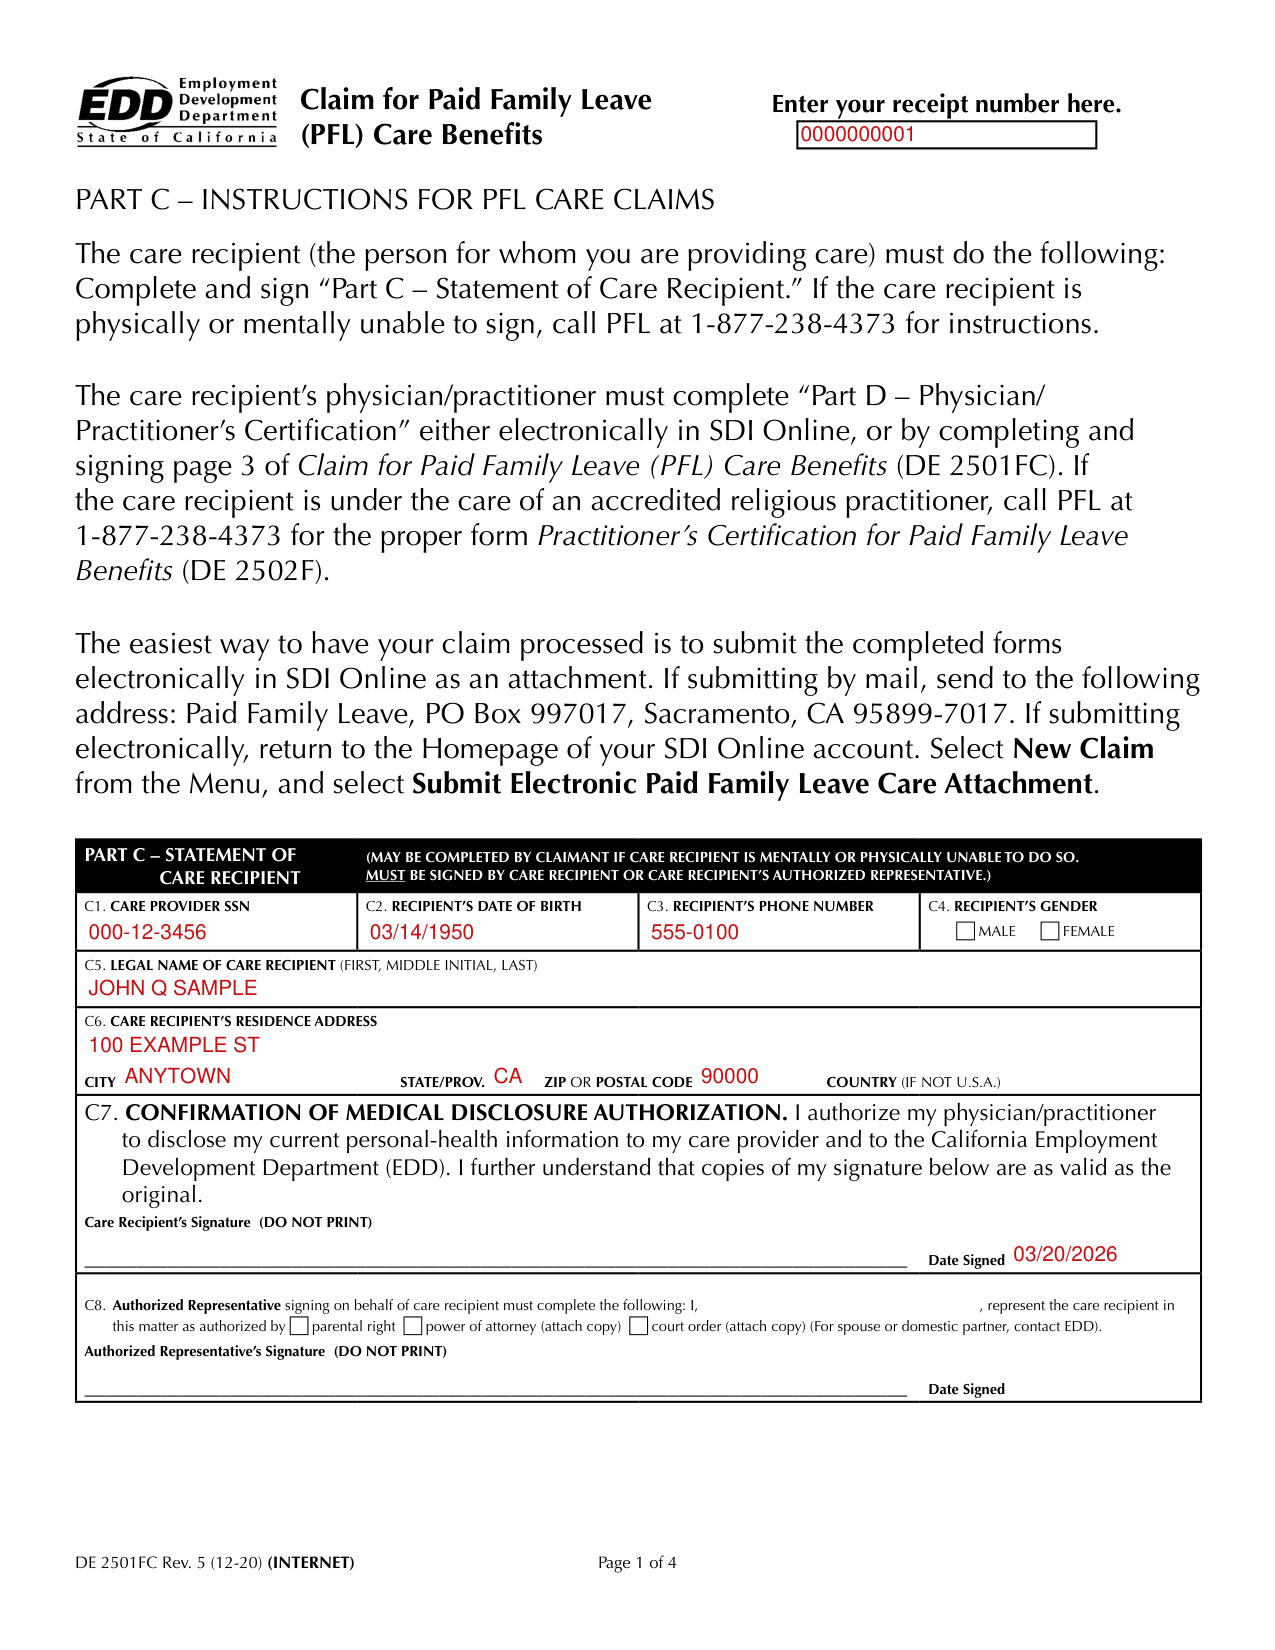
How to fill out Form DE 2501FC, box by box
Part C: the care recipient
Enter C1. Care Provider SSN, C2. Recipient's Date of Birth, C3. Recipient's Phone Number, C4. Recipient's Gender (Male or Female), C5. Legal Name of Care Recipient (First, Middle Initial, Last) and C6. Care Recipient's Residence Address.
Part D: the claimant and the patient
Medical certifications must be completed by a licensed physician or practitioner authorized to certify to a patient's disability/serious health condition pursuant to California Unemployment Insurance Code Section 2708.
Enter D1. PFL Claimant's (Care Provider's) Social Security Number and D2. PFL Claimant's Name (First, Middle Initial, Last).
Enter D3. Patient's Date of Birth. D4. Does your patient require care by the care provider? Yes or No (skip to D15).
Part D: diagnosis, dates and hours of care
Enter D5. Patient's Name (First, Middle Initial, Last) and D6. Diagnosis or, if not yet determined, a detailed statement of symptoms.
Enter D7. Primary ICD Code, D8. Secondary ICD Codes and D9. Date Patient's Condition Commenced.
Enter D10. First Date Care Needed, D11. Date you estimate patient will no longer require care by the care provider and D12. Date you expect recovery. The form also has check boxes Permanent Care Required and Never.
Enter D13. Approximately how many total hours per day will patient require care by a care provider? Hours, Comments.
D14. Would disclosure of the medical information on this certificate be medically or psychologically detrimental to your patient? Yes or No.
Part D: the physician or practitioner
Enter D15. Physician/Practitioner's License Number.
Enter D16. State or Country (if not U.S.A.) in which physician/practitioner is licensed to practice.
Enter D17. Physician/Practitioner's Name (First, Middle Initial, Last) and D18. Physician/Practitioner's Address (Post Office Box is not acceptable as the sole address), with City, State/Prov., ZIP or Postal Code and Country (if not U.S.A.).
Enter D19. Type of Physician/Practitioner and D20. Specialty (if any).
D21. Physician/Practitioner's Certification: “I certify under penalty of perjury that this patient has a serious health condition and requires a care provider. I have performed a physical examination and/or treated the patient. I am authorized to certify a patient disability or serious health condition pursuant to California Unemployment Insurance Code section 2708.”
More rules for Form DE 2501FC
Enter your receipt number here.
Sections 1143 and 3305 require additional administrative penalties.
The EDD requires disclosure of Social Security numbers on a mandatory basis to comply with California Unemployment Insurance Code, sections 1253 and 2627; with California Code of Regulations, Title 22, sections 1085, 1088, and 1326; with Code of Federal Regulations, Title 20, Part 604; and with U.S. Code, Title 8, sections 1621, 1641, and 1642.
Failure to supply any or all information may cause delay in issuing benefit payments or may cause you to be denied benefits to which you are entitled.
If you willfully make a false statement, representation, or knowingly withhold a material fact to obtain or increase any benefit or payment, the EDD will disqualify you from receiving benefits and/or services and may initiate criminal prosecution against you.
Principal purpose of the information: To determine eligibility for Paid Family Leave benefits.
If your situation is different
The care recipient is under the care of an accredited religious practitioner
The care recipient's physician/practitioner must complete “Part D - Physician/ Practitioner's Certification” either electronically in SDI Online, or by completing and signing page 3 of Claim for Paid Family Leave (PFL) Care Benefits (DE 2501FC). If the care recipient is under the care of an accredited religious practitioner, call PFL at 1-877-238-4373 for the proper form Practitioner's Certification for Paid Family Leave Benefits (DE 2502F).
Common questions about Form DE 2501FC
What is the phone number for California Paid Family Leave?
The care recipient (the person for whom you are providing care) must complete and sign “Part C - Statement of Care Recipient.” If the care recipient is physically or mentally unable to sign, call PFL at 1-877-238-4373 for instructions.
Where do I file it?
The easiest way to have your claim processed is to submit the completed forms electronically in SDI Online as an attachment. If submitting by mail, send to Paid Family Leave, PO Box 997017, Sacramento, CA 95899-7017. If submitting electronically, return to the Homepage of your SDI Online account. Select New Claim from the Menu, and select Submit Electronic Paid Family Leave Care Attachment.
Is there a penalty?
Under sections 2116 and 2122 of the California Unemployment Insurance Code, it is a violation for any individual who, with intent to defraud, falsely certifies the medical condition of any person in order to obtain disability insurance benefits, whether for the maker or for any other person, and is punishable by imprisonment and/or a fine not exceeding $20,000 (checked November 10, 2026).
Sources
[1] Form DE 2501FC, Claim for Paid Family Leave (PFL) Care Benefits, California Employment Development Department (the Official source link on this page).
