

Form DFS-F5-DWC-25 at a glance
What it is: Form DFS-F5-DWC-25 is the Florida Workers' Compensation Uniform Medical Treatment/Status Reporting Form.
Who signs: The Physician signs the Attestation Statement.
Health care providers shall legibly and accurately complete all sections of this form, limiting their responses to their area of expertise.
A filled-in Form DFS-F5-DWC-25 example: a physician reports a follow-up visit
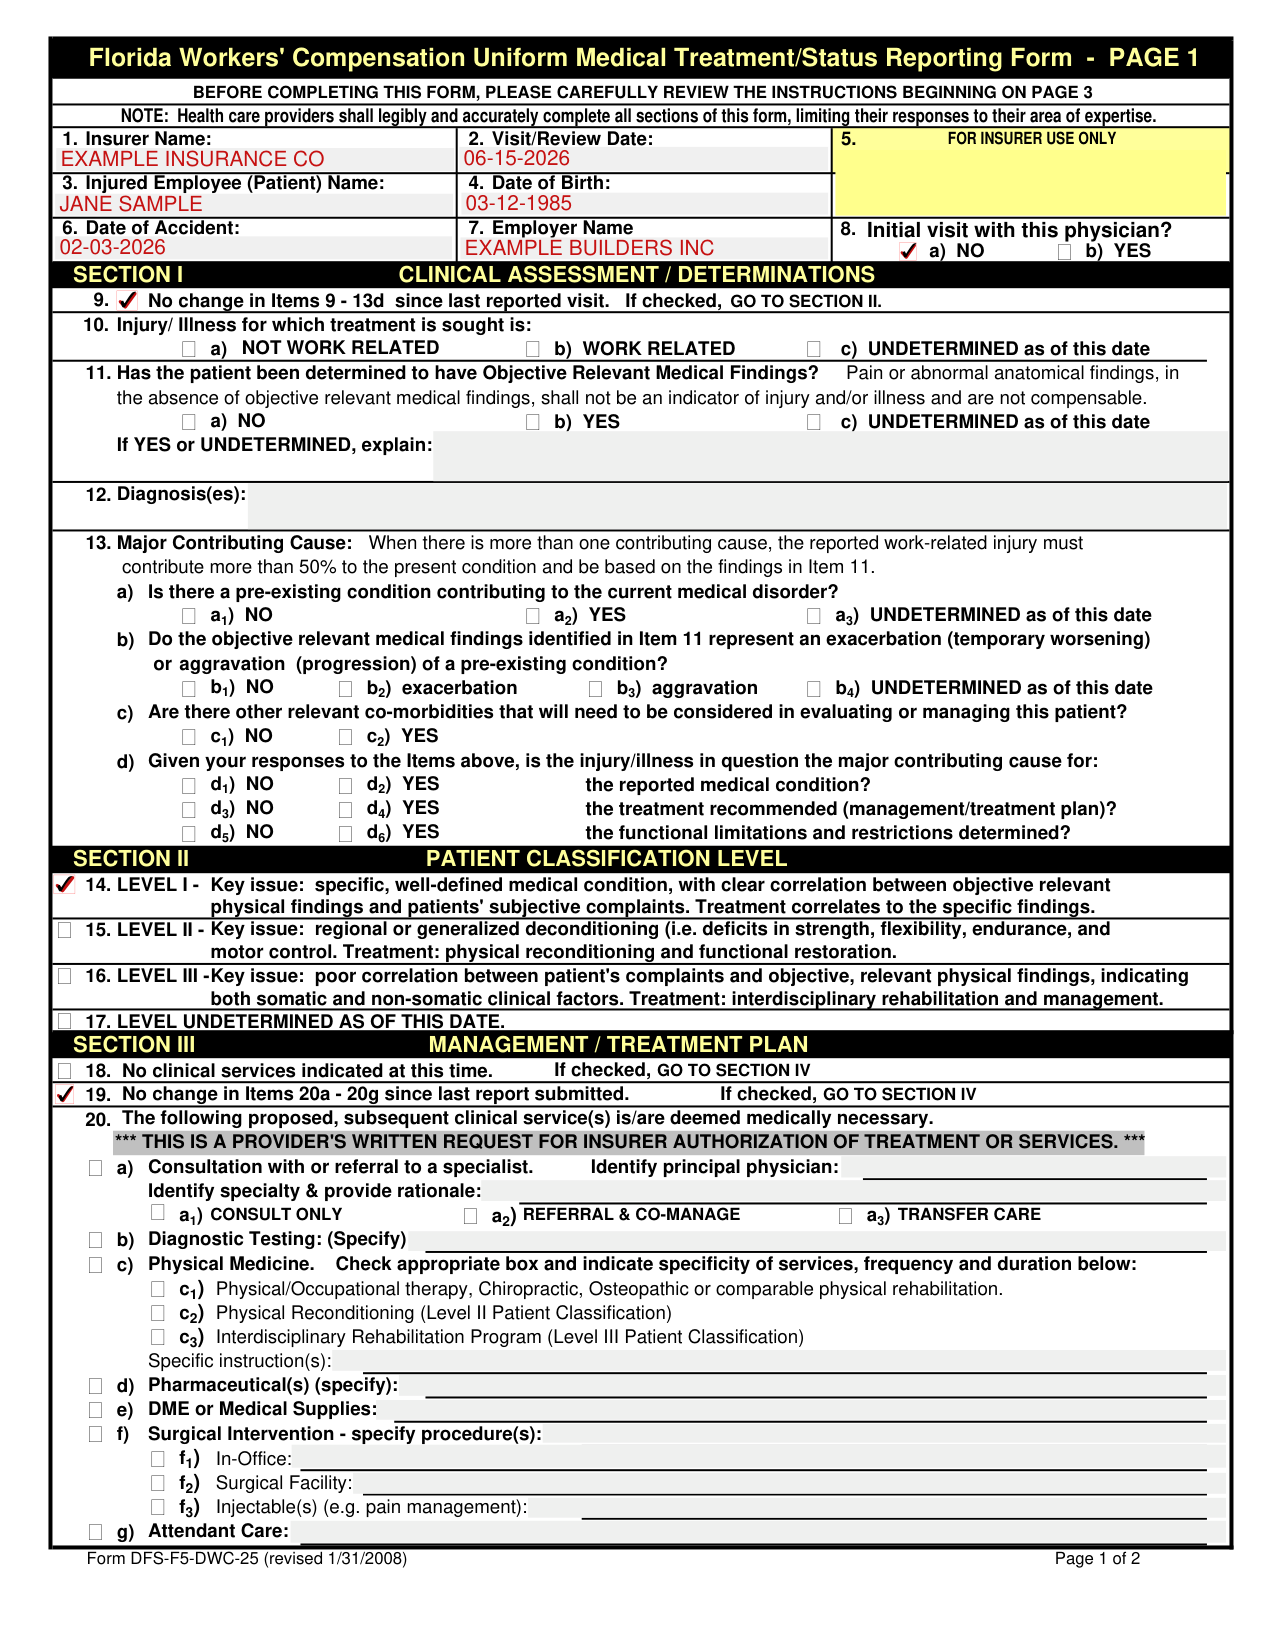
How to fill out Form DFS-F5-DWC-25, box by box
Boxes 1 to 5, the visit and the patient

Enter the Insurer Name.
Enter the Visit/Review Date, the Injured Employee (Patient) Name, the Date of Birth and the Social Security #.
Boxes 6 to 8, Date of Accident, Employer and Initial visit

Enter the Date of Accident and the Employer Name. For Initial visit with this physician? mark a) NO or b) YES.
Box 9, No change in Items 9 to 13d

Mark Item 9 for No change in Items 9 - 13d since the last reported visit; if checked, go to Section II.
Box 13, Major Contributing Cause
Major Contributing Cause: When there is more than one contributing cause, the reported work-related injury must contribute more than 50% to the present condition and be based on the findings in Item 11.
Is there a pre-existing condition contributing to the current medical disorder? Mark a1) NO, a2) YES or a3) UNDETERMINED.
Do the objective relevant medical findings identified in Item 11 represent an exacerbation (temporary worsening) or aggravation (progression) of a pre-existing condition? Mark b1) NO, b2) exacerbation, b3) aggravation or b4) UNDETERMINED.
Are there other relevant co-morbidities that will need to be considered? Mark c1) NO or c2) YES.
Is the injury/illness the major contributing cause for the reported medical condition (d1) NO or d2) YES), the treatment recommended (management/treatment plan) (d3) NO or d4) YES) and the functional limitations and restrictions determined (d5) NO or d6) YES)?
Section II, Patient Classification Level

Mark 14 for Level I, Key issue: specific, well-defined medical condition, with clear correlation between objective relevant physical findings and patients' subjective complaints.
Mark 15 for Level II, Key issue: regional or generalized deconditioning. Treatment: physical reconditioning and functional restoration.
Mark 16 for Level III, Key issue: poor correlation between patient's complaints and objective, relevant physical findings, indicating both somatic and non-somatic clinical factors. Treatment: interdisciplinary rehabilitation and management. Mark 17 for Level undetermined as of this date.
Boxes 18 and 19, no clinical services or no change

Mark 18 for No clinical services indicated at this time; if checked, go to Section IV.
Mark 19 for No change in Items 20a - 20g since last report submitted; if checked, go to Section IV.
Box 20, proposed subsequent clinical services
The following proposed, subsequent clinical service(s) is/are deemed medically necessary. This is a provider's written request for insurer authorization of treatment or services.
For a) Consultation with or referral to a specialist, identify specialty and provide rationale, identify principal physician, and mark a1) CONSULT ONLY, a2) REFERRAL & CO-MANAGE or a3) TRANSFER CARE.
For c) Physical Medicine, check the appropriate box and indicate specificity of services, frequency and duration, then enter the Specific instruction(s): c1) Physical/Occupational therapy, Chiropractic, Osteopathic or comparable physical rehabilitation; c2) Physical Reconditioning (Level II Patient Classification); c3) Interdisciplinary Rehabilitation Program (Level III Patient Classification).
Specify b) Diagnostic Testing and d) Pharmaceutical(s). List e) DME or Medical Supplies and g) Attendant Care. For f) Surgical Intervention, specify procedure(s) and mark f1) In-Office, f2) Surgical Facility or f3) Injectable(s) (e.g. pain management).
Page 2, Patient Name, D/A and Visit/Review Date

At the top of page 2, enter the Patient Name, D/A and Visit/Review Date.
Section IV, Functional Limitations and Restrictions
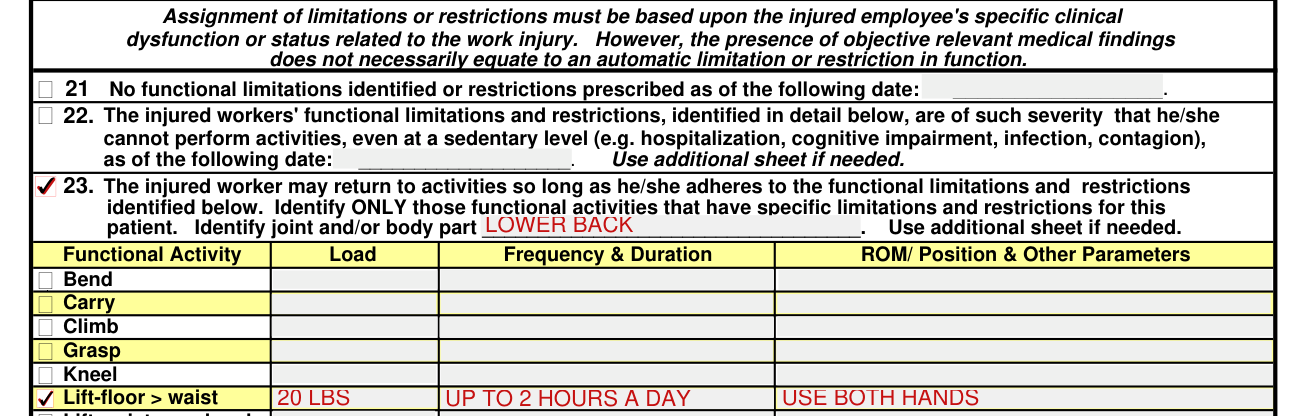
Assignment of limitations or restrictions must be based upon the injured employee's specific clinical dysfunction or status related to the work injury. The presence of objective relevant medical findings does not necessarily equate to an automatic limitation or restriction in function.
Mark 21 for No functional limitations identified or restrictions prescribed as of the following date, and enter that date.
Mark 22 when the injured worker's functional limitations and restrictions are of such severity that he/she cannot perform activities, even at a sedentary level (e.g. hospitalization, cognitive impairment, infection, contagion), as of the following date, and enter that date.
Mark 23 when the injured worker may return to activities so long as he/she adheres to the functional limitations and restrictions identified. Identify ONLY those functional activities that have specific limitations and restrictions for this patient. Use additional sheet if needed.
Identify the joint and/or body part. For each activity, enter the Load, the Frequency & Duration and the ROM/Position & Other Parameters.
Any functional limitations or restrictions assigned apply to both on and off the job activities, and are in effect until the next scheduled appointment unless otherwise noted or modified prior to the appointment date.
Specify those functional limitations and restrictions, in Item 23, which are permanent if MMI / PIR have been assigned in Item 24.
Boxes 24 to 27, Maximum Medical Improvement and Permanent Impairment Rating
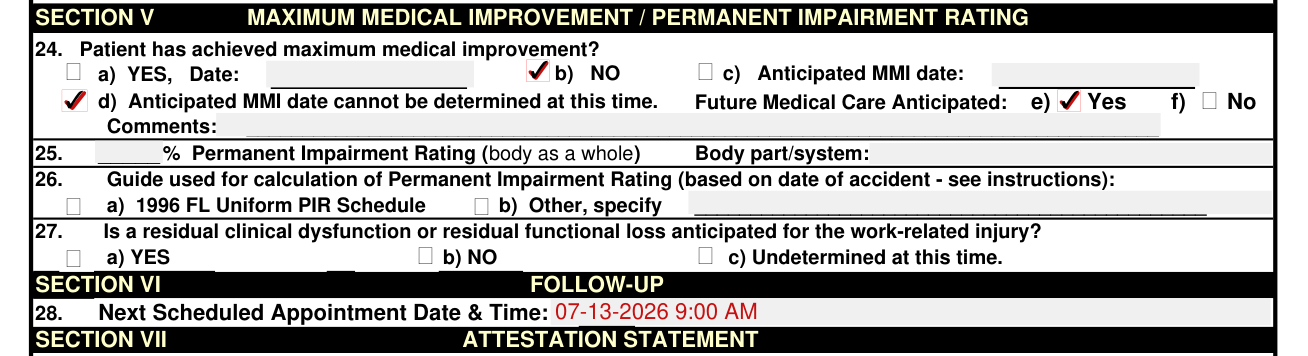
Patient has achieved maximum medical improvement? Mark a) YES and enter the Date, or mark b) NO. The form also has c) Anticipated MMI date, with a date to enter, and d) Anticipated MMI date cannot be determined at this time, each its own box.
Mark Yes or No for Future Medical Care Anticipated, and enter any Comments.
In Box 25, enter the % Permanent Impairment Rating (body as a whole) and the Body part/system.
Guide used for calculation of Permanent Impairment Rating (based on date of accident): mark a) 1996 FL Uniform PIR Schedule or b) Other, specify.
Is a residual clinical dysfunction or residual functional loss anticipated for the work-related injury? Mark a) YES, b) NO or c) Undetermined at this time.
Section VI, Next Scheduled Appointment Date & Time

Enter the Next Scheduled Appointment Date & Time.
Section VII, Attestation Statement

Sign, and enter the Physician Group, the Date, the Physician DOH License #, the Physician Name (print name) and the Physician Specialty.
The Physician attests that all responses herein have been made, in accordance with the instructions as part of this form, to a reasonable degree of medical certainty based on objective relevant medical findings. The responses are consistent with the medical documentation regarding this patient, and have been shared with the patient.
The Physician certifies to any MMI / PIR information provided in this form.
If your situation is different
A provider other than a physician rendered direct billable services
If any direct billable services for this visit were rendered by a provider other than a physician, the provider completes the Provider Signature, Provider Name (print name), Date and Provider DOH License #.
Common questions about Form DFS-F5-DWC-25
Who signs it?
The Physician signs the Attestation Statement.
Sources
[1] Form DFS-F5-DWC-25 (revised 1/31/2008), Florida Workers' Compensation Uniform Medical Treatment/Status Reporting Form, Florida Department of Financial Services (the Official source link on this page).