

Form DHCS 6247 at a glance
What it is: Authorization for Release of Protected Health Information to Third Parties is a form of the State of California Health and Human Services Agency Department of Health Care Services.
Notary: If no identification is attached, your signature must be notarized. Notarized By ___ On ___ (Date).
By completing this form, you authorize the California Department of Health Care Services to release your protected health information identified on the form to the persons or entities identified on the form. You also have the right to request copies of those records.
What to bring and attach to Form DHCS 6247
If you want copies of your records mailed, send a photocopy of your California driver's license, Department of Motor Vehicles Identification Card, or other valid identification. Also send documentation verifying your address.
A filled-in Form DHCS 6247 example: a parent asks for two kinds of records for a child
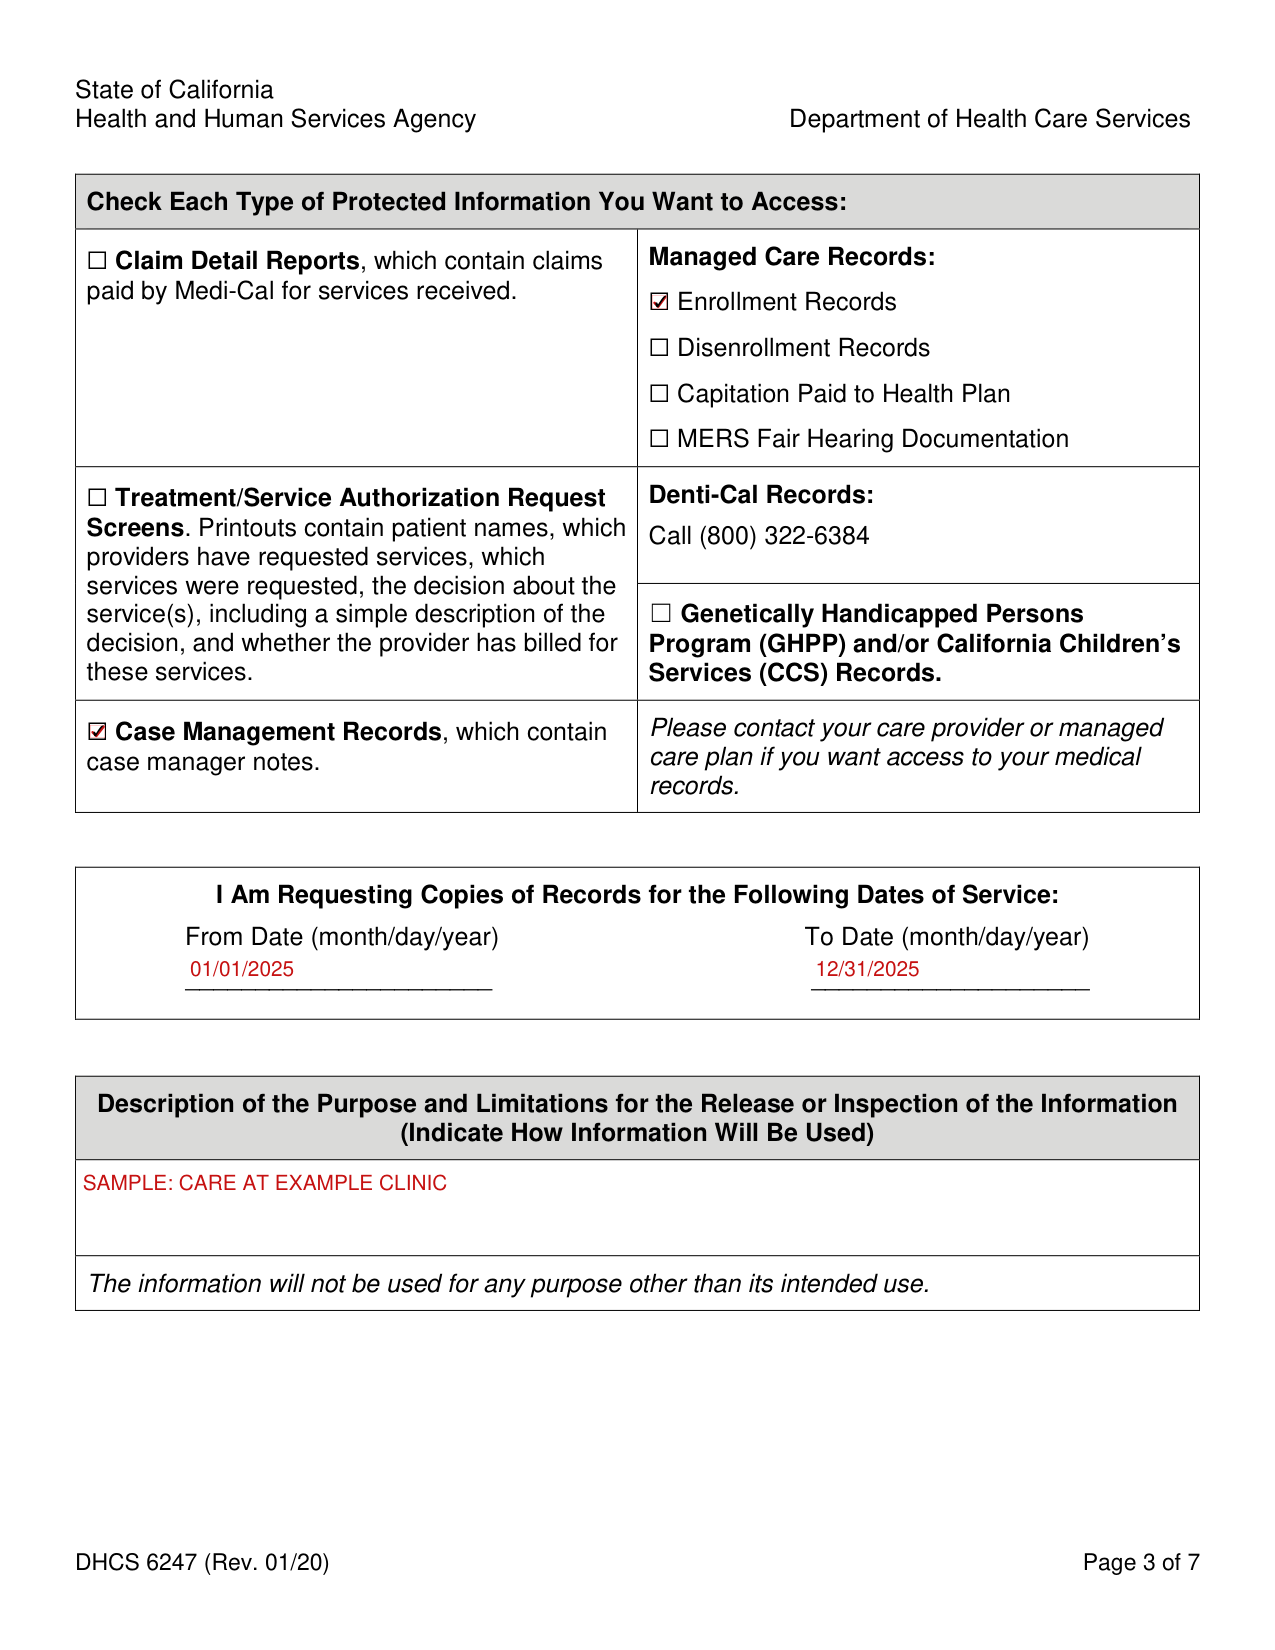
How to fill out Form DHCS 6247, box by box
Your Information
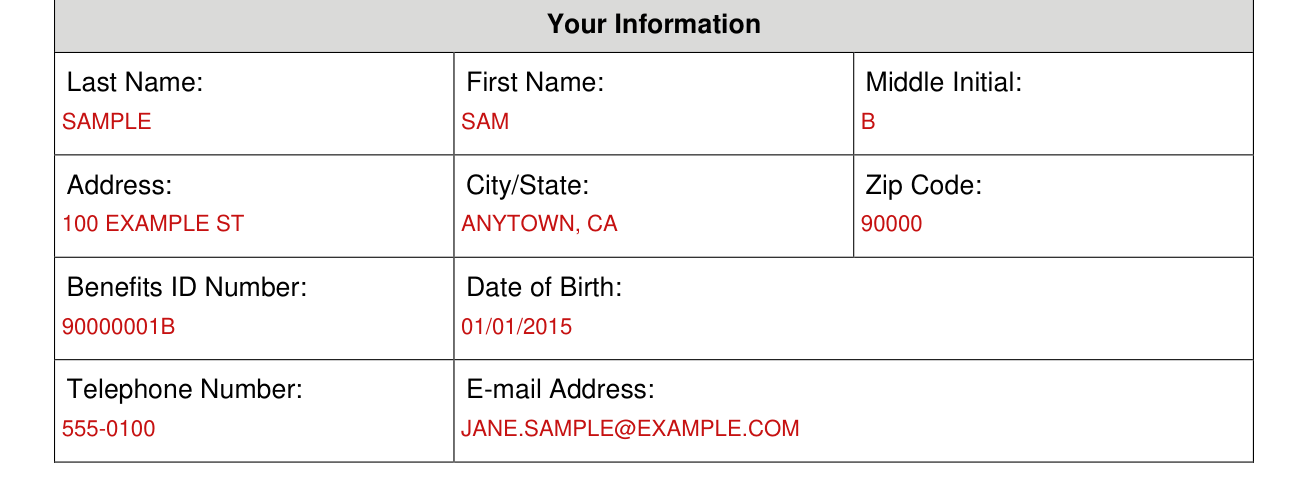
Under Your Information, enter your Last Name, First Name, Middle Initial, Address, City/State, Zip Code, Benefits ID Number, Date of Birth, Telephone Number and E-mail Address.
Person/Organization Providing the Information and to Receive the Information
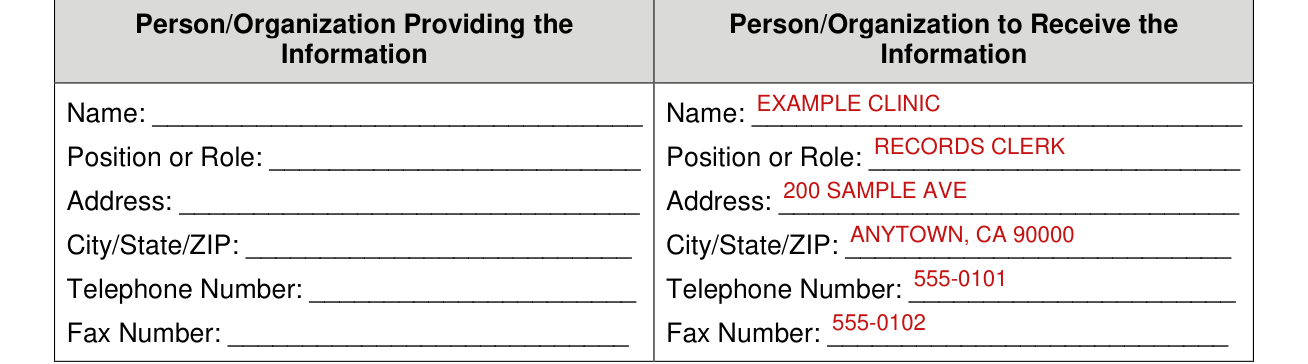
For the Person/Organization Providing the Information and the Person/Organization to Receive the Information, enter the Name, Position or Role, Address, City/State/Zip, Telephone Number and Fax Number.
Description of the Specific Information to be Released/Inspected
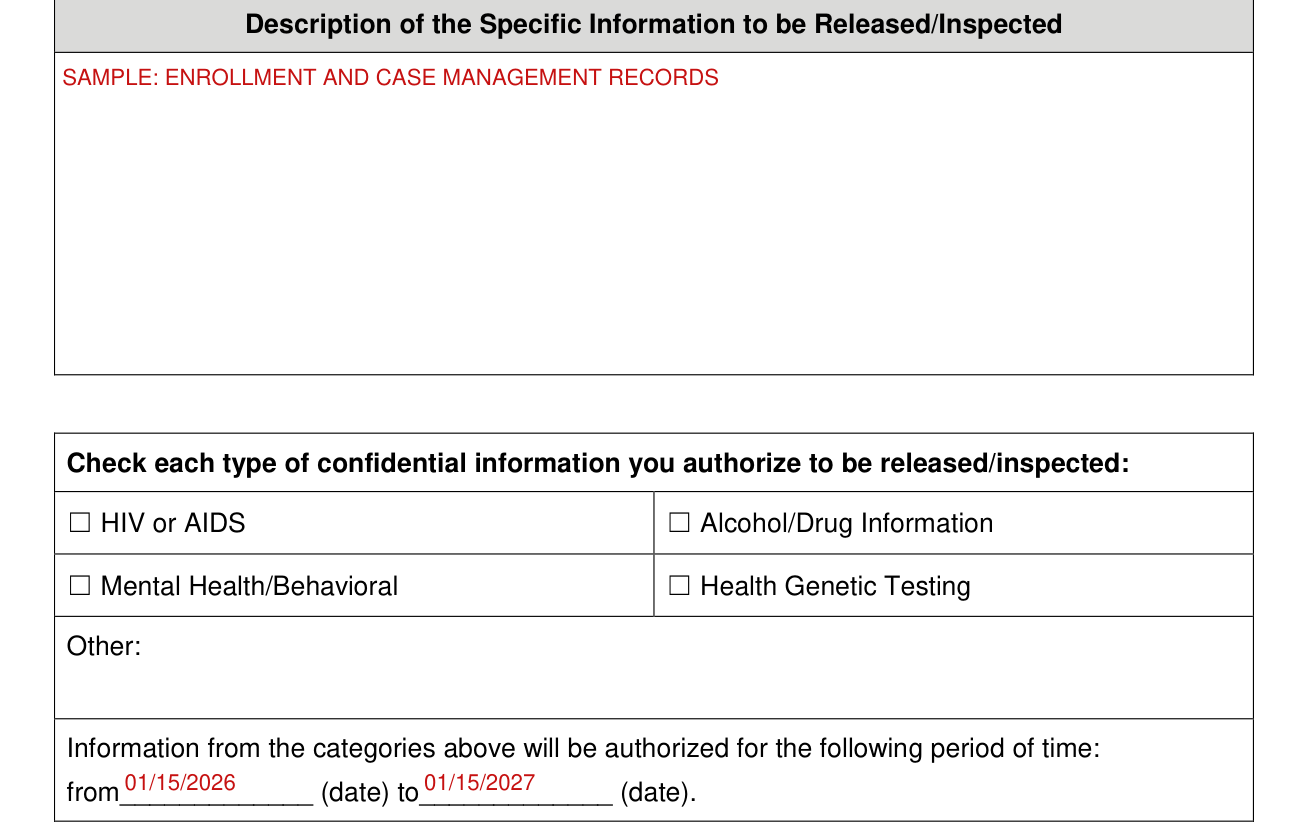
Enter the Description of the Specific Information to be Released/Inspected.
Check each type of confidential information you authorize to be released/inspected: HIV or AIDS, Alcohol/Drug Information, Mental Health/Behavioral, Health Genetic Testing or Other.
Enter the period of time for which information from the categories is authorized: from (date) to (date).
Check Each Type of Protected Information You Want to Access
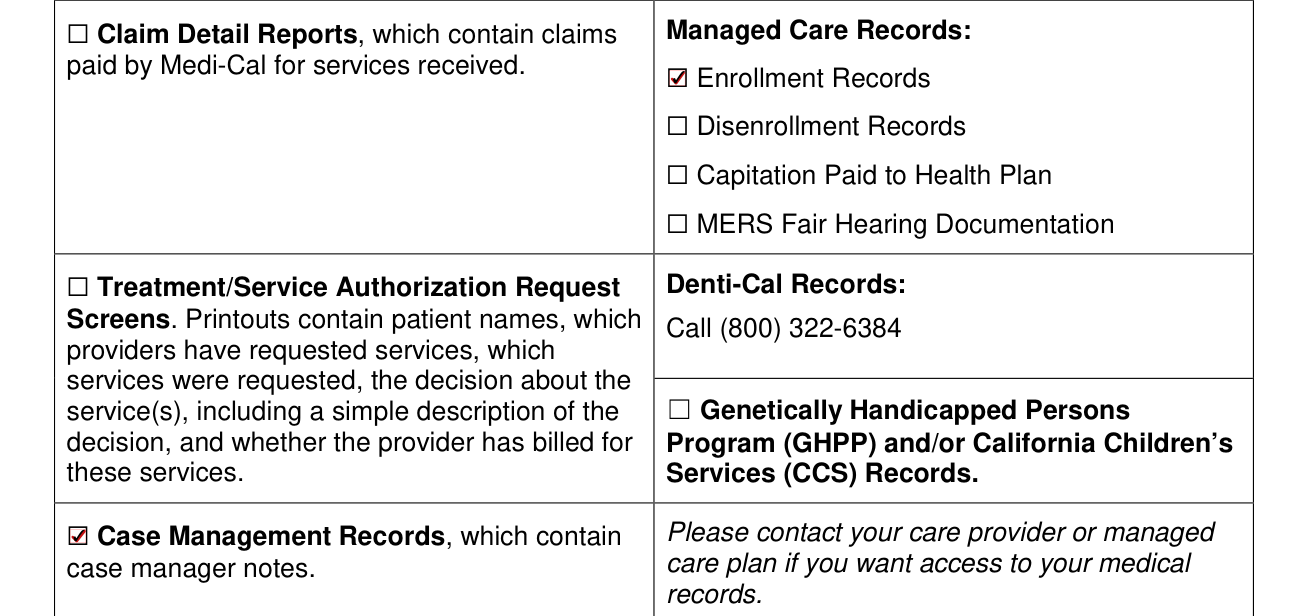
Check Each Type of Protected Information You Want to Access: Claim Detail Reports, which contain claims paid by Medi-Cal for services received.
Managed Care Records: Enrollment Records, Disenrollment Records, Capitation Paid to Health Plan and MERS Fair Hearing Documentation.
Treatment/Service Authorization Request Screens. Printouts contain patient names, which providers have requested services, which services were requested, the decision about the service(s), including a simple description of the decision, and whether the provider has billed for these services.
For Denti-Cal Records, call (800) 322-6384.
Genetically Handicapped Persons Program (GHPP) and/or California Children's Services (CCS) Records.
Case Management Records, which contain case manager notes.
Contact your care provider or managed care plan if you want access to your medical records.
I Am Requesting Copies of Records for the Following Dates of Service

Enter the From Date (month/day/year) and To Date (month/day/year) of the Following Dates of Service for which you are requesting copies of records.
Description of the Purpose and Limitations for the Release or Inspection of the Information

Enter the Description of the Purpose and Limitations for the Release or Inspection of the Information (Indicate How Information Will Be Used).
The information will not be used for any purpose other than its intended use.
Parent, Guardian, or Personal Representative Information

Under Parent, Guardian, or Personal Representative Information, enter the Last Name, First Name, Middle Initial, Address, City/State, Zip Code, Benefits ID Number, Date of Birth, Telephone Number and E-mail Address.
What Legal Authority Do You Have to Request Health Information
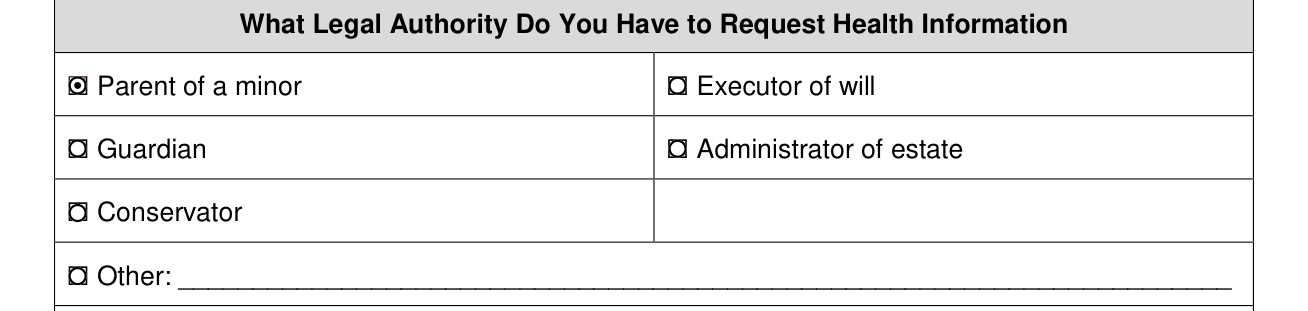
For What Legal Authority Do You Have to Request Health Information, check Parent of a minor, Executor of will, Guardian, Administrator of estate, Conservator or Other.
You Must Attach Legal Documentation to Verify That You Are the Parent, Conservator, Guardian, Executor of a Decedent's Will, or Have Medical Decision-Making Authority for the Individual.
Please mail me a copy of the requested information or I wish to review the requested information in person

Check Please mail me a copy of the requested information, or I wish to review the requested information in person. If you request to review records in person, you will be contacted to schedule an appointment. Location available for in person review: Sacramento Only.
I Request That a Person of My Choosing be Allowed to Inspect My Records

Check I Request That a Person of My Choosing be Allowed to Inspect My Records. Any person or attorney may be named. Records will not be sent to photocopy services.
Enter the Name, Telephone Number, Address and Relationship to you.
Identifying Information

Under Identifying Information, check Address verification attached and enter the Type (Utility Bill, Phone Bill, Driver's License, Etc.).
Check Copy of identification attached, then enter the Type (CA Driver's License, CA DMV Identification Card, Birth Certificate, Benefits Identification Card, Managed Care Card, State Or Federal Employee ID Card) and the Number.
Notarized By

If no identification is attached, your signature must be notarized. Notarized By ___ On ___ (Date).
Enter the Notary Public Number. Unofficial unless stamped by Notary Public.
This authorization will expire on
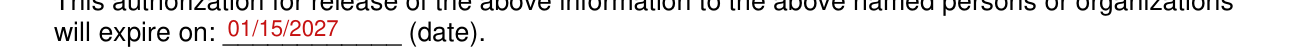
This authorization for release of the information to the named persons or organizations will expire on: (date).
Member Signature

I understand that by signing this authorization: I authorize the use and/or disclosure of my individually identifiable health information for the purpose listed. I understand that this authorization is voluntary.
I have the right to revoke this authorization at any time by sending a signed notice stopping this authorization to the address on page one. The authorization will cease on the date my valid revocation request is received. An individual may revoke an authorization at any time, provided that the revocation is in writing, except to the extent that: The covered entity has taken action in reliance thereon; or if the authorization was obtained as a condition of obtaining insurance coverage.
My treatment, payment, enrollment or eligibility for benefits will not be affected if I do not sign this authorization.
I have the right to receive a copy of this authorization.
Sign as Member Signature and enter the Date. "I declare under penalty of perjury that the information on this form is true and correct."
More rules for Form DHCS 6247
Under California law, the recipient of my medical information is prohibited from re-disclosing the information, except with a written authorization or as specifically required or permitted by law.
If the organization or person I have authorized to receive the information is not a health plan or health care provider; the released information may no longer be protected by federal privacy regulations.
Records and copies obtained relating to outpatient psychotherapy care shall be returned or destroyed at the expiration date of this authorization except those obtained for treatment and diagnosis purposes.
Common questions about Form DHCS 6247
Is there a deadline?
You will receive a response to your request within 30 days after the Department receives your request. A request for records of services provided up to six years ago is a 30-day process. All other requests have an approximate 60-day time frame for additional processing.
Where do I file it?
Mail the completed form to the Department of Health Care Services, DHCS/MEDI-CAL FIP. O. Box 526018, Sacramento, CA 95852-6018, (916) 636-1980.
Sources
[1] DHCS 6247 (Rev. 01/20), Authorization for Release of Protected Health Information to Third Parties, California Department of Health Care Services (the Official source link on this page).