

DHS 1169 at a glance
What it is: Evaluation for the Placement of Liens, State of Hawaii Med-QUEST Division: the information you give us will be used to determine if the State should place a lien on your home property.
Who signs: Applicant/Beneficiary: Signature or Mark. Authorized Representative or Witness: Signature.
PART I is to be completed by the Applicant/Beneficiary or Authorized Representative. The State is required to place a lien on the home property of certain individuals who receive medical assistance who is an inpatient in a nursing facility or other medical institution.
An inpatient in a nursing facility can include a person receiving HCBS or residing in a CCFFH or E-ARCH.
A filled-in DHS 1169 example: a nursing facility resident reports the home she owns
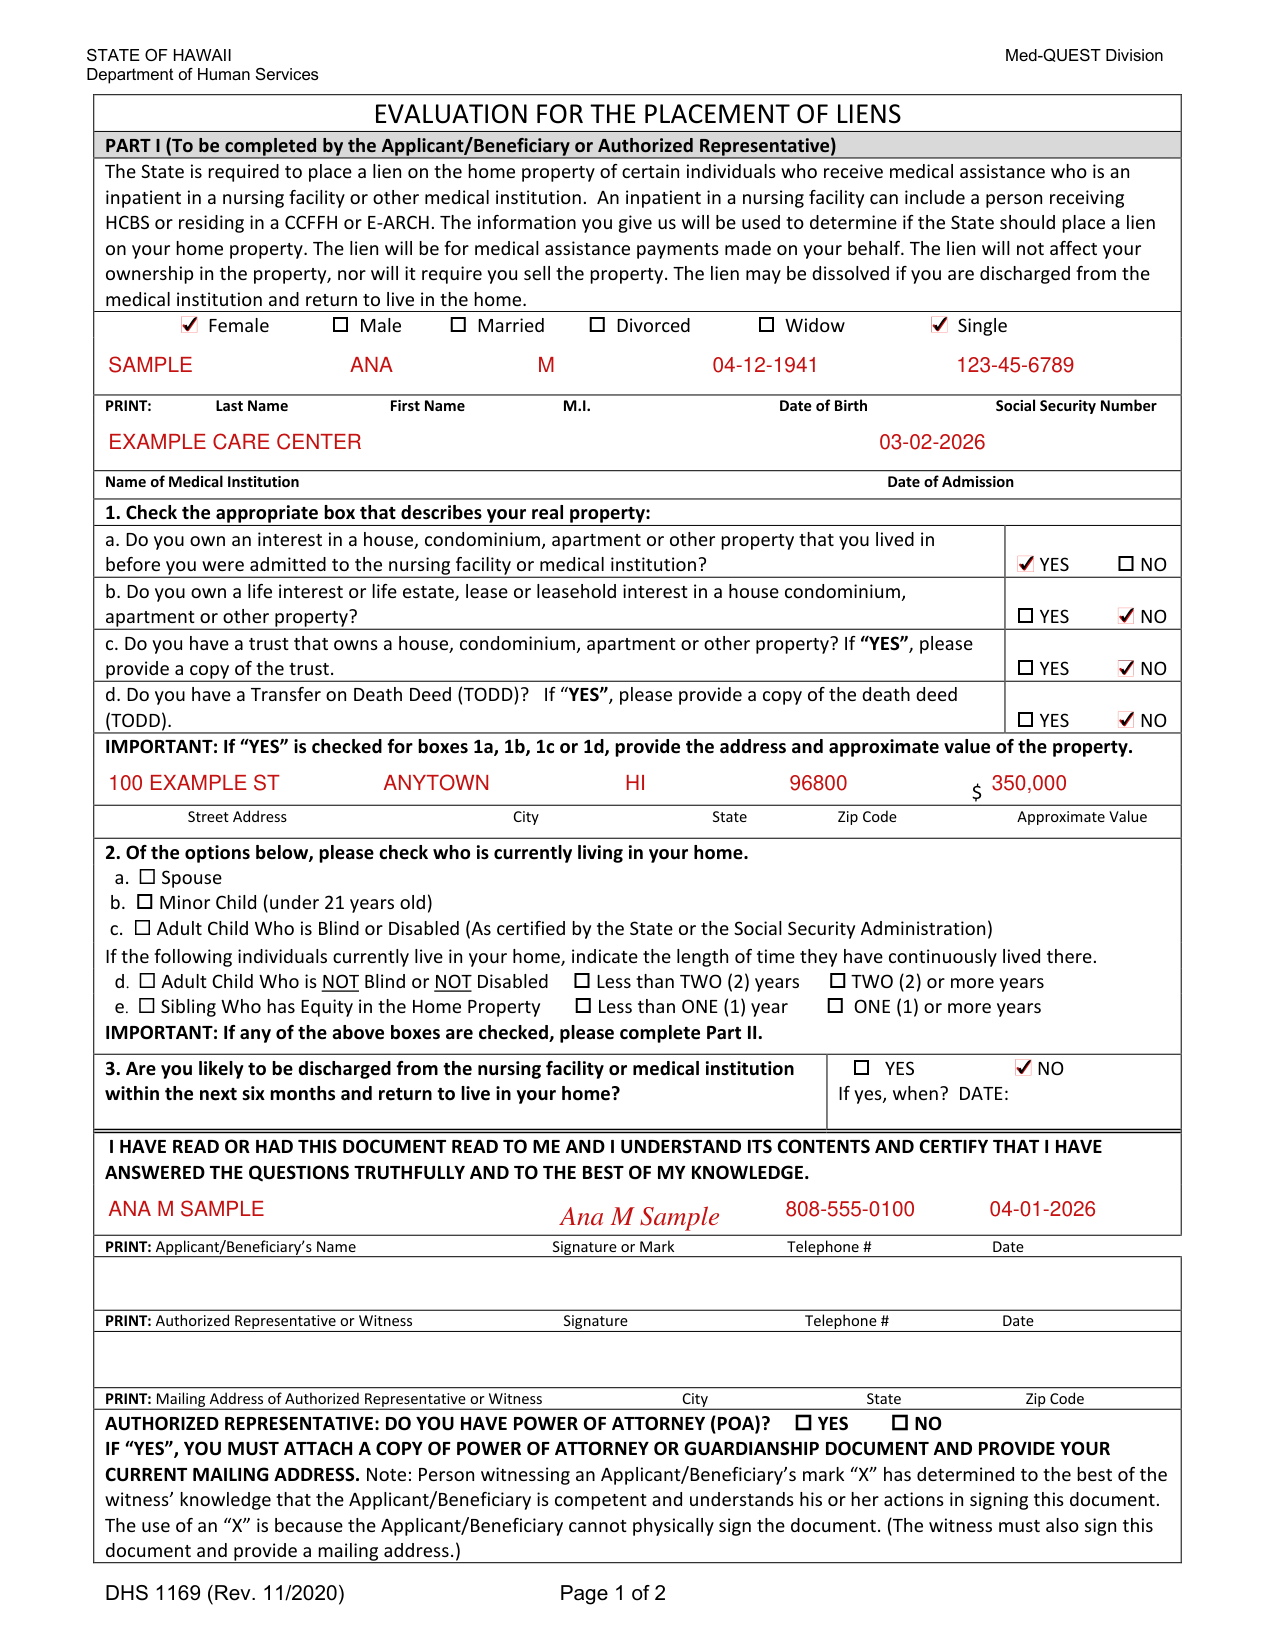
How to fill out DHS 1169, box by box
Name, date of birth and Social Security Number
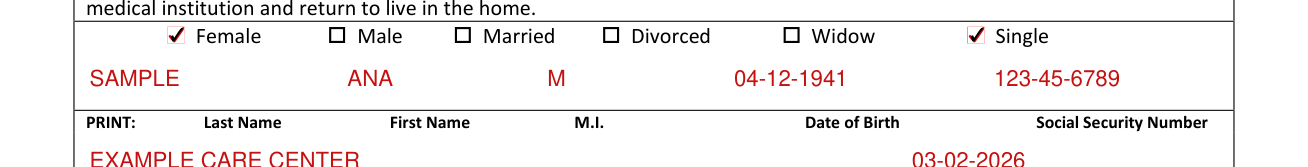
PRINT the Last Name, First Name, M.I., Date of Birth and Social Security Number, and check Female or Male and Married, Divorced, Widow or Single.
Name of Medical Institution and Date of Admission

Enter the Name of Medical Institution and the Date of Admission.
Check the appropriate box that describes your real property

Check the appropriate box that describes your real property: a. Do you own an interest in a house, condominium, apartment or other property that you lived in before you were admitted to the nursing facility or medical institution?
b. Do you own a life interest or life estate, lease or leasehold interest in a house condominium, apartment or other property? Check YES or NO.
c. Do you have a trust that owns a house, condominium, apartment or other property? If “YES”, please provide a copy of the trust. Check YES or NO.
d. Do you have a Transfer on Death Deed (TODD)? If “YES”, please provide a copy of the death deed (TODD).
Check YES or NO. If “YES” is checked for boxes 1a, 1b, 1c or 1d, provide the address and approximate value of the property: Street Address, City, State, Zip Code and Approximate Value.
Who is currently living in your home

Check who is currently living in your home.
a. Spouse, b. Minor Child (under 21 years old), c. Adult Child Who is Blind or Disabled (As certified by the State or the Social Security Administration).
If the following individuals currently live in your home, indicate the length of time they have continuously lived there: d. Adult Child Who is NOT Blind or NOT Disabled, Less than TWO (2) years or TWO (2) or more years; e. Sibling Who has Equity in the Home Property, Less than ONE (1) year or ONE (1) or more years.
If any of the above boxes are checked, please complete Part II.
Discharged within the next six months

Are you likely to be discharged from the nursing facility or medical institution within the next six months and return to live in your home? Check YES or NO; if yes, when? DATE:
Signing as the Applicant/Beneficiary and the Authorized Representative or Witness
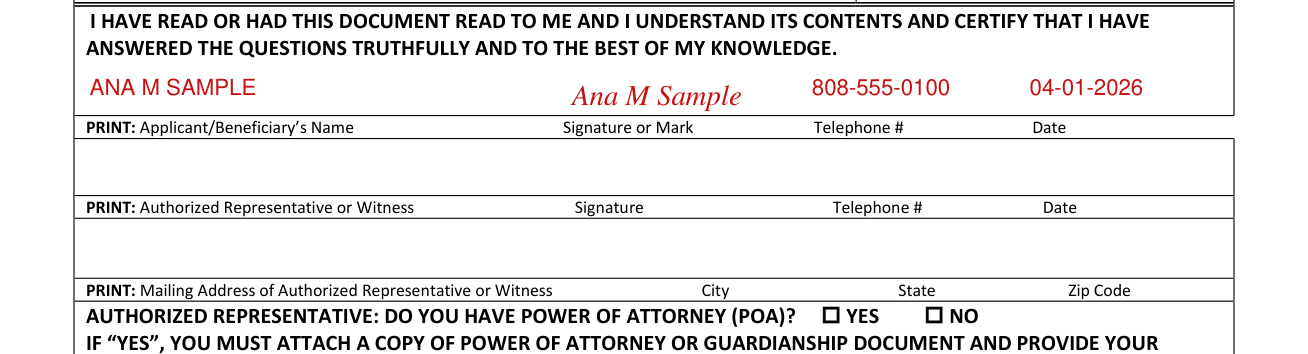
I have read or had this document read to me and I understand its contents and certify that I have answered the questions truthfully and to the best of my knowledge.
PRINT the Applicant/Beneficiary's Name, then add the Signature or Mark, Telephone # and Date.
PRINT the Authorized Representative or Witness, then add the Signature, Telephone # and Date.
Print the Mailing Address of Authorized Representative or Witness, City, State and Zip Code. Authorized representative: do you have power of attorney (POA)? Check YES or NO. If “YES”, you must attach a copy of power of attorney or guardianship document and provide your current mailing address. Note: Person witnessing an Applicant/Beneficiary's mark “X” has determined to the best of the witness' knowledge that the Applicant/Beneficiary is competent and understands his or her actions in signing this document. The use of an “X” is because the Applicant/Beneficiary cannot physically sign the document. (The witness must also sign this document and provide a mailing address.)
Part II: list the individuals living in your home
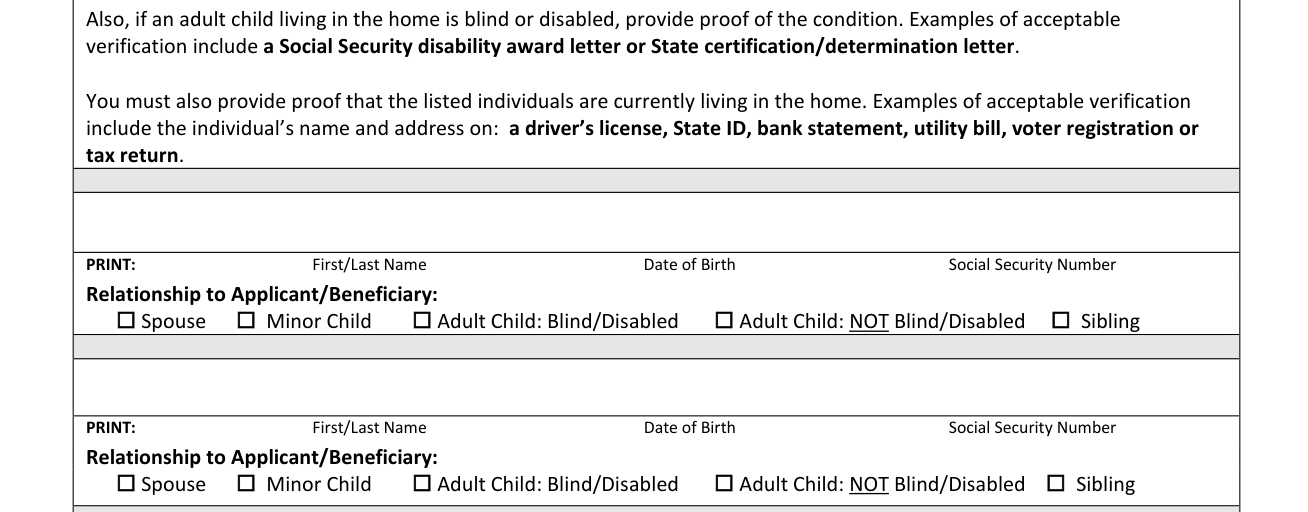
You indicated in Part I that your spouse, your children or your sibling(s) are currently living in your home. Please identify and list them. If you need more space, please attach a separate sheet of paper.
PRINT the First/Last Name, Date of Birth and Social Security Number, and check the Relationship to Applicant/Beneficiary: Spouse, Minor Child, Adult Child: Blind/Disabled, Adult Child: NOT Blind/Disabled or Sibling.
You must provide proof of your relationship to these listed individuals. Examples of acceptable verification include: birth certificates, marriage licenses, joint tax returns or baptismal records.
Also, if an adult child living in the home is blind or disabled, provide proof of the condition. Examples of acceptable verification include a Social Security disability award letter or State certification/determination letter.
You must also provide proof that the listed individuals are currently living in the home. Examples of acceptable verification include the individual's name and address on: a driver's license, State ID, bank statement, utility bill, voter registration or tax return.
Services that helped delay admission

Did your adult child, who is NOT blind/disabled and has continuously lived with you in your home for TWO (2) or more years, provide services that helped delay your admission to a medical institution? Check YES or NO; if yes, briefly describe the services.
More rules for DHS 1169
The lien will be for medical assistance payments made on your behalf.
The lien may be dissolved if you are discharged from the medical institution and return to live in the home.
PART III is to be completed by DHS.
Sources
[1] DHS 1169 (Rev. 11/2020), Evaluation for the Placement of Liens, State of Hawaii Med-QUEST Division, Department of Human Services (the Official source link on this page).
