
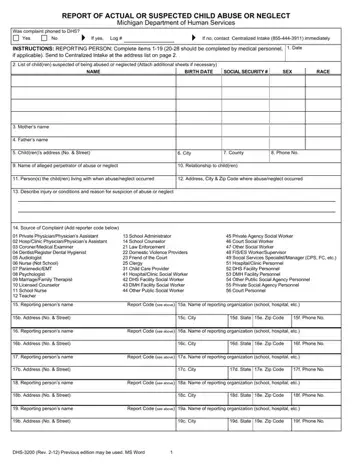
Form DHS-3200 at a glance
What it is: DHS-3200 is the Report of Actual or Suspected Child Abuse or Neglect of the Michigan Department of Health and Human Services (MDHHS).
Where and when to file: This form is to be completed as the written follow-up to the oral report (as required in Sec. 3 (1) of 1975 PA 238, as amended) and sent to Centralized Intake for Abuse & Neglect.
The reporting person is to fill out as completely as possible items 1-12.
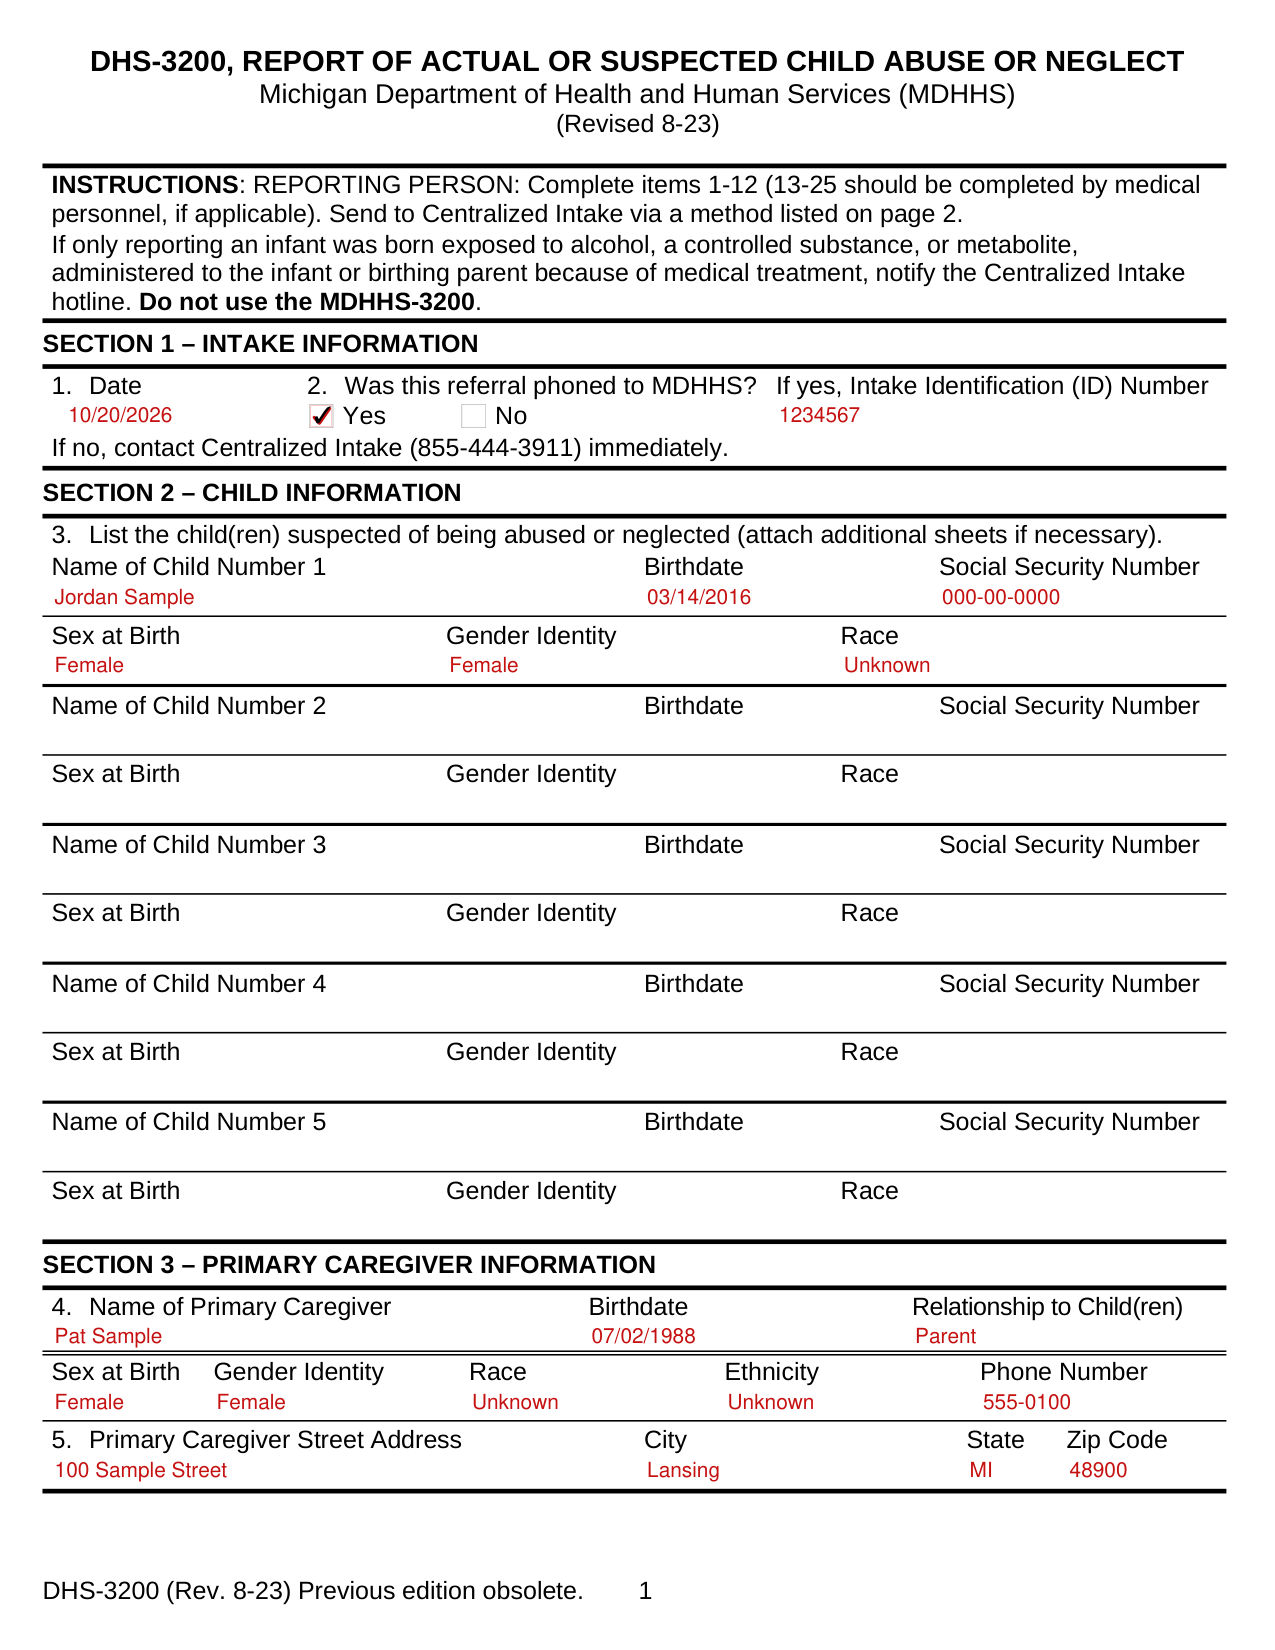
A filled-in Form DHS-3200 example: a teacher fills in page 1
How to fill out Form DHS-3200, box by box
SECTION 1 - INTAKE INFORMATION
Date - Enter the date the form is being completed.
Was this referral phoned to MDHHS? Indicate if this report was phoned into MDHHS as a report of suspected CA/N. If so, indicate the intake # (if known).
If yes, Intake Identification (ID) Number. If no, contact Centralized Intake (855-444-3911) immediately.
SECTION 2 - CHILD INFORMATION
Enter available information for the child(ren) believed to be abused or neglected.
3. List the child(ren) suspected of being abused or neglected (attach additional sheets if necessary). Name of Child Number 1, Birthdate, Social Security Number, Sex at Birth, Gender Identity, Race.
The form also has Name of Child Number 2, Name of Child Number 3, Name of Child Number 4 and Name of Child Number 5.
SECTION 3 - PRIMARY CAREGIVER INFORMATION
Name of primary caregiver - Enter the primary caregiver's name and other available information.
The primary caregiver is an adult, usually a parent or legal guardian living in the household, who assumes the most responsibility for the child's care. When two adult caregivers are present and it is unknown which one assumes the most caretaking responsibility, the adult legally responsible for the children involved in the incident should be selected. If this does not resolve the question, the legally responsible adult identified as the alleged perpetrator should be selected.
4. Name of Primary Caregiver, Relationship to Child(ren), Sex at Birth, Birthdate, Gender Identity, Race, Ethnicity, Phone Number.
Primary caregiver address - Enter the address and phone number of the primary caregiver.
SECTION 4 - ALLEGED PERPETRATOR INFORMATION
Name of alleged perpetrator - Enter the alleged perpetrator's name and other available information.
Alleged perpetrator address - Enter the address and phone number of the alleged perpetrator.
SECTION 5 - ABUSE/NEGLECT INFORMATION
When did the abuse/neglect occur? - Enter the date, or approximate date of when the abuse or neglect occurred.
9. Address where abuse/neglect occurred or description if unknown.
10. Describe injury or conditions and reason of suspicion of abuse or neglect - Indicate the basis for making a report and the information available about the abuse or neglect.
10. What suspected abuse/neglect occurred? Include details of who, what, and how. Attach additional sheets if necessary.
SECTION 6 - REPORTING SOURCE (RS) INFORMATION
11. Reporting Source - Enter name, code, and contact information for the reporting source.
RS Code, Name of Reporting Organization (school, hospital, etc.), Phone Number, Street Address, City, State, Zip Code.
12. Additional Reporting Source - Enter name, code, and contact information for the additional reporting source, if applicable.
SECTION 7 - TO BE COMPLETED BY MEDICAL PERSONNEL WHEN PHYSICAL EXAMINATION HAS BEEN DONE
13. Summary report and conclusions of physical examination, including laboratory and x-ray results (attach medical documentation).
14. Following injuries present.
15. These injuries are (select one): Concerning for physical abuse, Highly concerning for physical abuse, Diagnostic of physical abuse.
16. Is the injury consistent with the history provided by the caretaker(s)? Yes, No, Possibly, Unknown.
17. These injuries caused: Death of a child, Hospitalization required, Medical treatment but no hospitalization, Exam only of alleged injuries - no medical treatment required, Bruises, cuts, abrasions, or other injuries - no medical treatment required. 18. Select if applicable: Child discharged, Child admitted to hospital, Sibling(s) should have medical evaluation(s), Other.
19. If the concern is medical neglect, what is the immediate consequence to the child's health if treatment is not sought or continued? Continued symptoms, Significant complications to health, Severe impairment or death, N/A.
20. Additional information (specify).
21. History or physical signs of previous abuse/neglect: Yes, No.
22. Prior hospitalization or medical examination for this child: Dates, Places.
23. Physician Name and Signature. 24. Date. 25. Hospital (if applicable).
More rules for Form DHS-3200
Completion: Mandatory.
If your situation is different
You are only reporting an infant who was born exposed to alcohol, a controlled substance, or metabolite
Reporting person: Complete items 1-12 (13-25 should be completed by medical personnel, if applicable). If only reporting an infant was born exposed to alcohol, a controlled substance, or metabolite, administered to the infant or birthing parent because of medical treatment, notify the Centralized Intake hotline. Do not use the MDHHS-3200.
Common questions about Form DHS-3200
Where do I file it?
Mail this form to: Centralized Intake for Abuse & Neglect 5303 28th Street Court S.E. Suite A Grand Rapids, MI 49546 Or fax this form to 616-977-1158 or 616-977-1154, or email this form to MDHHS-CPS-CIGroup@michigan.gov.
Is there a penalty?
Penalty: None.
Sources
[1] Form DHS-3200 (Rev. 8-23), Report of Actual or Suspected Child Abuse or Neglect, Michigan Department of Health and Human Services (the Official source link on this page).
