
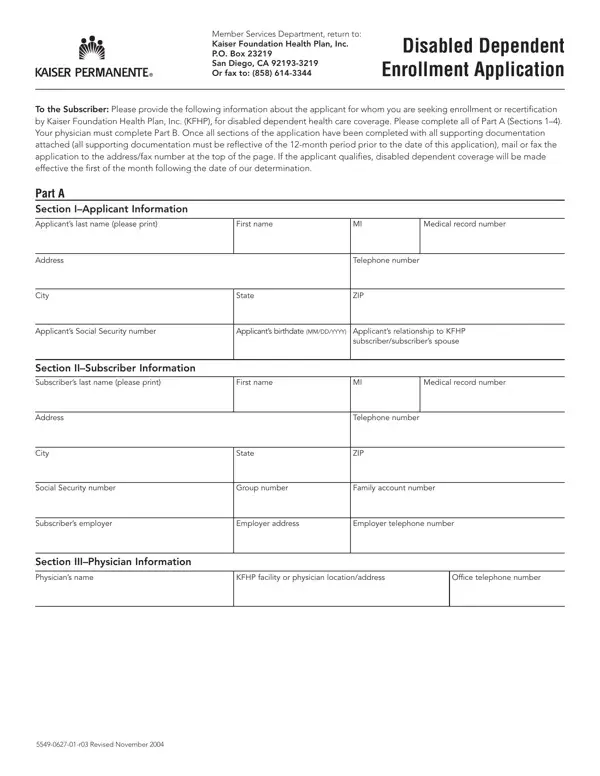
Disabled Dependent Enrollment Application at a glance
What it is: Disabled Dependent Enrollment Application, Member Services Department, Kaiser Foundation Health Plan, Inc.: return to P.O. Box 23219 San Diego, CA 92193-3219 Or fax to: (858) 614-3344.
Who signs: The Subscriber signs on the Subscriber's signature line: SIGN the Subscriber's signature and enter the Date. In Part B, the attending physician signs: SIGN the Attending physician's signature and enter the Date.
A filled-in Disabled Dependent Enrollment Application example: a subscriber applies for her adult son
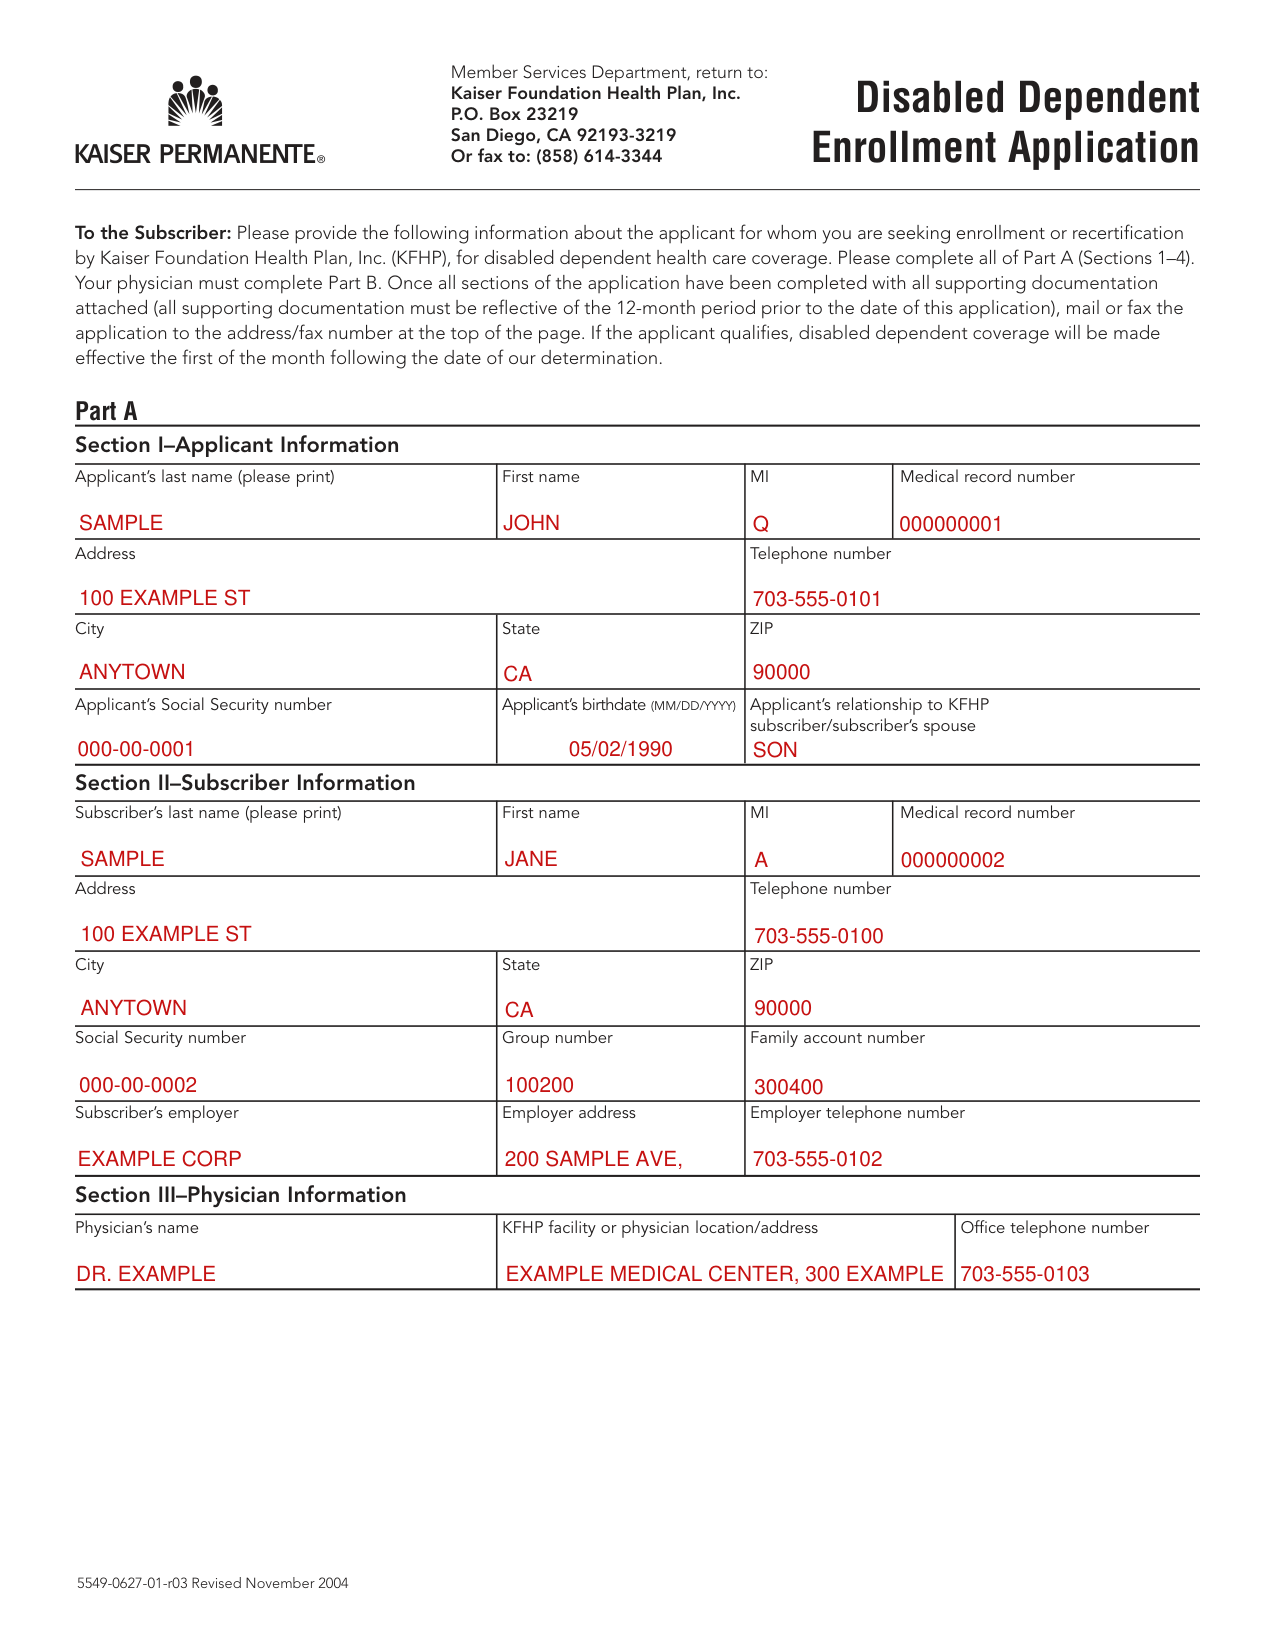
How to fill out Disabled Dependent Enrollment Application, box by box
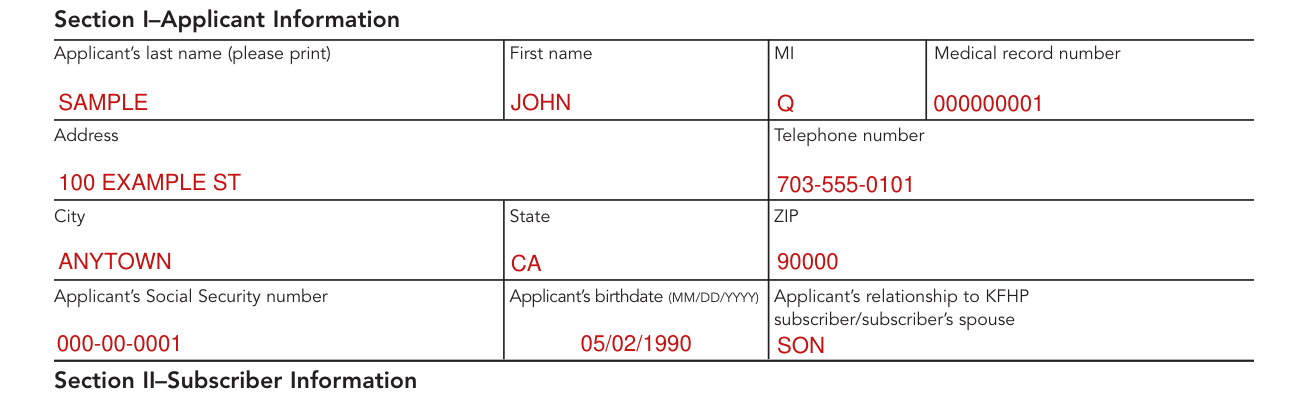
Section I-Applicant Information
To the Subscriber: Please provide the following information about the applicant for whom you are seeking enrollment or recertification by Kaiser Foundation Health Plan, Inc. (KFHP), for disabled dependent health care coverage. Please complete all of Part A (Sections 1-4). Your physician must complete Part B. Once all sections of the application have been completed with all supporting documentation attached (all supporting documentation must be reflective of the 12-month period prior to the date of this application), mail or fax the application to the address/fax number at the top of the page. If the applicant qualifies, disabled dependent coverage will be made effective the first of the month following the date of KFHP's determination.
Enter the Applicant's last name (please print), First name, MI and Medical record number.
In Section I, enter the Address, Telephone number, City, State and ZIP.
Enter the Applicant's Social Security number, Applicant's birthdate (MM/DD/YYYY) and Applicant's relationship to KFHP subscriber/subscriber's spouse.
Section II-Subscriber Information
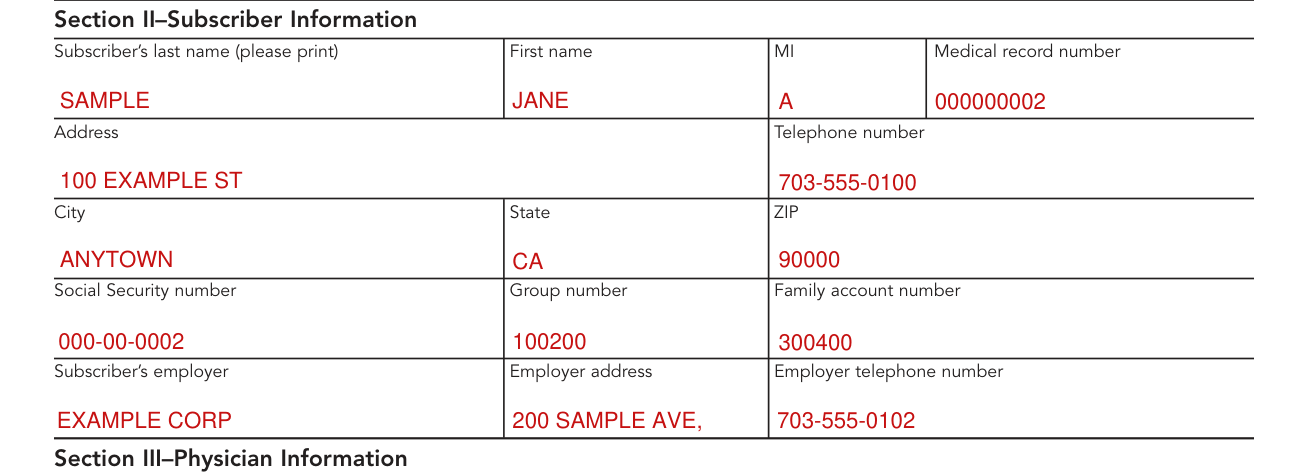
Enter the Subscriber's last name (please print), First name, MI and Medical record number.
In Section II, enter the Address, Telephone number, City, State and ZIP.
Enter the Social Security number, Group number and Family account number.
Enter the Subscriber's employer, Employer address and Employer telephone number.
Section III-Physician Information

Enter the Physician's name, KFHP facility or physician location/address and Office telephone number.
Section IV-Subscriber Questionnaire
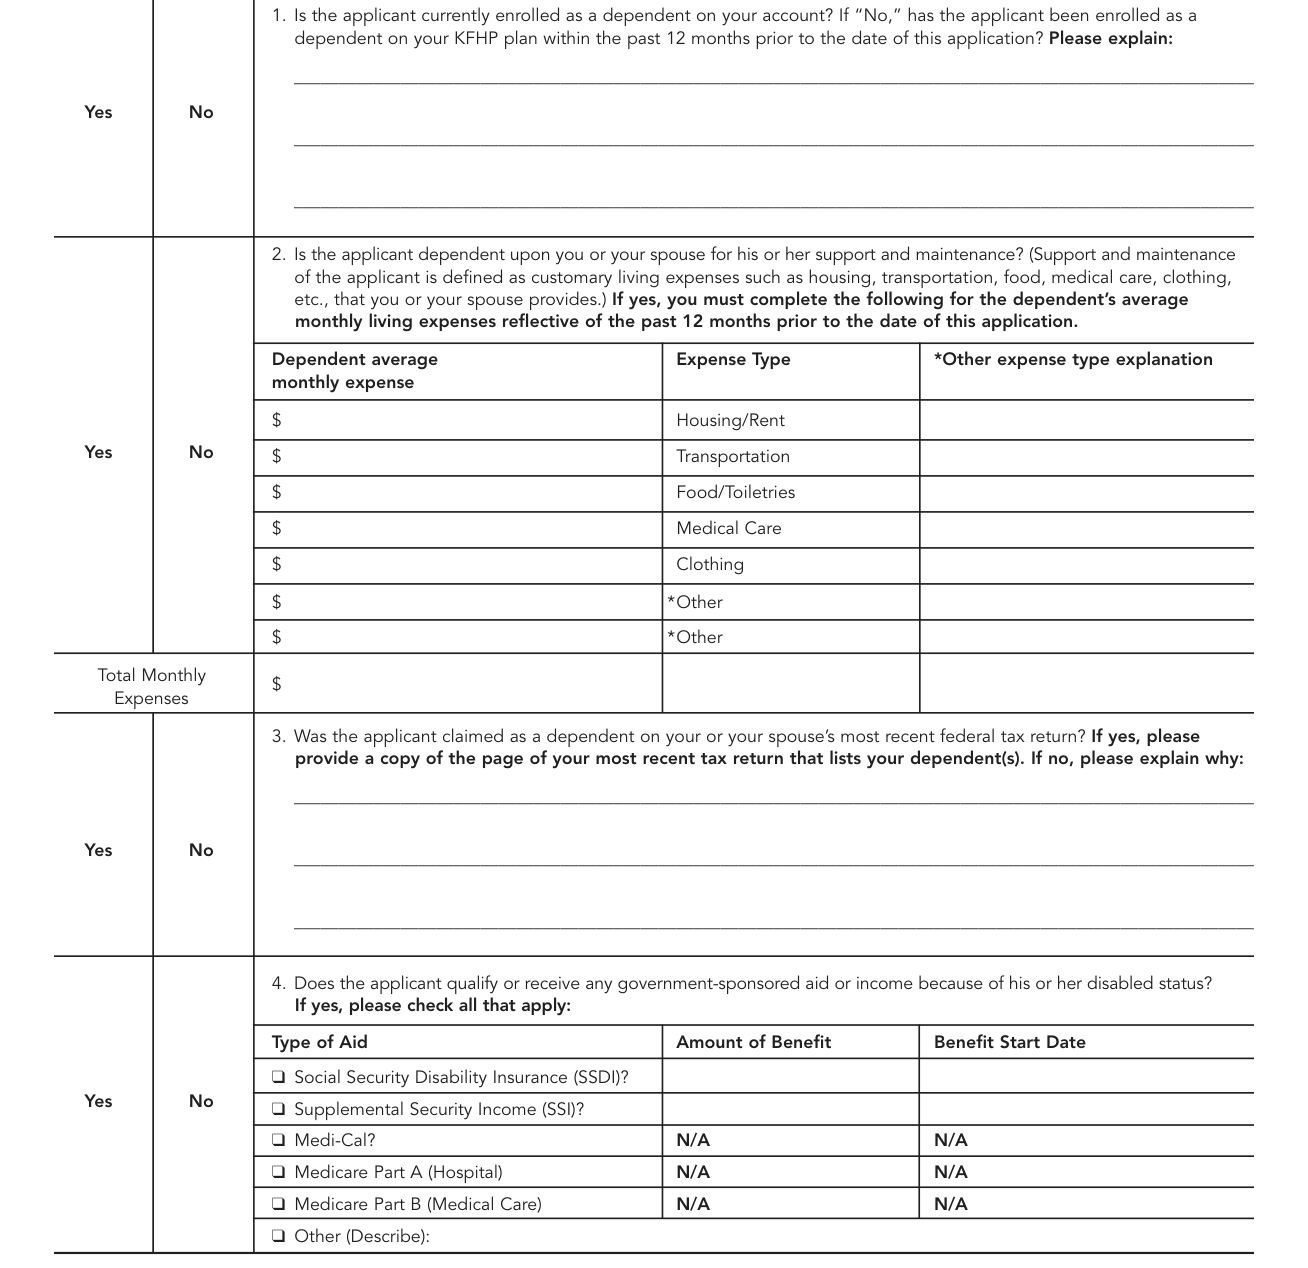
Please read each of the following statements carefully. Indicate a "Yes" or "No" response to the statements in Section IV.
1. Is the applicant currently enrolled as a dependent on your account? If "No," has the applicant been enrolled as a dependent on your KFHP plan within the past 12 months prior to the date of this application? Please explain.
2. Is the applicant dependent upon you or your spouse for his or her support and maintenance? (Support and maintenance of the applicant is defined as customary living expenses such as housing, transportation, food, medical care, clothing, etc., that you or your spouse provides.)
If yes, you must complete the following for the dependent's average monthly living expenses reflective of the past 12 months prior to the date of this application.
Enter the Dependent average monthly expense and the *Other expense type explanation for each Expense Type: Housing/Rent, Transportation, Food/Toiletries, Medical Care, Clothing, * Other and * Other, then the Total Monthly Expenses.
3. Was the applicant claimed as a dependent on your or your spouse's most recent federal tax return? If yes, please provide a copy of the page of your most recent tax return that lists your dependent(s). If no, please explain why.
4. Does the applicant qualify or receive any government-sponsored aid or income because of his or her disabled status? If yes, please check all that apply.
Check each Type of Aid that applies. For Social Security Disability Insurance (SSDI) and Supplemental Security Income (SSI), enter the Amount of Benefit and Benefit Start Date. Medi-Cal, Medicare Part A (Hospital) and Medicare Part B (Medical Care) print N/A N/A. For Other (Describe), describe the aid.
Section IV-Subscriber Questionnaire (continued)
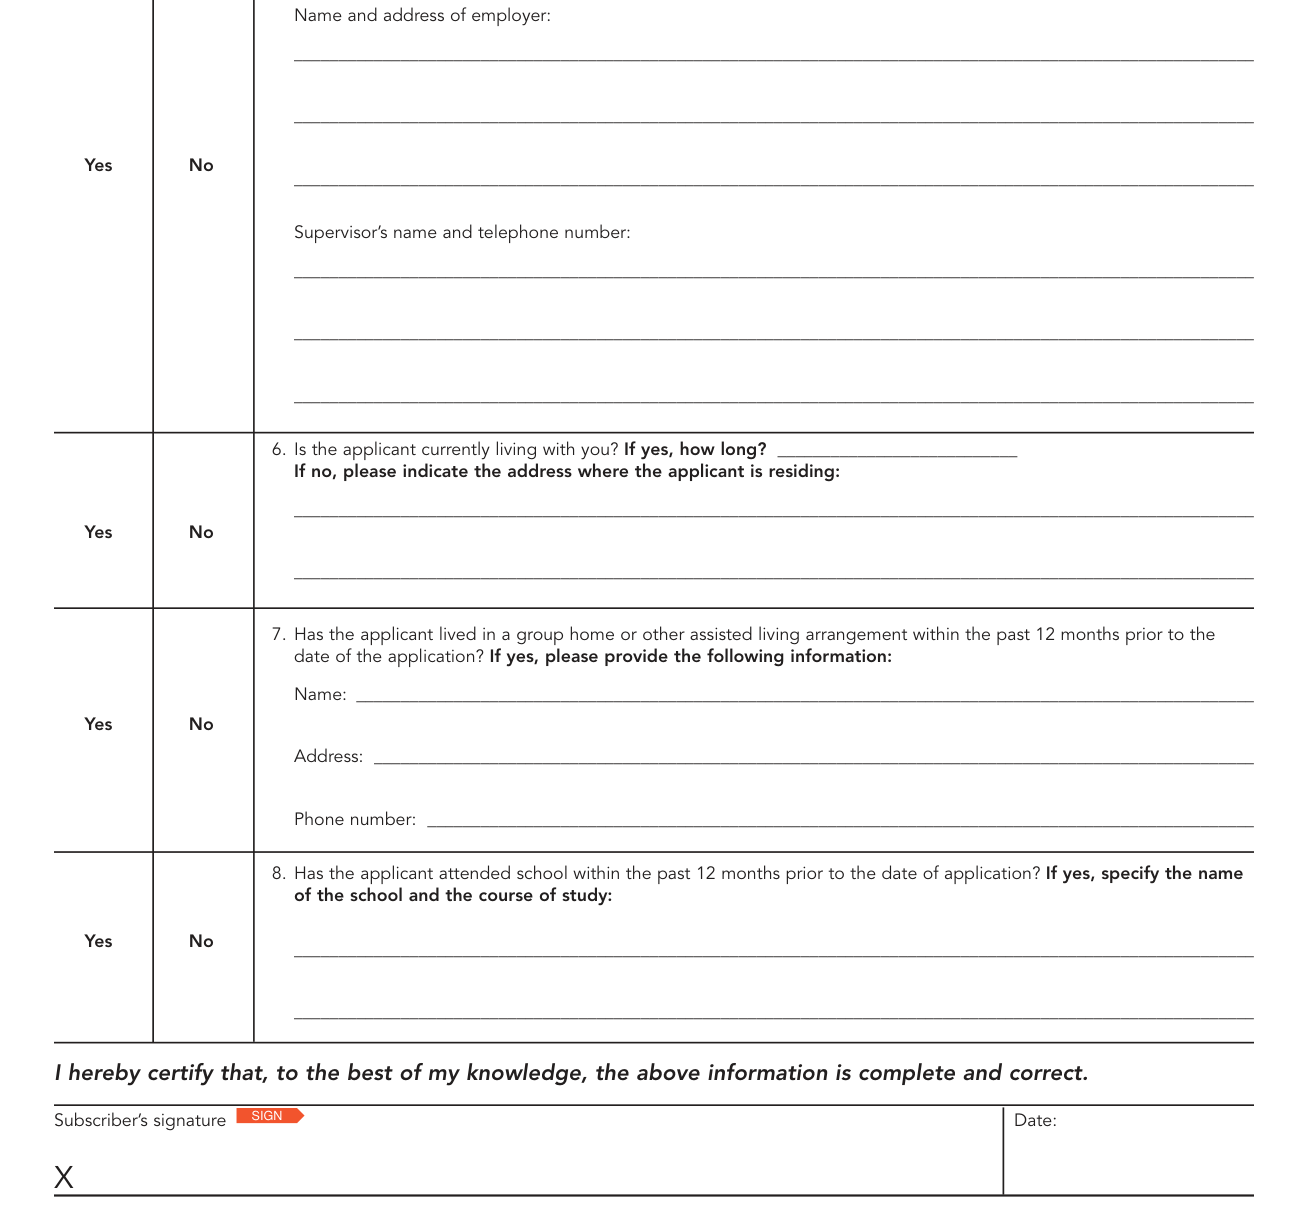
5. Has the applicant worked, including sheltered work, within the past 12 months prior to the end date of the application? If yes, please attach proof of the applicant's earnings for the past 12 months from the date of this application and provide the following information: Name and address of employer.
Enter the Supervisor's name and telephone number.
6. Is the applicant currently living with you? If yes, how long? If no, please indicate the address where the applicant is residing.
7. Has the applicant lived in a group home or other assisted living arrangement within the past 12 months prior to the date of the application? If yes, please provide the following information: Name, Address and Phone number. 8. Has the applicant attended school within the past 12 months prior to the date of application? If yes, specify the name of the school and the course of study.
By signing you certify that, to the best of your knowledge, the information is complete and correct.
Part B Section I-To be completed by applicant's physician

The following information is needed for use in connection with an application for continued health insurance coverage for a disabled dependent. Please provide your full reply and describe the nature and severity of the impairment.
NOTICE TO PHYSICIAN: PLEASE TYPE OR PRINT. Enter the Applicant's last name, first name and Medical record number, and the Subscriber's last name, first name and Medical record number.
The clinical description of applicant's condition, including diagnosis and prognosis causing disability and description of limitations and the physician comments must be completed by physician. To add more comments, please attach additional documentation.
Please provide answers to the following questions. 1) Date disability occurred.
2) In your medical opinion, is the disability: Mental retardation Yes No, Physical handicap Yes No, Biologically based psychiatric disorder Yes No.
3) In your medical opinion, is the disability likely to improve? Yes No.
4) In your medical opinion (choose one): Yes, the applicant is capable of self-sustaining employment, or No, the applicant is not capable of self-sustaining employment.
In Part B, the attending physician signs: SIGN the Attending physician's signature and enter the Date.
Enter the Physician's printed name, KFHP facility or physician's mailing address, City, ZIP and Physician's office telephone number.
If Part A has been completed in full and all supporting documentation is included, you may mail or fax this application to the address and fax number at the top of the page.
Statement of Authorized Representative
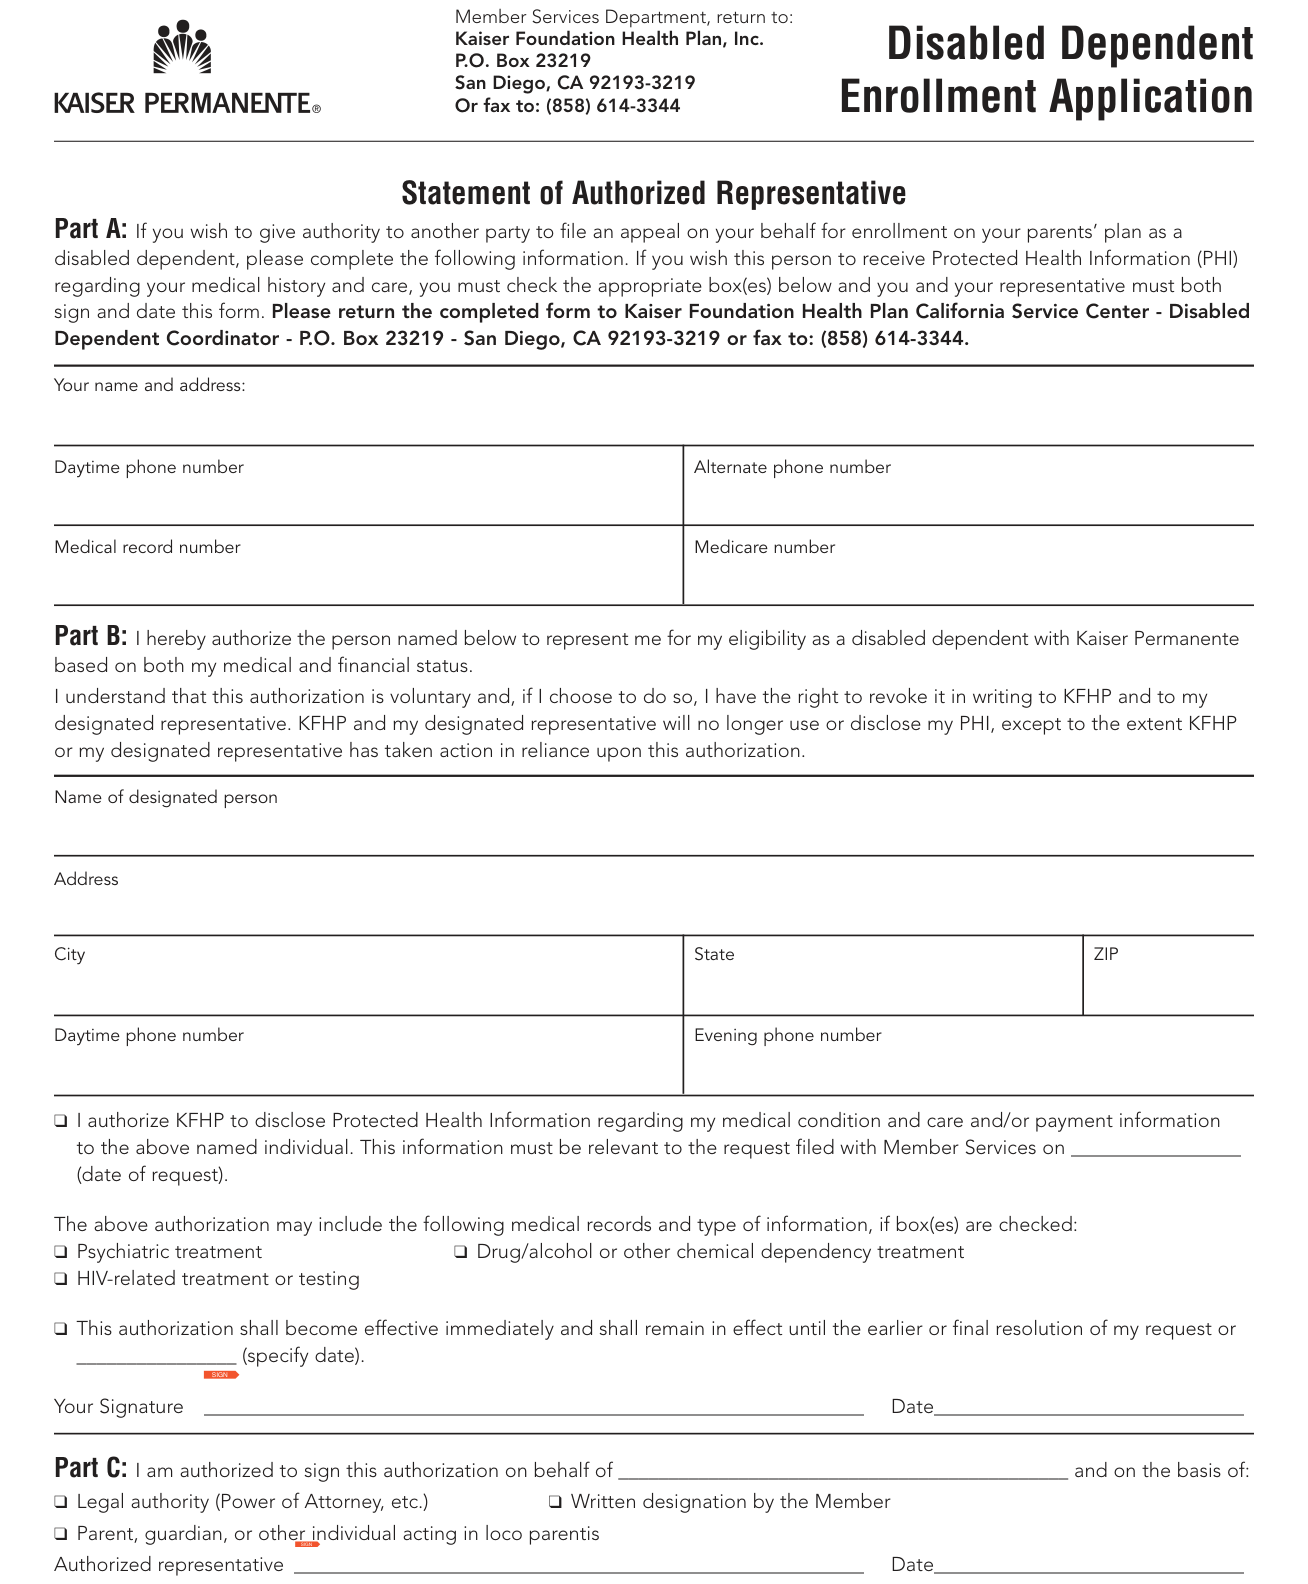
Part A: If you wish to give authority to another party to file an appeal on your behalf for enrollment on your parents' plan as a disabled dependent, please complete the following information. If you wish this person to receive Protected Health Information (PHI) regarding your medical history and care, you must check the appropriate box(es) and you and your representative must both sign and date this form.
Please return the completed form to Kaiser Foundation Health Plan California Service Center - Disabled Dependent Coordinator - P.O. Box 23219 - San Diego, CA 92193-3219 or fax to: (858) 614-3344.
Enter Your name and address, Daytime phone number, Alternate phone number, Medical record number and Medicare number.
Part B: Enter the Name of designated person, Address, City, State, ZIP, Daytime phone number and Evening phone number.
I authorize KFHP to disclose Protected Health Information regarding my medical condition and care and/or payment information to the named individual. This information must be relevant to the request filed with Member Services on (date of request).
This authorization may include the following medical records and type of information, if box(es) are checked: Psychiatric treatment, Drug/alcohol or other chemical dependency treatment, HIV-related treatment or testing.
This authorization shall become effective immediately and shall remain in effect until the earlier or final resolution of my request or (specify date).
SIGN Your Signature and enter the Date.
Part C: I am authorized to sign this authorization on behalf of ______ and on the basis of: Legal authority (Power of Attorney, etc.), Written designation by the Member, or Parent, guardian, or other individual acting in loco parentis. SIGN the Authorized representative line and enter the Date.
More rules for Disabled Dependent Enrollment Application
You must provide all information requested in order for your application to be processed. If you need more space, attach a separate sheet of paper.
Sources
[1] Disabled Dependent Enrollment Application, Revised November 2004 (the served file; no issuer file found) (the Official source link on this page).