


Form LS-1 at a glance
What it is: U.S. Department of Labor Office of Workers' Compensation Programs Request for Examination and/or Treatment.
Where and when to file: Mail the original to the Office of Workers' Compensation Programs (see Item 12 for address), and a copy to the company listed In Item 13 with charges for your services on a standard billing form.
Instructions to Employer. Part A of the form must be completed in full, and authorizes a physician of the employee's choice to examine and/or treat an employee, covered by the Federal Workers' Compensation Act marked in the box, for accidental injury, illness or disease arising out of and in the course or employment.
A filled-in Form LS-1 example: an employer authorizes treatment after a back injury

How to fill out Form LS-1, box by box
Authorization for examination and/or treatment under the Workers' Compensation Act

Box 1: This Authorization is for examination and/or treatment under the Workers' Compensation Act marked below: A Longshore and Harbor Workers' Compensation Act, B Defense Base Act, C Nonappropriated Fund Instrumentalities Act, or D Outer Continental Shelf Lands Act.
An employee may not select a physician who is currently not authorized by the Department of Labor to provide medical care under the Act.
Name and address of physician or medical facility authorized to provide medical service

Instructions to Employer, Box 2: Enter the name and address of physician or medical facility authorized to provide medical service * (The term "physician" includes doctors of medicine (MD), surgeons, podiatrists, dentists, clinical psychologists, optometrists, osteopathic practitioners, and chiropractors. Payment for chiropractic services is limited to charges for physical examinations, related laboratory tests, x-rays to diagnose a subluxation of the spine, and treatment consisting of manipulation of the spine to correct a subluxation demonstrated by x-ray. See 20 CFR 702.404)
Employee's name, date of injury, occupation and how the accident or illness occurred
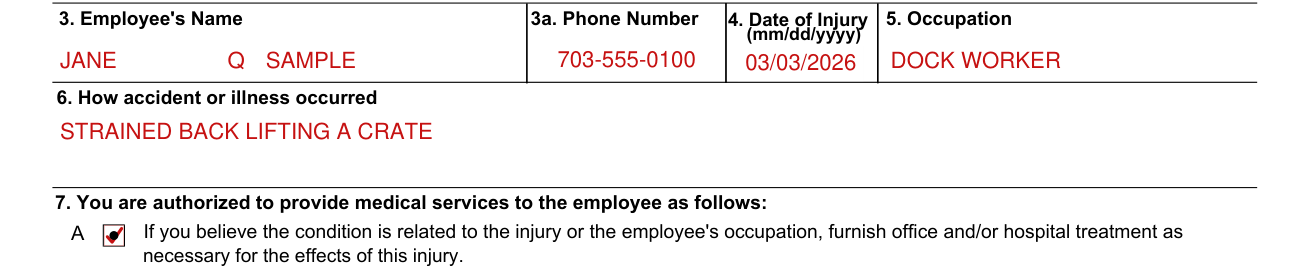
Box 3: Enter the Employee's Name and 3a. Phone Number. Box 4: Enter the Date of Injury (mm/dd/yyyy). Box 5: Enter the Occupation.
Box 6: Enter how accident or illness occurred.
You are authorized to provide medical services to the employee as follows

Box 7, box A: If you believe the condition is related to the injury or the employee's occupation, furnish office and/or hospital treatment as necessary for the effects of this injury.
Box 7, box B: If you are in doubt as to whether the condition(s) found on examination is related to the injury, you are authorized to examine the employee, using indicated non-surgical diagnostic studies, and should promptly advise those listed in item 13 whether you believe the disability is due to the alleged injury. Pending further advice you may provide necessary conservative treatment.
You are requested to submit a written report of first treatment within 10 days to the Office of Workers' Compensation Programs. See item 12 below (See back of this form for Instructions as to medical report and the submission of your charges).
Signature and title of authorizing official, employer and date authorized

Box 8: Sign the Signature and title of authorizing official (Sign all copies). Box 9: Enter the Name and address of employer. Box 10: Enter the Telephone number of authorizing official (Area code and local number). Box 11: Enter the Date authorized (mm/dd/yyyy).
Name and address of insurance carrier or self-insured employer
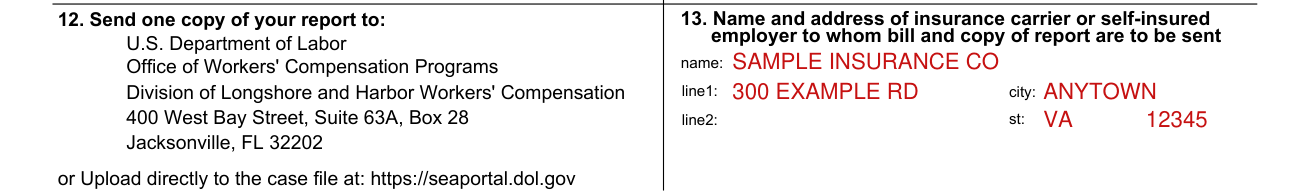
Box 13: Enter the Name and address of insurance carrier or self-insured employer to whom bill and copy of report are to be sent.
Box 12: Send one copy of your report to: U.S. Department of Labor Office of Workers' Compensation Programs Division of Longshore and Harbor Workers' Compensation 400 West Bay Street, Suite 63A, Box 28 Jacksonville, FL 32202 or Upload directly to the case file at: https://seaportal.dol.gov
History, findings, diagnosis and cause

Part B - Attending Physician's Report of Injury and Treatment Instructions To Physician: This initial report should be completed and submitted within 10 days.
14. What history of injury or disease did employee give you?
15. Is there any history or evidence of pre-existing injury, disease, or physical impairment? Check Yes - Please describe, or No.
16. What are your findings (include results of x-rays, laboratory tests, etc.)? 17. What is your diagnosis?
18. Do you believe the condition found was caused or aggravated by the employment activity described? (Please explain your answer.) Check No or Yes.
Hospitalization
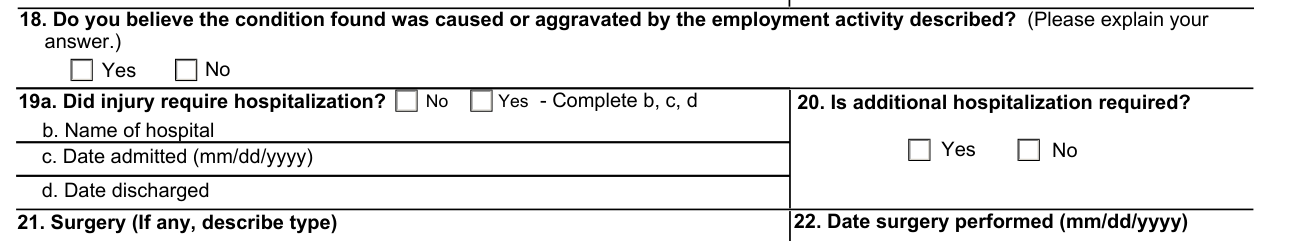
19a. Did injury require hospitalization? - Complete b, c, d. Check Yes or No. b. Name of hospital, c. Date admitted (mm/dd/yyyy) and d. Date discharged.
20. Is additional hospitalization required? Check Yes or No.
Surgery, treatment and permanent effects
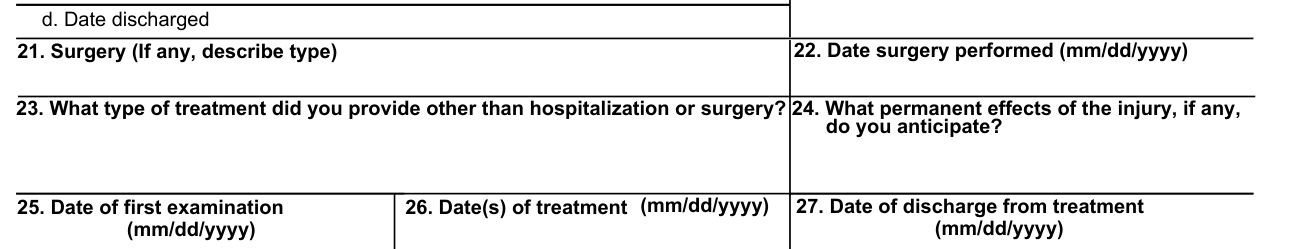
21. Surgery (If any, describe type). 22. Date surgery performed (mm/dd/yyyy).
23. What type of treatment did you provide other than hospitalization or surgery? 24. What permanent effects of the injury, if any, do you anticipate?
Dates of examination, treatment, discharge and disability

Enter 25. Date of first examination, 26. Date(s) of treatment and 27. Date of discharge from treatment, each as (mm/dd/yyyy).
28. Period of disability (if termination date unknown - so indicate): Total disability From To, Partial disability From To. 29. Date employee able to resume work: To light work, To regular work.
30. If employee is able to resume work, has he/she been advised? Furnish date advised (mm/dd/yyyy). Check Yes - No.
Physical limitations, remarks and specialty
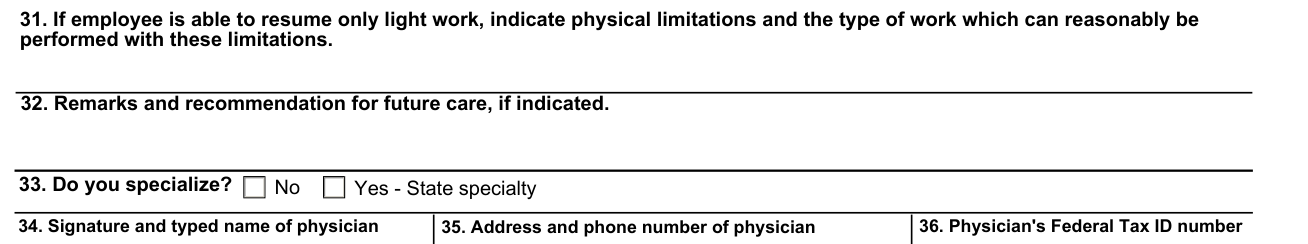
31. If employee is able to resume only light work, indicate physical limitations and the type of work which can reasonably be performed with these limitations.
32. Remarks and recommendation for future care, if indicated.
33. Do you specialize? Check Yes - State specialty, or No.
Signature, address and Federal Tax ID number of physician

34. Signature and typed name of physician. 35. Address and phone number of physician.
36. Physician's Federal Tax ID number. 37. Date of this report (mm/dd/yyyy).
More rules for Form LS-1
Mark either box A or B in item 7. The original and two copies of this form are to be given to the physician. The physician is to complete the medical report and the initial bill on the reverse, sending within ten days the original of the report to the Office of Workers' Compensation Programs and copies to the insurance company or employer named in item 13. Subsequent and regular follow-up reports should be submitted by the physician on Form LS-204 and/or in narrative reports, whenever requested.
Subsequent reports should be made regularly on form LS-204 and/or in narrative form while the employee is in your care.
Sources
[1] Form LS-1 (Rev. Nov 2023), Request for Examination and/or Treatment, U.S. Department of Labor Office of Workers' Compensation Programs (the Official source link on this page).