

Form DS 1891 at a glance
What it is: DS 1891 is the Applicant/Vendor Disclosure Statement of the California Department of Developmental Services, submitted as part of a complete application packet for vendorization.
Who signs: Enter the Name of Applicant/Vendor or Authorized Representative, Title and Date, and sign under Signature. Subject to the provisions of Title 17, California Code of Regulations, Section 54311 and Code of Federal Regulations, Title 42, Part 455.105, an applicant or vendored provider agrees to provide access for the review of any and all ownership disclosure information and/or documentation upon written request by the vendoring regional center, the Department of Developmental Services, the State Medicaid Agency, Department of Health Care Services, any State survey team, the Secretary of the United States Department of Health and Human Services, or any duly authorized representatives of the above named entities.
Every applicant or vendor must complete and submit a current Applicant/Vendor Disclosure Statement, DS 1891 (disclosure statement) as part of a complete application packet for vendorization or upon request of the vendoring regional center.
A filled-in Form DS 1891 example: a parent completes Part 1

How to fill out Form DS 1891, box by box
Part 1. Applicant/Vendor Information
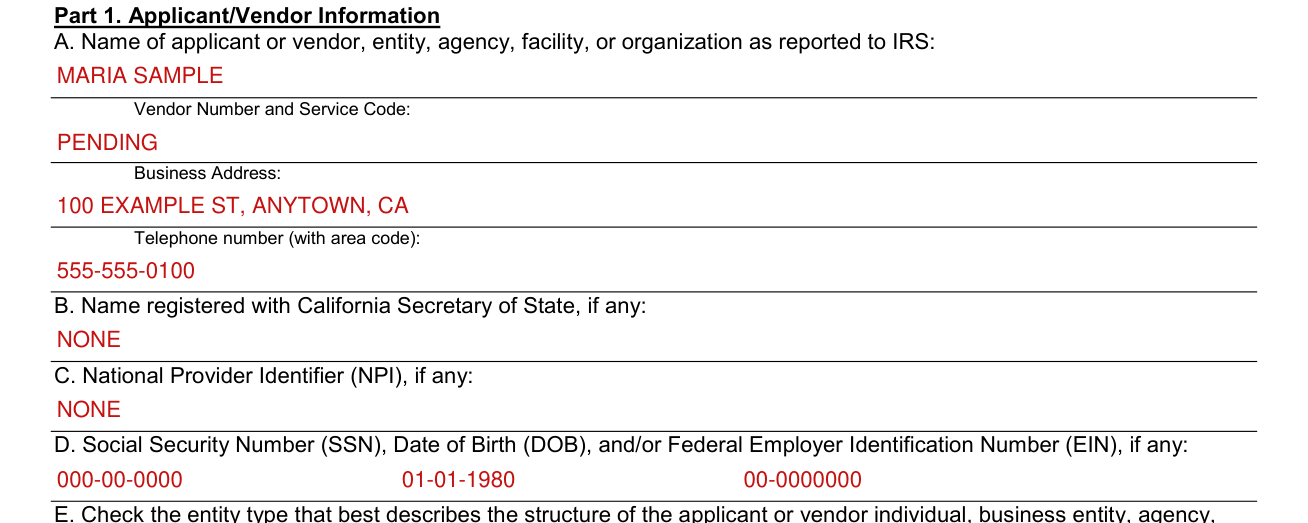
Specify name of the applicant or vendor, agency, facility or organization, vendor number and service code, business address, and telephone number of applicant or vendor submitting the vendor application. Telephone number (with area code).
Specify in what capacity the applicant or vendor is doing business. For example: The name of the corporation under which they are doing business. This name must match the license name, if applicable. Name registered with California Secretary of State, if any.
List the National Provider Identifier, of the applicant or vendor, if any.
List the Social Security Number, Date of Birth, and/or the Federal Employer Identification Number (EIN) of the applicant or vendor, if any. Enter Vendor's nine-digit EIN assigned by the IRS in the format XX-XXXXXXX.
Parent or Consumer, and the entity type
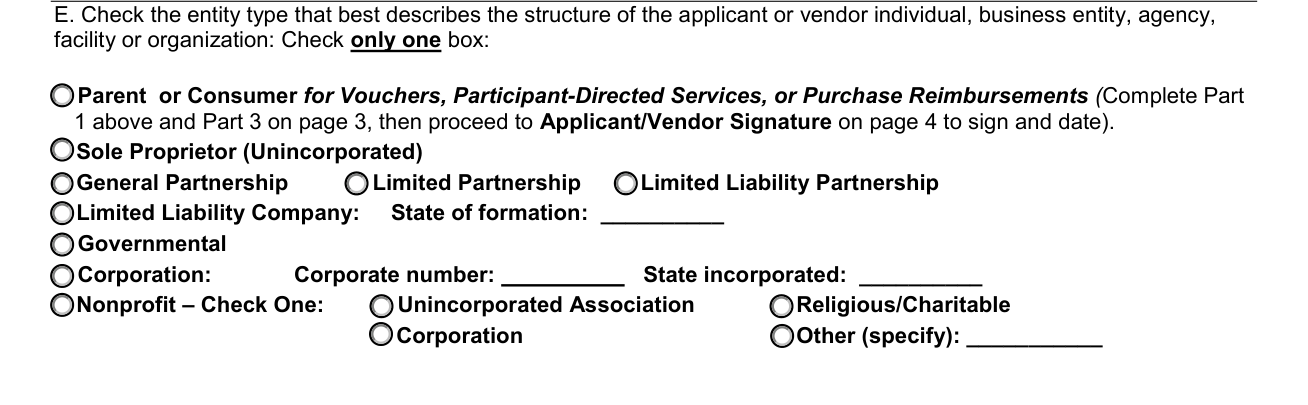
Check the entity type that best describes the structure of the applicant or vendor individual, business entity, agency, facility or organization: Check only one box: Parent or Consumer for Vouchers, Participant-Directed Services, or Purchase Reimbursements (Complete Part 1 above and Part 3 on page 3, then proceed to Applicant/Vendor Signature on page 4 to sign and date). If you check Limited Liability Company, enter the State of formation. If you check Corporation, enter the Corporate number and State incorporated. Under Nonprofit, Check One: Unincorporated Association, Religious/Charitable, Corporation or Other (specify).
Part 2. A. Ownership, indirect ownership, and managing employee interests
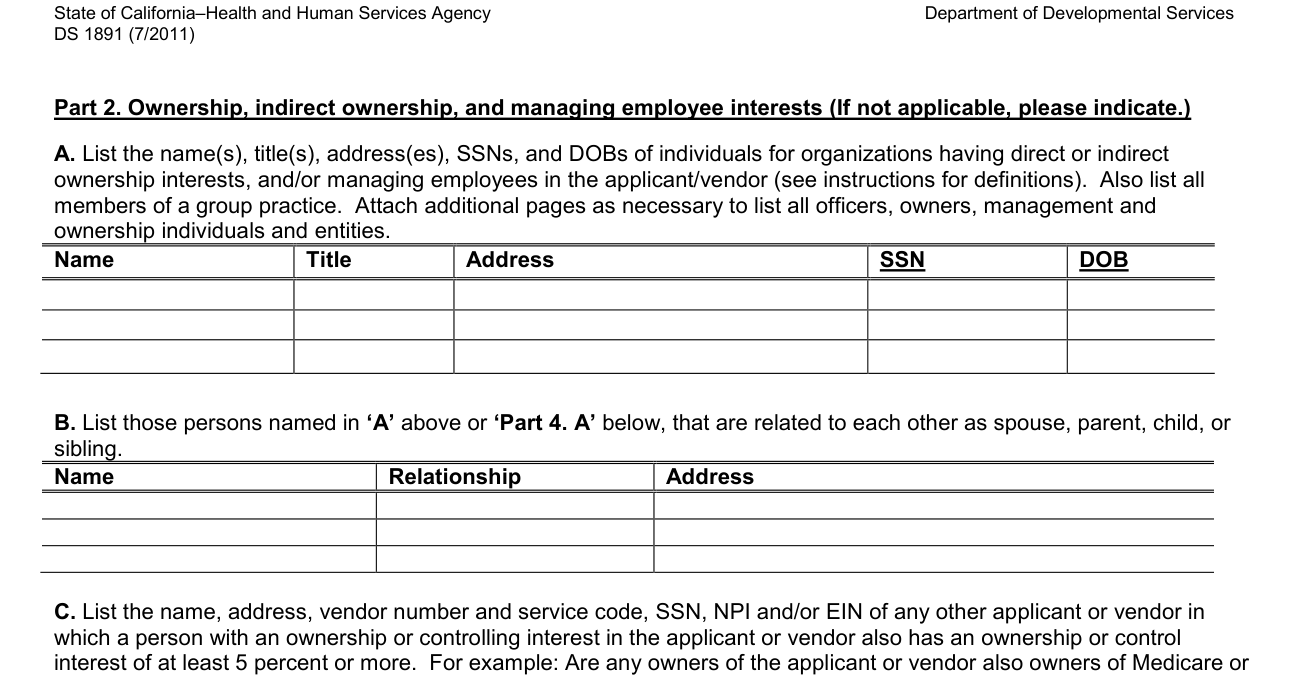
In Part 2. A., list the name(s), title(s), address(es), SSNs, and DOBs of individuals for organizations having direct or indirect ownership interests, and/or managing employees in the applicant/vendor (see instructions for definitions). If not applicable, please indicate.
Also list all members of a group practice. Attach additional pages as necessary to list all officers, owners, management and ownership individuals and entities.
“Ownership Interest” means the possession of equity in the capital, the stock, or the profits of the applicant or vendor.
“Managing Employee” means a general manager, business manager, administrator, director, or other individual who exercises operational or managerial control over, or who directly or indirectly conducts the day-to-day operation of an institution, organization, agency or business entity;
Part 2. B. Persons related to each other

List those persons named in A or in Part 4. A. that are related to each other as spouse, parent, child, or sibling. Enter Name, Relationship and Address.
Part 2. C. Other applicants or vendors with an ownership or control interest
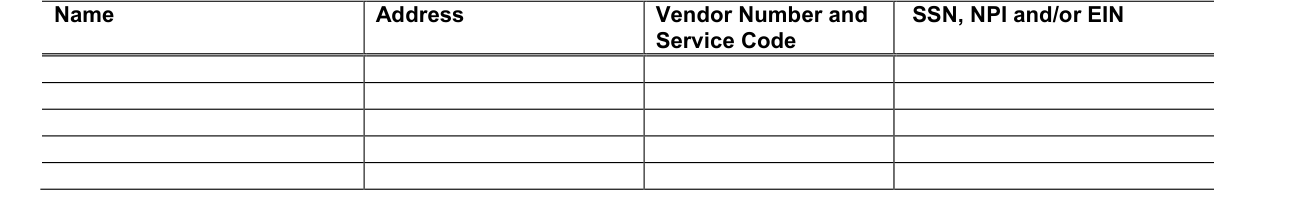
List the name, address, vendor number and service code, SSN, NPI and/or EIN of any other applicant or vendor in which a person with an ownership or controlling interest in the applicant or vendor also has an ownership or control interest of at least 5 percent or more. For example: Are any owners of the applicant or vendor also owners of Medicare or Medicaid facilities? (Example: sole proprietor, partnership or members of Board of Directors.)
Part 3. Excluded Individuals or Entities

In Part 3. Excluded Individuals or Entities (If not applicable, please indicate.), list the name, title, and address of any person, as applicant or vendor, or entity with an ownership or control interest, any agent, director, officer, or managing employee of the applicant or vendor who is an excluded individual or entity, as defined on page 2.
“Excluded Individuals or Entities” means those individuals and entities that have been placed on either the U.S. Department of Health and Human Services Office of Inspectors' General (OIG) List of Excluded Individuals/Entities or the Department of Health Care Services (DHCS) Medi-Cal Suspended and Ineligible Provider List of persons, or individuals and entities that have been convicted of a criminal offense related to involvement in any program under Medicare, Medicaid or the Title XX services program, or those individuals and entities that meet the criteria included in Title 17, Section 54311(a)(6).
Part 4. A. Subcontractor

In Part 4. Subcontractor (If not applicable, please indicate.), A. list the name, title, address, SSN, NPI and/or EIN of each person or entity with an ownership or control interest in any subcontractor in which the applicant or vendor has direct or indirect ownership of 5 percent or more. State percentage.
“Subcontractor” means an individual, agency, or organization to which an applicant or vendor has contracted or delegated some of the management functions or responsibilities of providing services.
Part 4. B. Significant business transactions

List the name, title, address, SSN, NPI and/or EIN of each subcontractor or wholly owned supplier in which the applicant or vendor has had any significant business transactions within 5 years of the application or request.
“Significant Business Transaction” means any business transaction or series of transactions that, during any one fiscal year, exceed the lesser of $25,000 and 5 percent of an applicant or vendor's total operating expenses. (checked November 11, 2026)
“Wholly Owned Supplier” means a supplier whose total ownership interest is held by an applicant or vendor or by a person, persons, or other entity with an ownership or control interest in an applicant or vendor.
Applicant/Vendor Signature

By signing this disclosure statement, you hereby certify and swear under penalty of perjury that (a) you have knowledge concerning the information in this disclosure statement, and (b) the information in this disclosure statement is true and accurate.
You agree to inform the vendoring Regional Center, in writing, within 30 days of any changes or if additional information becomes available.
Knowingly and willfully failing to fully and accurately disclose the information requested may result in denial of a request to become vendored, or if the service provider already is vendored, a termination of its vendorization.
More rules for Form DS 1891
It is essential that all applicable questions be answered accurately and that all information be current. Answer all questions as of the current date.
Type or print clearly in ink.
If applicant or vendor must make corrections, please line through, date, and initial in ink. Do not use correction fluid.
If additional space is needed, attach a sheet referencing the part and question being completed.
Failure to disclose complete and accurate information will result in a denial of enrollment and/or may be cause for termination of vendorization.
Common questions about Form DS 1891
Where do I file it?
Return this completed statement with the complete application package to the regional center to which you are applying.
Sources
[1] Form DS 1891 (7/2011), Applicant/Vendor Disclosure Statement, California Department of Developmental Services (the Official source link on this page).