


Form DEU 101 at a glance
What it is: The Request for Summary Rating Determination of Qualified Medical Evaluator's Report is a State of California Division of Workers' Compensation Disability Evaluation Unit form.
Where and when to file: INSTRUCTIONS TO THE PHYSICIAN: 1. If the employee is unrepresented, review and comment upon the Employee's Disability Questionnaire, (DEU Form 100), in your report. (If the employee does not have a completed Form 100 at the time of the appointment, please provide the form to the employee.) 2. Submit your completed medical evaluation and, if the employee is unrepresented, the DEU Form 100, to the Disability Evaluation Unit district office listed under Submit To. PLEASE USE THIS FORM AS A COVER SHEET FOR SUBMISSION TO THE DISABILITY EVALUATION UNIT. 3. Serve a copy of your report and the Form 100 upon the claims administrator and the employee.
INSTRUCTIONS TO THE CLAIMS ADMINISTRATOR: 1. Use this form if employee is unrepresented and has not filed an application for adjudication. 2. Complete this form and forward it along with a complete copy of all medical reports and medical records concerning this case to the physician scheduled to evaluate the existence and extent of permanent impairment or disability. 3. Send the EMPLOYEE'S DISABILITY QUESTIONNAIRE, DEU FORM 100 to the employee in time for the medical evaluation. 4. This form must be served on the employee prior to the evaluation. Be sure to complete the proof of service.
A filled-in Form DEU 101 example: a claims administrator requests a summary rating

How to fill out Form DEU 101, box by box
Date of first medical report and last temporary disability date

Enter the Date of first medical report indicating the existence of permanent impairment or disability and the Last date for which temporary disability indemnity was paid, as MM/DD/YYYY.
Submit To: Disability Evaluation Unit

Under Submit To: Disability Evaluation Unit, enter the Address/PO Box, City and Zip Code.
Physician and Exam Date

Enter the Physician and the Exam Date as MM/DD/YYYY.
Claims Administrator

Under Claims Administrator, enter the Company Name, Street Address1/PO Box, Street Address2/PO Box, Zip Code, State and City. Please leave blank spaces between numbers, names or words.
Claim numbers, phone, adjustor and employer
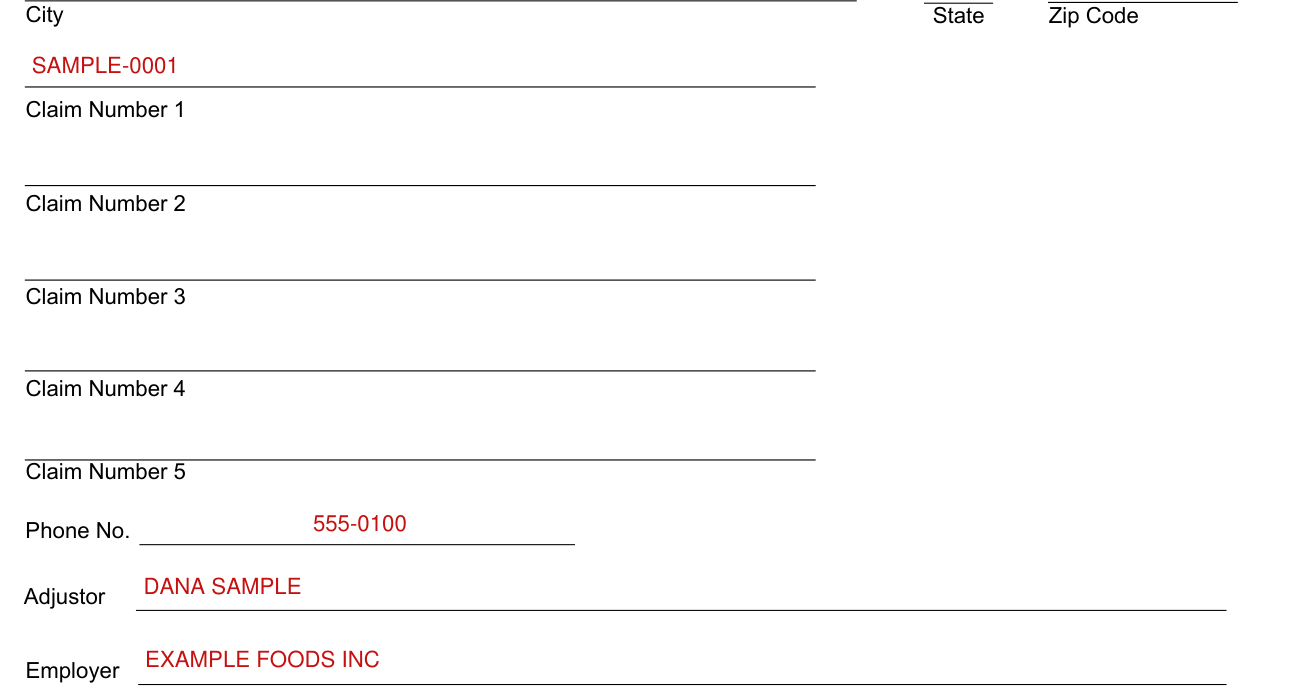
Enter Claim Number 1, Claim Number 2, Claim Number 3, Claim Number 4 and Claim Number 5, then the Phone No., Adjustor and Employer.
Employee name and address

Under Employee, enter the First Name, Last Name, Street Address 1/PO Box, Street Address 2/PO Box and International Address.
Enter the City, Zip Code and State.
Date of Injury, Date of Birth, SSN and Case No

Enter the Date of Injury and the Date of Birth as MM/DD/YYYY.
Enter the SSN (Numbers Only).
Enter the Case No (if any).
Occupation and weekly gross earnings

Enter the OCCUPATION. Please attach job description or job analysis, if available.
Enter the WEEKLY GROSS EARNINGS. Attach a wage statement/DLSR 5020 if earnings are less than maximum.
Include the value of additional advantages provided such as meals, lodging, etc. If earnings are irregular or for less than 30 hours per week, include a detailed description of all earnings of the employee from all sources, including other employers, for one year prior to the date of injury.
Benefits will be calculated at MAXIMUM RATE unless a complete and detailed statement of earnings is attached.
Common questions about Form DEU 101
What am I certifying when I sign?
PROOF OF SERVICE BY MAIL (11/2008): You state that you served a copy of this Request for Summary Rating Determination on the employee by placing a true copy enclosed in a sealed envelope with postage fully prepaid, and deposited in the U.S. Mail. "I declare under penalty of perjury under the laws of the State of California that the foregoing is true and correct."
Sources
[1] Form DWC-AD 101 (DEU) (REV. 11/2008), Request for Summary Rating Determination of Qualified Medical Evaluator's Report, California Division of Workers' Compensation (the Official source link on this page).