

Form DWC003 at a glance
What it is: DWC003 is the Employer's wage statement.
Who signs: SIGN. Signature and Date.
A filled-in Form DWC003 example: an employer reports 13 weeks of hourly wages
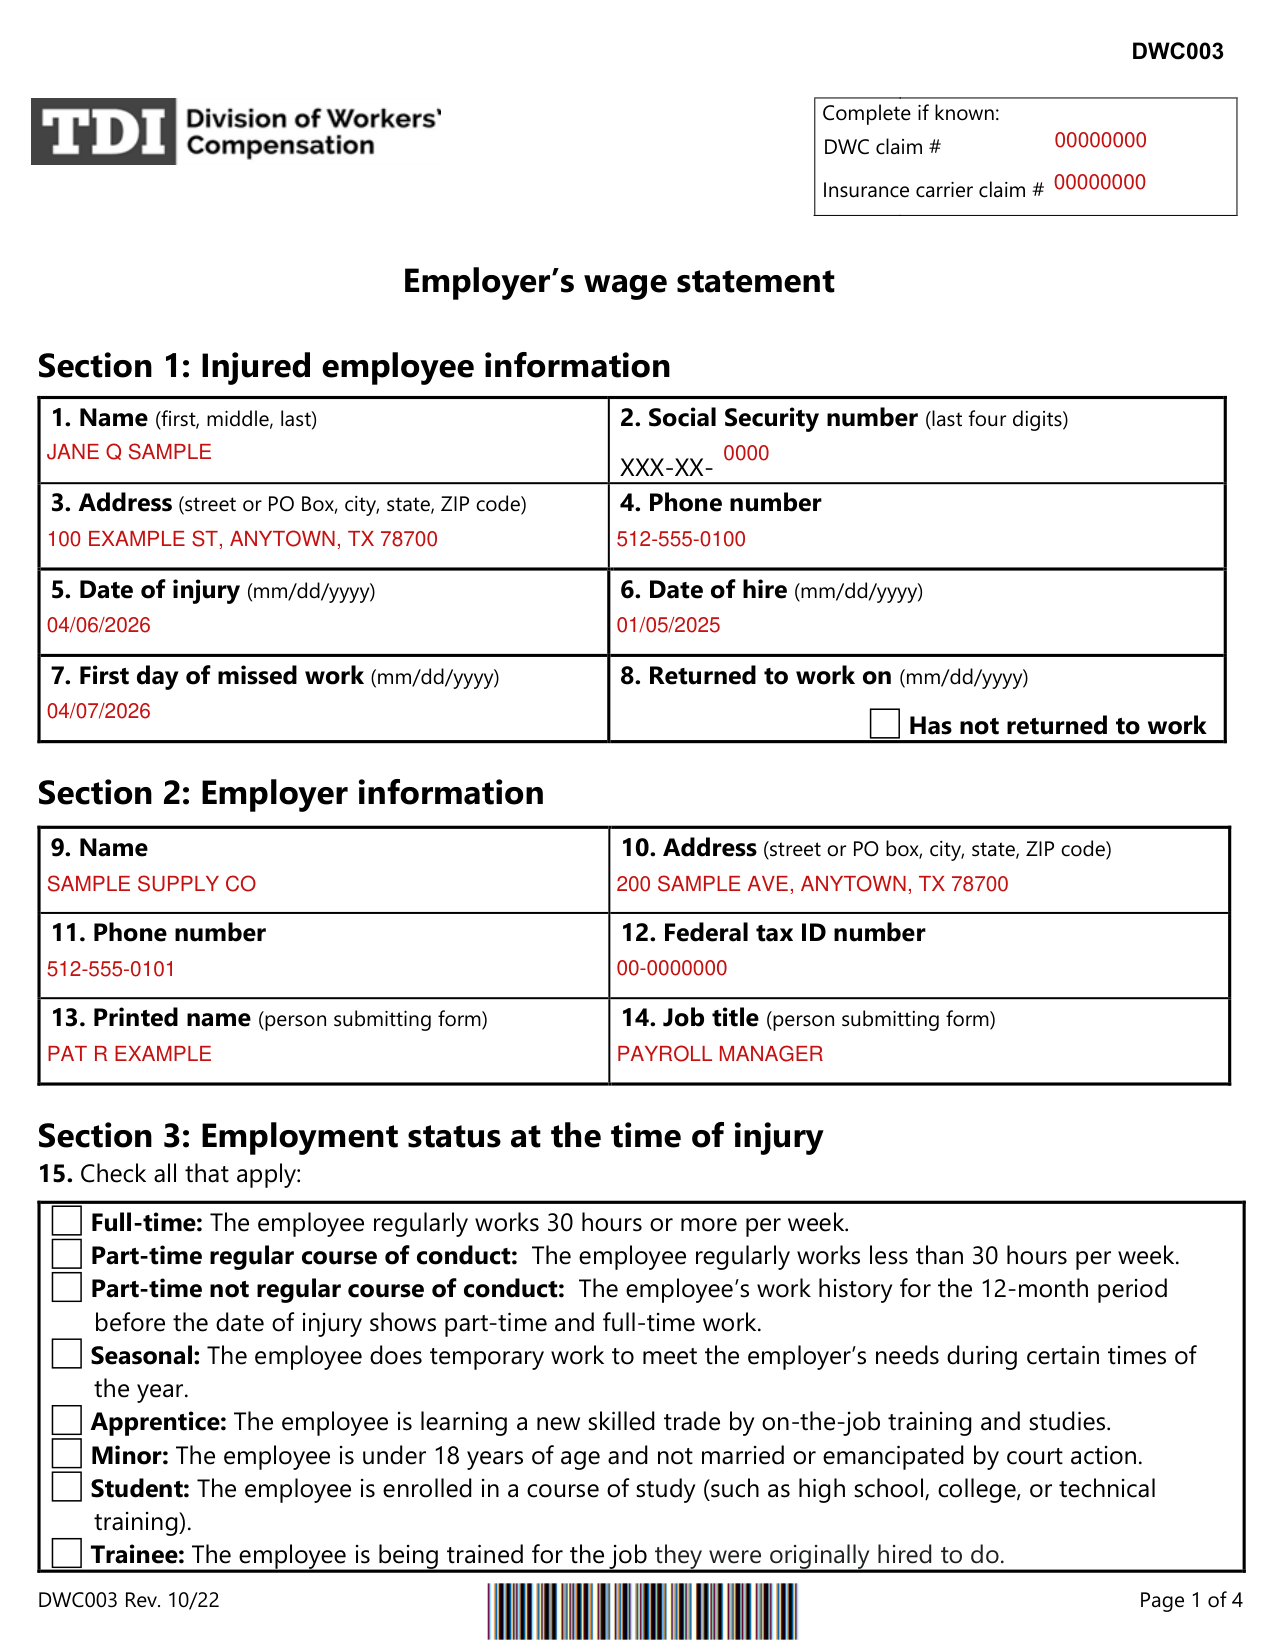
How to fill out Form DWC003, box by box
Section 1: Injured employee information
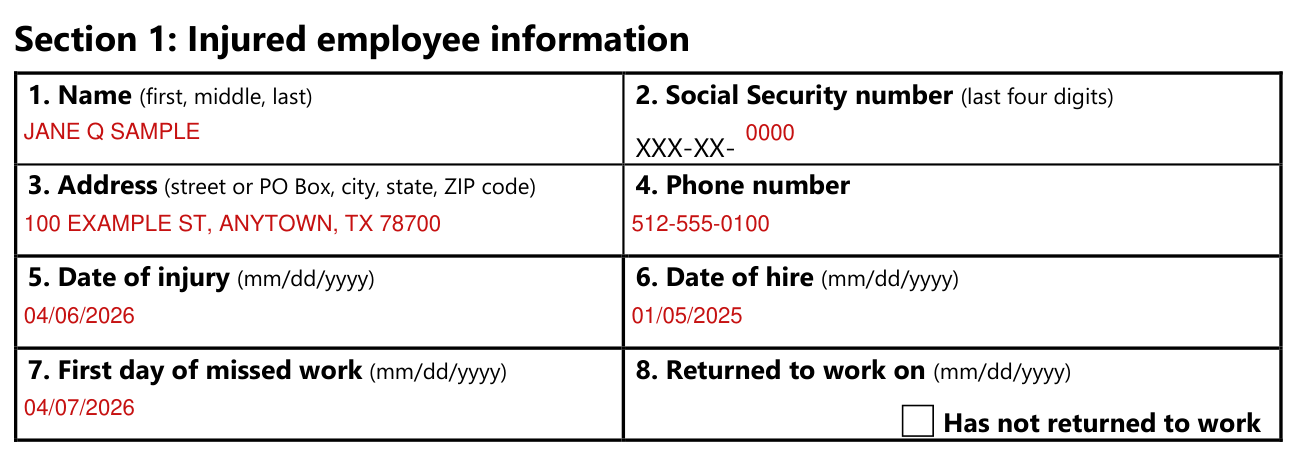
Under Section 1: Injured employee information, enter 1. Name (first, middle, last), 2. Social Security number (last four digits), 3. Address (street or PO Box, city, state, ZIP code) and 4. Phone number.
Enter 5. Date of injury (mm/dd/yyyy), 6. Date of hire (mm/dd/yyyy), 7. First day of missed work (mm/dd/yyyy) and 8. Returned to work on (mm/dd/yyyy), or mark Has not returned to work.
Section 2: Employer information
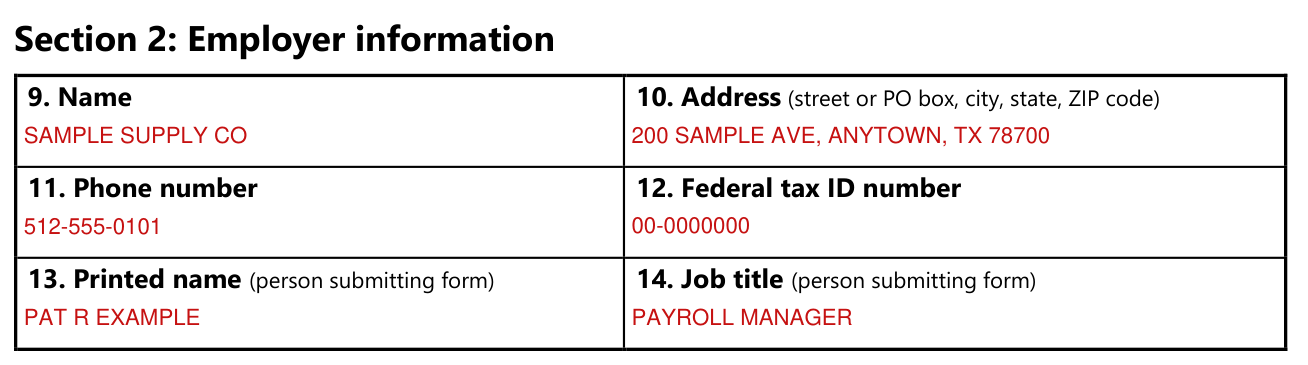
Under Section 2: Employer information, enter 9. Name, 10. Address (street or PO box, city, state, ZIP code), 11. Phone number, 12. Federal tax ID number, 13. Printed name (person submitting form) and 14. Job title (person submitting form).
Section 3: Employment status at the time of injury

Under Section 3: Employment status at the time of injury, 15. Check all that apply.
Full-time: The employee regularly works 30 hours or more per week.
Part-time regular course of conduct: The employee regularly works less than 30 hours per week.
Part-time not regular course of conduct: The employee's work history for the 12-month period before the date of injury shows part-time and full-time work.
Seasonal: The employee does temporary work to meet the employer's needs during certain times of the year.
Apprentice: The employee is learning a new skilled trade by on-the-job training and studies.
Minor: The employee is under 18 years of age and not married or emancipated by court action.
Student: The employee is enrolled in a course of study (such as high school, college, or technical training).
Trainee: The employee is being trained for the job they were originally hired to do.
Section 4, Part 1: Wage information
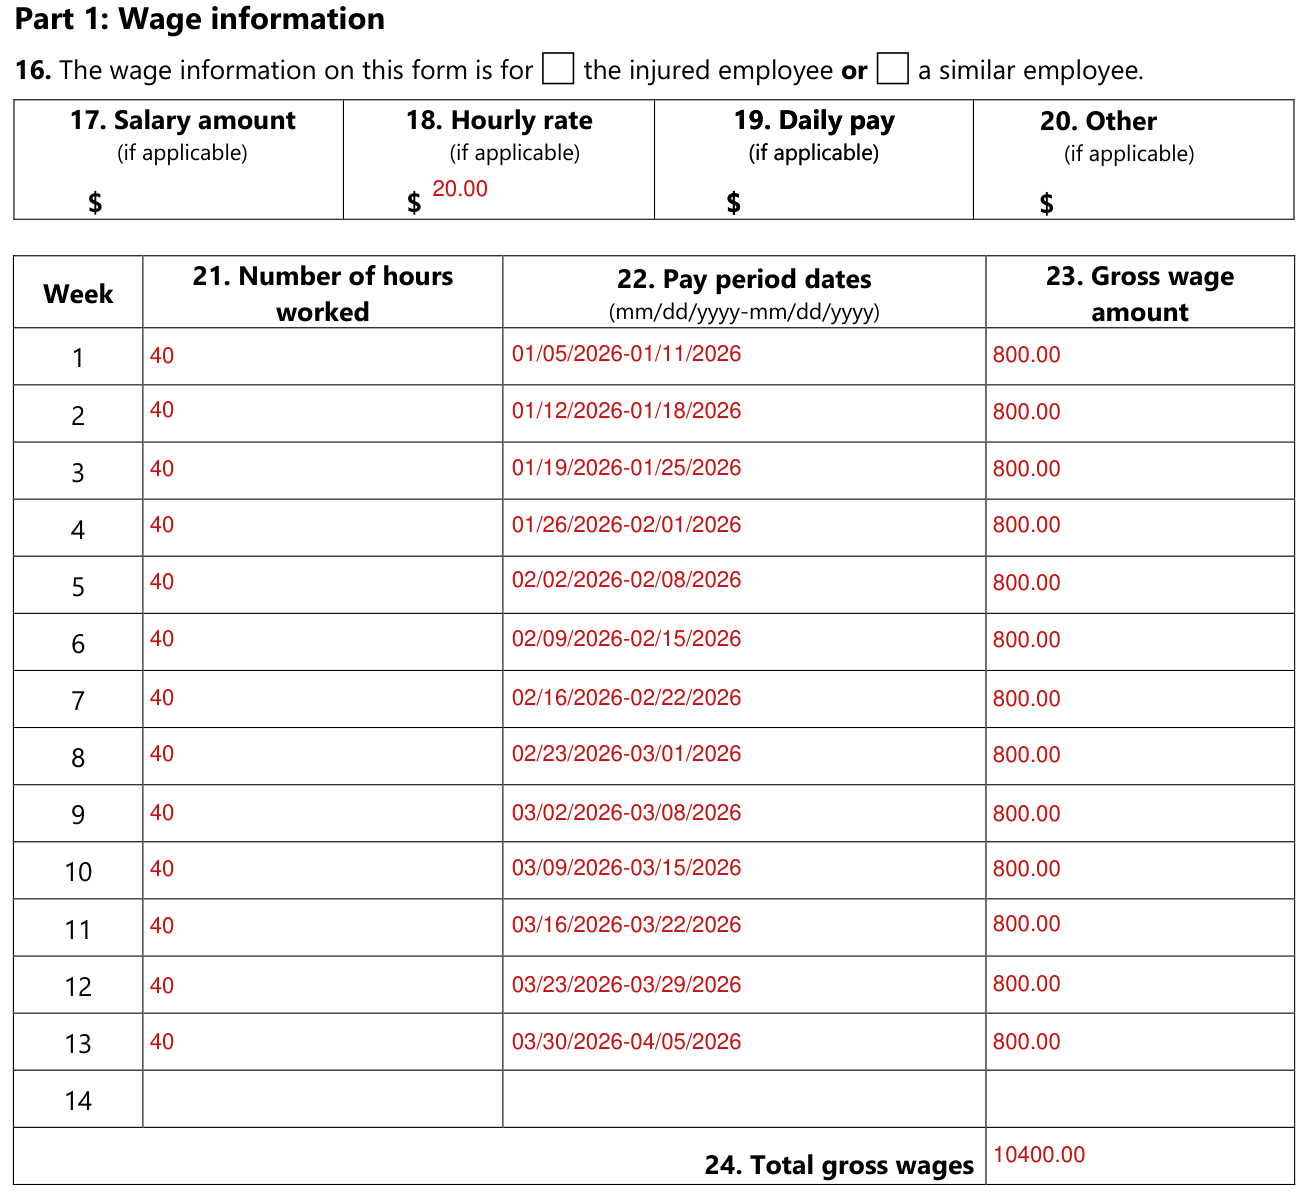
16. Mark one: the wage information on this form is for the injured employee or a similar employee.
Report all wages paid in the 13 weeks before the date of injury according to the employee's pay period.
Employers may report 14 weeks if paid biweekly or three months if paid monthly. In all cases, list the dates that each period covers.
If the employee was not employed for 13 weeks before their injury, report wages of an employee who has the training, experience, skills, same pay, and same number of hours.
If no similar employee exists, report all wages the injured employee earned before the injury (28 TAC Section 120.4).
Enter 17. Salary amount (if applicable), 18. Hourly rate, 19. Daily pay (if applicable) and 20. Other (if applicable).
For each Week, enter 21. Number of hours worked, 22. Pay period dates (mm/dd/yyyy-mm/dd/yyyy) and 23. Gross wage amount.
Enter 24. Total gross wages.
Section 4, Part 2: Nonpecuniary wage information
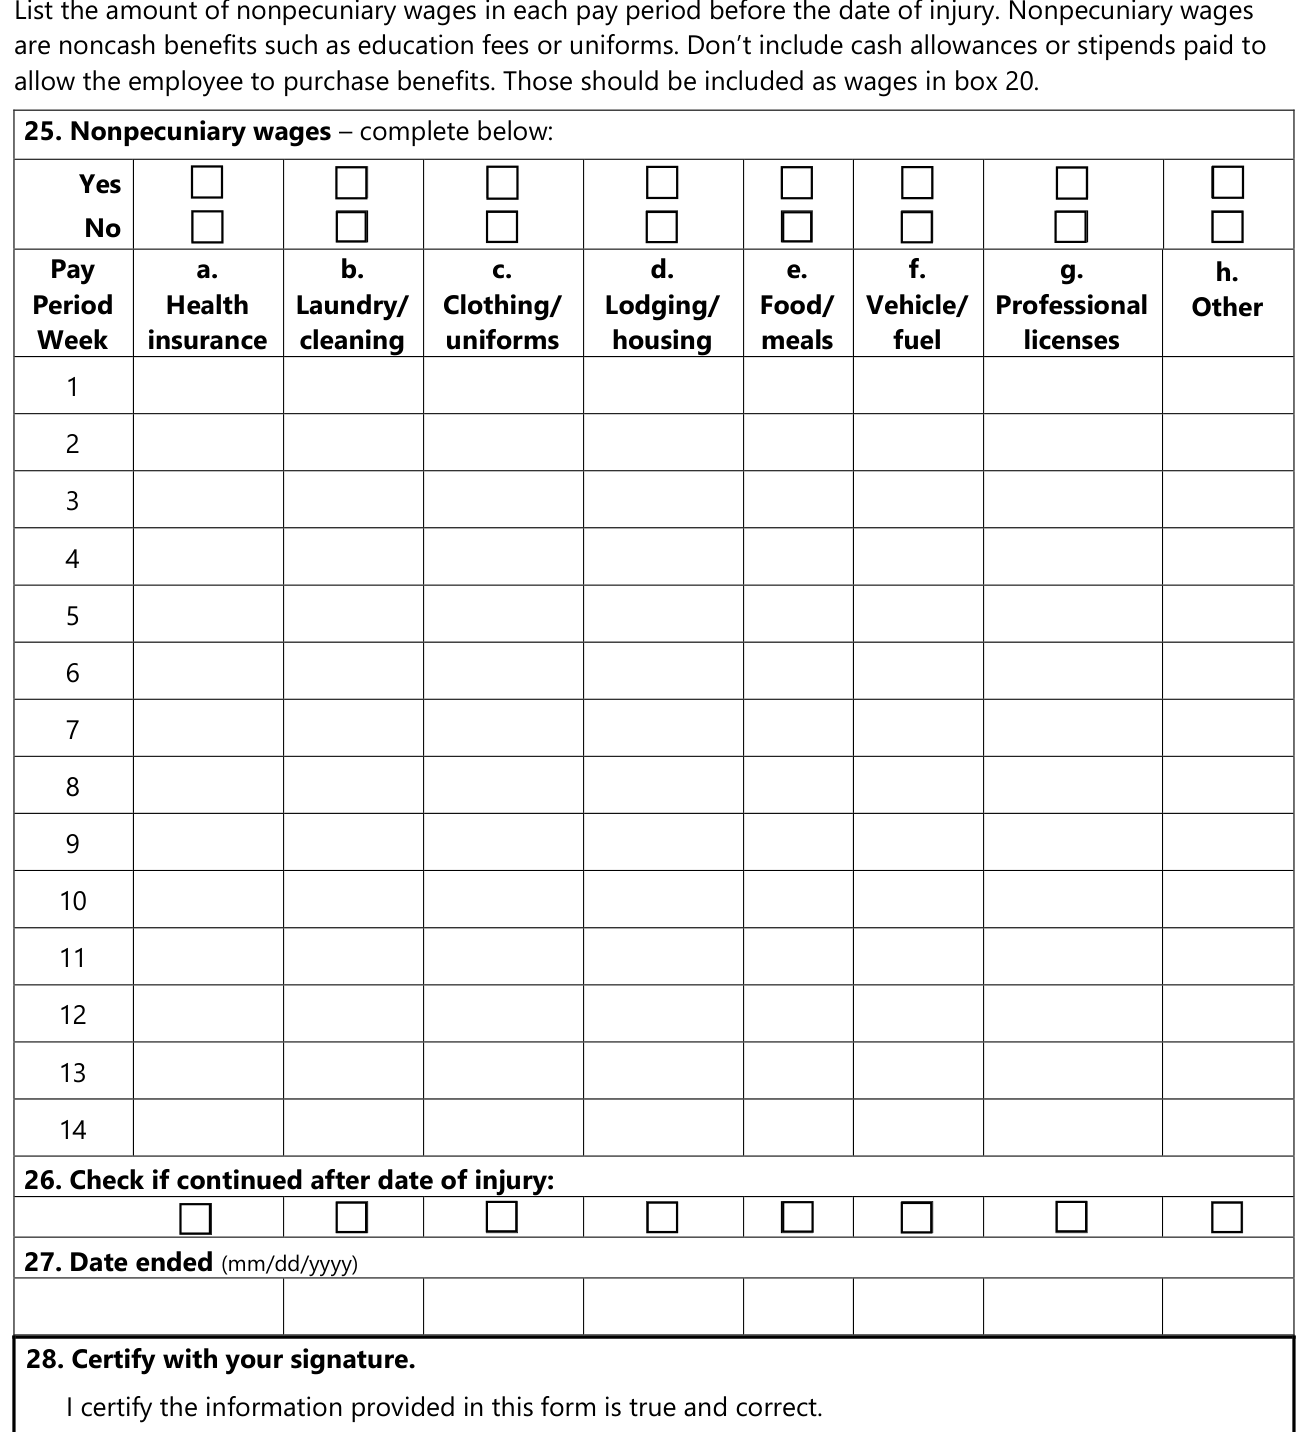
Part 2: Nonpecuniary wage information (paid by employer only for injured employees).
List the amount of nonpecuniary wages in each pay period before the date of injury.
Nonpecuniary wages are noncash benefits such as education fees or uniforms.
Don't include cash allowances or stipends paid to allow the employee to purchase benefits. Those should be included as wages in box 20.
Report all benefits paid to the employee in a form other than money. This includes, but is not limited to, the benefit categories listed in Section 4, Part 2.
25. Nonpecuniary wages: Yes or No.
Pay Period, Week: a. Health insurance, b. Laundry/ cleaning, c. Clothing/ uniforms, d. Lodging/ housing, e. Food/ meals, f. Vehicle/ fuel, g. Professional licenses and h. Other.
26. Check if continued after date of injury: 27. Date ended (mm/dd/yyyy).
Certify with your signature

28. Certify with your signature: by signing you certify that the information provided in this form is true and correct.
More rules for Form DWC003
What if my employee has multiple jobs? The injured employee will submit the DWC Form-003ME, Employee's Multiple Employment Wage Statement to their other employer. The injured employee will submit the completed form to the insurance carrier (28 TAC Section 122.5).
Average weekly wage: The gross average amount of money the employer paid the injured employee each week in the 13 weeks before the injury or illness.
Common questions about Form DWC003
What is the phone number for the Texas Department of Insurance regarding workers' compensation?
Call 1-800-252-7031, Monday to Friday, 8 a.m. to 5 p.m., Central time.
Is there a deadline?
Within 30 days from the earliest of the date the employer is notified that the employee is entitled to income benefits, or the date the employee's death is a result of the injury (compensable); and within seven days from getting a request from the Texas Department of Insurance, Division of Workers' Compensation (DWC).
Where do I file it?
An employer must file the completed form with the insurance carrier, the injured employee, and the injured employee's representative (if any) within 30 days from the earliest of the date the employer is notified that the employee is entitled to income benefits, or the date the employee's death is a result of the injury (compensable).
Is there a penalty?
Fine: an employer who fails to timely file a complete wage statement without good cause, as required by 28 Texas Administrative Code (TAC) Section 120.4(a) and Texas Labor Code Section 408.063(c), may be fined.
Sources
[1] Form DWC003 (Rev. 10/22), Employer's wage statement, Texas Department of Insurance, Division of Workers' Compensation (the Official source link on this page).