

Form PR-4 at a glance
What it is: Form PR-4 is the State of California Primary Treating Physician's Permanent and Stationary Report, designed to report the initial evaluation of permanent disability to the claims administrator.
Who signs: Physician signature: Primary Treating Physician (original signature, do not stamp).
This form is designed to be used by the primary treating physician and is required for ratings prepared pursuant to the 2005 Permanent Disability Rating Schedule and the AMA Guides to the Evaluation of Permanent Impairment (5th Ed.).
It should be completed if the patient has residual effects from the injury or may require future medical care. In such cases, it should be completed once the patient's condition becomes permanent and stationary.
A filled-in Form PR-4 example: a physician completes the report

How to fill out Form PR-4, box by box
Additional pages attached

You must address each of the issues on this report. You may substitute or append a narrative report if you require additional space to adequately report on these issues.
Patient
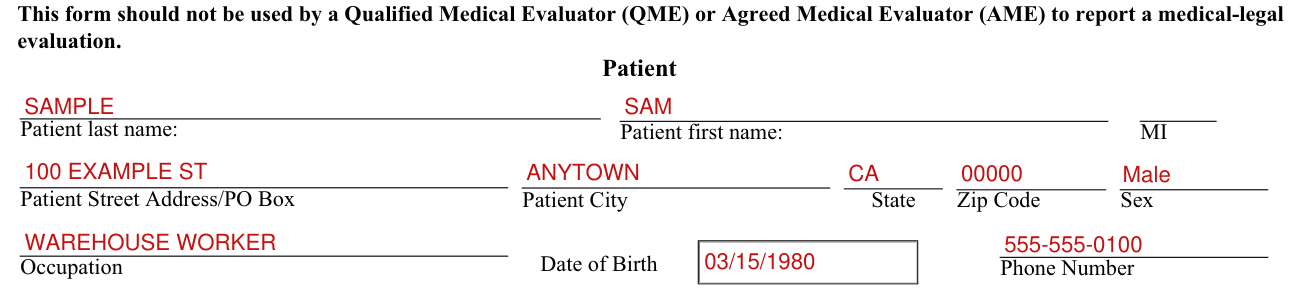
Under Patient, enter the Patient last name, Patient first name and MI.
Enter the Patient Street Address/PO Box, Patient City, State, Zip Code and Sex, then the Occupation, Date of Birth and Phone Number.
Claims Administrator
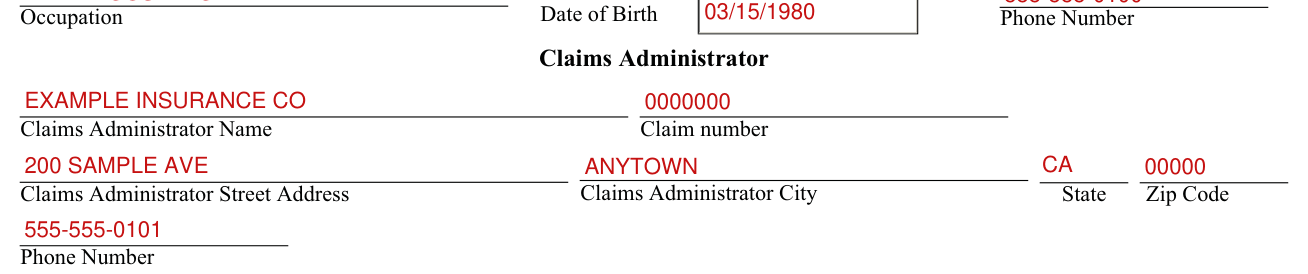
Under Claims Administrator, enter the Claims Administrator Name and the Claim number.
Enter the Claims Administrator Street Address, Claims Administrator City, State and Zip Code, then the Phone Number.
Employer
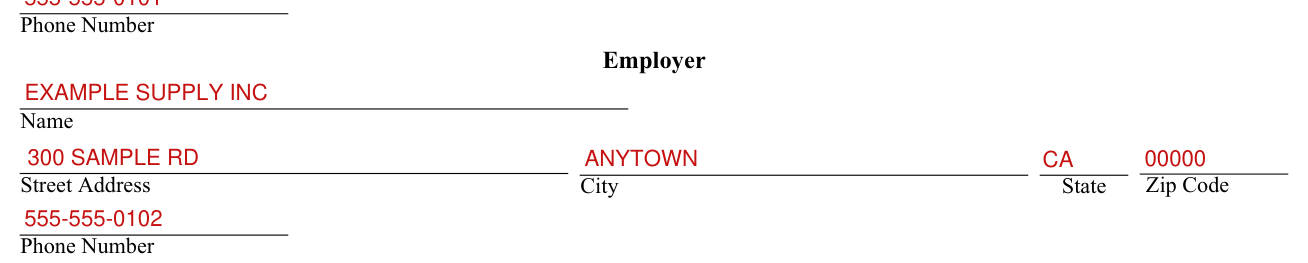
Under Employer, enter the Name, the Street Address, City, State and Zip Code, and the Phone Number.
Date of Injury, Last Date Worked, Date of Last Exam, Date of Current Exam and Permanent & Stationary Date

Enter the Date of Injury, Last Date Worked, Date of Last Exam, Date of Current Exam and Permanent & Stationary Date. For dates use mm/dd/yyyy.
Description of how injury/illness occurred and Patient's Complaints

Describe how the injury/illness occurred (e.g., Hand caught in punch press; fell from height onto back; exposed 25 years ago to asbestos), then enter the Patient's Complaints.
Objective Findings
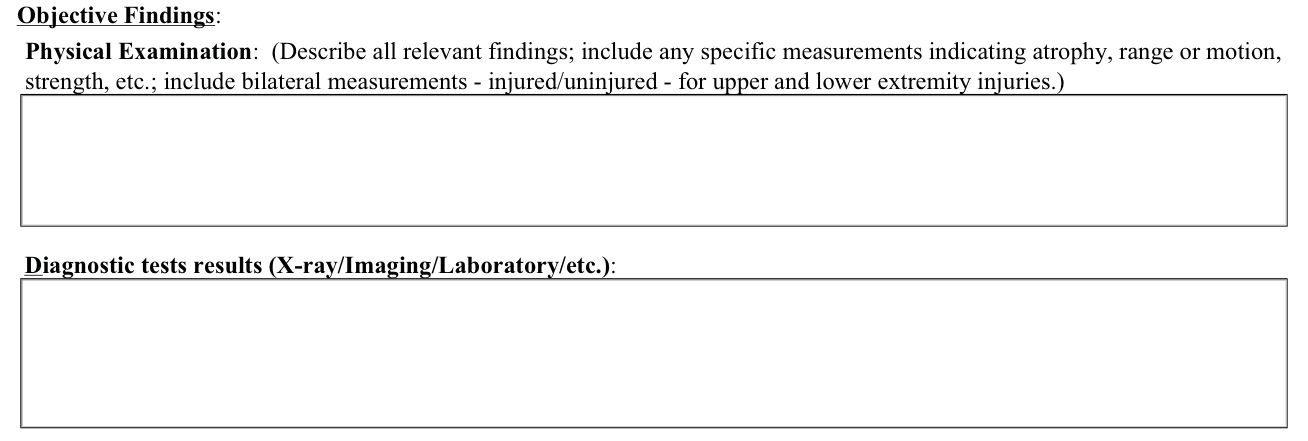
Under Objective Findings, Physical Examination: Describe all relevant findings; include any specific measurements indicating atrophy, range or motion, strength, etc.; include bilateral measurements - injured/uninjured - for upper and lower extremity injuries.
Enter the Diagnostic tests results (X-ray/Imaging/Laboratory/etc.).
Diagnoses
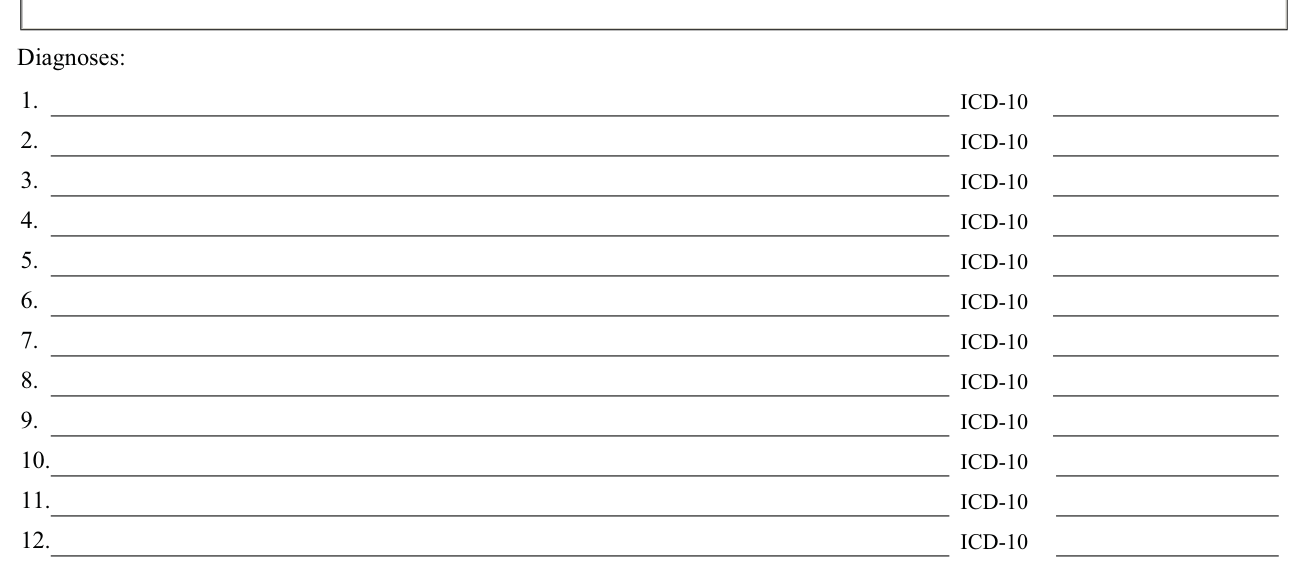
Under Diagnoses, enter each diagnosis on its own line, 1. to 12., and its ICD-10.
Impairment Rating

Impairment Rating: Report the whole person impairment (WPI) for each impairment using the AMA Guides, 5th Edition, and explain how the rating was derived. List tables used and page numbers.
Each row has Impairment, WPI%, Table #(s), Page #(s) and Explanation.
Apportionment

Mark Yes or No: Is the permanent disability directly cased by an injury or illness arising out of and in the scope of employment?
Mark Yes or No: Is the permanent disability caused, in whole or in part, by other factors besides this industrial injury or illness, including any prior industrial injury or illness?
If the answer to the second question is "yes," provide the following: (1) the approximate percentage of the permanent disability that is due to factors other than the injury or illness arising out of and in the course of employment; and (2) a complete narrative description of the basis for your apportionment finding.
If you are unable to include an apportionment determination in your report, state the specific reasons why you could not make this determination. You may attach your findings on a separate sheet.
Any physician who prepares a report addressing permanent disability due to a claimed industrial injury is required to address the issue of causation of the permanent disability, and in order for a permanent disability report to be complete, the report must include an apportionment determination.
Future Medical Treatment

Under Future Medical Treatment, describe any continuing medical treatment related to this injury that you believe must be provided to the patient. ("Continuing medical treatment" is defined as occurring or presently planned treatment.)
Describe any medical treatment the patient may require in the future. ("Future medical treatment" is defined as treatment which is anticipated at some time in the future to cure or relieve the employee from the effects of the injury.)
Include medications, surgery, physical medicine services, durable equipment, etc.
Functional Capacity Assessment
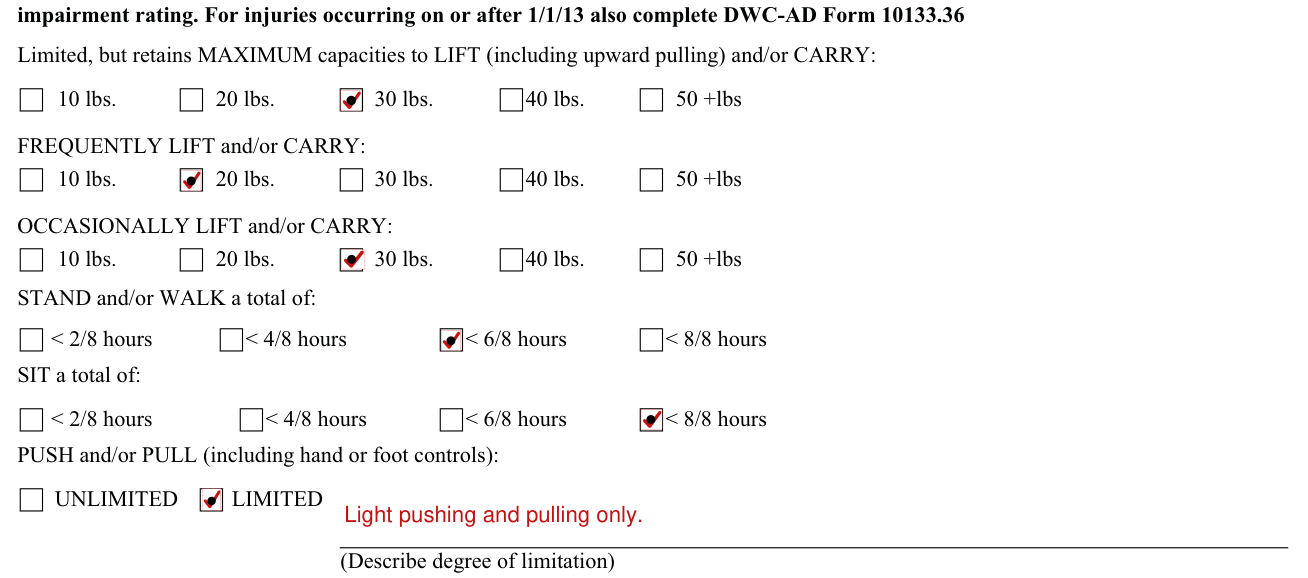
Functional Capacity Assessment: The assessment of functional capacity is to be prepared by the treating physician, solely for the purpose of determining a claimant's ability to return to his or her usual and customary occupation, and will not be considered in the permanent impairment rating.
For injuries occurring on or after 1/1/13 also complete DWC-AD Form 10133.36.
Limited, but retains MAXIMUM capacities to LIFT (including upward pulling) and/or CARRY: mark 10 lbs., 20 lbs., 30 lbs., 40 lbs. or 50 +lbs. Do the same for FREQUENTLY LIFT and/or CARRY and OCCASIONALLY LIFT and/or CARRY.
For STAND and/or WALK a total of and for SIT a total of, mark < 2/8 hours, < 4/8 hours, < 6/8 hours or < 8/8 hours.
For PUSH and/or PULL (including hand or foot controls), mark UNLIMITED or LIMITED. (Describe degree of limitation)
ACTIVITIES ALLOWED
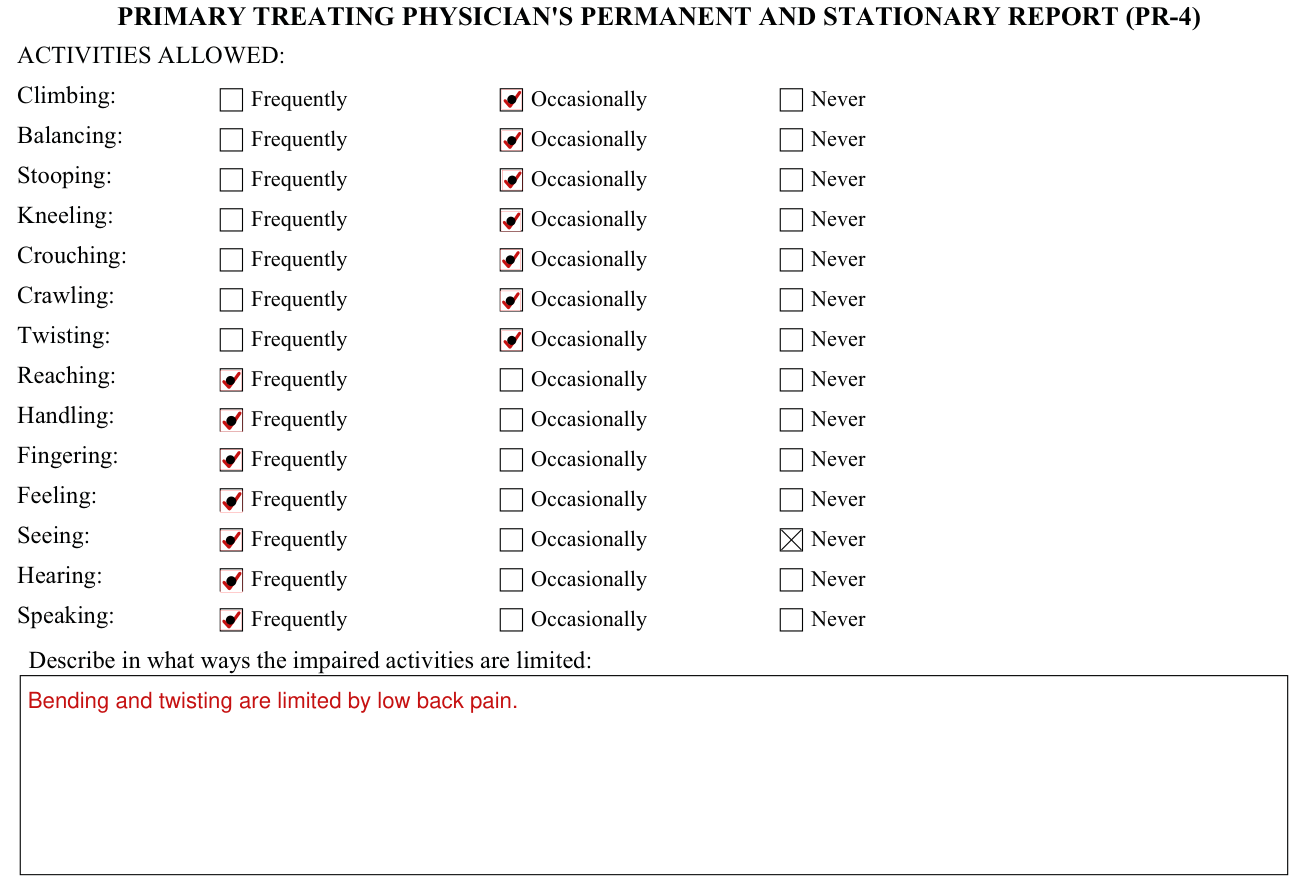
Under ACTIVITIES ALLOWED, mark Frequently, Occasionally or Never for each of Climbing, Balancing, Stooping, Kneeling, Crouching, Crawling, Twisting, Reaching, Handling, Fingering, Feeling, Seeing, Hearing and Speaking.
Describe in what ways the impaired activities are limited.
Environmental restrictions

Enter the Environmental restrictions (e.g., heights, machinery, temperature extremes, dust, fumes, humidity, vibration, etc.).
Return to his/her usual occupation

Mark Yes or No: Can this patient now return to his/her usual occupation?
Medical Records
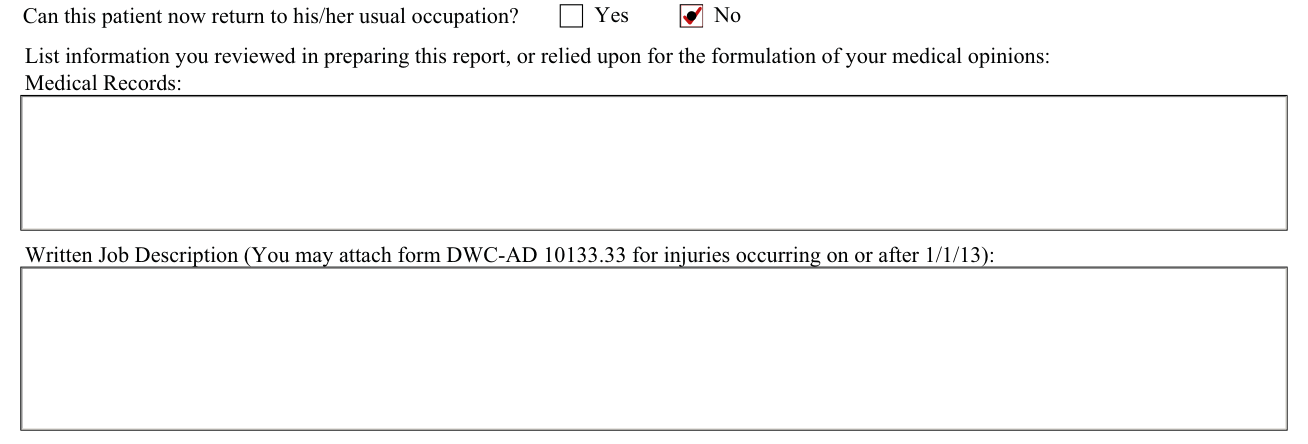
List information you reviewed in preparing this report, or relied upon for the formulation of your medical opinions: Medical Records.
Under Written Job Description, you may attach form DWC-AD 10133.33 for injuries occurring on or after 1/1/13.
Physician signature, Cal. License Number and Date

Enter the Cal. License Number with the Physician signature.
"I declare under penalty of perjury that this report is true and correct to the best of my knowledge and that I have not violated Labor Code section 139.3."
Enter the Date (mm/dd/yyyy), Executed at, Physician Name, Specialty, Physician address and Phone Number.
More rules for Form PR-4
PR-4 Pain Assessment: If the burden of the worker's condition has been increased by pain-related impairment in excess of the pain component already incorporated into the WPI rating under Chapters 3-17 of the AMA Guides, 5th Edition, specify the additional whole person impairment rating (0% up to 3% WPI) attributable to such pain.
For excess pain involving multiple impairments, attribute the pain in whole number increments to the appropriate impairments.
The sum of all pain impairment ratings may not exceed 3% for a single injury.
Common questions about Form PR-4
When is this form not the right one?
This form should not be used by a Qualified Medical Evaluator (QME) or Agreed Medical Evaluator (AME) to report a medical-legal evaluation.
Sources
[1] Form PR-4 (Rev. 02/2016), Primary Treating Physician's Permanent and Stationary Report, State of California Division of Workers' Compensation (the Official source link on this page).