


Form DE 230 at a glance
What it is: DE 230, Request for Preliminary Worker Classification Assessment or Audit Lead Referral, is used by a worker who believes he/she is misclassified as an independent contractor.
Where and when to file: Upon completion, return to EMPLOYMENT DEVELOPMENT DEPARTMENT FACD - Audit Section, MIC 94 PO Box 826880 Sacramento, CA 94280-0001.
The form may also be used to provide information on the business entity to the Employment Development Department (EDD) as a potential employment tax audit lead.
A filled-in Form DE 230 example: a worker asks the EDD for an opinion

How to fill out Form DE 230, box by box
Check either the OPINION or AUDIT LEAD box
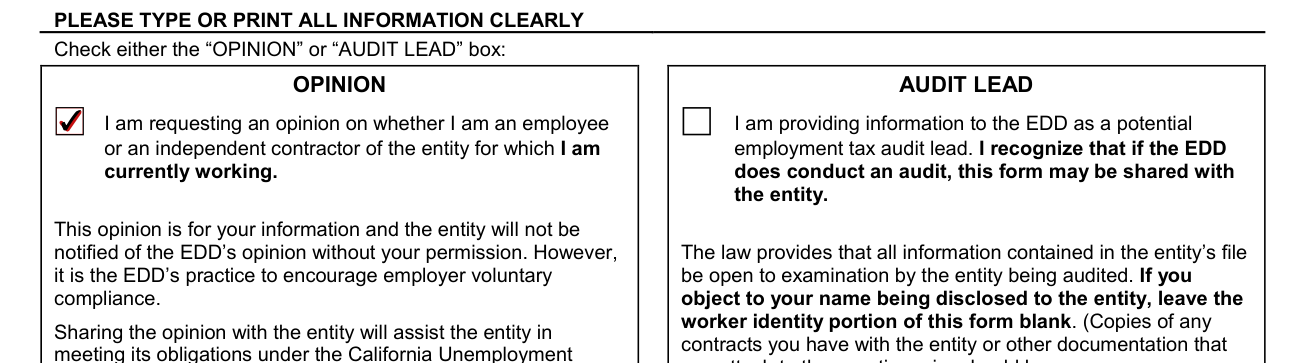
Check either the “OPINION” or “AUDIT LEAD” box. Check OPINION if you are requesting an opinion on whether you are an employee or an independent contractor of the entity for which you are currently working.
Check AUDIT LEAD if you are providing information to the EDD as a potential employment tax audit lead. If the EDD does conduct an audit, this form may be shared with the entity.
This opinion is for your information and the entity will not be notified of the EDD's opinion without your permission. However, it is the EDD's practice to encourage employer voluntary compliance.
May the EDD supply the entity with a copy of the opinion

May the EDD supply the entity with a copy of the opinion? If you checked “No,” the entity will not be contacted. If you checked “Yes,” the EDD's notification to the entity will not include your name, address, Social Security number, or a copy of this form.
Name of worker and name of entity
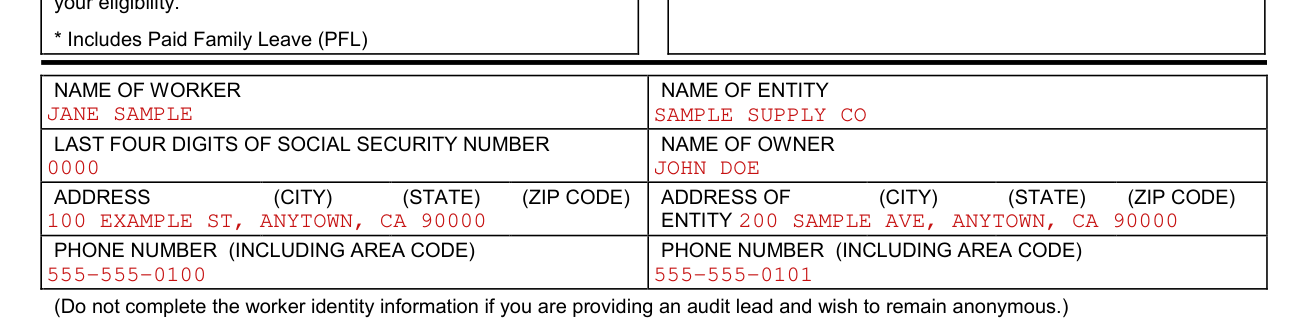
The law provides that all information contained in the entity's file be open to examination by the entity being audited. If you object to your name being disclosed to the entity, leave the worker identity portion of this form blank. Copies of any contracts you have with the entity or other documentation that you attach to the questionnaire should have your name, address, and Social Security number blacked out in order to prevent your identity from being disclosed.
If you wish to remain anonymous and are also requesting an opinion, please submit two separate requests (DE 230) with the worker identification completed for the “Opinion” request and the worker identity blank for the “Audit Lead.”
Do not complete the worker identity information if you are providing an audit lead and wish to remain anonymous.
For the worker, enter the NAME OF WORKER, the LAST FOUR DIGITS OF SOCIAL SECURITY NUMBER, the ADDRESS (CITY) (STATE) (ZIP CODE) and the PHONE NUMBER (INCLUDING AREA CODE).
For the entity, enter the NAME OF ENTITY, the NAME OF OWNER, the ADDRESS OF ENTITY (CITY) (STATE) (ZIP CODE) and the PHONE NUMBER (INCLUDING AREA CODE).
Are you currently working for this business entity

Are you currently working for this business entity? Yes No If “No,” please provide the date last worked and explain why you were terminated, laid off, or quit.
Complete the remainder of the form only if you are submitting this as an audit lead or are currently working with the entity.
The declaration: name printed, signature and date

If you wish to remain anonymous, do not complete the NAME PRINTED, SIGNATURE and DATE lines. By signing, you declare that all copies of contracts and all statements submitted are true, correct, and complete to the best of your knowledge and belief. If any misrepresentation has been made or facts have been omitted, you understand that the determination will not be valid and will not be binding upon the EDD. Enter the NAME PRINTED and the DATE, and sign on the SIGNATURE line.
More rules for Form DE 230
This form is designed to cover many work activities. Some of the questions may not apply to you. You should answer all of the questions or mark them “UNKNOWN” or “DOES NOT APPLY.”
If additional space is needed, please attach another sheet. If you require assistance in the completion of this form, contact the nearest Employment Tax Office listed on the EDD website at www.edd.ca.gov/office_locator/ or call 888-745-3886.
The information you provide will be forwarded to a local Employment Tax Office.
The EDD's determination will not affect your future eligibility for employee-related benefits, such as California Unemployment Insurance and State Disability Insurance, which includes Paid Family Leave (PFL). If you file a claim for benefits, a separate determination will be made to determine your eligibility.
Type or print all information clearly.
Say how you learned of the job (e.g., advertisement on the Internet or in a newspaper, word of mouth). Please attach a copy of the job announcement, if you have a copy.
Are your services performed under a written agreement or contract? Yes No If “Yes,” please attach a copy.
If the agreement is not in writing, no copy is available, or the terms of the written agreement are not complied within practice, describe the actual terms and conditions of the arrangement.
Do you have helpers? Yes No If “Yes,” answer questions 17b through 17g. If “No,” go to question 18.
Does the entity allow you to provide services for others during the same time periods services are performed for the entity? Yes No Unknown If “Yes,” answer questions 18b through 18e. If “No,” or “Unknown,” go to question 19.
Is a license or certificate required to perform the services you perform for the entity? Yes No If “Yes,” do you possess such a license or certificate? Yes No If “Yes,” does the entity possess such a valid license or certificate? Yes No Unknown
Are you required to provide reports to the entity or its representative on the status or progress of your services for the entity? Yes No If “Yes,” how often?
Please attach copies of report forms used in reporting to the entity.
Has any other governmental agency ruled on the status of services performed by you for this entity? Yes No If “Yes,” please attach a copy of the ruling and explain.
Please explain why you believe you are an employee or an independent contractor of the entity.
Common questions about Form DE 230
Where do I file it?
Upon completion, return to EMPLOYMENT DEVELOPMENT DEPARTMENT FACD - Audit Section, MIC 94 PO Box 826880 Sacramento, CA 94280-0001.
Sources
[1] Form DE 230 (9-15), Request for Preliminary Worker Classification Assessment or Audit Lead Referral, Employment Development Department (the Official source link on this page).