


Form EMEDNY-436901 at a glance
What it is: The New York State Medicaid Enrollment Form, EMEDNY-436901, is for those who ONLY ORDER-REFER-ATTENDING-PRESCRIBE or are in a Managed Care Network (non-billers).
Where and when to file: Mail to: eMedNY PO Box 4603 Rensselaer, NY 12144-4603.
This enrollment form should be used by practitioners seeking enrollment as an ordering referring, attending or prescribing practitioner (attending providers should use this form if their name and NPI will only appear on the hospital's claim), or as a Medicaid Managed Care Network provider. These providers will not submit claims to Medicaid and, therefore will not receive payment from the Medicaid Program.
A filled-in Form EMEDNY-436901 example: an inactive practitioner reinstates
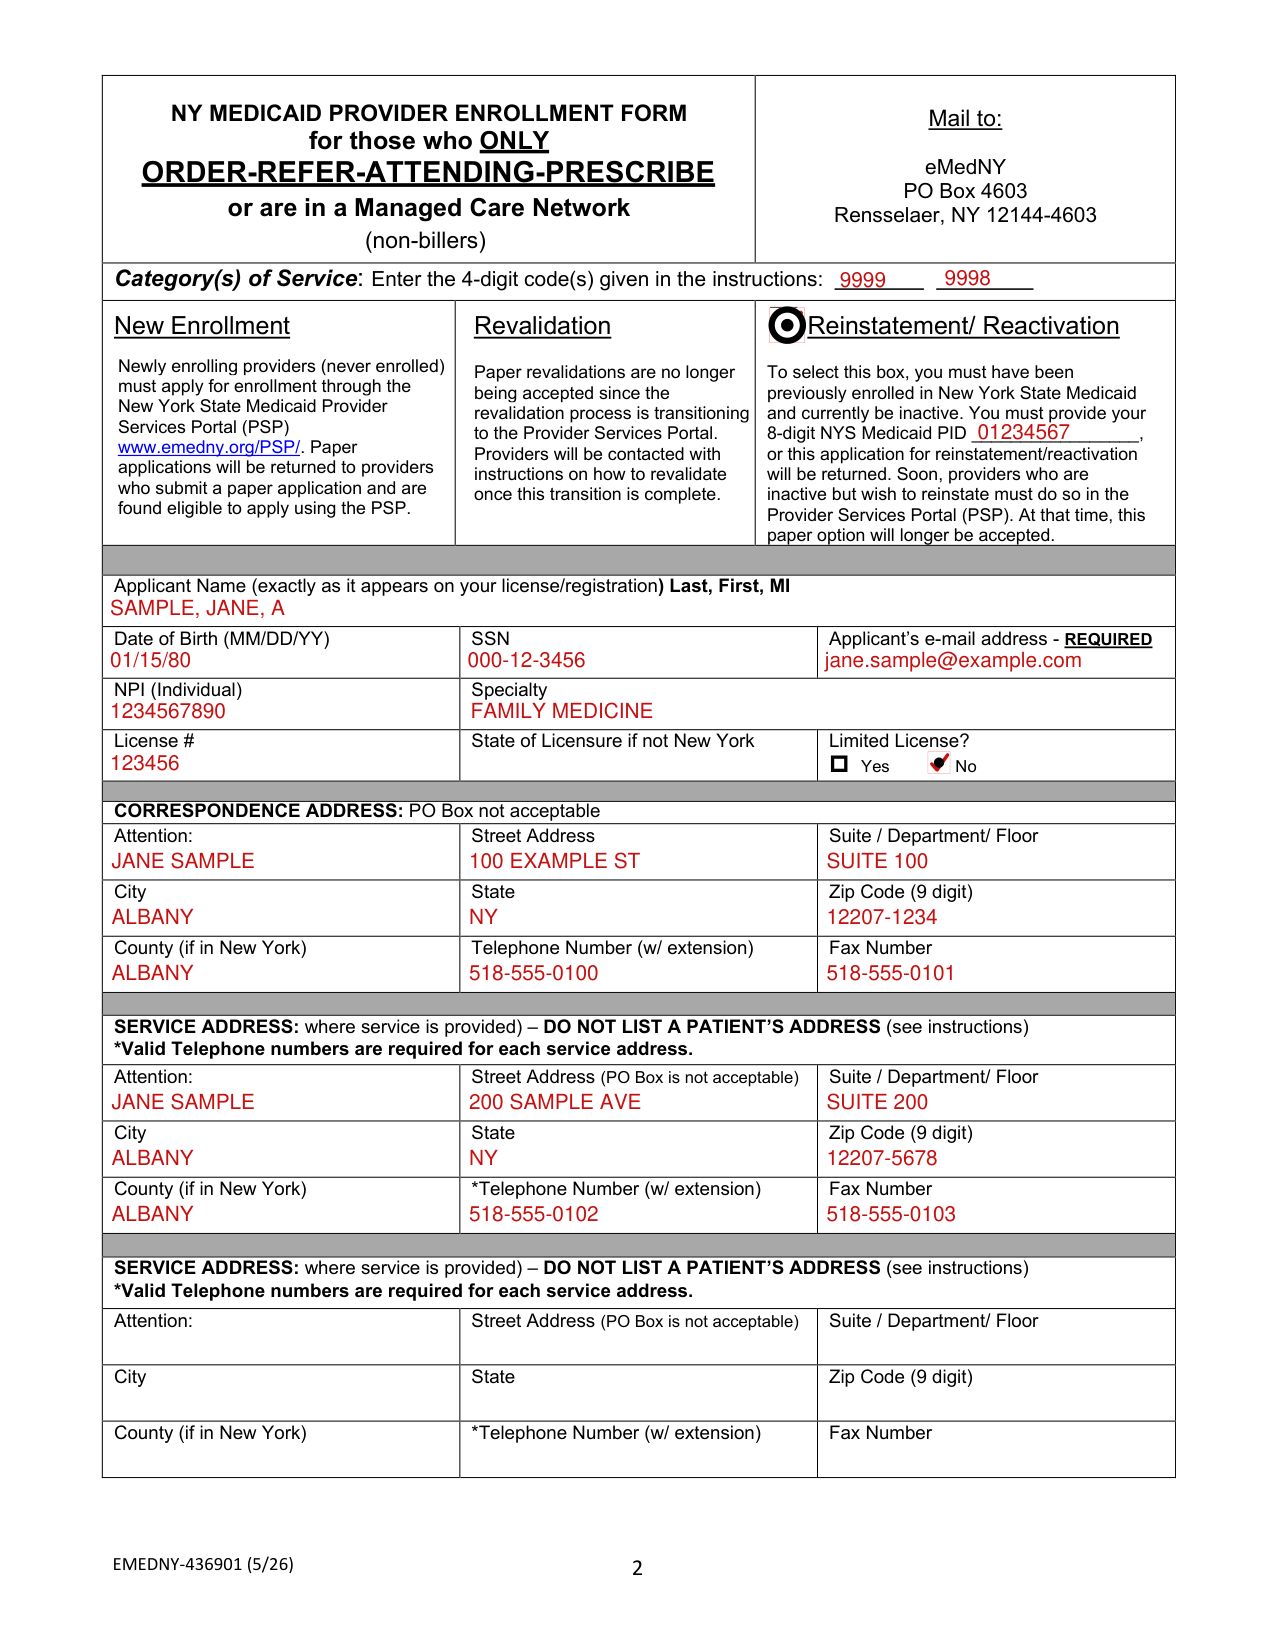
How to fill out Form EMEDNY-436901, box by box
Category(s) of Service
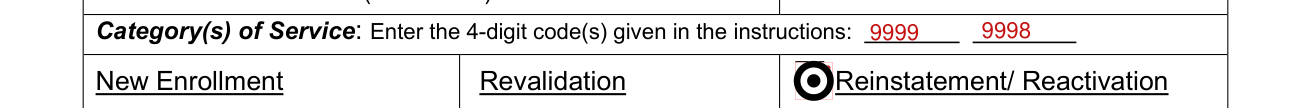
In Category(s) of Service, enter the 4-digit code(s) given in the instructions.
Reinstatement/ Reactivation, New Enrollment and Revalidation

Newly enrolling providers (never enrolled) must apply for enrollment through the New York State Medicaid Provider Services Portal (PSP). Paper applications will be returned to providers who submit a paper application and are found eligible to apply using the PSP.
Paper revalidations are no longer being accepted since the revalidation process is transitioning to the Provider Services Portal. Providers will be contacted with instructions on how to revalidate once this transition is complete.
To select Reinstatement/ Reactivation, you must have been previously enrolled in New York State Medicaid and currently be inactive. You must provide your 8-digit NYS Medicaid PID, or this application for reinstatement/reactivation will be returned.
Soon, providers who are inactive but wish to reinstate must do so in the Provider Services Portal (PSP). At that time, this paper option will no longer be accepted.
Applicant Name, Date of Birth, SSN and e-mail address

Enter the Applicant Name exactly as it appears on your license/registration: Last, First, MI.
Enter the Date of Birth (MM/DD/YY), the SSN and the Applicant's e-mail address, which is REQUIRED.
NPI, Specialty, License # and Limited License

Enter the NPI (Individual), the Specialty and the License #. Enter the State of Licensure if not New York. Mark Yes or No for Limited License?
CORRESPONDENCE ADDRESS

For the CORRESPONDENCE ADDRESS, a PO Box is not acceptable. Enter Attention, Street Address, Suite / Department/ Floor, City, State, Zip Code (9 digit), County (if in New York), Telephone Number (w/ extension) and Fax Number.
SERVICE ADDRESS
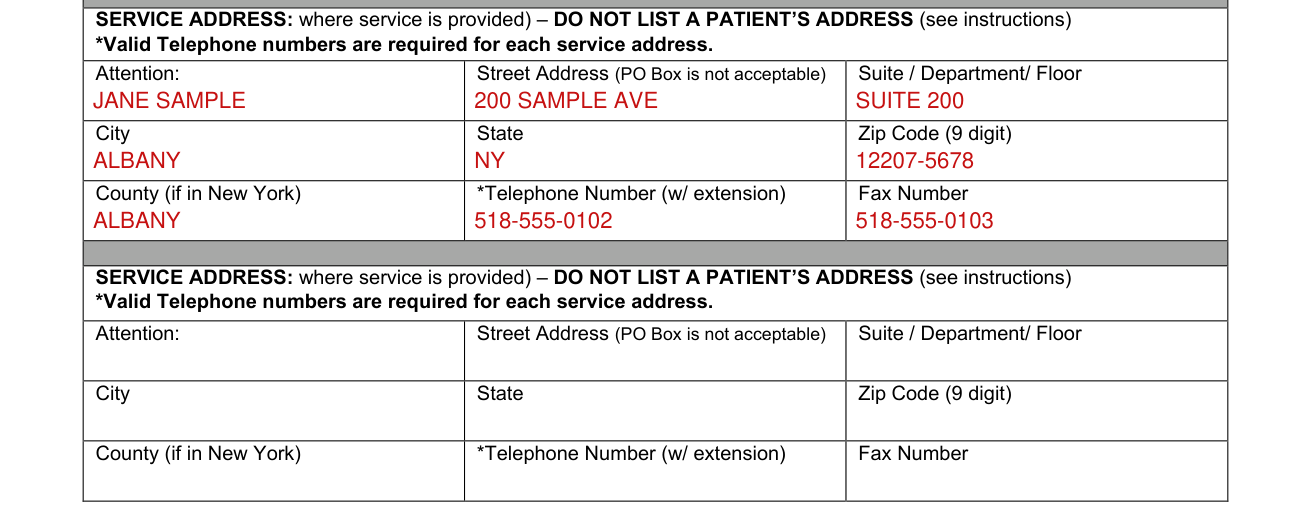
For each SERVICE ADDRESS, where service is provided, do not list a patient's address; valid telephone numbers are required for each service address. Enter Attention, Street Address (a PO Box is not acceptable), Suite / Department/ Floor, City, State, Zip Code (9 digit), County (if in New York), Telephone Number (w/ extension) and Fax Number.
SECTION 1: Disclosing Entity / Applicant
Completion is required by 42 CFR Part 455.104. Failure to provide the information requested will cause the application to be returned.
In SECTION 1, for the Disclosing Entity / Applicant (Individual named on page 2 of this application), enter Name, NPI, Home Address - Street, City & State, Zip Code (9 digits), SSN and Date of Birth.
For Ownership in Applicant (if required by 18NYCRR, Section 504.1(d)(18)(iv)), enter Name of Individual or Entity, % of Ownership, NPI, Address (Home Address if individual), City & State, Zip Code (9 digits), SSN (if indiv)/ FEIN (if entity), Date of Birth (if individual) and Familial Relationship (if individual, if any). Include familial relationship to the Applicant and other Owners (spouse, parent, child, sibling), if any. The address for corporate entities must include every business address.
SECTION 2: Ownership in Other Disclosing Entities, SECTION 3: Ownership in Subcontractors and SECTION 4: Familial Relationship in Subcontractors
Complete SECTION 2, Ownership in Other Disclosing Entities(ODE), if any identified in Section 1 has an ownership or control interest in ODE: enter Name (from Section 1), Name of ODE and NPI or Medicaid ID of ODE.
SECTION 3, Ownership in Subcontractors: if the Applicant has an ownership or control interest of 5% or more in a subcontractor and an Owner of the Applicant also has an ownership or control interest in the subcontractor, enter the Owner's Name (from Section 1), Subcontractor Name and Tax Identification Number.
SECTION 4, Familial Relationship in Subcontractors: if those identified in Section 3 have a familial relationship (parent, child, sibling, spouse) with a person with ownership or control interest in one of the subcontractors identified in Section 3, enter the Owner's Name (from Section 1), Subcontractor's Name and Name & Familial Relationship.
SECTION 5: Managing Employees, Agents, & Those with a Control Interest
In SECTION 5, list Managing Employees, Agents, & Those with a Control Interest - Including, but not necessarily limited to, the Compliance Officer and all Managing Employees. Enter Name, Association Type (see instructions), Home Address - Street, City & State, Zip Code (9 digits), SSN, Date of Birth and Familial Relationship, which is the relationship to the Provider (spouse, parent, child, sibling), if any. If additional space is needed, copy form; all entries must be on the form.
SECTION 6: questions 1 to 5
SECTION 6: respond to the questions on behalf of the Applicant, all individuals and entities identified in Sections 1 & 5 and any entity in which the Applicant has a 5% or more ownership. Mark Yes or No for each of questions 1 to 4. All questions must be answered.
If you answered “Yes” to any of the questions above in SECTION 6, you must complete and submit the “Prior Conduct Questionnaire” available at www.emedny.org.
Answer Question 5: do you, including any entity in which you have ownership, have any unpaid balances owed to the NY Medicaid Program? If yes, indicate amount; if yes, has payment been arranged? If yes, attach verification of arrangement. If no to payment arranged, this enrollment will be reviewed by the OMIG.
SIGNATURE AND AFFIRMATION
Sign the Applicant / Provider's Signature line (original; no stamps), and enter the Date and the Name & Telephone Number of Person who Prepared Application.
Whoever knowingly and willfully makes or causes to be made a false statement or representation on this statement may be prosecuted under applicable Federal or State laws.
More rules for Form EMEDNY-436901
Complete pages 2 through 5; the form must be completed in its entirety.
Common questions about Form EMEDNY-436901
Where do I file it?
Mail to: eMedNY PO Box 4603 Rensselaer, NY 12144-4603.
When is this form not the right one?
If you will also provide medical services to patients, or as an attending provider will submit a separate claim to Medicaid for your service, do not complete this form.
Sources
[1] Form EMEDNY-436901 (5/26), New York State Medicaid Enrollment Form, New York State Department of Health (the Official source link on this page).