


EPSDT-PCS Form 90 at a glance
What it is: This is the Request for Medicaid EPSDT - Personal Care Services, and the Personal Care Services are to be provided in the home and not in an institution.
Who signs: By signing this form you give your consent for your medical information to be released to the Department of Health and Hospitals to be used in determining eligibility for Personal Care Services; enter the Signature and the Date. Sign on the Practitioner's Signature line and enter the Date.
A filled-in EPSDT-PCS Form 90 example: a mother requests care for her daughter

How to fill out EPSDT-PCS Form 90, box by box
Box 1, Applicant Name

In box 1, enter the Applicant Name and the MID#.
Enter the Address, the Ph#, and the DOB, and check Male or Female.
Box 2, Responsible Party/Curator
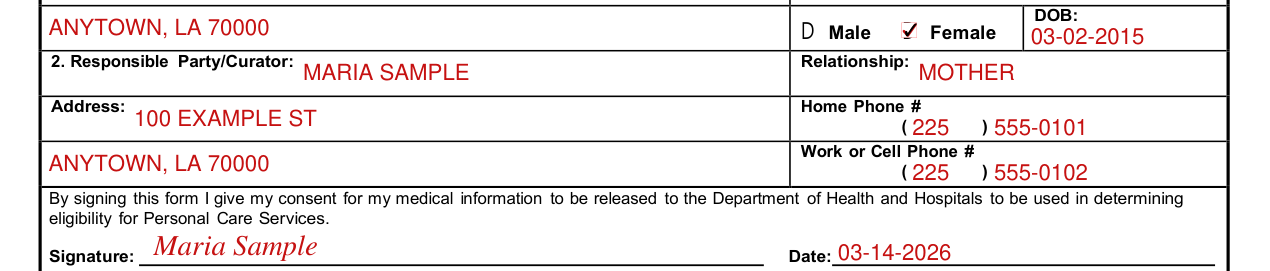
In box 2, enter the Responsible Party/Curator and the Relationship.
Enter the Address, the Home Phone # and the Work or Cell Phone #.
II. Medical information, boxes 1 to 8
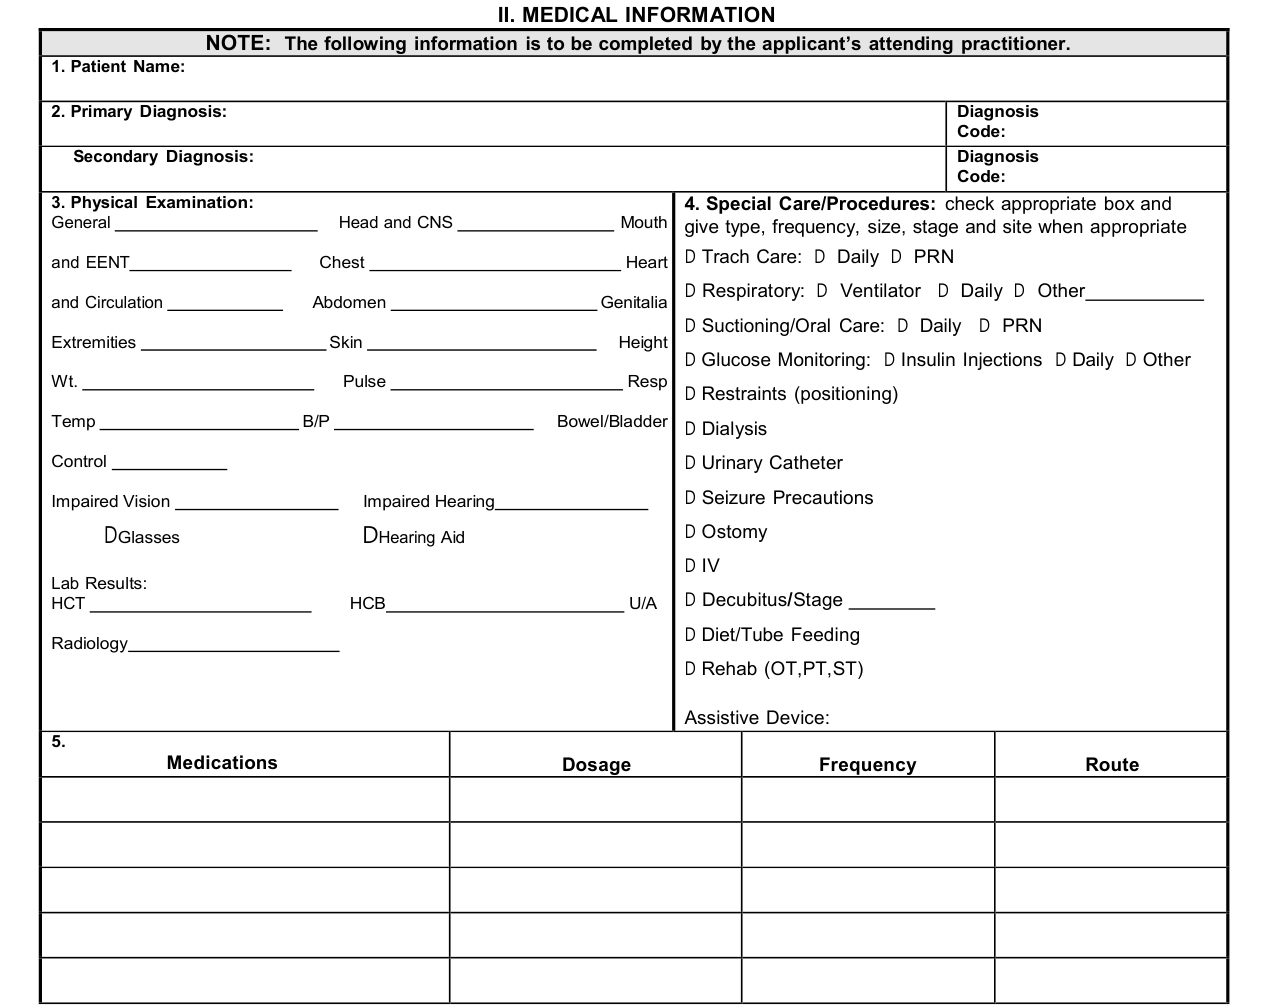
II. MEDICAL INFORMATION is to be completed by the applicant's attending practitioner; in box 1, enter the Patient Name.
In box 2, enter the Primary Diagnosis with its Diagnosis Code, and the Secondary Diagnosis with its Diagnosis Code.
In box 3, Physical Examination, enter General, Head and CNS, Mouth and EENT, Chest, Heart and Circulation, Abdomen, Genitalia, Extremities, Skin, Height, Wt., Pulse, Resp, Temp, B/P, Bowel/Bladder Control, Impaired Vision, Impaired Hearing, the Lab Results HCT, HCB and U/A, and the Radiology.
In box 4, Special Care/Procedures, check the appropriate box and give type, frequency, size, stage and site when appropriate.
Check Trach Care (Daily or PRN), Respiratory (Ventilator, Daily or Other), Suctioning/Oral Care (Daily or PRN), Glucose Monitoring (Insulin Injections, Daily or Other), Restraints (positioning), Dialysis, Urinary Catheter, Seizure Precautions, Ostomy, IV, Decubitus/Stage, Diet/Tube Feeding and Rehab (OT,PT,ST).
Enter the Assistive Device. In 5. Medications, enter the Medication with its Dosage, Frequency and Route.
In II. MEDICAL INFORMATION (Continued), under 6. Recent Hospitalizations, include psychiatric.
In 7. Mental Status/Behavior, check Yes or No. If Yes, indicate frequency: 1 = seldom; 2 = frequent; 3 = always.
Check Yes or No for Oriented, Depressed, Cooperative, Physically Abusive, Verbally Abusive, Passive, Verbal, Comatose, Hostile, Forgetful, Confused, Combative and Non-responsive.
Check Yes or No for Injures Self/Others (1 2 3). In 8. Impairments, please rate the following, 1- Mild, 2-Moderate, 3-Severe:
Walking, Chronic heart failure, Vision impairment, Spasticity, Speech impairment, Oral feeding, Bladder and bowel incontinence, Limb weakness, Seizure Disorder, Intellectual impairment, Chronic Resp distress, Hypotonia, Developmental delay and Hearing impairment.
III. Level of care
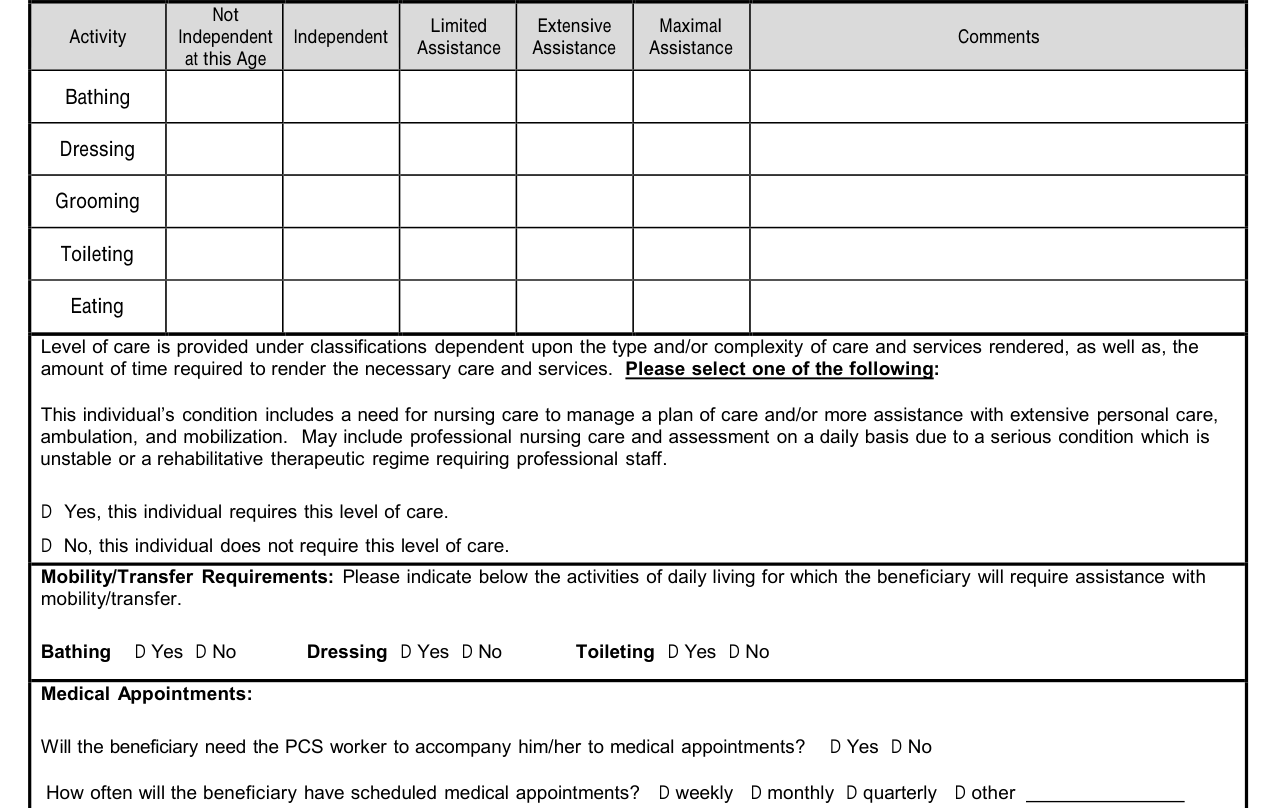
In III. LEVEL OF CARE DETERMINATION, Activities of Daily Living, the attending practitioner should check the appropriate box as it applies to the beneficiary's ability to perform this age appropriate tasks. Not Independent at this Age - not age appropriate to perform this task independently. Independent - the beneficiary is able to perform the task without assistance. Limited Assistance - the beneficiary aids in the task, but receives help from other persons some of the time. Extensive Assistance - the beneficiary aids in the task, but receives help from other persons all of the time. Maximal Assistance - the beneficiary is entirely dependent on other persons.
An additional 15 minutes can be added to bathing, dressing and toileting if mobility/transfer assistance is required (EPSDT - PCS Level of Assistance Guide).
Additional time to complete the tasks will be considered if there is sufficient medical documentation provided. Please use the comments section and attach documentation to support the need for additional time to complete the ADL's.
In addition to the PCS tasks listed, assistance with incidental household chores may be approved. This does not include routine household chores such as regular laundry, ironing, mopping, dusting, etc.
The following information is to be completed by the applicant's attending practitioner. Check the appropriate box using the definitions and EPSDT PCS Level of Assistance Guide to assist with determining the level of care.
For each Activity (Bathing, Dressing, Grooming, Toileting and Eating), check Not Independent at this Age, Independent, Limited Assistance, Extensive Assistance or Maximal Assistance, and enter Comments.
Level of care is provided under classifications dependent upon the type and/or complexity of care and services rendered, as well as, the amount of time required to render the necessary care and services.
Please select one of the following: Yes, this individual requires this level of care, or No, this individual does not require this level of care. This individual's condition includes a need for nursing care to manage a plan of care and/or more assistance with extensive personal care, ambulation, and mobilization. May include professional nursing care and assessment on a daily basis due to a serious condition which is unstable or a rehabilitative therapeutic regime requiring professional staff.
Mobility/Transfer Requirements: Please indicate Yes or No for Bathing, Dressing and Toileting, the activities of daily living for which the beneficiary will require assistance with mobility/transfer.
Under Medical Appointments, check Yes or No: will the beneficiary need the PCS worker to accompany him/her to medical appointments? Check how often the beneficiary will have scheduled medical appointments: weekly, monthly, quarterly or other. Reason for PCS worker to accompany child to medical appointments.
IV. Practitioner's order and signature
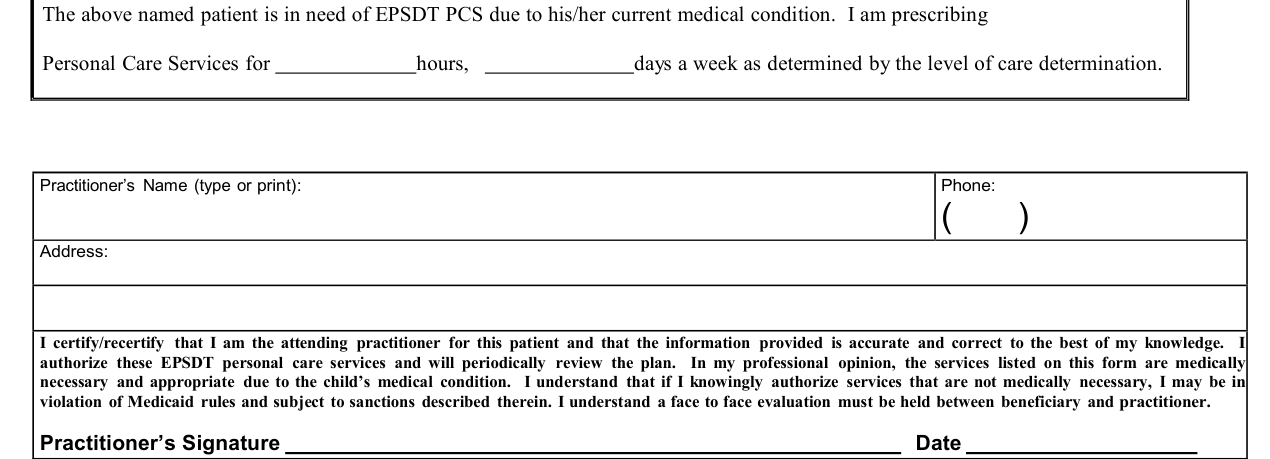
In IV. PRACTITIONER'S ORDER, the patient is in need of EPSDT PCS due to his/her current medical condition; enter the hours and the days a week of Personal Care Services as determined by the level of care determination.
Enter the Practitioner's Name (type or print), the Phone and the Address.
The attending practitioner certifies or recertifies that the information provided is accurate and correct to the best of their knowledge, authorizes these EPSDT personal care services and will periodically review the plan. In the practitioner's professional opinion, the services listed on this form are medically necessary and appropriate due to the child's medical condition. The practitioner understands that if they knowingly authorize services that are not medically necessary, they may be in violation of Medicaid rules and subject to sanctions described therein. A face to face evaluation must be held between beneficiary and practitioner.
Sources
[1] EPSDT-PCS Form 90 (Revised May 2019), Request for Medicaid EPSDT - Personal Care Services, Louisiana Medicaid (the Official source link on this page).