


Form 90-L at a glance
What it is: OIDD Form 90-L is the REQUEST FOR MEDICAL ELIGIBILITY DETERMINATION.
Who signs: SIGN: G. Applicant/Responsible Party Signature and Date. MD or Nurse Practitioner signature is required.
A filled-in Form 90-L example: a son requests an eligibility determination for his mother
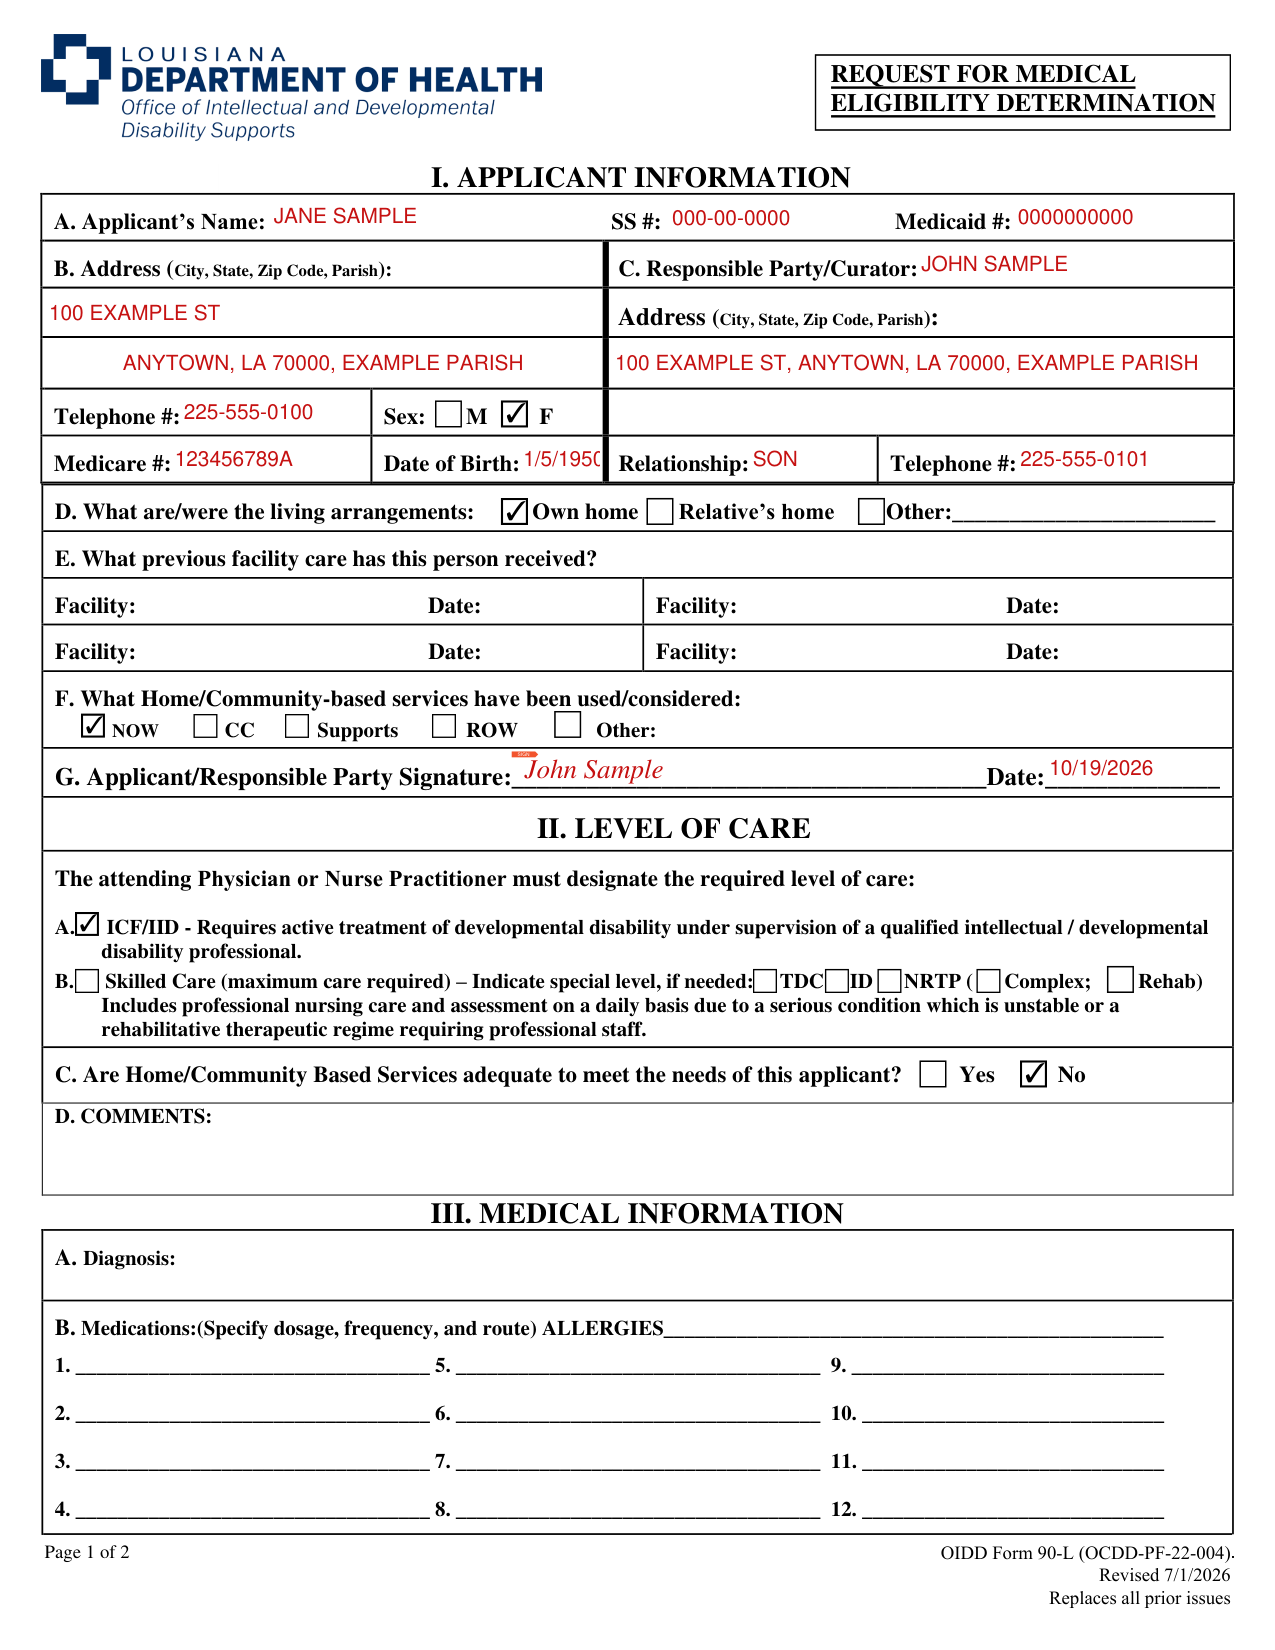
How to fill out Form 90-L, box by box
I. APPLICANT INFORMATION
Under I. APPLICANT INFORMATION, enter A. Applicant's Name, SS # and Medicaid #.
Enter B. Address (City, State, Zip Code, Parish) and C. Responsible Party/Curator, with the Address (City, State, Zip Code, Parish).
Enter the Telephone #, mark Sex M or F, and enter the Medicare #, Date of Birth, Relationship and Telephone #.
D. What are/were the living arrangements: mark Own home, Relative's home or Other, and write the Other.
E. What previous facility care has this person received? Enter each Facility and Date.
F. What Home/Community-based services have been used/considered: mark NOW, CC, Supports, ROW or Other, and write the Other.
Applicant/Responsible Party Signature
Sign on the Applicant/Responsible Party Signature line and enter the Date.
II. LEVEL OF CARE
The attending Physician or Nurse Practitioner must designate the required level of care.
A. ICF/IID requires active treatment of developmental disability under supervision of a qualified intellectual / developmental disability professional.
B. Skilled Care (maximum care required) includes professional nursing care and assessment on a daily basis due to a serious condition which is unstable or a rehabilitative therapeutic regime requiring professional staff; indicate special level, if needed: TDC, ID or NRTP (Complex; Rehab).
C. Are Home/Community Based Services adequate to meet the needs of this applicant? Mark Yes or No.
Write any comments under D. COMMENTS.
III. MEDICAL INFORMATION
Under III. MEDICAL INFORMATION, write the A. Diagnosis.
Under B. Medications, specify dosage, frequency, and route, and enter ALLERGIES.
Write the C. Recent Hospitalizations.
D. Mental Status/Behavior: check Yes or No for 1. Oriented, 2. Forgetful, 3. Depressed, 4. Comatose, 5. Confused, 6. Wanders, 7. Hostile and 8. Combative. If Yes, indicate frequency: 1 = seldom; 2 = frequent; 3 = always.
E. Communications: mark Verbal or Non-verbal.
F. Activities of Daily Living
F. Activities of Daily Living: check appropriate box, SELF, ASSIST or TOTAL, for 1. Eating, 2. Bathing, 3. Personal, 4. Ambulation, 5. Transfer, 6. Bowel Incontinence, 7. Bladder Incontinence and 8. Urinary Catheter.
Also fill in 9. Impaired vision (Glasses), 10. Impaired hearing (Hearing Aid) and 11. Dentures.
G. SPECIAL CARE/PROCEDURES
G. SPECIAL CARE/PROCEDURES: check appropriate box: when appropriate give type, frequency, size, stage, and site for 1. Ostomy care, 2. Glucose Monitoring, 3. Restraints, 4. IV's, 5. Suctioning, 6. Specialized Rehab, 7. MRSA/Infections, 8. Diet/Tube Feeding, 9. Dialysis, 10. Respiratory, 11. Wound Care/Decubitus, 12. Tracheostomy Care, 13. Ventilator Dependent and 14. Other.
H. PHYSICAL EXAMINATION
Under H. PHYSICAL EXAMINATION, enter Height, Weight, Pulse, Resp, Temp and B/P; under Lab Results, enter HCT, HGB and U/A; then enter Radiology, General, Head and CNS, Mouth and EENT, Chest, Heart and Circulation, Abdomen, Genitalia, Extremities, Skin and Other.
Physician, Nurse Practitioner or Physician Assistant Signature
MD signature may be delegated to a Physician Assistant. In this case, a supervising physician must be identified.
Print the Physician or Nurse Practitioner's Name and enter the Phone and the Address.
Print the Physician Assistant Name.
Sign on the Physician/Nurse Practitioner/Physician Assistant Signature line, enter the Date, and identify the signer's profession/credentials.
Sources
[1] OIDD Form 90-L (OCDD-PF-22-004), Revised 7/1/2026, ldh.la.gov (the Official source link on this page).