
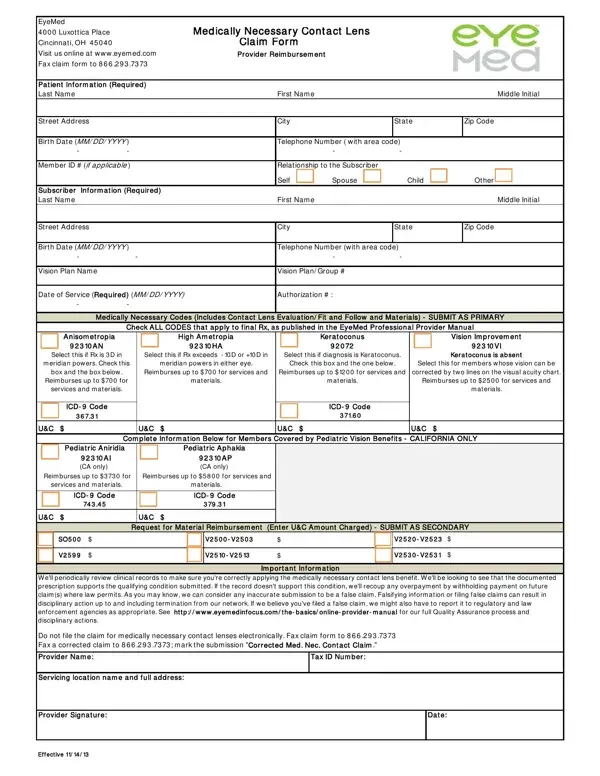
Medically Necessary Contact Lens In-network Claim Form at a glance
What it is: The Medically Necessary Contact Lens In-network Claim Form is a claim form of First American Administrators, Inc., a wholly owned subsidiary of EyeMed Vision Care, LLC.
Who signs: Provider Attestation: By signing the provider attests that the patient meets the requirements to receive medically necessary contact lenses per the criteria on this form, and that the patient is unable to achieve adequate functional vision without contact lenses.
A filled-in Medically Necessary Contact Lens In-network Claim Form example: a provider files a claim for high ametropia
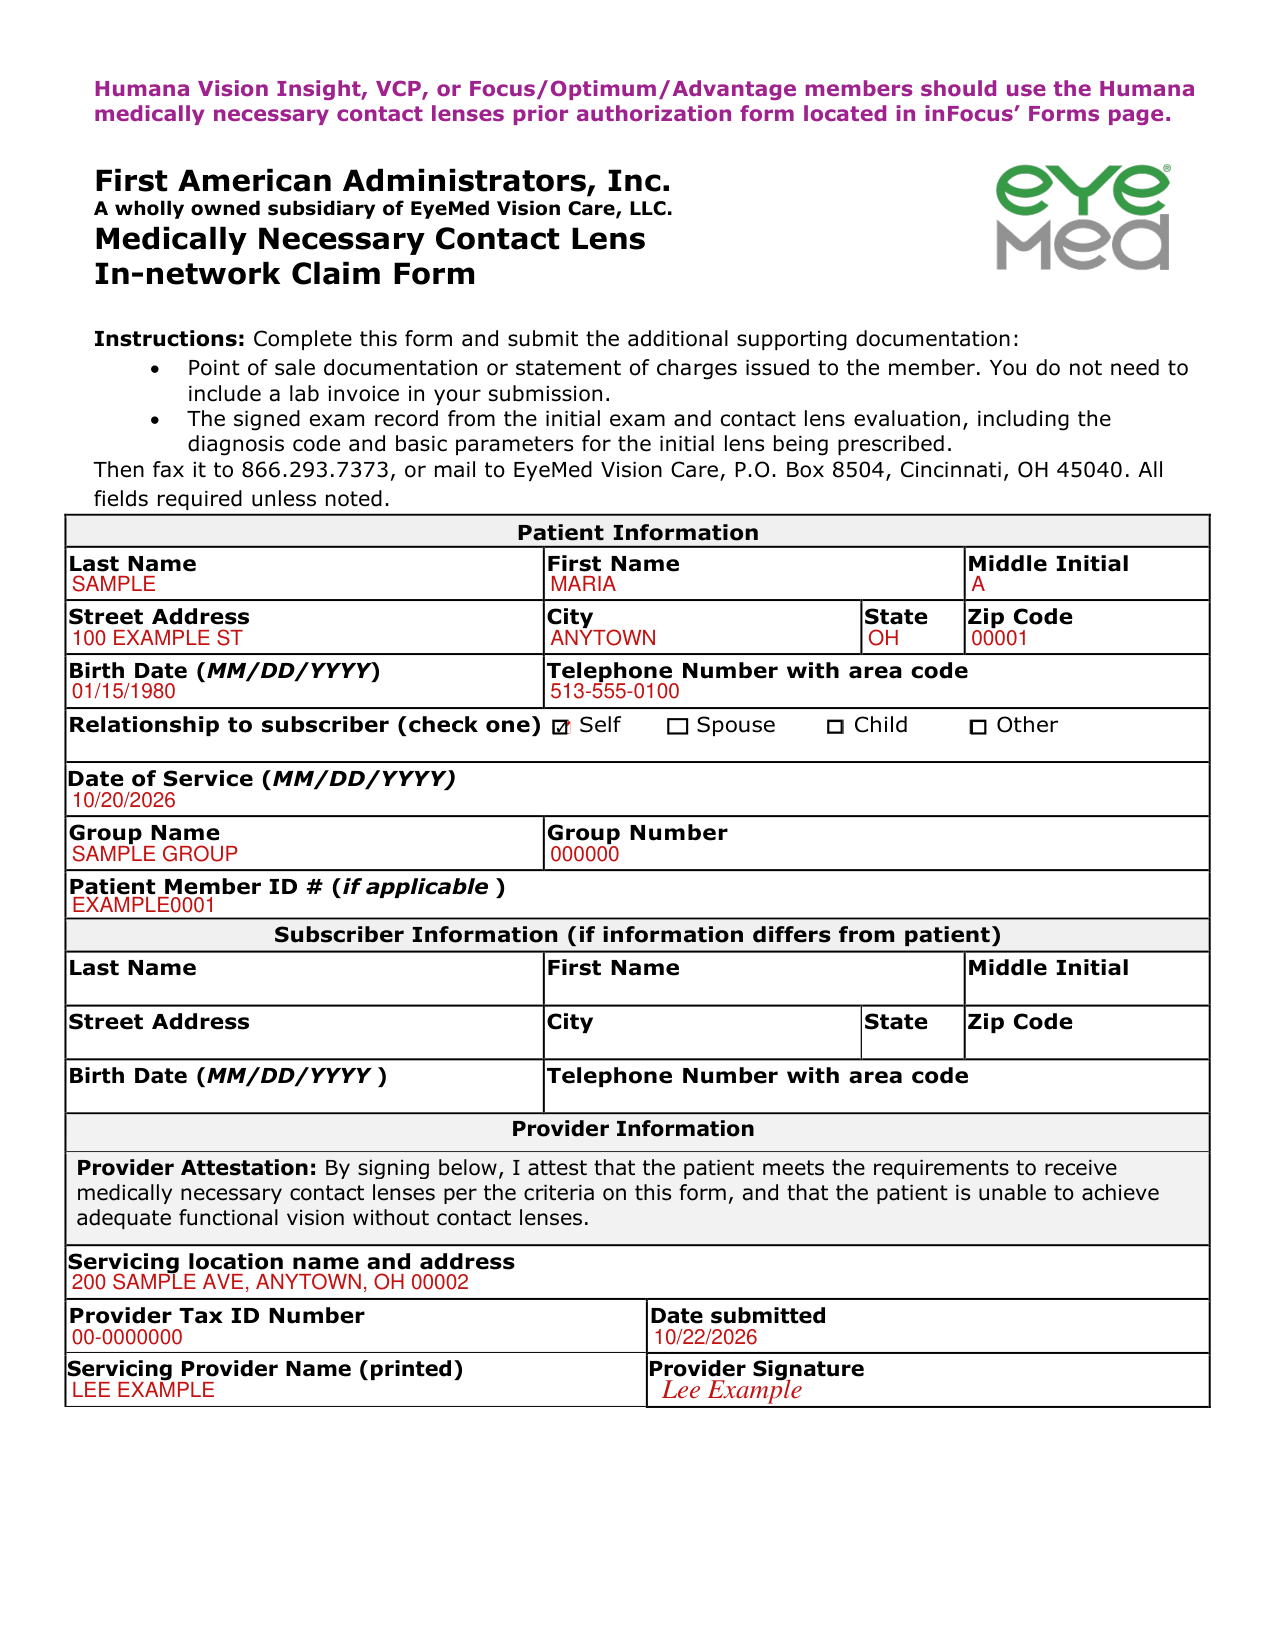
How to fill out Medically Necessary Contact Lens In-network Claim Form, box by box
Patient Information

Under Patient Information, enter Last Name, First Name and Middle Initial.
Enter Street Address, City, State and Zip Code.
Enter Birth Date (MM/DD/YYYY) and Telephone Number with area code.
Relationship to subscriber (check one)

Relationship to subscriber (check one): Self, Spouse, Child or Other.
Date of Service, Group Name, Group Number and Patient Member ID
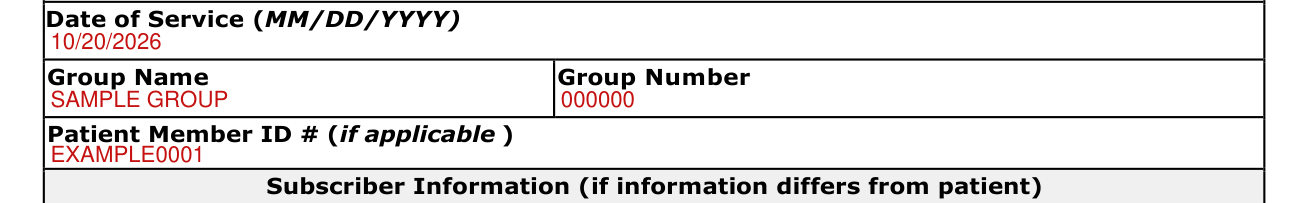
Enter Date of Service (MM/DD/YYYY), Group Name, Group Number and Patient Member ID # (if applicable).
Subscriber Information (if information differs from patient)
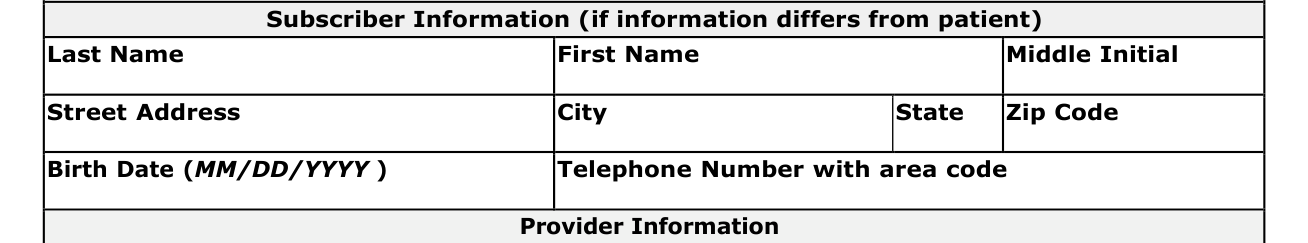
Subscriber Information (if information differs from patient): enter Last Name, First Name, Middle Initial, Street Address, City, State, Zip Code, Birth Date (MM/DD/YYYY) and Telephone Number with area code.
Servicing location, Provider Tax ID Number and Provider Signature
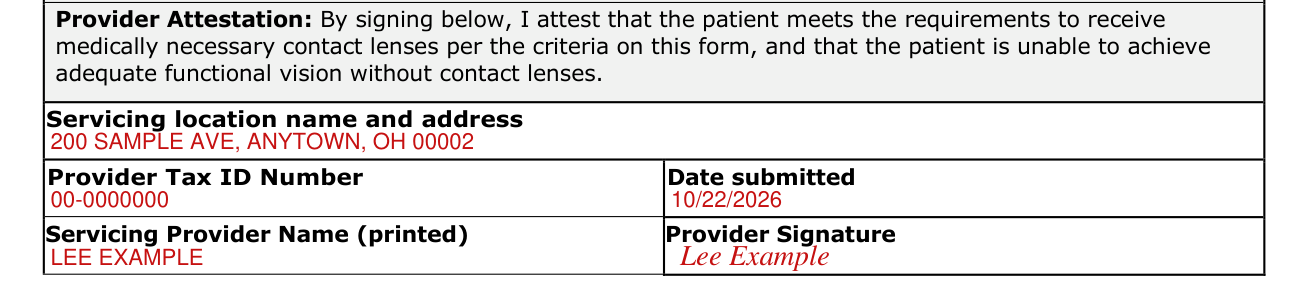
Enter the Servicing location name and address, Provider Tax ID Number, Date submitted, Servicing Provider Name (printed) and Provider Signature.
Medically Necessary Qualifying Conditions
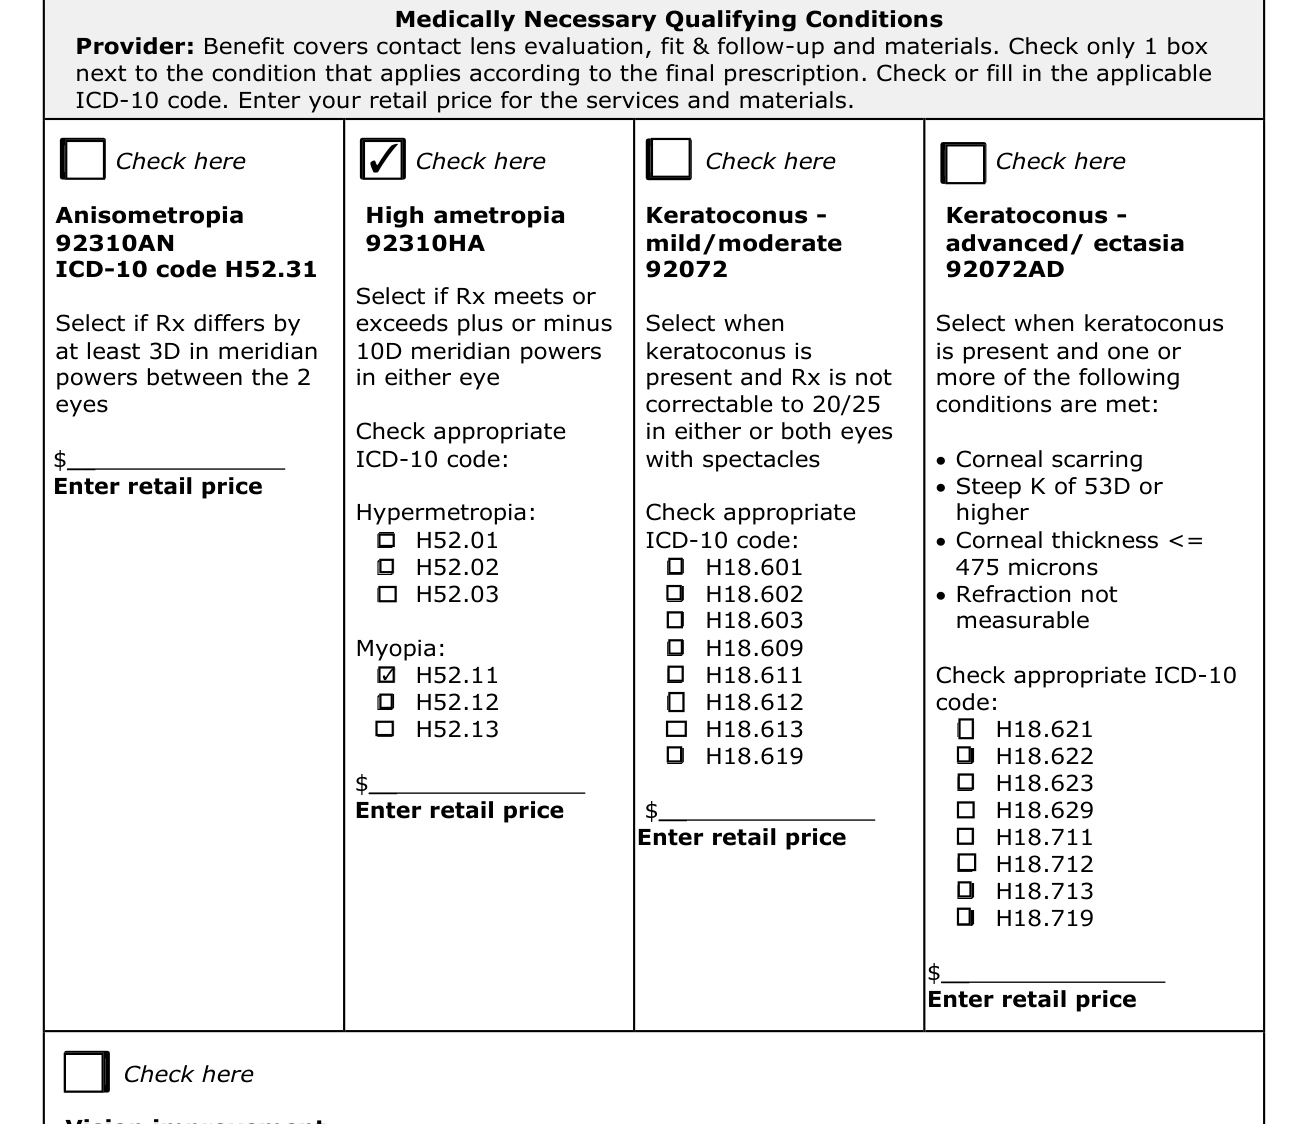
Benefit covers contact lens evaluation, fit & follow-up and materials. Check only 1 box next to the condition that applies according to the final prescription.
Check or fill in the applicable ICD-10 code. Enter your retail price for the services and materials.
Anisometropia 92310AN, ICD-10 code H52.31: select if Rx differs by at least 3D in meridian powers between the 2 eyes.
High ametropia

High ametropia 92310HA: select if Rx meets or exceeds plus or minus 10D meridian powers in either eye. Check appropriate ICD-10 code: Hypermetropia: H52.01, H52.02, H52.03. Myopia: H52.11, H52.12, H52.13.
Keratoconus - mild/moderate
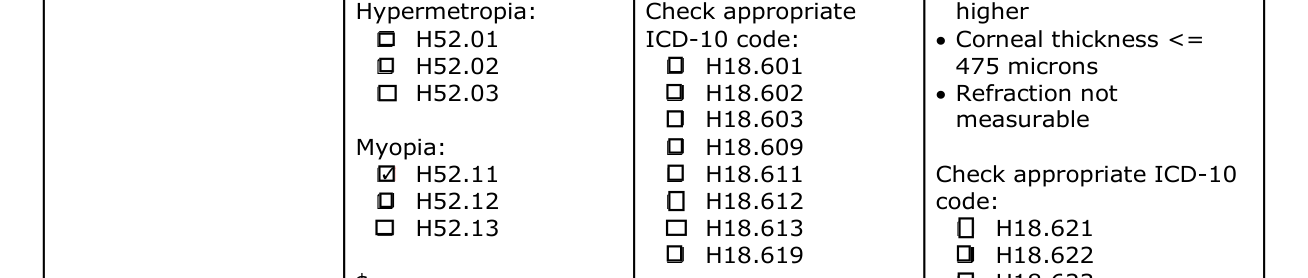
Keratoconus - mild/moderate 92072: select when keratoconus is present and Rx is not correctable to 20/25 in either or both eyes with spectacles. Check appropriate ICD-10 code: H18.601, H18.602, H18.603, H18.609, H18.611, H18.612, H18.613, H18.619.
Keratoconus - advanced/ ectasia
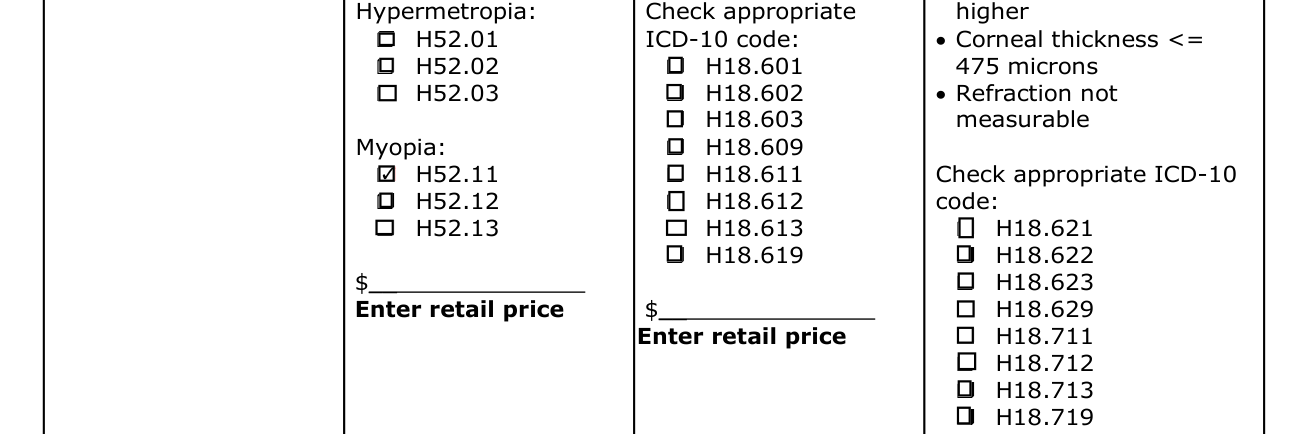
Keratoconus - advanced/ ectasia 92072AD: select when keratoconus is present and one or more of the following conditions are met: Corneal scarring; Steep K of 53D or higher; Corneal thickness <= 475 microns; Refraction not measurable. Check appropriate ICD-10 code: H18.621, H18.622, H18.623, H18.629, H18.711, H18.712, H18.713, H18.719.
Vision improvement

Vision improvement 92310VI: Keratoconus is absent. Select for members whose vision can be improved by 2 lines on the visual acuity chart when compared to best corrected standard spectacle lenses. Enter ICD-10 code: ___.___
More rules for Medically Necessary Contact Lens In-network Claim Form
Humana Vision Insight, VCP, or Focus/Optimum/Advantage members should use the Humana medically necessary contact lenses prior authorization form located in inFocus' Forms page.
Medically necessary contact lens claims are subject to state-specific fraud warnings (PDF-2403-P-332 3).
Common questions about Medically Necessary Contact Lens In-network Claim Form
Where do I file it?
Complete this form and submit the additional supporting documentation: point of sale documentation or statement of charges issued to the member (you do not need to include a lab invoice in your submission) and the signed exam record from the initial exam and contact lens evaluation, including the diagnosis code and basic parameters for the initial lens being prescribed. Then fax it to 866.293.7373, or mail to EyeMed Vision Care, P.O. Box 8504, Cincinnati, OH 45040. All fields required unless noted.
Sources
[1] Medically Necessary Contact Lens In-network Claim Form (PDF-2403-P-332), First American Administrators, Inc., EyeMed Vision Care (the Official source link on this page).