
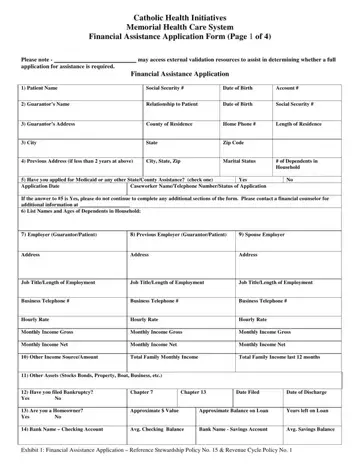
Financial Assistance Application at a glance
What it is: Catholic Health Initiatives Memorial Health Care System Financial Assistance Application Form.
Who signs: Sign on the Signature (Guarantor/Patient) line and add the Date. The Signature (Spouse) line also has a Date.
A filled-in Financial Assistance Application example: a patient who is also the guarantor
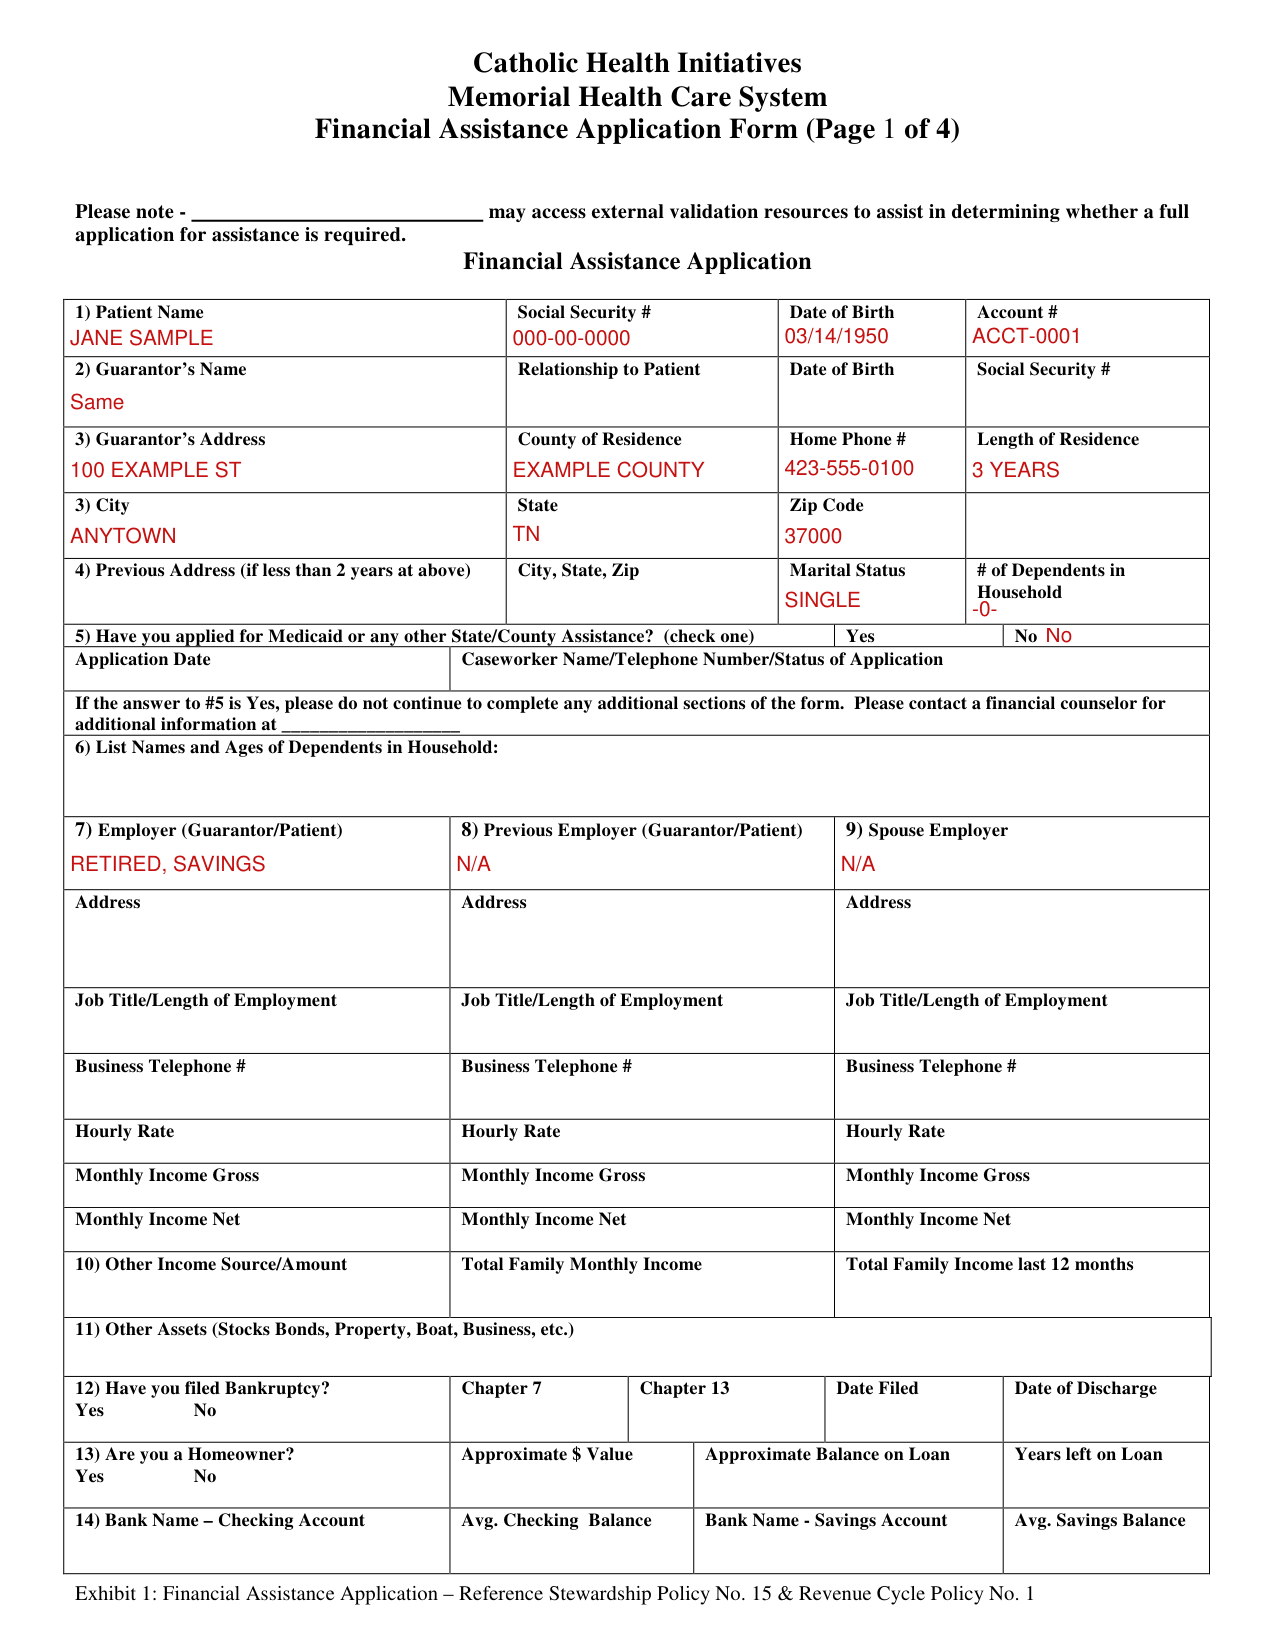
How to fill out Financial Assistance Application, box by box
Patient

Complete the patient name, patient's social security number, patient's date of birth, and the hospital account number(s) if known.
Guarantor

2) Complete the guarantor name, relationship to patient, guarantor's date of birth, and guarantor's social security number. If the guarantor is the same as the patient, note “Same” in this field.
Guarantor’s address
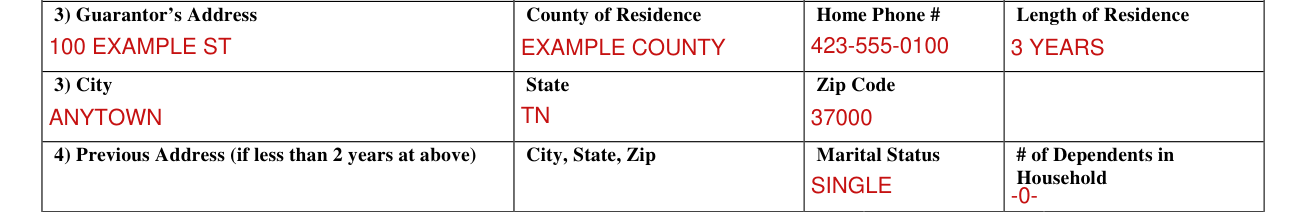
3) Complete the guarantor's address, home telephone number and length of residence at the guarantor's address.
Previous address, marital status and dependents

4) Complete the guarantor's previous address (if current residence is less than two years), guarantor's marital status, and number of dependents living in household. If there are no dependents, please mark “-0-“ in the dependent field.
Medicaid or other State/County assistance

5) Complete the questions regarding Medicaid and other State/County assistance. Please advise if you have applied for assistance (and on what date). Provide the assigned Caseworker's name, telephone number and the status of the application. You may attach a separate sheet if needed.
If your response is “Yes”, please do not proceed to complete any additional sections of the form. Please contact a financial counselor for additional information.
If this section does not apply to you, please indicate this by marking it with N/A.
Names and ages of dependents

6) List the names and ages of dependents.
Employer, previous employer and spouse employer
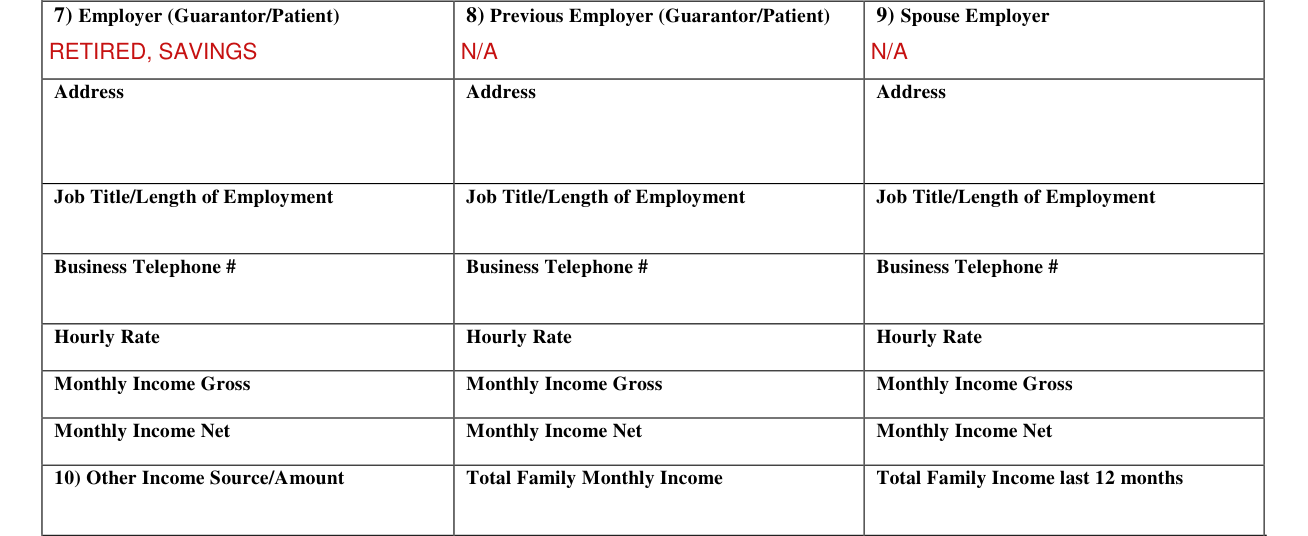
7) Complete the employer information for the guarantor or patient, depending upon who has responsibility for the balance. Please complete the name of the employer, the employer's address, the guarantor/patient's job title and length of employment.
Please also include the guarantor/patient's business telephone number, hourly (or salary) rate, and the monthly income (both gross and net).
If there is no employment, please note how expenses are being met.
8) Complete the previous employer information for the guarantor/patient. This includes the employer's name and address, the guarantor/patient's job title and length of employment, business telephone number, hourly rate, and monthly income (both gross and net). If there is no prior employment, mark “N/A”.
9) Complete the income information for the guarantor/patient's spouse. Include the name of the employer, the employer's address, job title/length of employment, business telephone number, hourly rate, and monthly income (both gross and net). If the spouse is unemployed, or there is no spouse, mark “N/A”.
Other income and total family income

10) Complete the other income source/amount. This is for child support, social security, bonus amounts from employers, etc. This also includes rental income, alimony, pension income, welfare and VA benefits.
Complete the total family income (add the guarantor/patient net income), then complete the total family income from the last 12 months.
Other assets, bankruptcy, home and banks
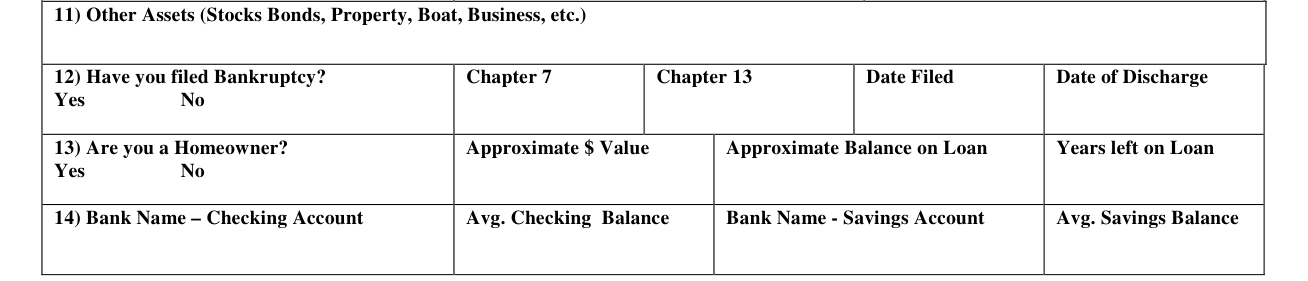
11) Please complete the section listing other assets you may have. This includes stocks, bonds, property, boats and businesses you may own. Use additional paper if needed to give complete details. If there are no additional assets, please mark “N/A”.
12) Please indicate if you have ever filed bankruptcy. If you have not filed bankruptcy, please mark “No”. Please verify that all questions have been completed. Attach additional paper if needed for any explanations.
13) Please complete the homeowner information. If you are a homeowner, please note the approximate dollar value, the approximate balance on the loan, and the number of years left on the loan. If you are not a homeowner, please mark “No”.
14) Please complete the banking information as requested and list the bank name. Complete the checking account number and provide the average checking account balance. Please do the same for the savings account field. If there is no savings account, please place “N/A” in the savings field.
Automobiles and monthly expenses
15) For automobile information, please list the make, model and year of your vehicle. Please list the monthly payment amount and the current balance. Attach additional documentation for more than four autos.
Please verify the amount you are paying in rent or by mortgage. If you do not pay rent or mortgage, please note why you have no payment or if you live with relatives or others.
Please indicate any charge card payments you are currently making. Please indicate the monthly payment amount, to whom the payment is made, the account number and the current balance due. Please indicate the credit limit for each card. If you have no charge cards please note “N/A”.
Please indicate any bank loans you may be paying. If you have no bank loans, please mark “N/A”.
Please list any educational loans you may be paying. Please specify if you are paying school loans, etc. If this does not apply to you, please mark “N/A”.
Please list the amount paid on a monthly basis for electricity, gas, water, trash and any other utility you may pay. Please add these and place the total (for all of them) in the utilities section. If there are no monthly utilities paid, please mark “N/A” in this section and explain.
Please place the total amount you pay on a monthly basis for auto insurance. If you pay on a quarterly basis, please divide the quarterly payment by three and place the amount in this section. If you pay every six months, please divide the total amount you pay by six and place the amount in this section.
Please estimate your monthly expenses and place this amount in this section.
Signing and attachments
Income verification must be attached - W2, Pay Stub, Tax Return with schedules, etc. In addition to the items requested by this application, you may attach bank statements, copies of social security checks (or letters).
If there is no income, please verify how expenses are being met. It is important to explain a lack of income completely so that full consideration of your application can be made.
If the guarantor/patient or the spouse is self-employed, please attach the last 2-3 months of bank statements.
All documentation must be attached for full consideration. If the application is incomplete, it will be returned.
CERTIFICATION 1. “I, the undersigned, certify that the completed information in this document is true and accurate to the best of my knowledge.”
Sign on the Signature (Guarantor/Patient) line and add the Date. The Signature (Spouse) line also has a Date.
Common questions about Financial Assistance Application
Where do I file it?
Please complete and mail your Financial Assistance Application to: Attn: Business Office - Financial Assistance Request, Memorial Health Care System, 2525 de Sales Avenue, Chattanooga, TN 37404
Sources
[1] Financial Assistance Application (the served file; no issuer file found) (the Official source link on this page).
