
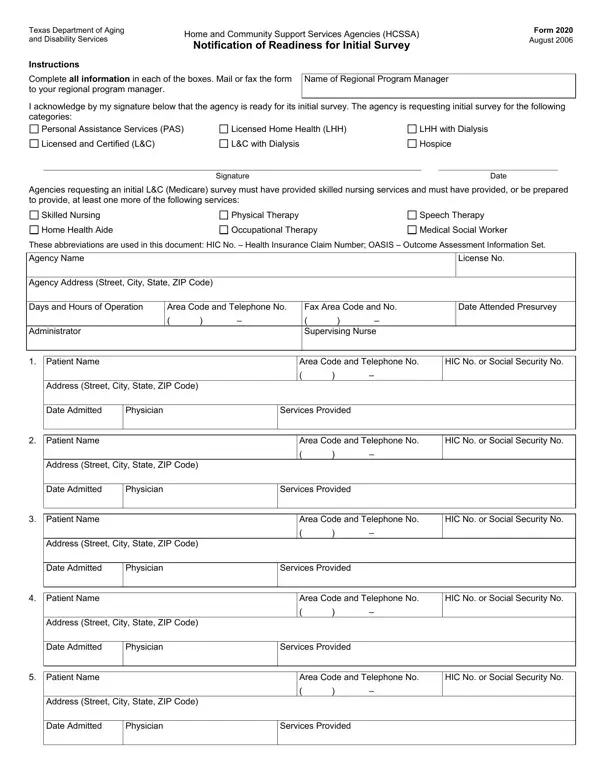

Form 2020 at a glance
What it is: Form 2020 is the Home and Community Support Services Agencies (HCSSA) Notification of Readiness for Initial Survey, with Section 1 - An Agency's Request for an Initial Licensure Survey.
Who signs: By signature, the Authorized Representative acknowledges that the agency is ready for its initial survey. Enter the Date.
No later than six months after the effective date of an agency's initial license, an agency must admit and provide services to clients as described in 26 TAC Section 558.521(b) and submit this form to the designated survey office, except as described in 26 TAC Section 558.521(f).
No later than six months after the effective date of the initial license of a hospice with an inpatient unit located at the hospice's principal place of business, a hospice must admit and provide routine home services to clients as described in 26 TAC Section 558.521(b), admit and provide inpatient services to at least one client, and submit this form to the designated survey office, except as described in 26 TAC Section 558.521(f).
A filled-in Form 2020 example: a home health agency gives notice of readiness
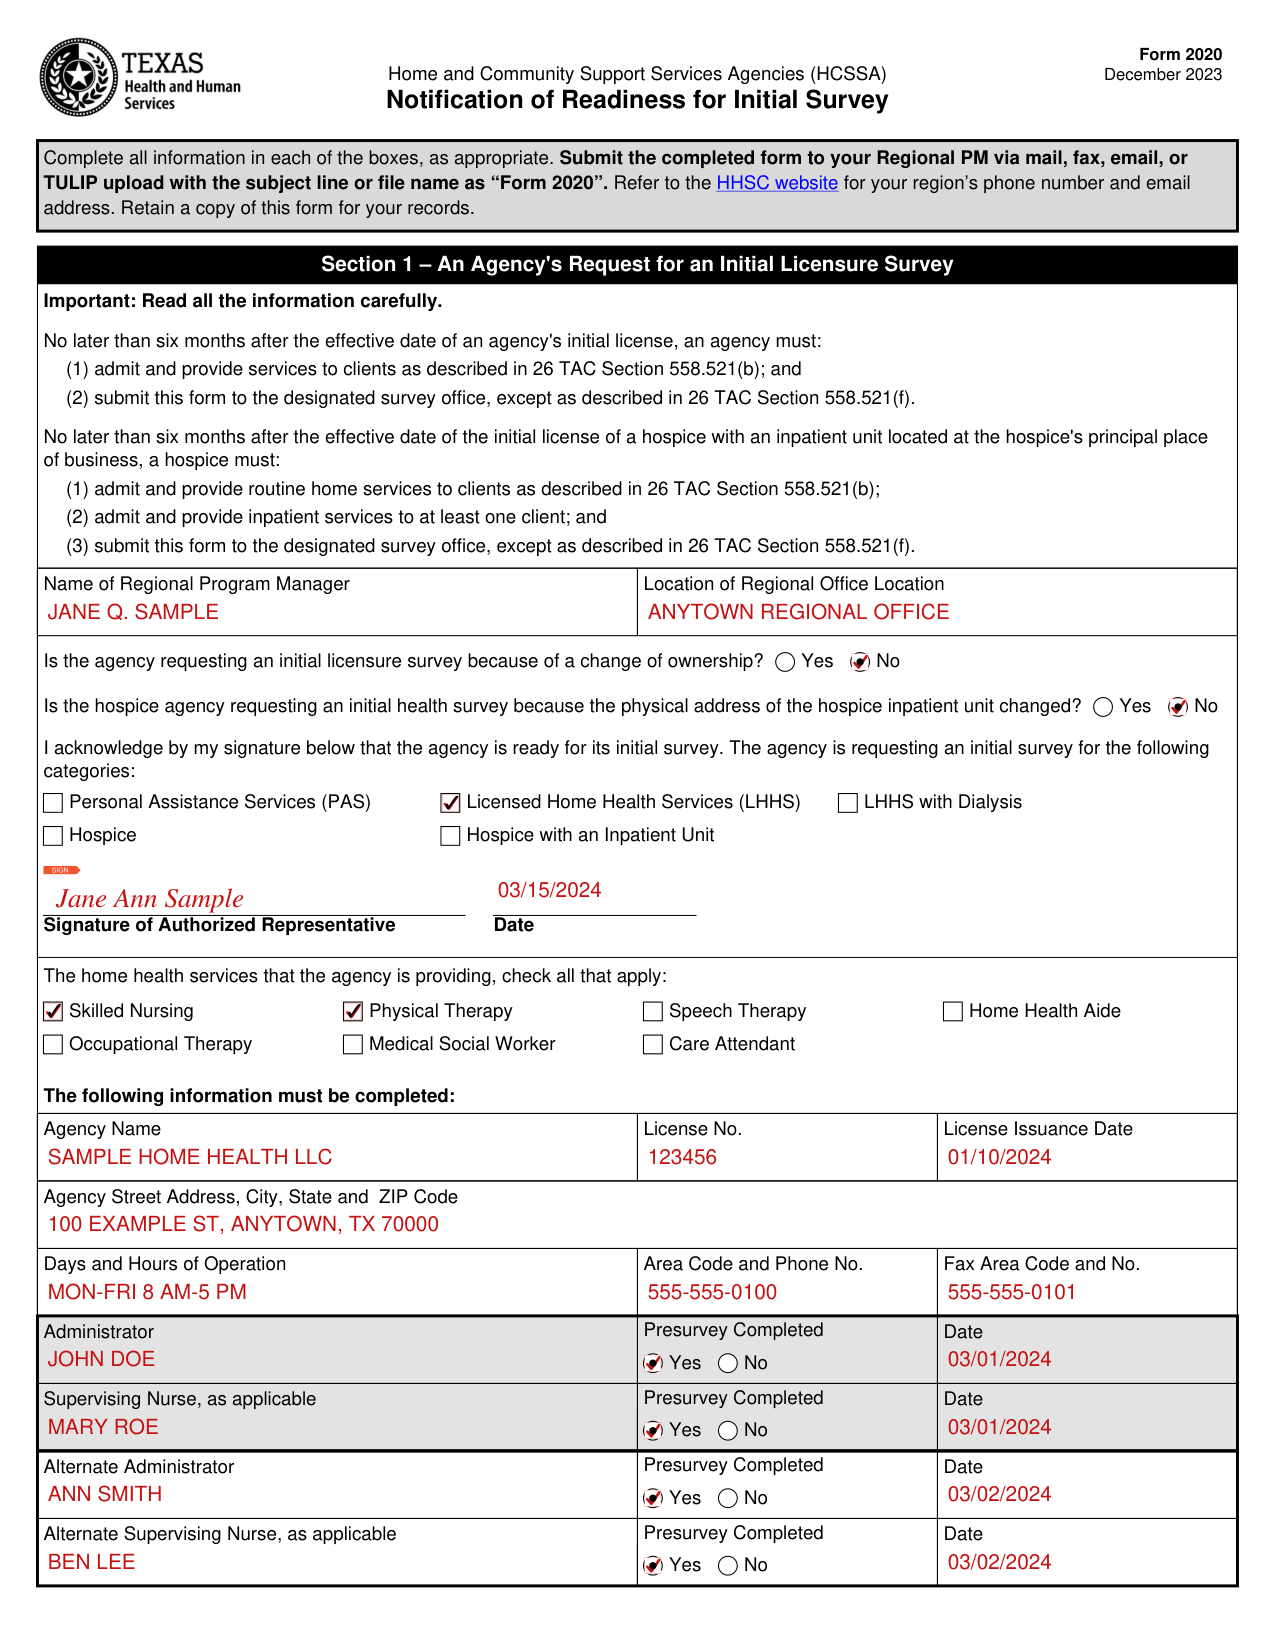
How to fill out Form 2020, box by box
Name of Regional Program Manager and Location of Regional Office

Enter the Name of Regional Program Manager and the Location of Regional Office Location.
Is the agency requesting an initial licensure survey because of a change of ownership?
Is the agency requesting an initial licensure survey because of a change of ownership? Mark Yes or No.
Is the hospice agency requesting an initial health survey because the physical address of the hospice inpatient unit changed?
Is the hospice agency requesting an initial health survey because the physical address of the hospice inpatient unit changed? Mark Yes or No.
The agency is requesting an initial survey for the following categories

The agency is requesting an initial survey for the following categories: Personal Assistance Services (PAS), Licensed Home Health Services (LHHS), LHHS with Dialysis, Hospice, Hospice with an Inpatient Unit.
By signature, the Authorized Representative acknowledges that the agency is ready for its initial survey. Enter the Date.
The home health services that the agency is providing, check all that apply

The home health services that the agency is providing, check all that apply: Skilled Nursing, Physical Therapy, Speech Therapy, Home Health Aide, Occupational Therapy, Medical Social Worker, Care Attendant.
The following information must be completed
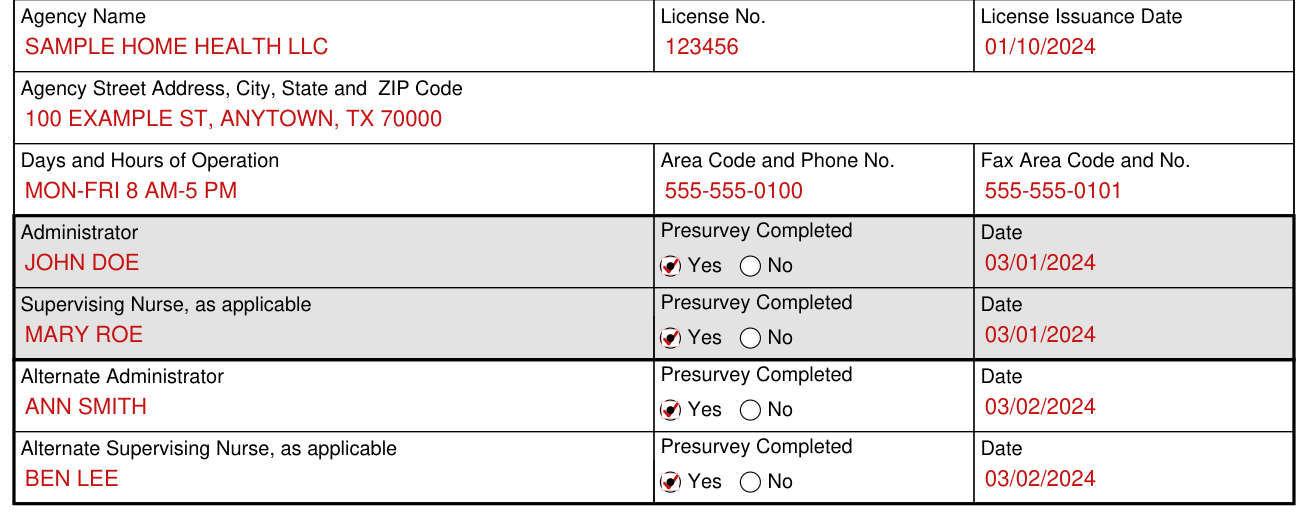
The following information must be completed: Agency Name, License No., License Issuance Date, Agency Street Address, City, State and ZIP Code, Days and Hours of Operation, Area Code and Phone No., Fax Area Code and No.
For the Administrator, the Supervising Nurse, as applicable, the Alternate Administrator and the Alternate Supervising Nurse, as applicable, mark Presurvey Completed Yes or No and enter the Date.
Patient Name, HIC No., ID No. or CR No.
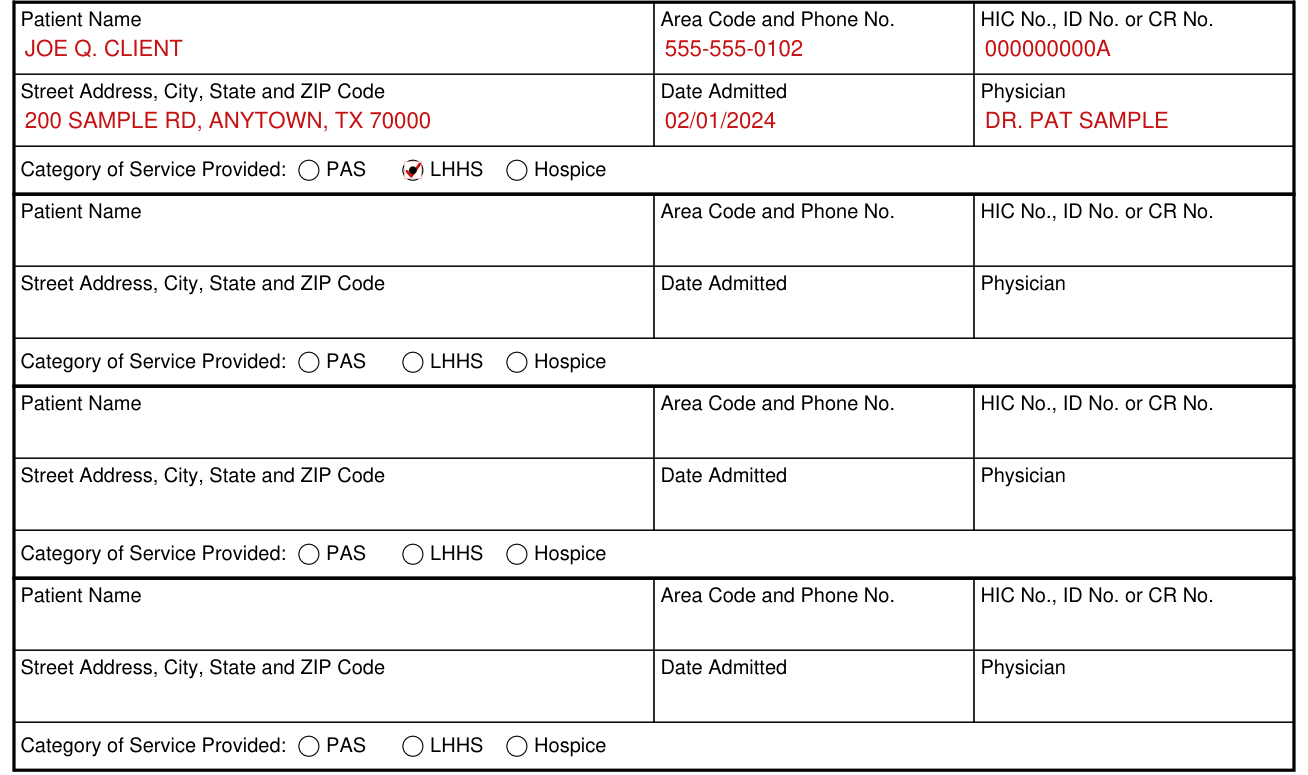
For each patient, enter Patient Name, Area Code and Phone No., HIC No., ID No. or CR No., Street Address, City, State and ZIP Code, Date Admitted and Physician, and mark the Category of Service Provided: PAS, LHHS or Hospice.
These abbreviations are used in this document: HIC No. - Health Insurance Claim Number; ID No. - Identification Number; CR No. - Clinical Record Number; and OASIS - Outcome Assessment Information Set.
Section 2 - An Agency's Request for an Initial Medicare Certification Survey
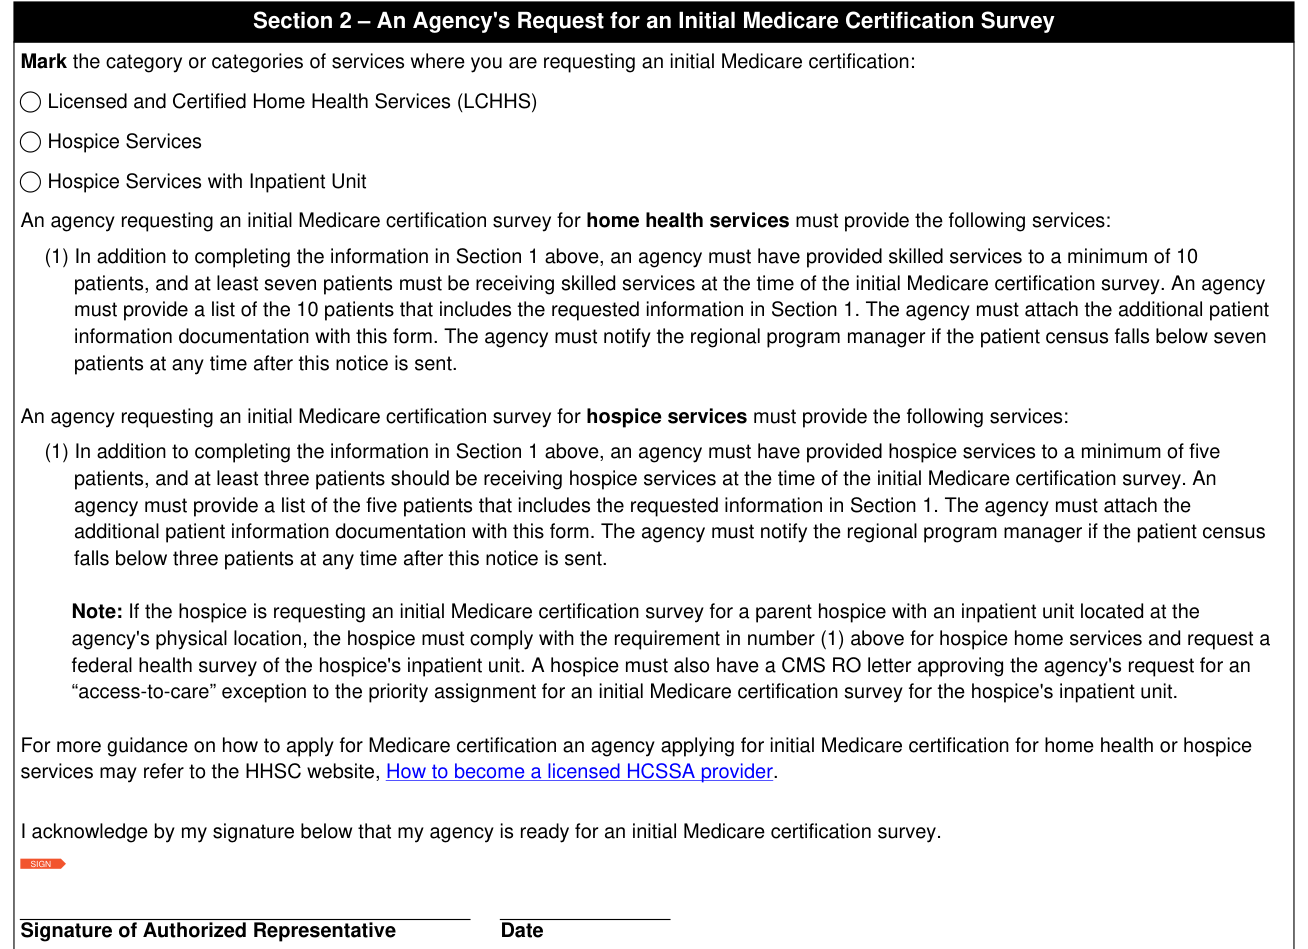
Mark the category or categories of services where you are requesting an initial Medicare certification: Licensed and Certified Home Health Services (LCHHS), Hospice Services or Hospice Services with Inpatient Unit.
An agency requesting an initial Medicare certification survey for home health services must provide the following services: In addition to completing the information in Section 1, an agency must have provided skilled services to a minimum of 10 patients, and at least seven patients must be receiving skilled services at the time of the initial Medicare certification survey.
An agency must provide a list of the 10 patients that includes the requested information in Section 1. The agency must attach the additional patient information documentation with this form.
"The agency must notify the regional program manager if the patient census falls below seven patients at any time after this notice is sent."
An agency requesting an initial Medicare certification survey for hospice services must provide the following services: In addition to completing the information in Section 1, an agency must have provided hospice services to a minimum of five patients, and at least three patients should be receiving hospice services at the time of the initial Medicare certification survey.
An agency must provide a list of the five patients that includes the requested information in Section 1.
"The agency must notify the regional program manager if the patient census falls below three patients at any time after this notice is sent."
If the hospice is requesting an initial Medicare certification survey for a parent hospice with an inpatient unit located at the agency's physical location, the hospice must comply with the requirement in number (1) for hospice home services and request a federal health survey of the hospice's inpatient unit. A hospice must also have a CMS RO letter approving the agency's request for an “access-to-care” exception to the priority assignment for an initial Medicare certification survey for the hospice's inpatient unit.
For more guidance on how to apply for Medicare certification an agency applying for initial Medicare certification for home health or hospice services may refer to the HHSC website, How to become a licensed HCSSA provider.
By signature, the Authorized Representative acknowledges that the agency is ready for an initial Medicare certification survey. Enter the Date.
More rules for Form 2020
Complete all information in each of the boxes, as appropriate.
Retain a copy of this form for your records.
To request an initial Medicare certification survey, proceed to Section 2.
After completing Section 1, this Notification of Readiness for Initial Survey form is complete.
An agency requesting an initial Medicare certification survey for home health or hospice services must apply with a Centers for Medicare & Medicaid Services (CMS)-approved national accrediting organization (AO) with deeming authority.
An agency must notify HHSC of the AO selection.
Mark the AO that will be conducting your agency's initial Medicare certification survey: JC, CHAP or ACHC.
Common questions about Form 2020
Where do I file it?
Submit the completed form to your Regional PM via mail, fax, email, or TULIP upload with the subject line or file name as “Form 2020”.
Sources
[1] Form 2020 (12-2023), Home and Community Support Services Agencies (HCSSA) Notification of Readiness for Initial Survey, Texas Health and Human Services Commission (the Official source link on this page).