

Form 3613-A at a glance
What it is: Form 3613-A is the Provider Investigation Report for SNF, NF, ICF/IID, ALF, DAHS and PPECC.
Where and when to file: Fax Cover Sheet, To: Complaint and Incident Intake, Area Code and Fax No.: 877-438-5827 (if 15 total pages or fewer).
For use by skilled nursing facilities (SNFs), nursing facilities (NFs), intermediate care facilities for individuals with an intellectual disability or related conditions (ICF/ IIDs), assisted living facilities (ALFs), day and activity health services facilities (DAHS) including Individualized Skills and Socialization (ISS) providers, and prescribed pediatric extended care centers (PPECCs) only.
What to bring and attach to Form 3613-A
Attach all documents and pertinent information for HHSC to complete the review of your investigation.
A filled-in Form 3613-A example: a missing resident
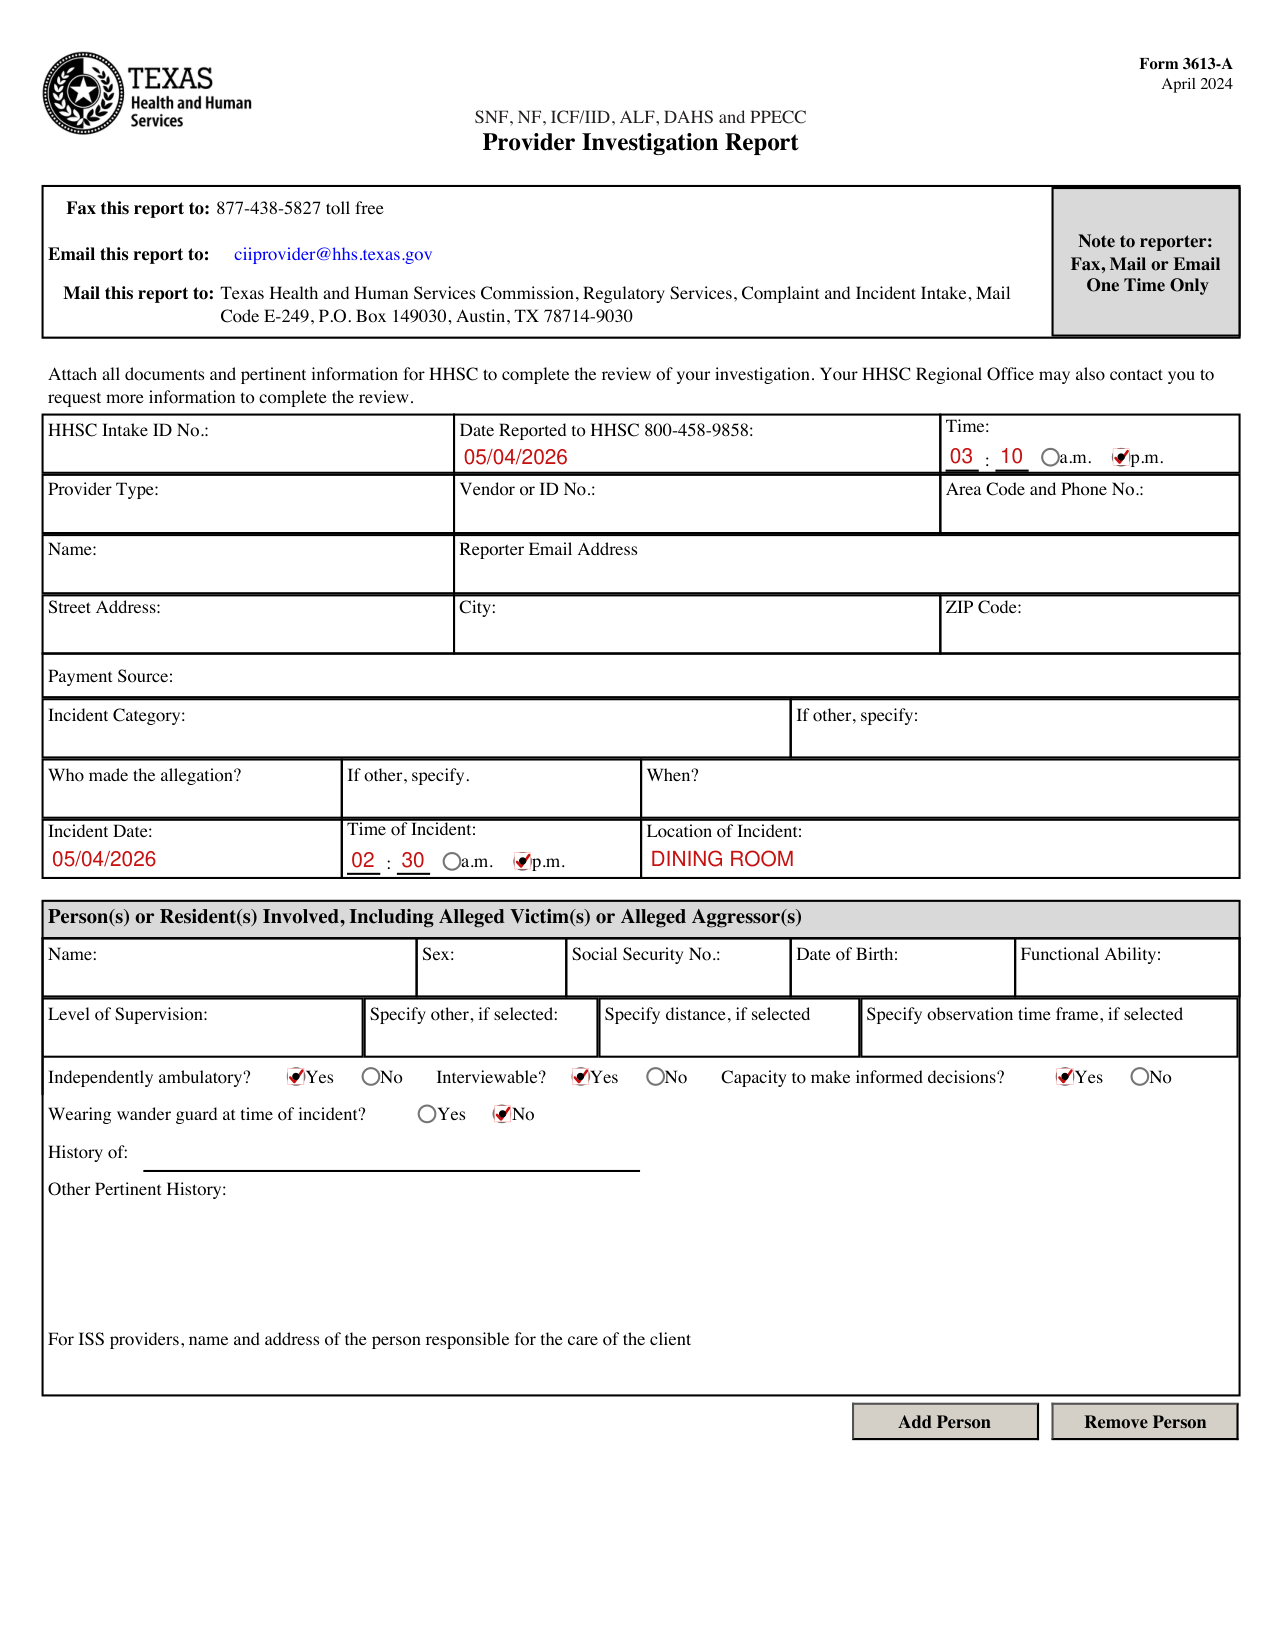
How to fill out Form 3613-A, box by box
Fax Cover Sheet

Fax Cover Sheet, To: Complaint and Incident Intake, Area Code and Fax No.: 877-438-5827 (if 15 total pages or fewer).
Enter the Intake ID No., the No. of Pages, including cover, the Provider Name and the Vendor or ID No.
HHSC Intake ID No., Date Reported to HHSC, Time and Provider Type

Enter the HHSC Intake ID No., the Date Reported to HHSC 800-458-9858 and the Time, a.m. or p.m.
Enter the Provider Type, Vendor or ID No., Area Code and Phone No., Name, Reporter Email Address, Street Address, City, ZIP Code and Payment Source.
Incident Category and Who made the allegation

Enter the Incident Category; If other, specify. Who made the allegation? If other, specify. When?
Incident Date, Time of Incident and Location of Incident

Enter the Incident Date, the Time of Incident, a.m. or p.m., and the Location of Incident.
Person(s) or Resident(s) Involved
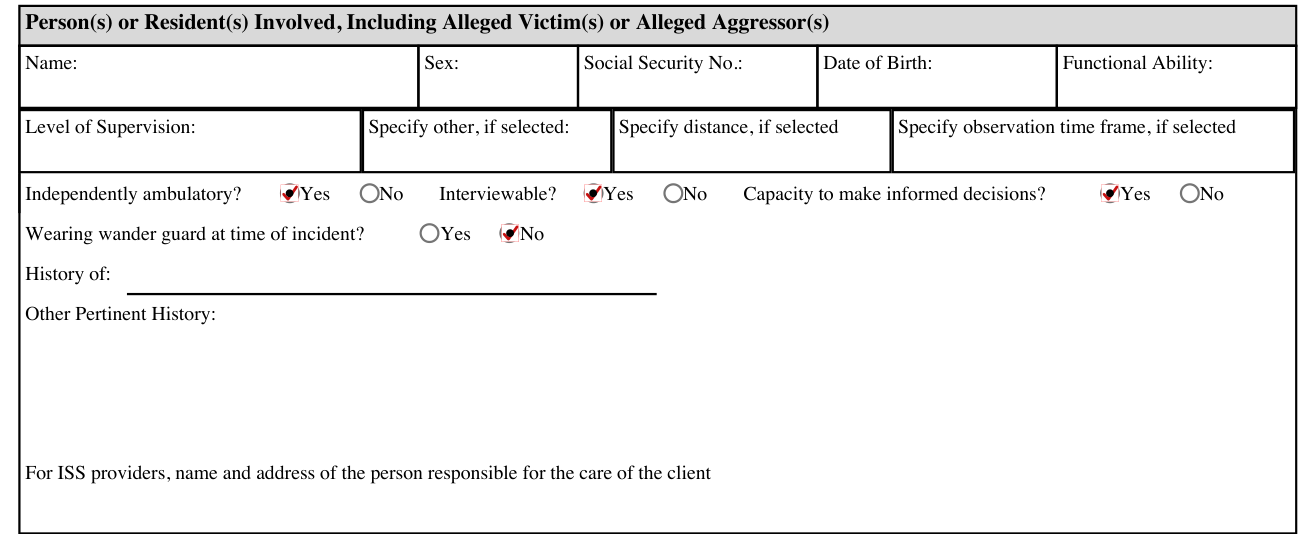
For each of the Person(s) or Resident(s) Involved, Including Alleged Victim(s) or Alleged Aggressor(s), enter Name, Sex, Social Security No., Date of Birth and Functional Ability.
Enter the Level of Supervision; Specify other, if selected; Specify distance, if selected; Specify observation time frame, if selected.
Independently ambulatory? Yes No Interviewable? Yes No Capacity to make informed decisions? Yes No Wearing wander guard at time of incident? Yes No
Enter the History of and the Other Pertinent History.
For ISS providers, name and address of the person responsible for the care of the client.
Alleged Perpetrator(s) (AP)
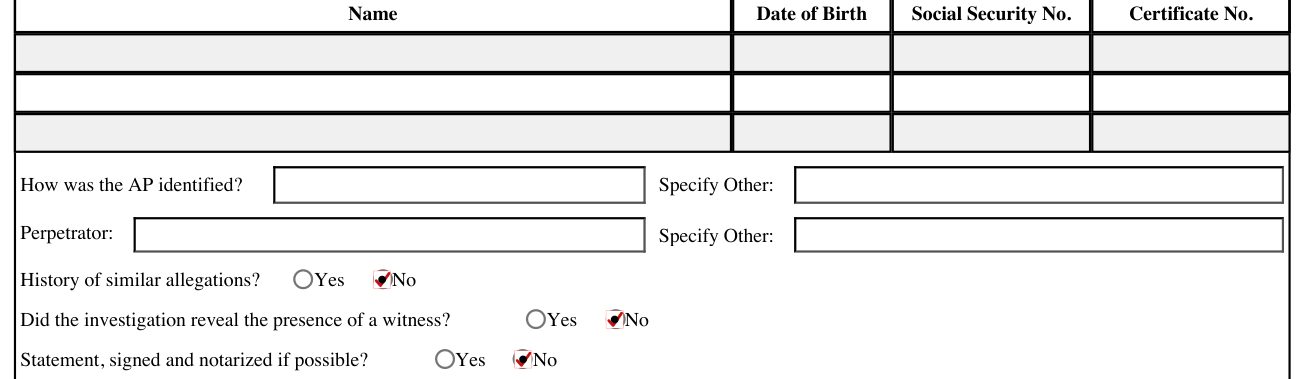
Under Alleged Perpetrator(s) (AP), enter Name, Date of Birth, Social Security No. and License or Certificate No.
If alleged perpetrator is somebody other than a staff member, indicate this person's relationship to the person. Example: relative, visitor.
How was the AP identified? Specify Other: Perpetrator: Specify Other: History of similar allegations? Yes No
Witness(es)
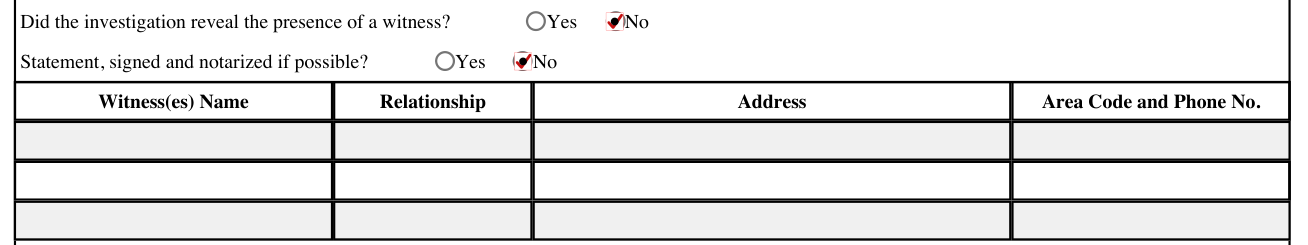
Did the investigation reveal the presence of a witness? Yes No Statement, signed and notarized if possible? Yes No
For each witness, enter Name, Relationship, Address and Area Code and Phone No.
Description of the Allegation

Enter the Description of the Allegation and At the time of the incident was the person receiving ISS services? Yes No NA
Assessment

Under Assessment, enter the Date and Time, a.m. or p.m.; Injury or Adverse effect? Yes No; enter the Treatment or Transfer Date and Time; and the Name and title of person who completed assessment.
Description of assessment including extent of injuries. Provide details of any physical harm, pain, or mental anguish including serious bodily injury, other injuries including but not limited to measurements, location, color of bruises, scratches, lacerations, fractures, changes in resident's behavior that differs from the normal baseline.
Treatment provided?

Treatment provided? Yes No Treatment location: In-House? Yes No Off-site Location: City: Was the incident reported to the police? Yes No If so, provide case number:
Provider Response and Investigation Summary
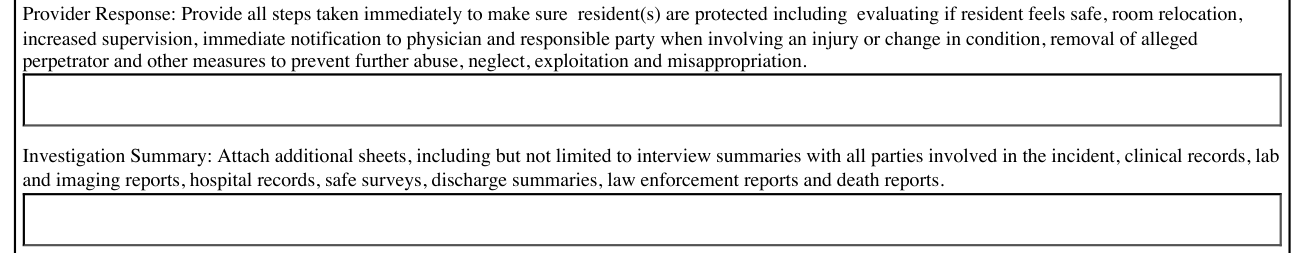
Provider Response: Provide all steps taken immediately to make sure resident(s) are protected including evaluating if resident feels safe, room relocation, increased supervision, immediate notification to physician and responsible party when involving an injury or change in condition, removal of alleged perpetrator and other measures to prevent further abuse, neglect, exploitation and misappropriation.
Investigation Summary: Attach additional sheets, including but not limited to interview summaries with all parties involved in the incident, clinical records, lab and imaging reports, hospital records, safe surveys, discharge summaries, law enforcement reports and death reports.
Were other parties notified? Facility Investigation Findings and SIGN
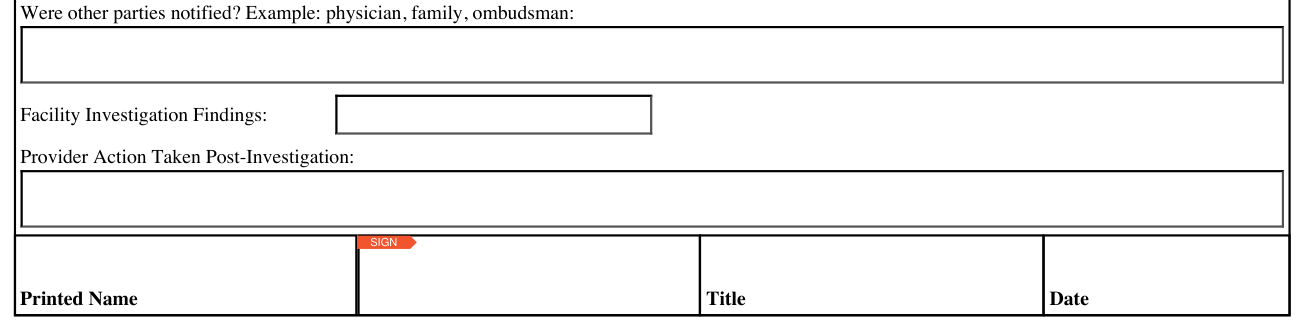
Enter Were other parties notified? Example: physician, family, ombudsman:, the Facility Investigation Findings and the Provider Action Taken Post-Investigation.
SIGN and enter Printed Name, Title and Date.
Common questions about Form 3613-A
Where do I file it?
Fax this report to: 877-438-5827 toll free. Email this report to: ciiprovider@hhs.texas.gov. Mail this report to: Texas Health and Human Services Commission, Regulatory Services, Complaint and Incident Intake, Mail Code E-249, P.O. Box 149030, Austin, TX 78714-9030. Note to reporter: Fax, Mail or Email One Time Only.
Where to get help with Form 3613-A
Your HHSC Regional Office may also contact you to request more information to complete the review.
Sources
[1] Form 3613-A (April 2024), Texas Health and Human Services Commission (the Official source link on this page).
