
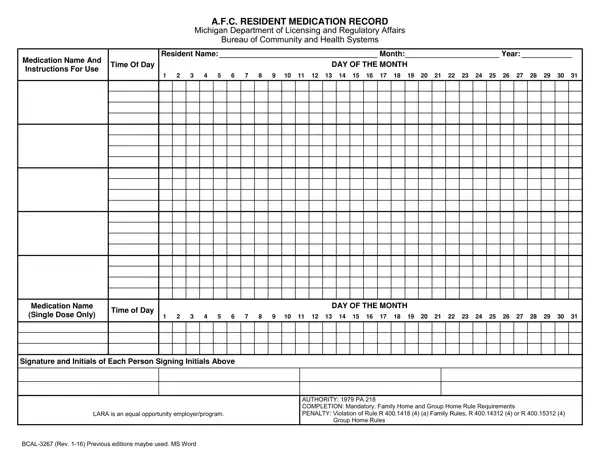
How to Fill Out BCHS-3267

BCHS-3267 at a glance

What it is: This is the A.F.C. Resident Medication Record of the Michigan Department of Licensing and Regulatory Affairs, Bureau of Community and Health Systems.

Who signs: Each Person Signing Initials enters a Signature and Initials.

A filled-in BCHS-3267 example: one morning medication for March 2026
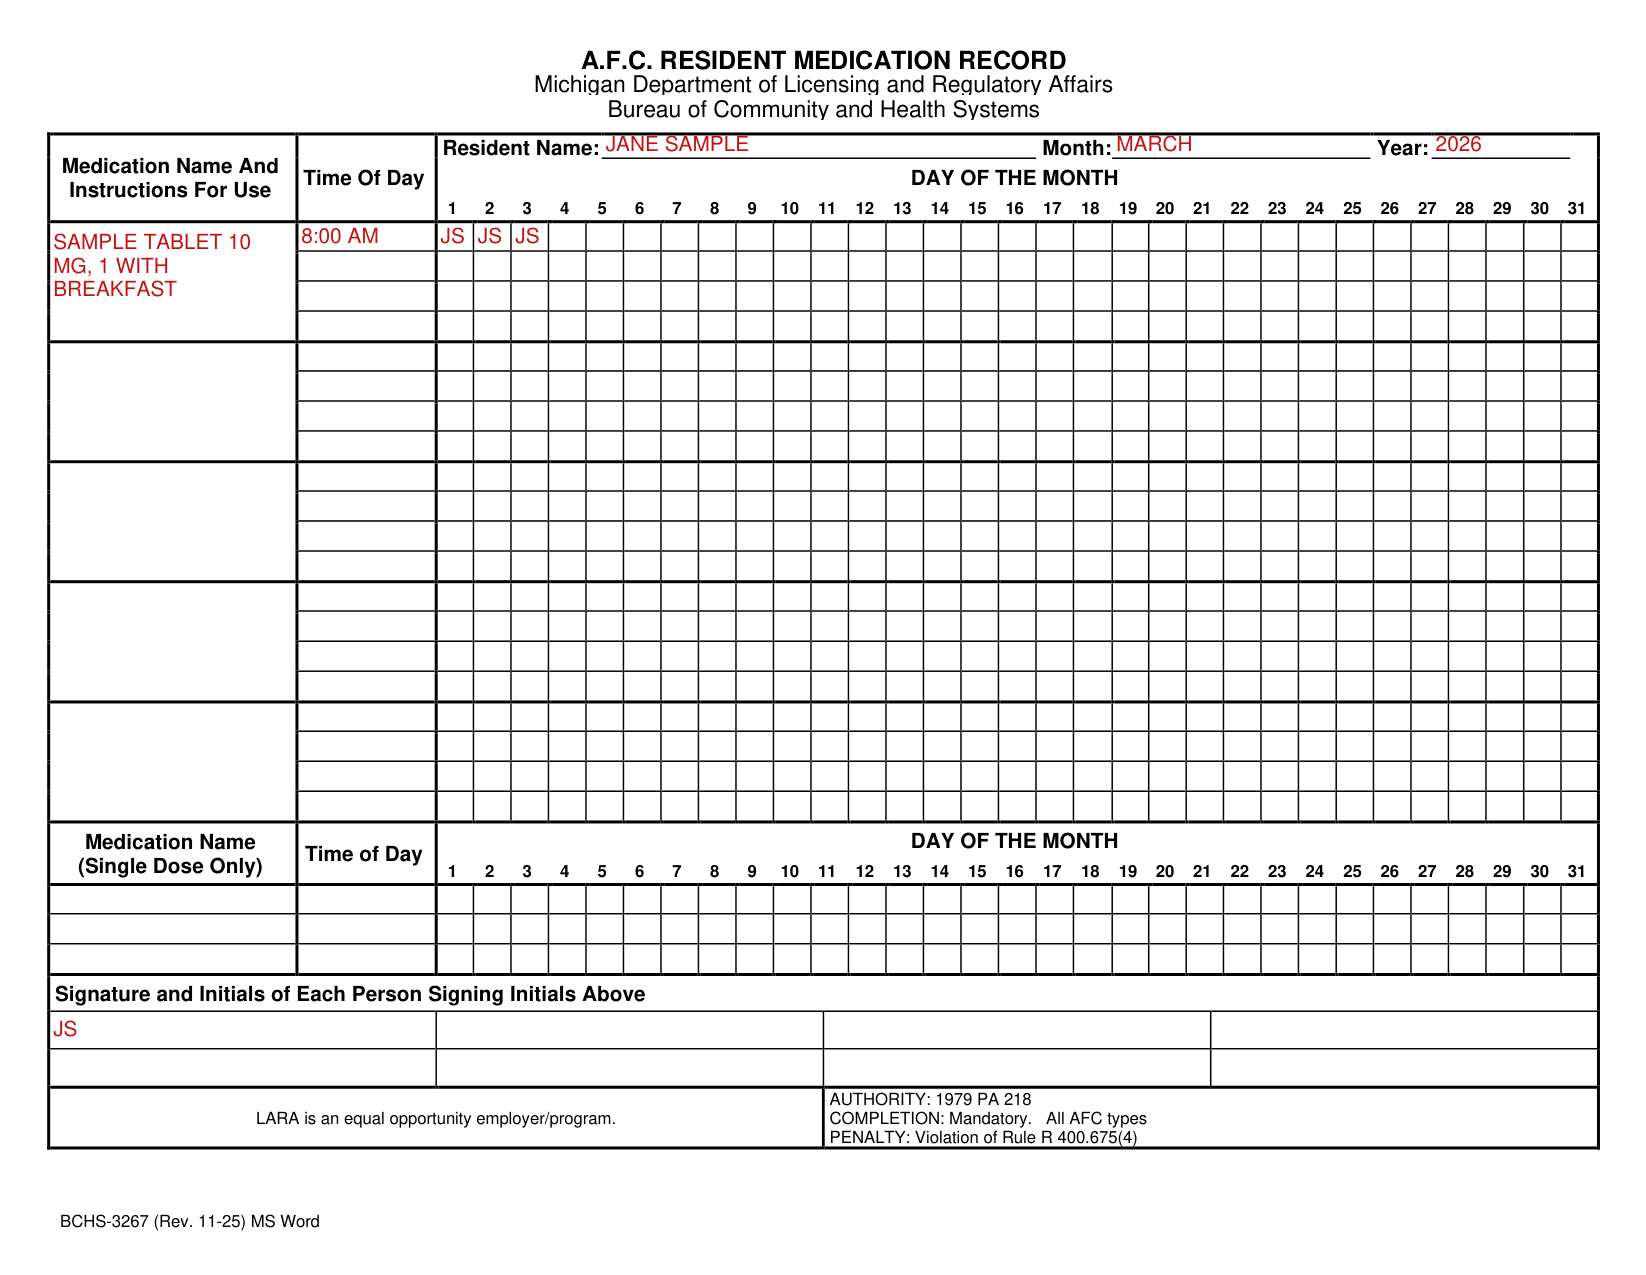
BCHS-3267 example filled out, example: one morning medication for March 2026
A staff member fills out the BCHS-3267 A.F.C. Resident Medication Record. One medication is given each morning, and initials are entered for the first three days. The picture shows March 2026, and none of its entries is real. The initials JS belong to the person who gave the medication. Nothing goes in Medication Name (Single Dose Only) because no single dose is given.

How to fill out BCHS-3267, box by box

Resident Name, Month and Year

BCHS-3267 example filled out, resident Name, Month and Year

Enter the Resident Name, the Month and the Year.

Medication Name And Instructions For Use
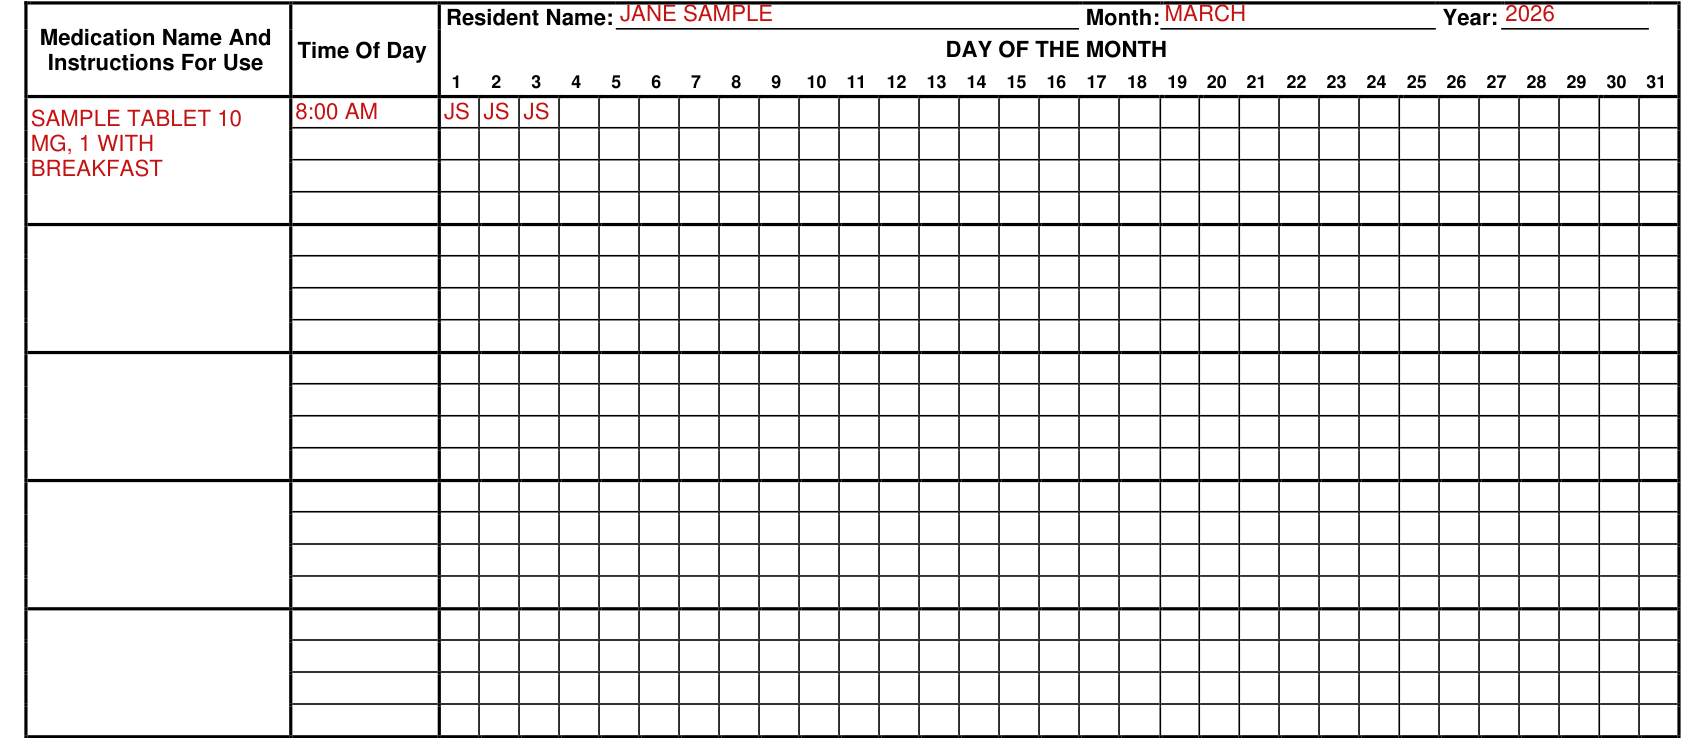
BCHS-3267 example filled out, medication Name And Instructions For Use

Under Medication Name And Instructions For Use, write each medication and its instructions, and enter its Time Of Day.

Medication Name (Single Dose Only)

BCHS-3267 example filled out, medication Name (Single Dose Only)

Under Medication Name (Single Dose Only), write each single dose medication and enter its Time of Day.

Signature and Initials of Each Person Signing Initials Above
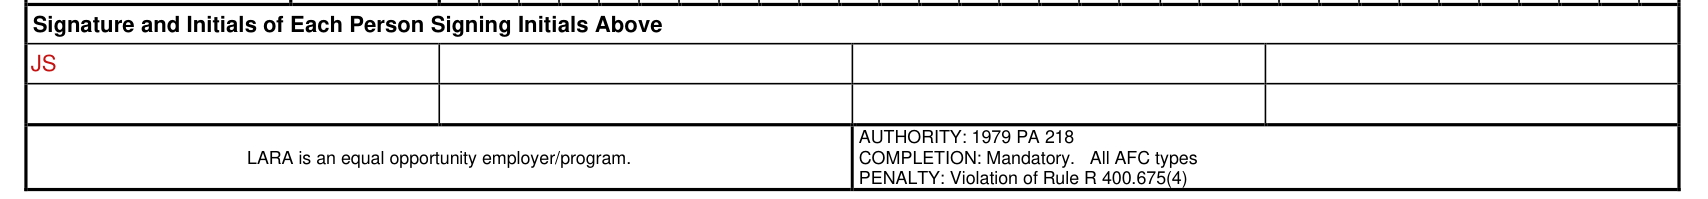
BCHS-3267 example filled out, signature and Initials of Each Person Signing Initials Above

Each Person Signing Initials enters a Signature and Initials.

Common questions about BCHS-3267

Is there a penalty?

Completion is mandatory for all AFC types; the penalty is for violation of Rule R 400.675(4).

Sources

[1] BCHS-3267 (Rev. 11-25), A.F.C. Resident Medication Record, Michigan Department of Licensing and Regulatory Affairs (the Official source link on this page).

BCHS-3267 PDF Details

Resident Name, Month, Year and Day of the month.

Medication: Medication Name And Instructions For Use, with the Time Of Day.

Signatures: Signature and Initials of Each Person Signing.

Completion: Mandatory.

Authority: 1979 PA 218.

QuestionAnswer
Form NameBCHS-3267
Form Length1 page
Fillable?Yes
Fillable fields756
Avg. time to fill out60+ min
EditionRev 11-25
Issuing agencyMichigan Department of Licensing and Regulatory Affairs
Other namesBCHS-3267, BCHS 3267, 3267, A.F.C. Resident Medication Record, AFC Resident Medication Record
Official sourceBCHS-3267 (Rev 11-25), Michigan Department of Licensing and Regulatory Affairs