

Form C-4 at a glance
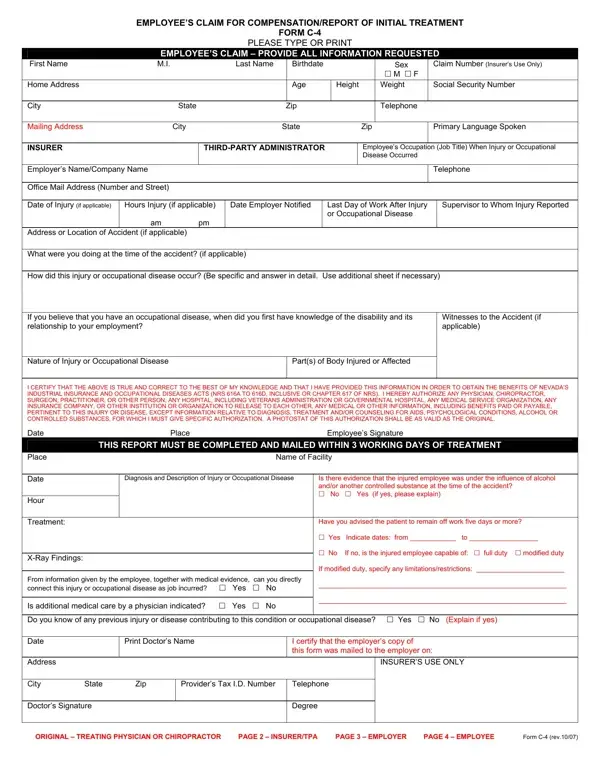
What it is: Form C-4 is the Employee's Claim for Compensation/Report of Initial Treatment.
Who signs: The employee signs on the Employee's Original or Electronic Signature line, and the health care provider signs on the Health Care Provider's Original or Electronic Signature line.
Where and when to file: This report must be completed and mailed within 3 working days of treatment.
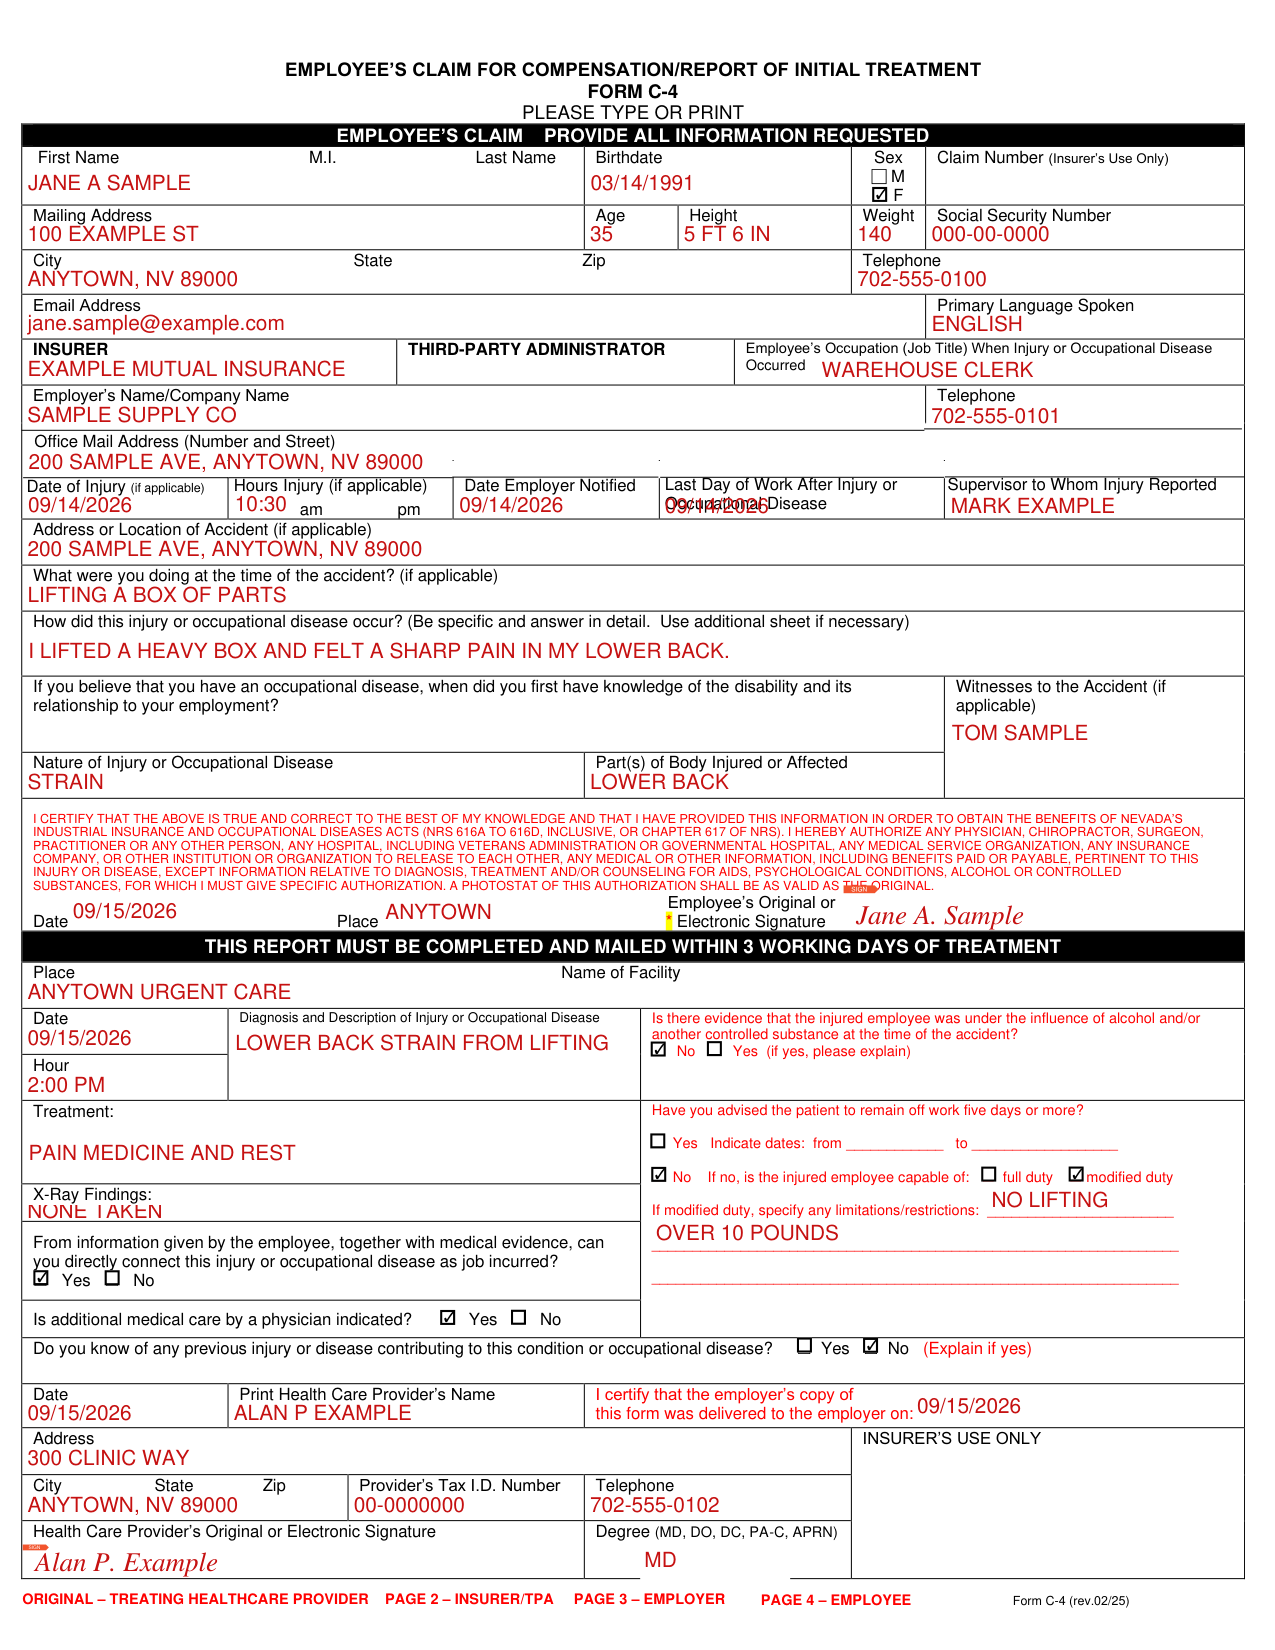
A filled-in Form C-4 example: an employee and her doctor complete Form C-4
How to fill out Form C-4, box by box
Name, Birthdate, Sex and Claim Number

Enter the First Name, M.I. and Last Name, and the Birthdate.
Check M or F under Sex.
The Claim Number is for the Insurer's Use Only.
Mailing Address, Telephone and Email Address

Enter the Mailing Address, Age, Height, Weight and Social Security Number.
Fill in the City, State, Zip and Telephone.
Write the Email Address and the Primary Language Spoken.
Insurer, Occupation and Employer
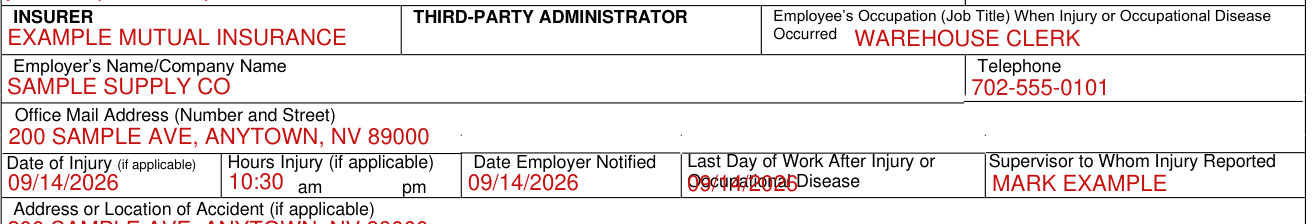
Use the Insurer box and the Third-Party Administrator box.
Enter the Employee's Occupation (Job Title) When Injury or Occupational Disease Occurred.
Write the Employer's Name/Company Name and Telephone.
Write the Office Mail Address (Number and Street).
Date of Injury, Hours Injury and Supervisor to Whom Injury Reported

Enter the Date of Injury (if applicable) and the Hours Injury (if applicable), in the am or pm box.
Enter the Date Employer Notified and the Last Day of Work After Injury or Occupational Disease.
Write the Supervisor to Whom Injury Reported.
Accident, Injury or Occupational Disease and Witnesses
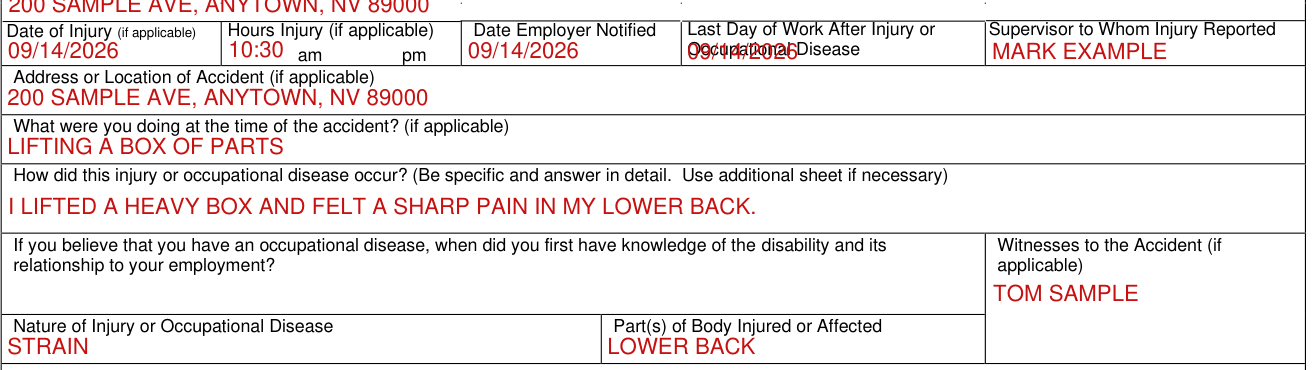
Write the Address or Location of Accident (if applicable) and what you were doing at the time of the accident (if applicable).
Answer in detail: How did this injury or occupational disease occur? Be specific, and use an additional sheet if necessary.
If you believe that you have an occupational disease, enter when you first had knowledge of the disability and its relationship to your employment.
List the Witnesses to the Accident (if applicable).
Enter the Nature of Injury or Occupational Disease and the Part(s) of Body Injured or Affected.
Certification and Employee's signature

Signing certifies that the information entered on page 1 is true and correct to the best of your knowledge, and that you have provided this information in order to obtain the benefits of Nevada's industrial insurance and occupational diseases Acts (NRS 616A to 616D, inclusive, or Chapter 617 of NRS).
Signing authorizes any physician, chiropractor, surgeon, practitioner or any other person, any hospital, including Veterans Administration or governmental hospital, any medical service organization, any insurance company, or other institution or organization to release to each other any medical or other information, including benefits paid or payable, pertinent to this injury or disease, except information relative to diagnosis, treatment and/or counseling for AIDS, psychological conditions, alcohol or controlled substances, for which you must give specific authorization.
A photostat of the authorization is as valid as the original.
Sign on the Employee's Original or Electronic Signature line, and enter the Date and the Place.
Place Name of Facility, Diagnosis and alcohol or controlled substance

Write the Place and the Name of Facility.
Enter the Date and the Hour, and the Diagnosis and Description of Injury or Occupational Disease.
Check No or Yes: Is there evidence that the injured employee was under the influence of alcohol and/or another controlled substance at the time of the accident? If yes, please explain.
Treatment

Write the Treatment.
Check Yes and indicate dates from and to if you have advised the patient to remain off work five days or more.
If No, check the duty the injured employee is capable of: full duty or modified duty.
If modified duty, specify any limitations/restrictions.
Enter the X-Ray Findings.
Job incurred, additional medical care and previous injury
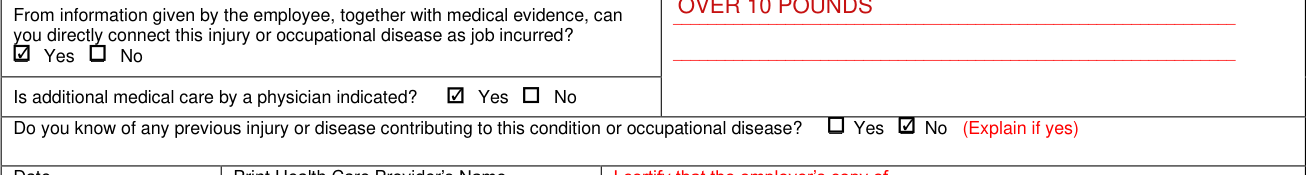
Check Yes or No: From information given by the employee, together with medical evidence, can you directly connect this injury or occupational disease as job incurred?
Check Yes or No: Is additional medical care by a physician indicated?
Check Yes or No: Do you know of any previous injury or disease contributing to this condition or occupational disease? Explain if yes.
Health Care Provider's name, address and signature

Enter the Date and print the Health Care Provider's Name.
Certify that the employer's copy of this form was delivered to the employer by entering the date it was delivered.
Fill in the Address. The Insurer's Use Only box is for the insurer.
Write the City, State, Zip, Provider's Tax I.D. Number and Telephone.
Sign on the Health Care Provider's Original or Electronic Signature line, and choose the Degree (MD, DO, DC, PA-C, APRN) if applicable.
Before you go
Type or print the employee's claim and provide all information requested.
Common questions about Form C-4
What is a C4 form?
Form C-4 is the Employee's Claim for Compensation/Report of Initial Treatment. The form marks the Original for the treating healthcare provider, page 2 for the insurer/TPA, page 3 for the employer and page 4 for the employee.
Is there a deadline?
This report must be completed and mailed within 3 working days of treatment.
Sources
[1] Form C-4 (rev.02/25), Employee's Claim for Compensation/Report of Initial Treatment, dir.nv.gov (the Official source link on this page).