

Form CDPH 183 at a glance
What it is: HHA Training Programs must use this form to submit student data to the Aide and Technician Certification Section (ATCS) for certification UPON COMPLETION of the HHA Training Program.
Who signs: The Registered Nurse (RN) responsible for the HHA training program signs the form.
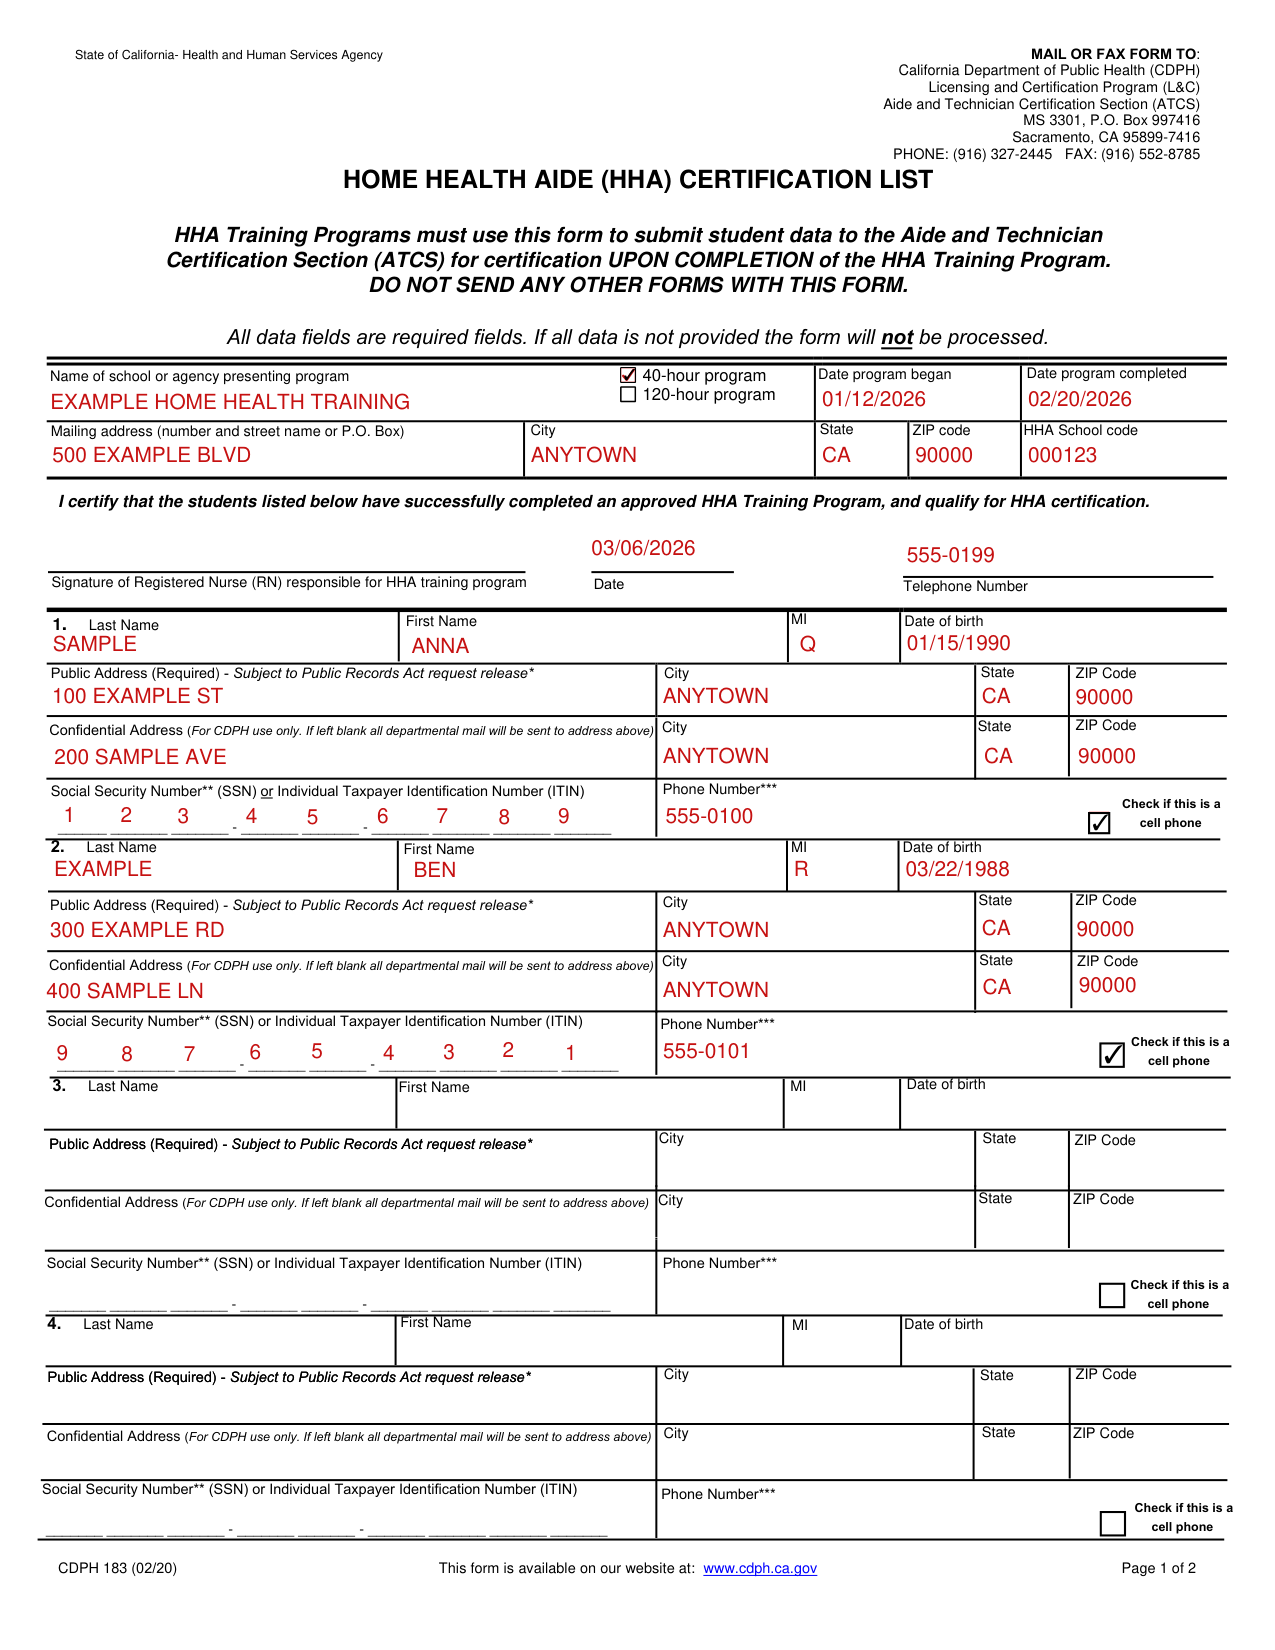
A filled-in Form CDPH 183 example: a nurse certifies two graduates
How to fill out Form CDPH 183, box by box
School or agency, program and dates

Enter the Name of school or agency presenting program.
Mark the 40-hour program or the 120-hour program.
Enter the Date program began and the Date program completed.
Mailing address and HHA school code

Enter the Mailing address (number and street name or P.O. Box), City, State, ZIP code and HHA School code.
Certification by the Registered Nurse (RN)

By signing, you certify that the students listed have successfully completed an approved HHA Training Program, and qualify for HHA certification.
The Registered Nurse (RN) responsible for the HHA training program signs, then enters the Date of Signature and Telephone Number.
Last Name, First Name, MI and Date of birth

Enter the Last Name, First Name, MI and Date of birth.
Public Address and Confidential Address

Public Address (Required) - Subject to Public Records Act request release. Confidential Address (For CDPH use only. If left blank all departmental mail will be sent to the Public Address). Enter the City, State and ZIP Code for each.
Effective May 22, 2018, the California Department of Public Health will be required under a court order to release the address of record for certified nurse assistants, home health aides, certified hemodialysis technicians, and licensed nursing home administrators in response to a Public Records Act (PRA) request. Court Order: Service Employee International Union-United Healthcare Workers v. California Department of Public Health, Sacramento County Superior Court, February 21, 2018, No. 34-2017-80002636.
Social Security Number (SSN) or ITIN and Phone Number

Enter the Social Security Number (SSN) or Individual Taxpayer Identification Number (ITIN) and the Phone Number.
Check if this is a cell phone.
If you use an invalid SSN, your application process may be delayed. Providing your telephone number and email address is for the California Department of Public Health's internal use only for contacting applicants. This information will not be released to the public nor will it be displayed online.
More rules for Form CDPH 183
Do not send any other forms with this form.
All data fields are required fields. If all data is not provided the form will not be processed.
Common questions about Form CDPH 183
Where do I file it?
MAIL OR FAX FORM TO: California Department of Public Health (CDPH) Licensing and Certification Program (L&C) Aide and Technician Certification Section (ATCS) MS 3301, P.O. Box 997416 Sacramento, CA 95899-7416 PHONE: (916) 327-2445 FAX: (916) 552-8785
Sources
[1] Form CDPH 183 (02/20), Home Health Aide (HHA) Certification List, California Department of Public Health (the Official source link on this page).
