

Form CF-ES 2282 at a glance
What it is: The Medicaid/Medicare Buy-In Application, CF-ES 2282.
Who signs: Sign and date as Applicant; the Spouse and the Designated Representative sign and date only if there is one.
A filled-in Form CF-ES 2282 example: an applicant with no spouse fills out page 1
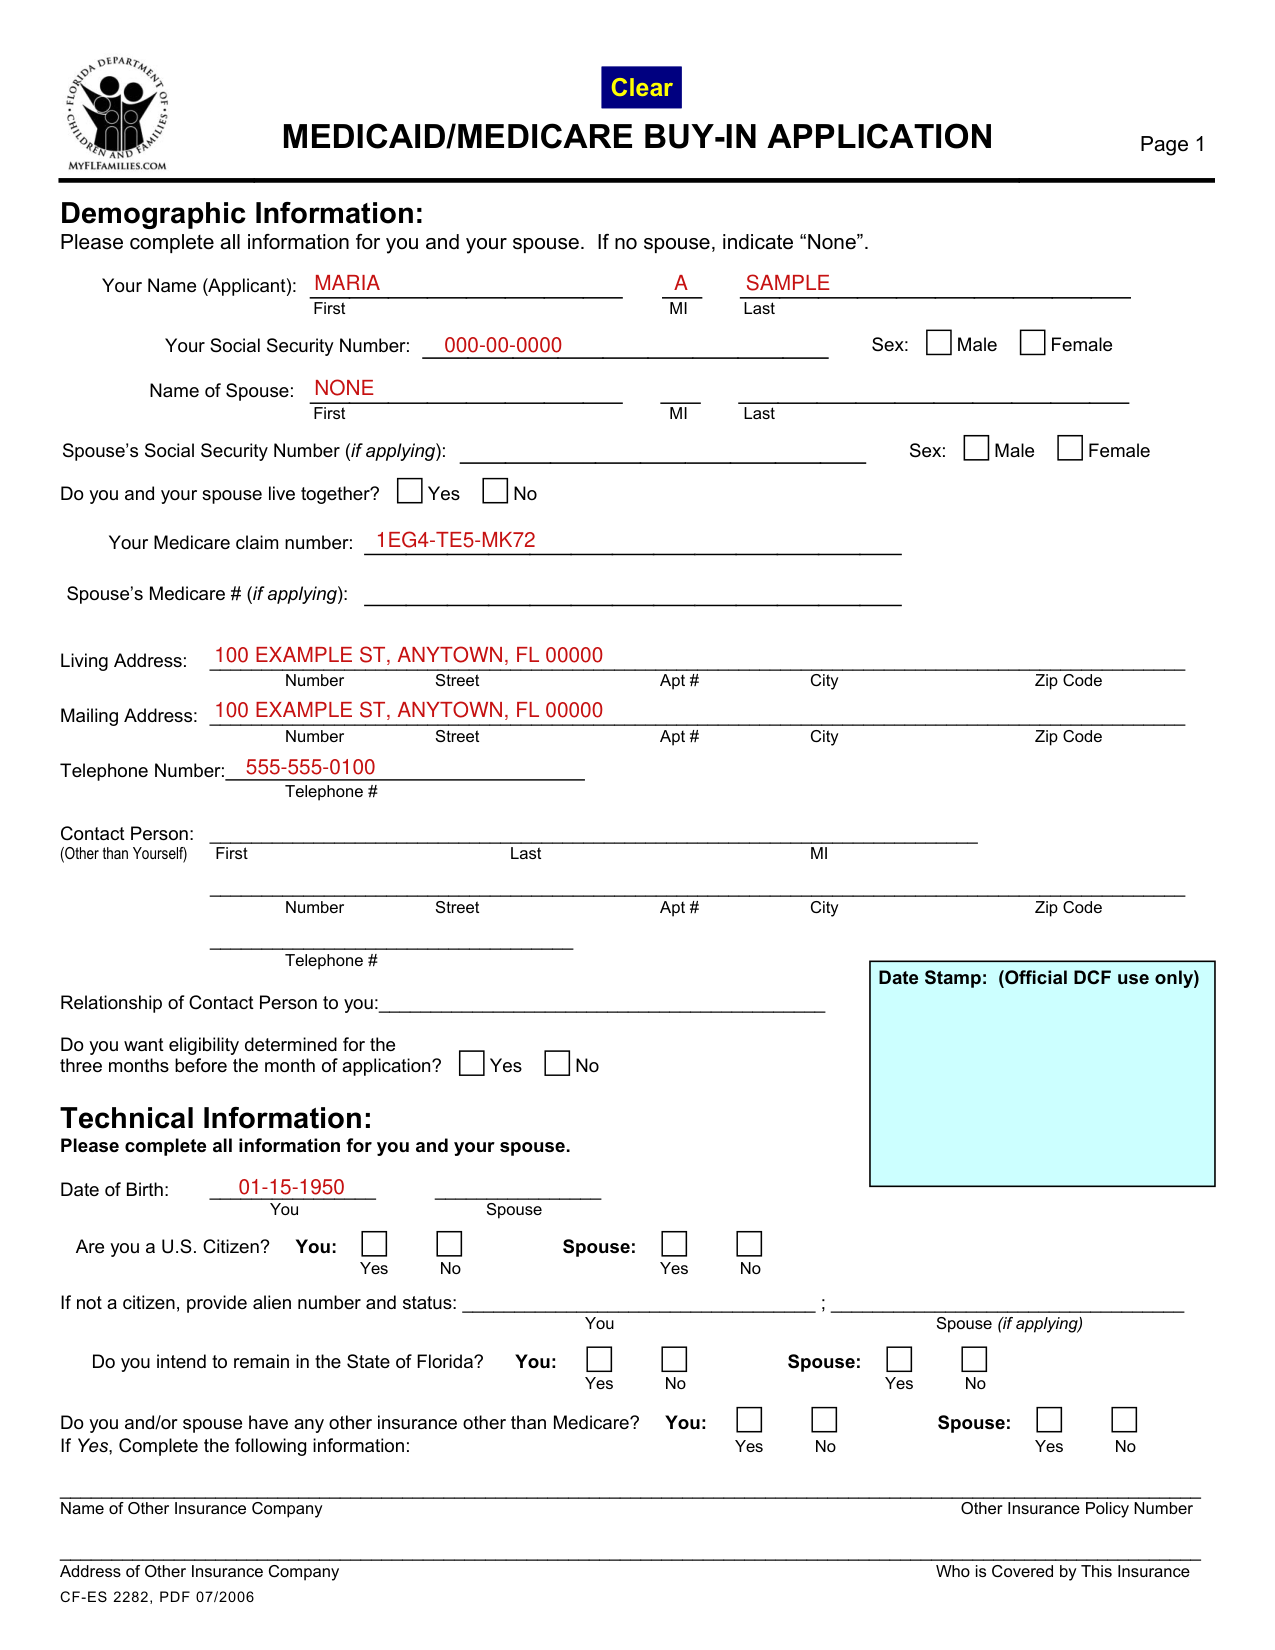
How to fill out Form CF-ES 2282, box by box
Your name, your spouse and Medicare claim numbers
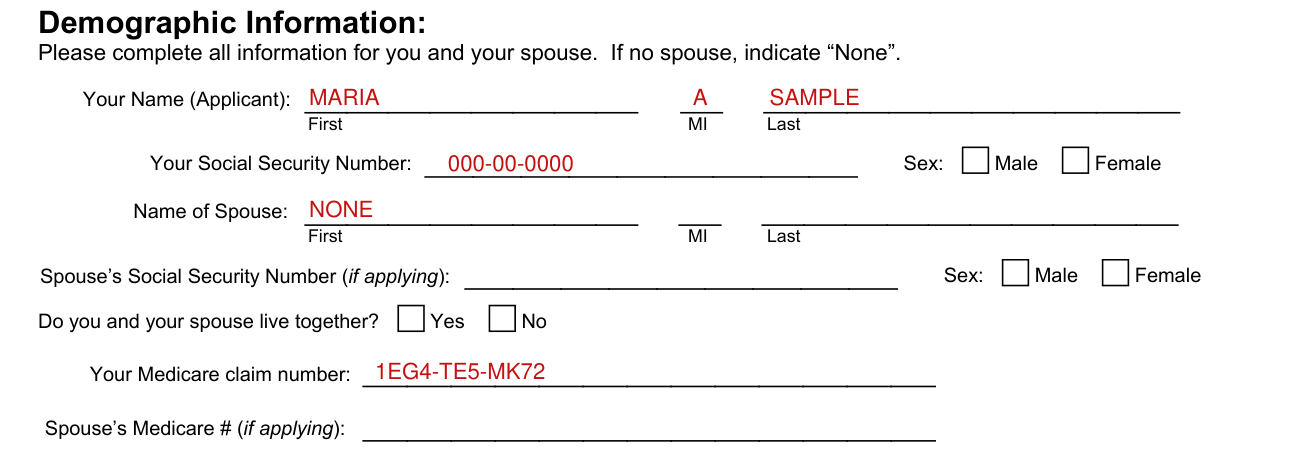
Complete all information for you and your spouse. If no spouse, indicate “None”.
Enter Your Name (Applicant) as First, MI and Last, and Your Social Security Number. Mark Male or Female for Sex.
Enter the Name of Spouse as First, MI and Last, and the Spouse's Social Security Number (if applying). Mark Male or Female for Sex.
Do you and your spouse live together? Yes or No.
Enter Your Medicare claim number and the Spouse's Medicare # (if applying).
Addresses, telephone numbers and contact person
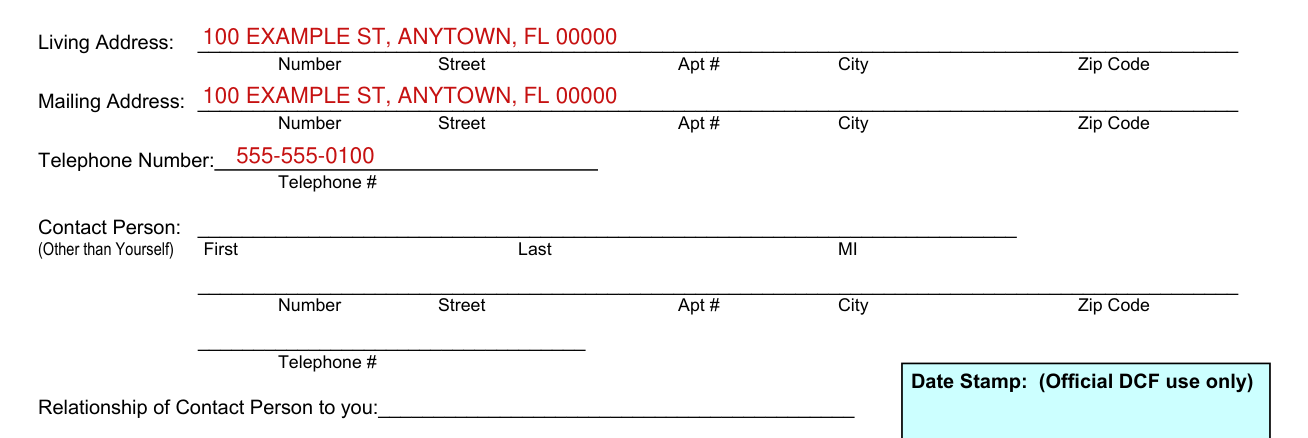
Enter the Living Address and the Mailing Address, each as Number, Street, Apt #, City and Zip Code.
Enter your Telephone Number, and a Contact Person (Other than Yourself) as First, Last and MI, with a Telephone #.
If there is a Contact Person, enter the Relationship of Contact Person to you.
Date of birth and eligibility for the three months before

Do you want eligibility determined for the three months before the month of application? Yes or No.
Enter the Date of Birth for You and Spouse.
Citizenship, Florida and other insurance

Are you a U.S. Citizen? Yes or No, for You and Spouse. If not a citizen, provide alien number and status.
Do you intend to remain in the State of Florida? Yes or No, for You and Spouse.
Do you and/or spouse have any other insurance other than Medicare? Yes or No, for You and Spouse. If Yes, Complete the following information:
Name of Other Insurance Company, Other Insurance Policy Number, Address of Other Insurance Company and Who is Covered by This Insurance.
Asset Information
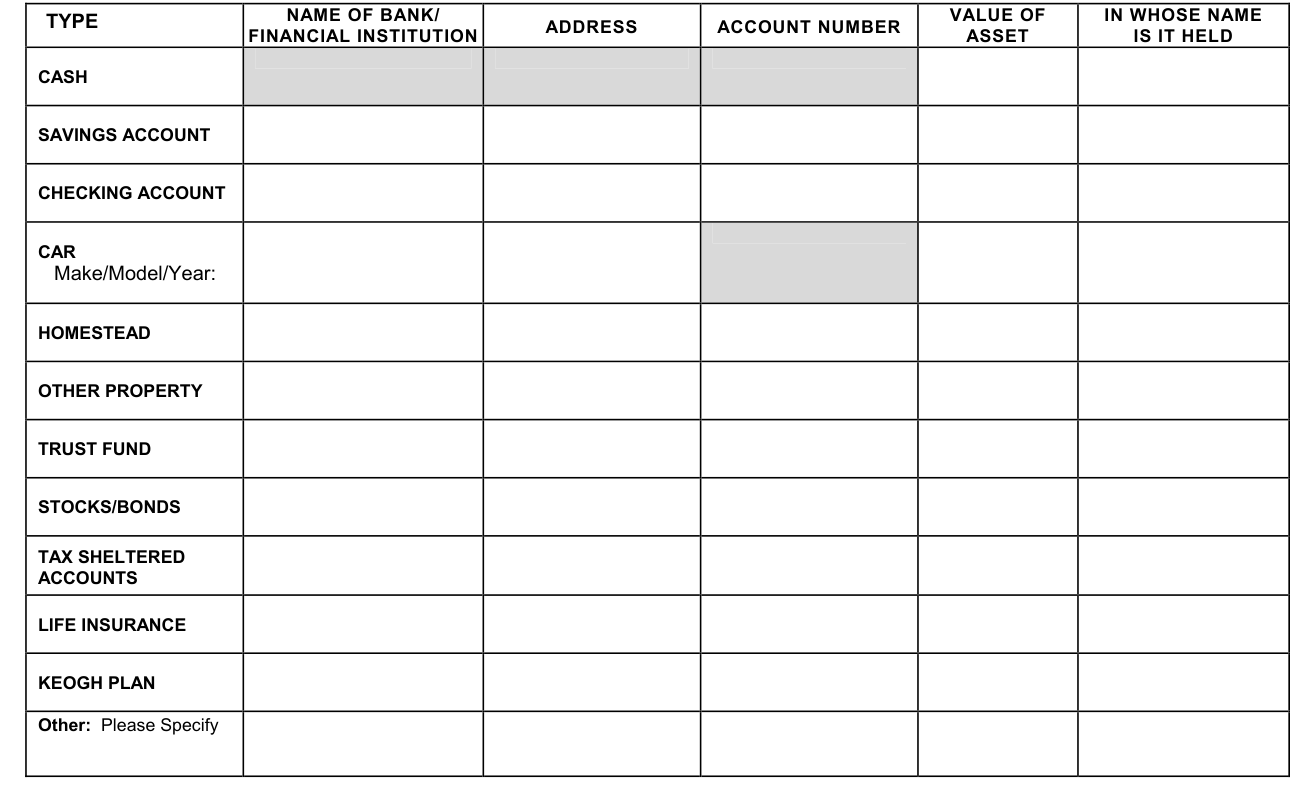
Page 2, Asset Information: Please list all assets owned by you and/or spouse (even if your spouse is not applying).
Type, Name of Bank/ Financial Institution, Address, Account Number, Value of Asset and In Whose Name Is It Held.
Income Information
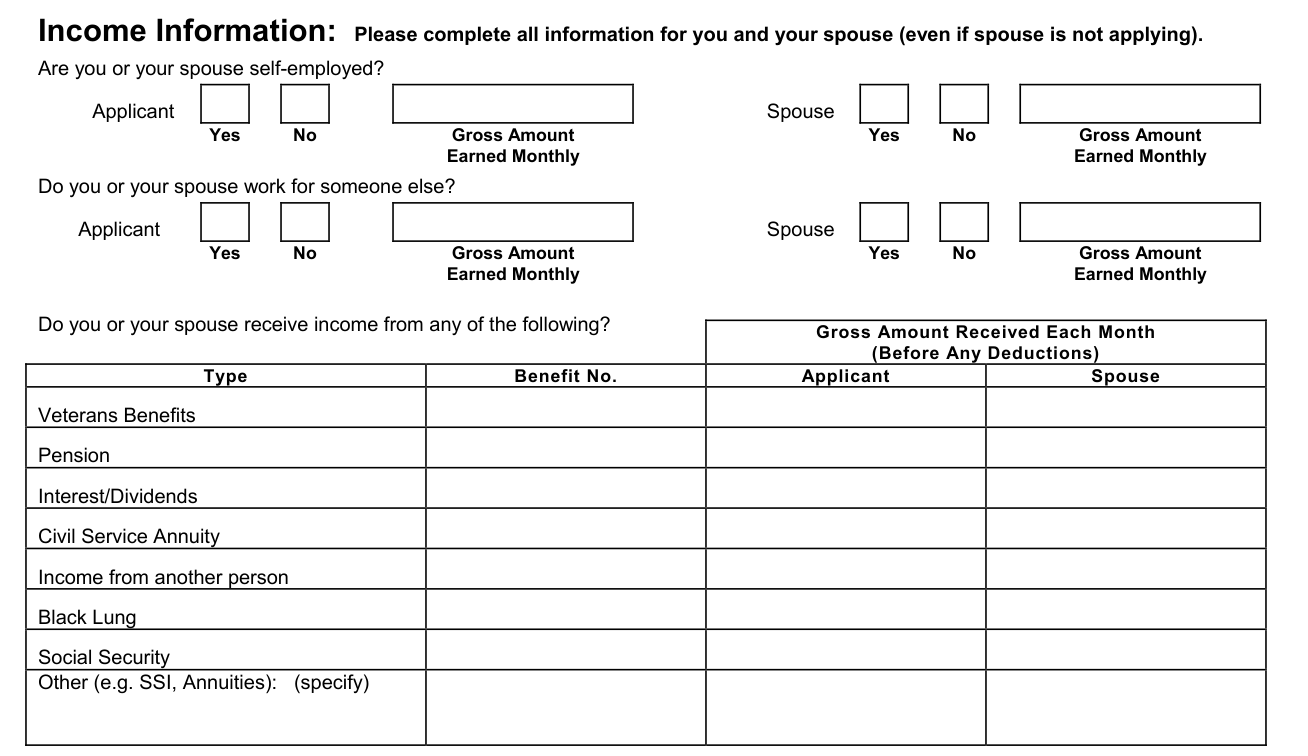
Income Information: Please complete all information for you and your spouse (even if spouse is not applying).
Are you or your spouse self-employed? Yes or No, for the Applicant and the Spouse.
Do you or your spouse work for someone else? Yes or No, for the Applicant and the Spouse, with the Gross Amount Earned Monthly.
Do you or your spouse receive income from any of the following? Enter the Gross Amount Received Each Month (Before Any Deductions) for the Applicant and the Spouse.
Veterans Benefits, Pension, Interest/Dividends, Civil Service Annuity, Income from another person, Black Lung, Social Security, Other (e.g. SSI, Annuities): (specify).
Signing your rights and responsibilities page

Page 3, YOUR RIGHTS AND RESPONSIBILITIES: Read this sheet before you sign your name.
“In signing this application, I swear and affirm, under penalty of perjury, that the information I have given on this application is correct and complete to the best of my knowledge.”
Sign and date as Applicant; the Spouse and the Designated Representative sign and date only if there is one.
More rules for Form CF-ES 2282
Assist in determining your eligibility by giving complete and correct information and provide written proof of information, as requested, within the time limits given.
Declare the citizenship or alien status for you and your spouse by signing the Medicaid/Medicare Buy-In Application.
Report your (and your spouse's, if applying) Social Security numbers.
If you get medical assistance for which you do not qualify, you may have to repay the cash value of that assistance.
Common questions about Form CF-ES 2282
Is there a deadline?
Report changes in your situation (e.g., income, assets) within 10 days of the change.
Is there a penalty?
Any person (including the designated representative) who knowingly withholds information or knowingly misrepresents the truth may be punished under federal or state law or both.
What am I certifying when I sign?
“Certification of Citizenship/Alien Status: I certify, under the penalty of perjury, by signing my name on this application, that I and my spouse (if applicable) are U.S. citizens or nationals of the United States or qualified aliens.”
Sources
[1] Form CF-ES 2282 (07/2006), Medicaid/Medicare Buy-In Application, Florida Department of Children and Families (the Official source link on this page).
