

Form CNP-925 at a glance
What it is: Form CNP - 925 is the Medical Statement to Request Special Meals and/or Accommodations.
Who signs: For box 13, Signature of Registered Dietitian (RD) or State Licensed Healthcare Professional: RDs are now permitted to complete and sign a written medical statement for school meal modifications due to a disability.
A filled-in Form CNP-925 example: a dietitian asks for chopped food
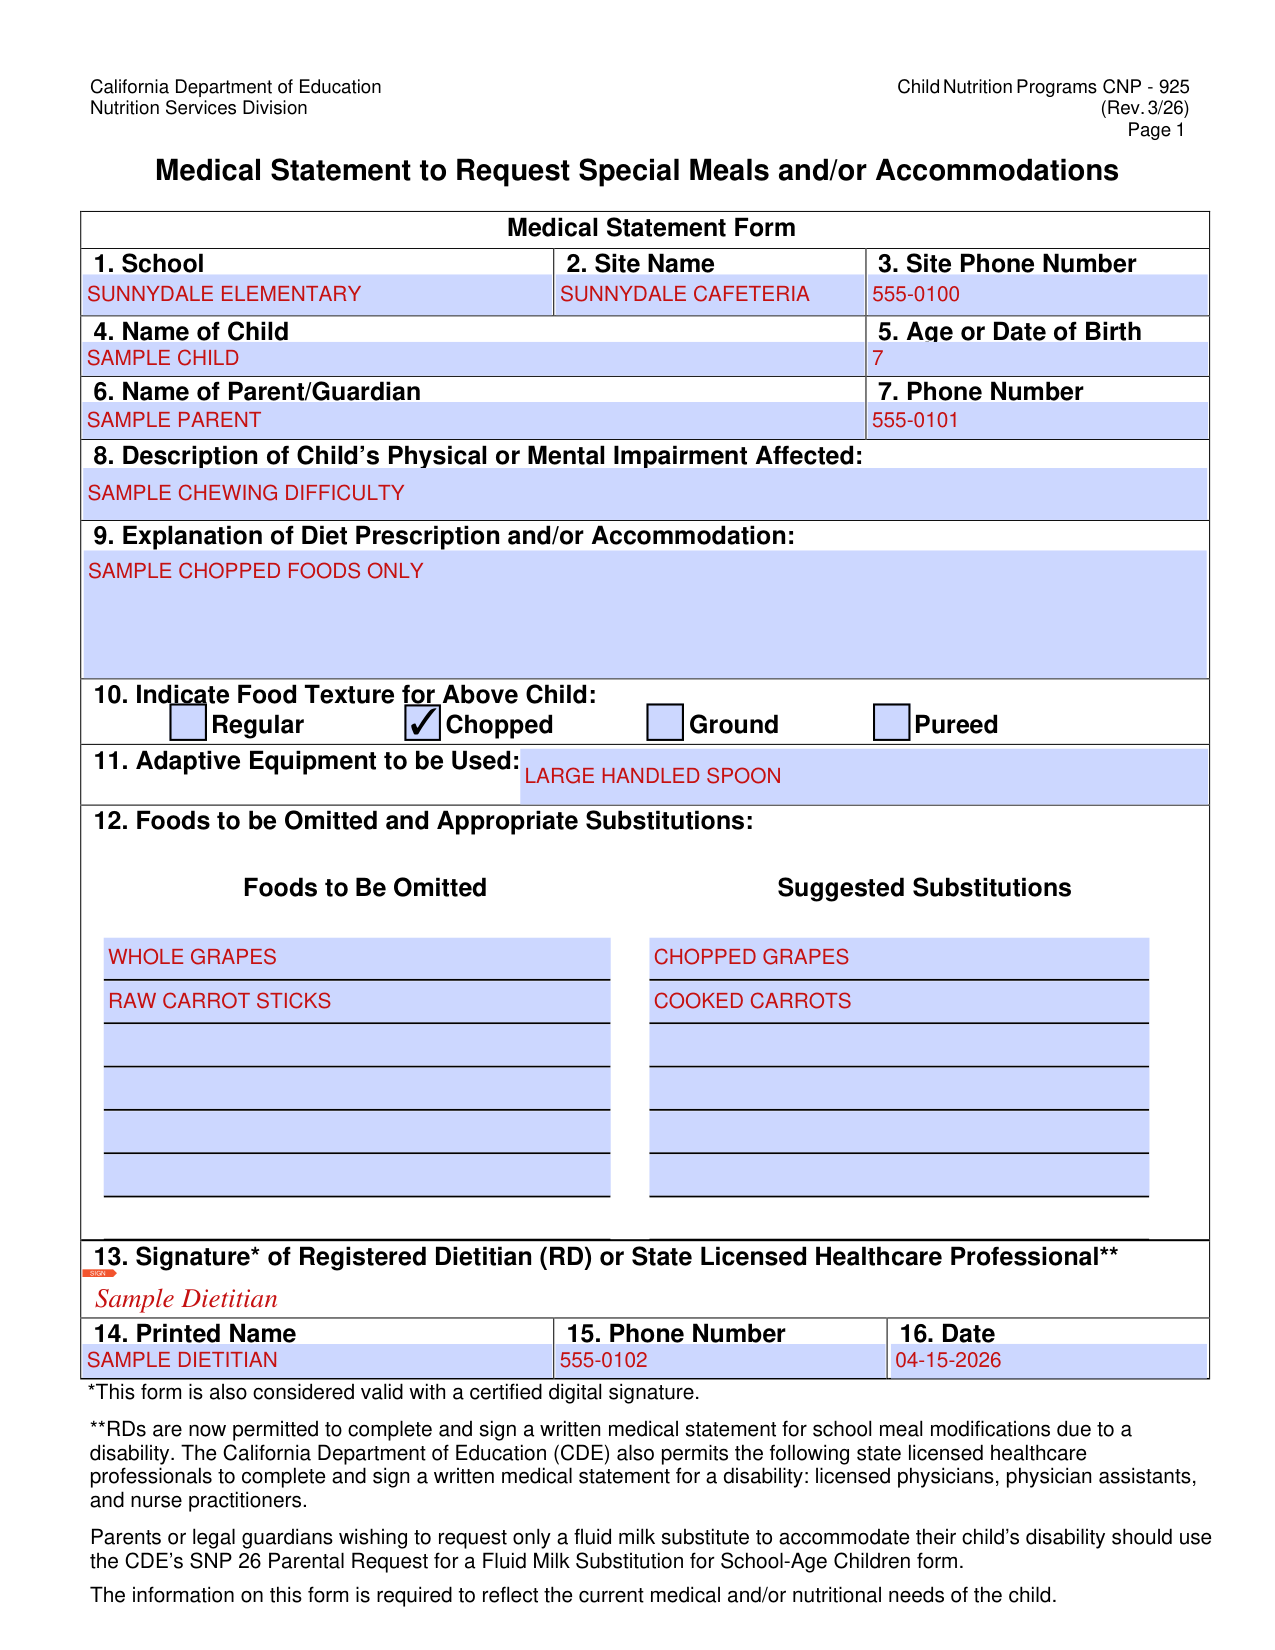
How to fill out Form CNP-925, box by box
School, site and site phone number

In School, print the name of the school that is providing the form to the parent/legal guardian.
In Site, print the name of the site where meals will be served.
In Site Phone Number, print the phone number of site where meal will be served.
Name of child, age or date of birth, parent/guardian and phone number

In Name of Child, print the name of the child to whom the information pertains.
In Age of Child, print the age of the child. For infants, please use date of birth.
In Name of Parent/Legal Guardian, print the name of the person requesting the child's medical statement.
In Phone Number, print the phone number of parent/legal guardian.
Description of impairment and explanation of diet prescription

In Description of Child's Physical or Mental Impairment Affected, describe how the physical or mental impairment restricts the child's diet.
In Explanation of Diet Prescription and/or Accommodation, describe a specific diet or accommodation that has been prescribed by the RD or state licensed healthcare professional.
Food texture and adaptive equipment
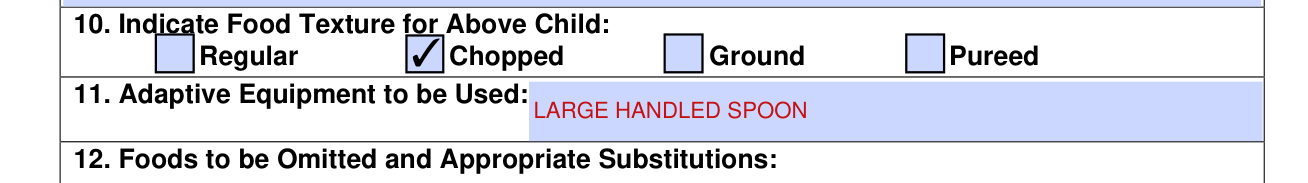
In Indicate Food Texture, if the child does not need any modification, check Regular.
In Adaptive Equipment to be Used, describe specific equipment required to assist the child with dining (e.g., sippy cup, large handled spoon, wheelchair accessible furniture, etc.).
Foods to be omitted and suggested substitutions
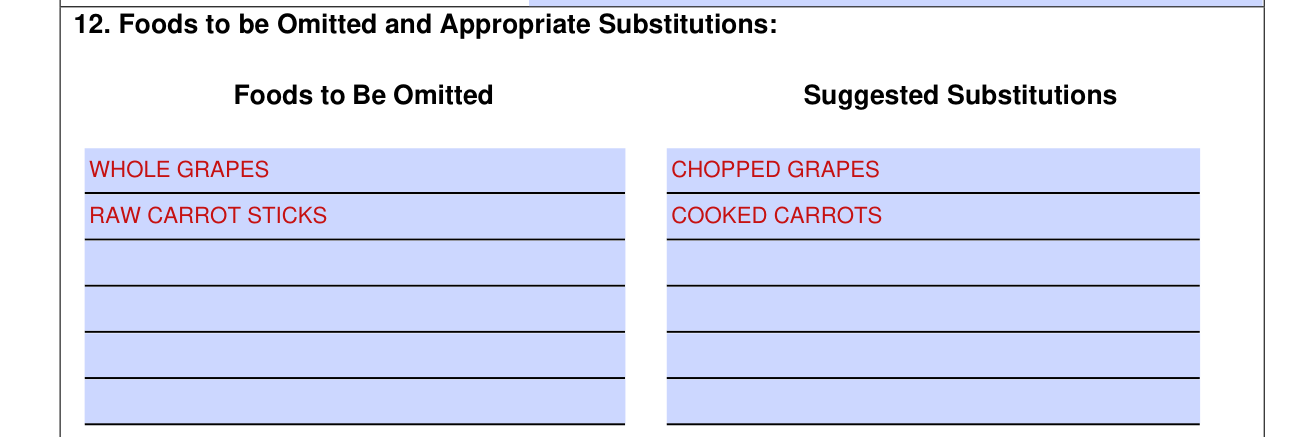
In Foods to be Omitted, list specific foods that must be omitted.
In Suggested Substitutions, list specific foods to include in the diet.
Signature, printed name, phone number and date

In Signature of RD or State Licensed Healthcare Professional: the signature of the RD or state licensed healthcare professional requesting the special meal or accommodation.
For box 13, Signature of Registered Dietitian (RD) or State Licensed Healthcare Professional: the California Department of Education (CDE) also permits the following state licensed healthcare professionals to complete and sign a written medical statement for a disability: licensed physicians, physician assistants, and nurse practitioners.
For box 13, Signature of Registered Dietitian (RD) or State Licensed Healthcare Professional, this form is also considered valid with a certified digital signature.
In Printed Name, print name of RD or state licensed healthcare professional.
In Phone Number, print the phone number of RD or state licensed healthcare professional.
In Date, print the date RD or state licensed healthcare professional signed the form.
More rules for Form CNP-925
The information on this form is required to reflect the current medical and/or nutritional needs of the child.
Common questions about Form CNP-925
When is this form not the right one?
Parents or legal guardians wishing to request only a fluid milk substitute to accommodate their child's disability should use the CDE's SNP 26 Parental Request for a Fluid Milk Substitution for School-Age Children form.
Sources
[1] Form CNP-925 (Rev. 3/26), Medical Statement to Request Special Meals and/or Accommodations, California Department of Education (the Official source link on this page).