

Form DHCS 6182 at a glance
What it is: Nonemergency Medical Transportation (NEMT) Require Justification, from the Department of Health Care Services.
Who signs: The Licensed Provider signs (No proxy, no stamps).
A filled-in Form DHCS 6182 example: a clinic requests one transport to a routine visit

How to fill out Form DHCS 6182, box by box
Patient, SNF face sheet and Dates of Service

In order to appropriately evaluate your request, complete all form fields including licensed provider signature and date of signature. If any field is incomplete, further documentation may be requested. This form constitutes a prescription. [References: California Code of Regulations (CCR), Title 22, Sections 51003, 51303, 51323 and the Medi-Cal Provider Manual]
Enter 1. Patient's Name and 2. Medical I. D. Number.
In Box 3, mark the current Skilled Nursing Facility (SNF) face sheet as attached, since this patient currently resides in a SNF, or as not applicable, since this patient resides at home.
In Box 4, Dates of Service (DOS), enter From and To.
Appointment Time and Day(s) of the week
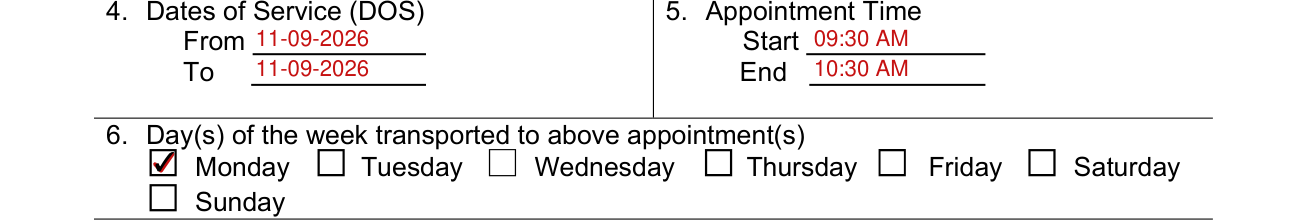
In Box 5, Appointment Time, enter Start and End.
In Box 6, mark the Day(s) of the week transported to above appointment(s): Monday, Tuesday, Wednesday, Thursday, Friday, Saturday, Sunday.
Documentation, diagnosis and treatment plan

In Box 7, mark Documentation is attached, since transport is not to the nearest facility that can meet the patient's medical needs, or not applicable, as transport is to the nearest facility that can meet the patient's medical needs. In Box 8, enter the Diagnosis specific to visit(s).
In Box 9, enter the Medical purpose/justification for visit(s).
In Box 10, mark that the prescribed treatment plan including problems, interventions, and goals (along with why original goals were not met, if this is a reauthorization TAR) is attached or is not applicable. Mark is attached, since request is for multiple transports that are ongoing to same provider for same chronic diagnosis. Mark is not applicable, since request is for a single transport for a routine visit or one-time medical event.
How the patient mobilizes and the required mode of transport
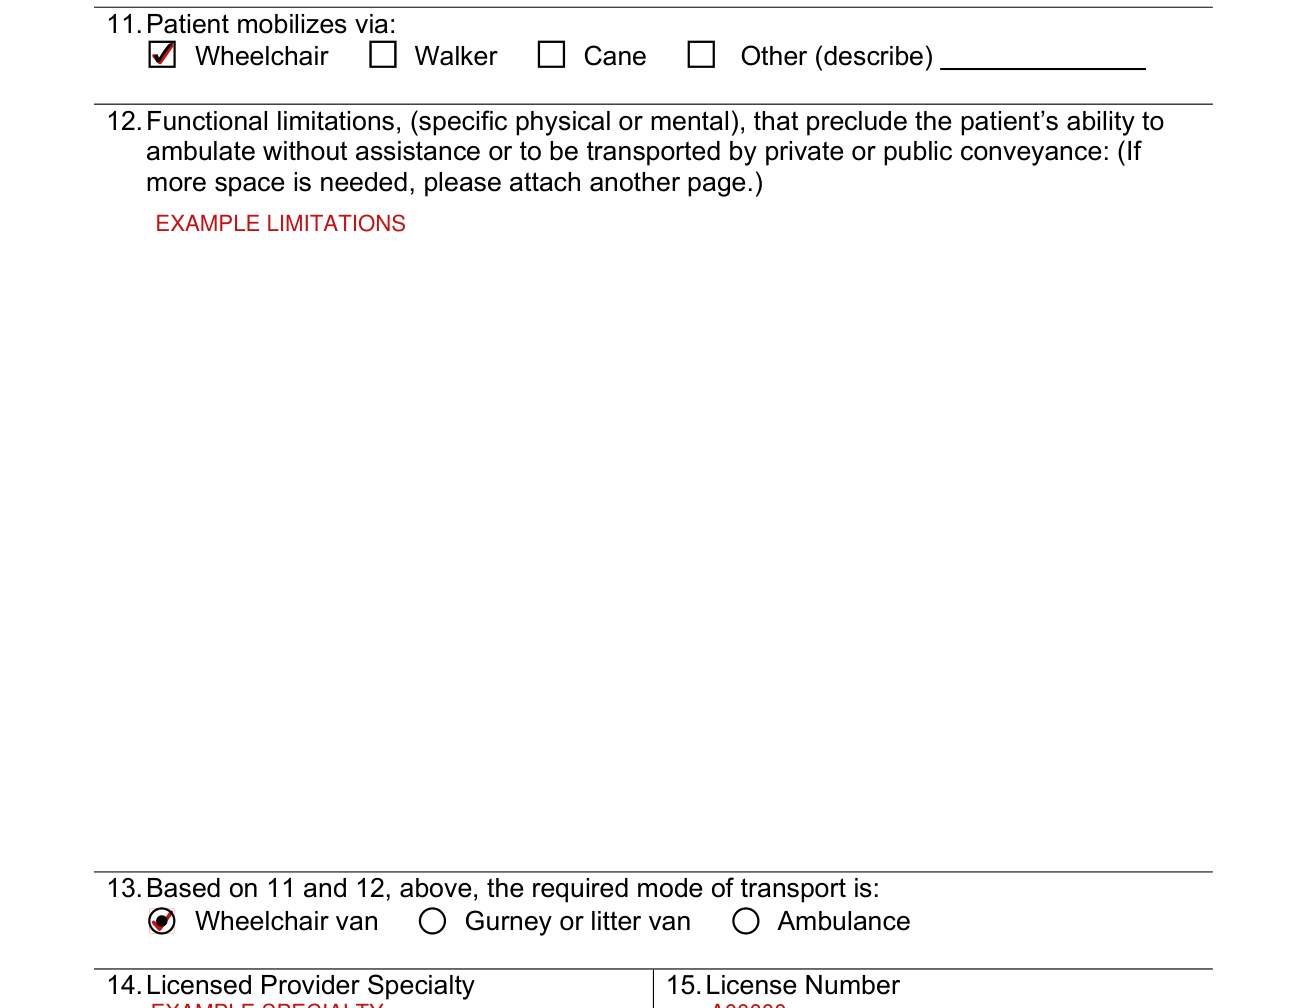
In Box 11, mark how the patient mobilizes via: Wheelchair, Walker, Cane or Other (describe).
In Box 12, enter the Functional limitations, (specific physical or mental), that preclude the patient's ability to ambulate without assistance or to be transported by private or public conveyance. If more space is needed, please attach another page.
In Box 13, based on 11 and 12, mark the required mode of transport: Wheelchair van, Gurney or litter van or Ambulance.
Licensed Provider and signature
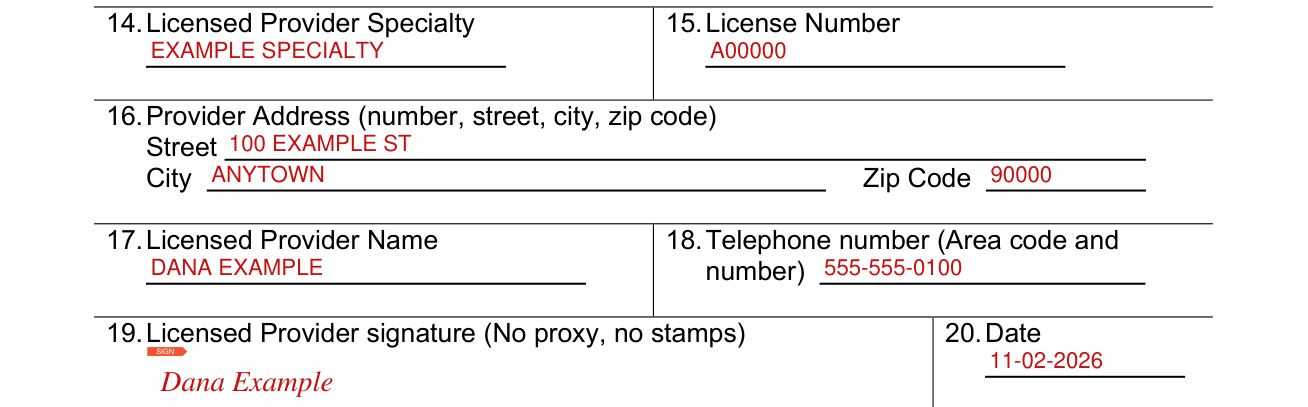
Enter the Licensed Provider Specialty in Box 14 and the License Number in Box 15.
In Box 16, enter the Provider Address (number, street, city, zip code): Street, City and Zip Code.
Enter the Licensed Provider Name in Box 17 and the Telephone number (Area code and number) in Box 18.
Sign at SIGN with the Licensed Provider signature (No proxy, no stamps) in Box 19, and enter the Date in Box 20.
Sources
[1] Form DHCS 6182 (Revised 04/2023), Nonemergency Medical Transportation (NEMT) Require Justification, Department of Health Care Services (the Official source link on this page).