
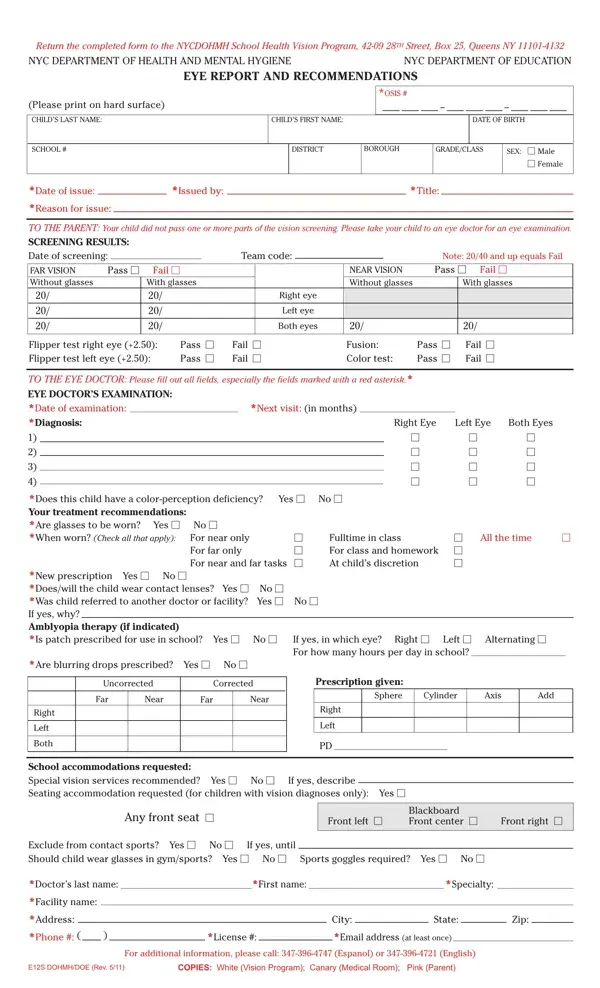
Please take your child to an eye doctor for an examination.
Where to send: return the completed form to School Health Vision Program, 42-09 28th Street, Box 25, L.I.C. NY 11101-4132.
Fax: please fax completed forms to: 347-396-8965.
Questions: if you have questions about the form, please call: 855-771-EYES (3937).
Very low vision: if your child has very low vision, he or she may be eligible for special services provided by the New York City Public Schools.
| Question | Answer |
|---|---|
| Form Name | Form E12S |
| Form Length | 2 pages |
| Fillable? | No |
| Fillable fields | 0 |
| Avg. time to fill out | 6 min |
| Edition | 7 2025 |
| Where to send | School Health Vision Program |
| Matches the agency's file | Yes, checked October 1, 2026 |
| Other names | E12S, E-12S, E12S DOHMH-NYCPS, Eye Report and Recommendations |
| Official source | Form E12S (Rev 7 2025), NYC Department of Health and Mental Hygiene |
Form E12S Dohmh Doe isn’t the one you’re looking for?