

Form FA-24 at a glance
What it is: This form is the Nevada Medicaid and Check Up Authorization Request for Personal Care Services (PCS).
Who signs: Transfers: complete Section 2: A and page 3, with Recipient/LRI/PCR Signature with Date, and Provider Signature with Date.
A filled-in Form FA-24 example: an initial personal care services request
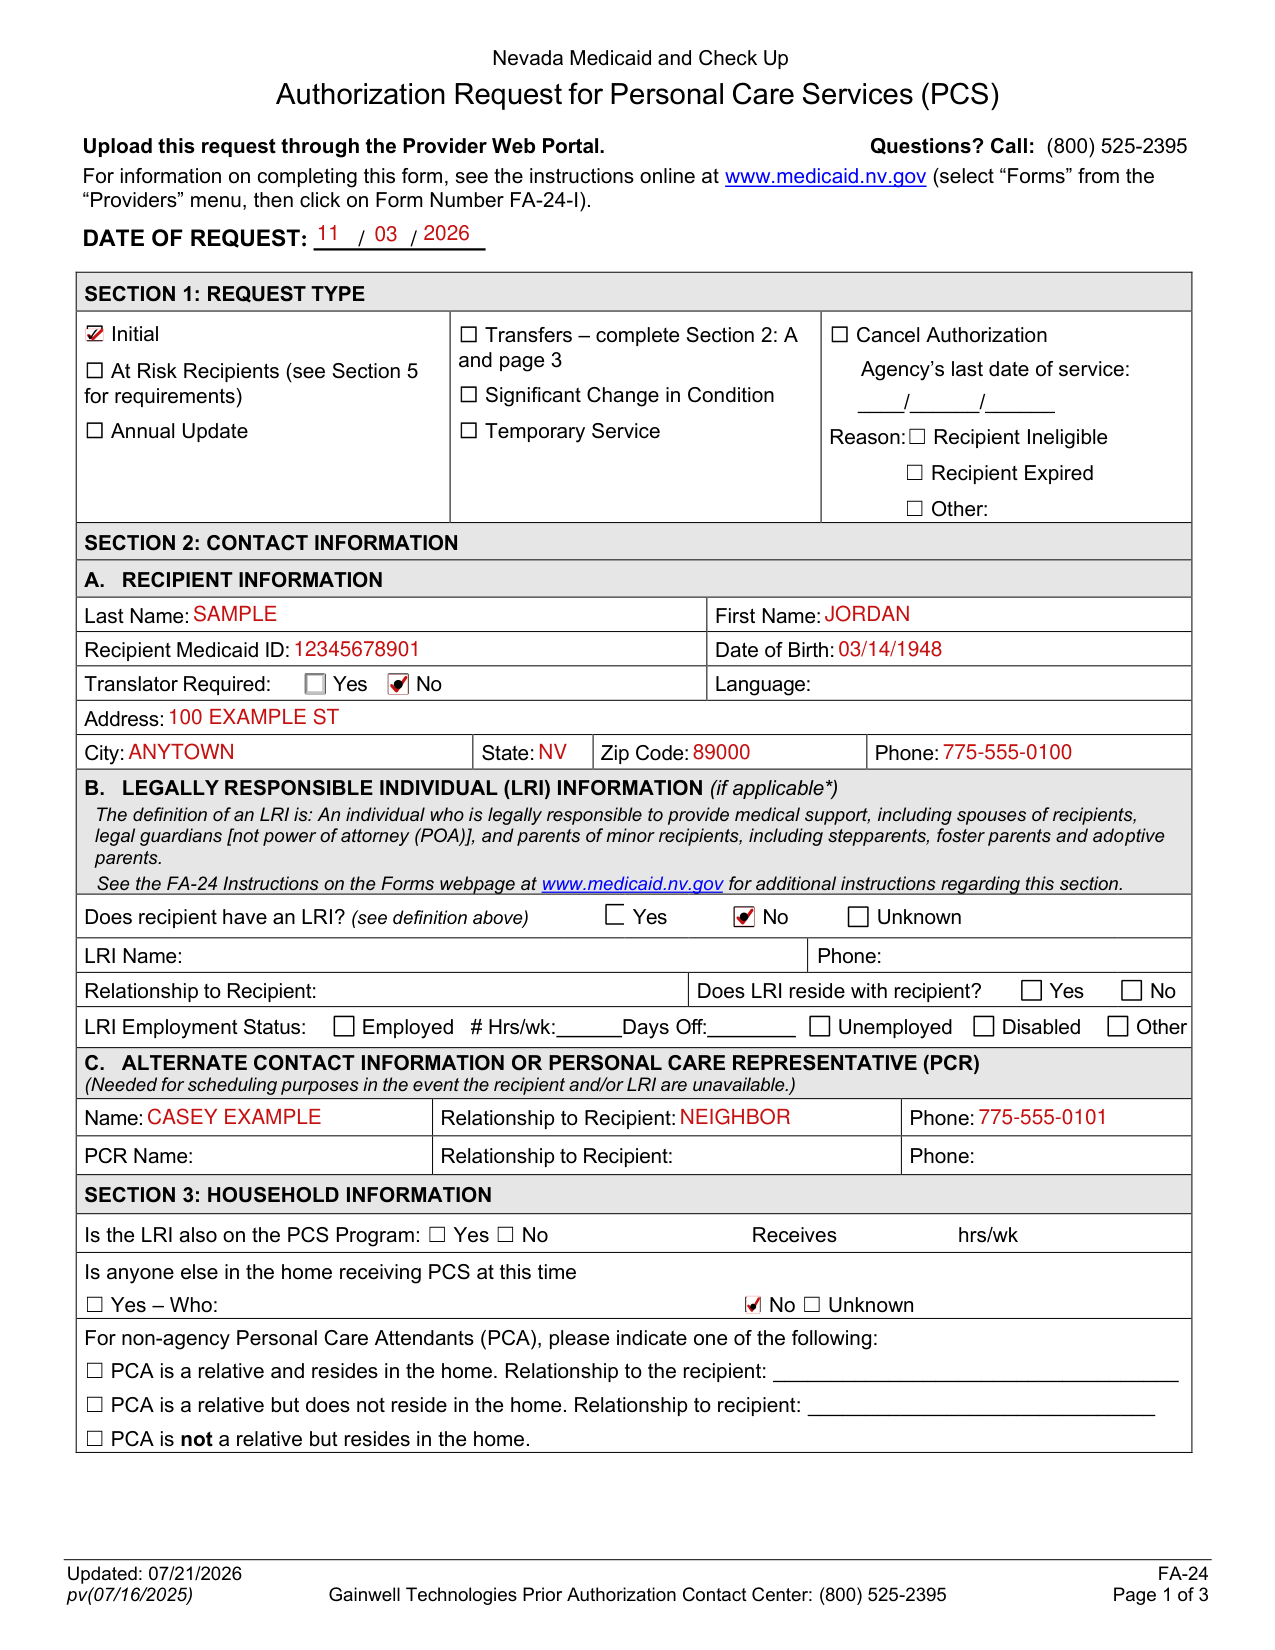
How to fill out Form FA-24, box by box
Date of request and request type
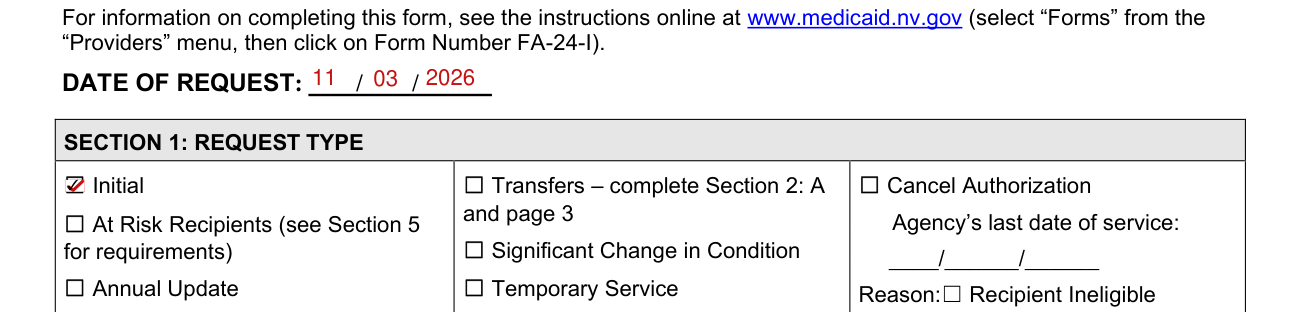
Enter the DATE OF REQUEST.
In SECTION 1: REQUEST TYPE, check Initial, At Risk Recipients (see Section 5 for requirements), Significant Change in Condition, Annual Update or Temporary Service.
Cancel Authorization

Cancel Authorization: enter the Agency's last date of service and check the Reason: Recipient Ineligible, Recipient Expired or Other.
Recipient information
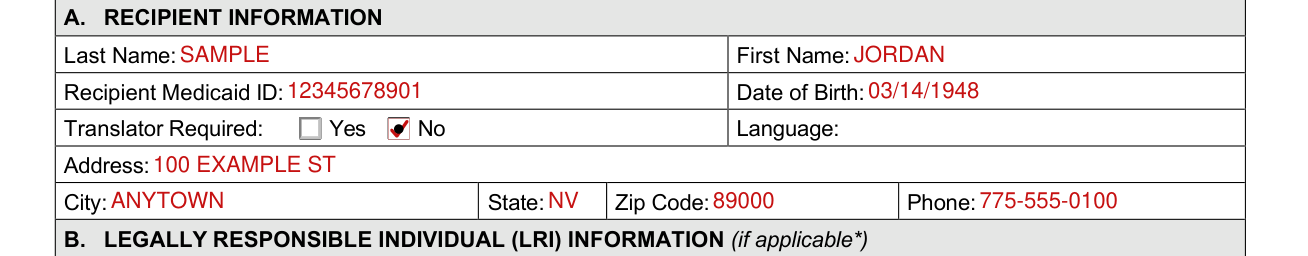
In SECTION 2: CONTACT INFORMATION, A. RECIPIENT INFORMATION, enter Last Name, First Name, Recipient Medicaid ID, Date of Birth, Language, Address, City, State, Zip Code and Phone, and mark Translator Required Yes or No.
Legally responsible individual (LRI) information
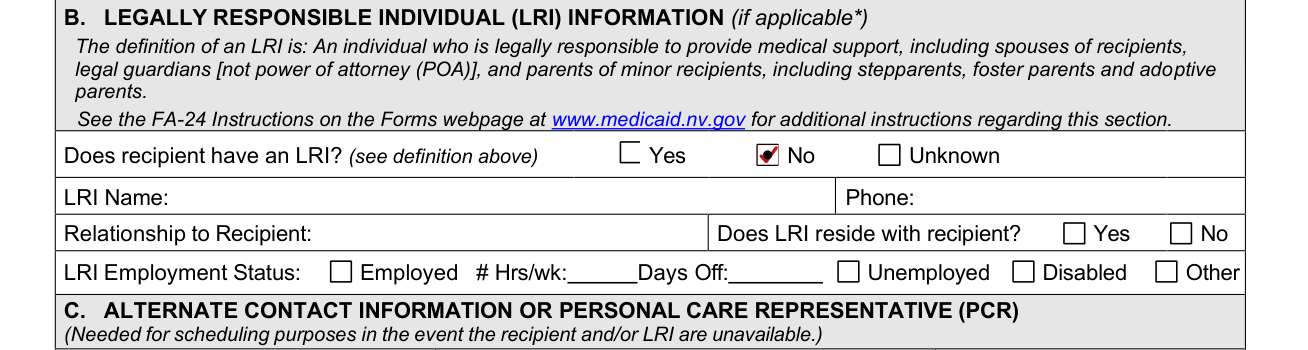
B. LEGALLY RESPONSIBLE INDIVIDUAL (LRI) INFORMATION (if applicable*): The definition of an LRI is: An individual who is legally responsible to provide medical support, including spouses of recipients, legal guardians [not power of attorney (POA)], and parents of minor recipients, including stepparents, foster parents and adoptive parents.
Does recipient have an LRI? Mark Yes, No or Unknown.
For an LRI, enter LRI Name, Phone and Relationship to Recipient, mark Does LRI reside with recipient? Yes or No, and under LRI Employment Status mark Employed with # Hrs/wk and Days Off, Unemployed, Disabled or Other.
Alternate contact or personal care representative (PCR)

C. ALTERNATE CONTACT INFORMATION OR PERSONAL CARE REPRESENTATIVE (PCR) is needed for scheduling purposes in the event the recipient and/or LRI are unavailable: enter Name, Relationship to Recipient and Phone, and the PCR Name, Relationship to Recipient and Phone.
Household information
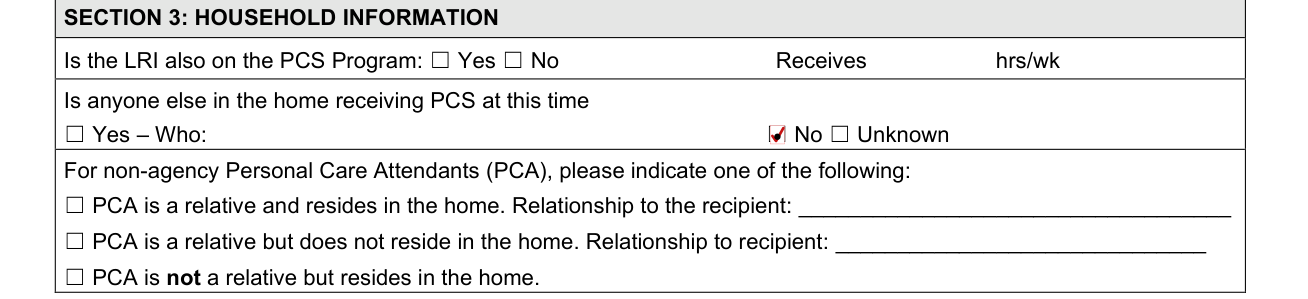
In SECTION 3: HOUSEHOLD INFORMATION, mark Is the LRI also on the PCS Program: Yes or No, with the hrs/wk the LRI receives.
Is anyone else in the home receiving PCS at this time: Yes with Who, No or Unknown.
For non-agency Personal Care Attendants (PCA), indicate one of the following: PCA is a relative and resides in the home, with the Relationship to the recipient; PCA is a relative but does not reside in the home, with the Relationship to recipient; or PCA is not a relative but resides in the home.
Diagnoses and tasks
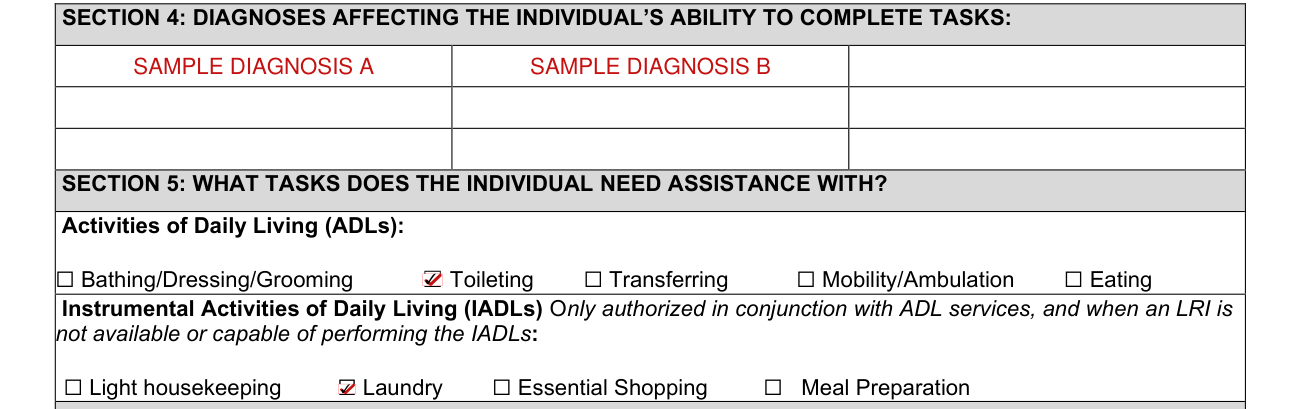
SECTION 4: DIAGNOSES AFFECTING THE INDIVIDUAL'S ABILITY TO COMPLETE TASKS: enter the diagnoses.
Section 5: What tasks does the individual need assistance with? Check Activities of Daily Living (ADLs): Bathing/Dressing/Grooming, Toileting, Transferring, Mobility/Ambulation or Eating. Instrumental Activities of Daily Living (IADLs) are only authorized in conjunction with ADL services, and when an LRI is not available or capable of performing the IADLs: Light housekeeping, Laundry, Essential Shopping or Meal Preparation.
At risk recipients (for initial requests only)

SECTION 6: AT RISK RECIPIENTS (For Initial requests only): In order to qualify for an immediate service authorization, a recipient must live alone and be unable to independently perform one of the ADLs Toilet, Ambulate or Feed themselves.
Summary of major incidents and comments

Section 7: Summary of major incidents including serious occurrences and changes in condition within the last 120 days: provide a summary of all significant changes or incidents.
SECTION 8: COMMENTS: General comments that would assist an assessor in completing an accurate assessment; include reason for request.
Personal care agency and the person completing this request
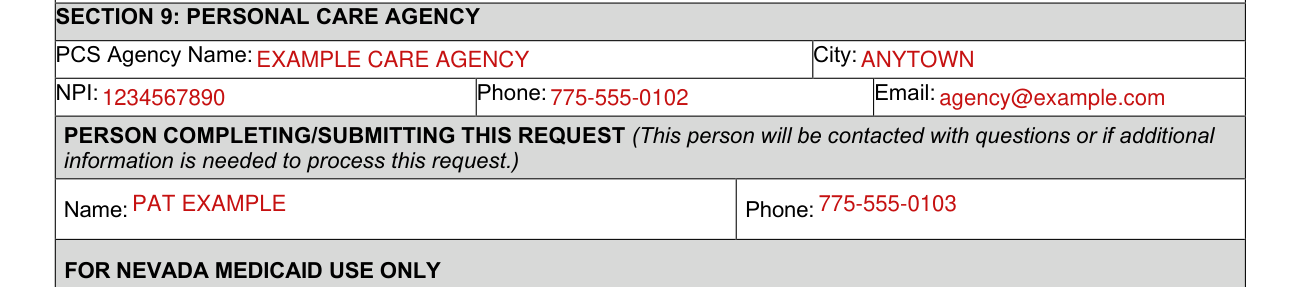
In SECTION 9: PERSONAL CARE AGENCY, enter the PCS Agency Name, City, NPI, Phone and Email.
Under PERSON COMPLETING/SUBMITTING THIS REQUEST, enter Name and Phone: this person will be contacted with questions or if additional information is needed to process this request.
Transfer requests only

SECTION 10: TRANSFER REQUESTS ONLY: enter the Reason for transfer of service to new provider.
Recipient/LRI/PCR must initial, complete and sign: I understand that I am authorized to receive service from only one agency at a time. Enter Recipient/LRI/PCR (print name) and Relationship to Recipient.
Recipient/LRI/PCR, for the Medicaid recipient, certifies that they have completed this form and understand the actions that will take place upon their signature.
New provider information
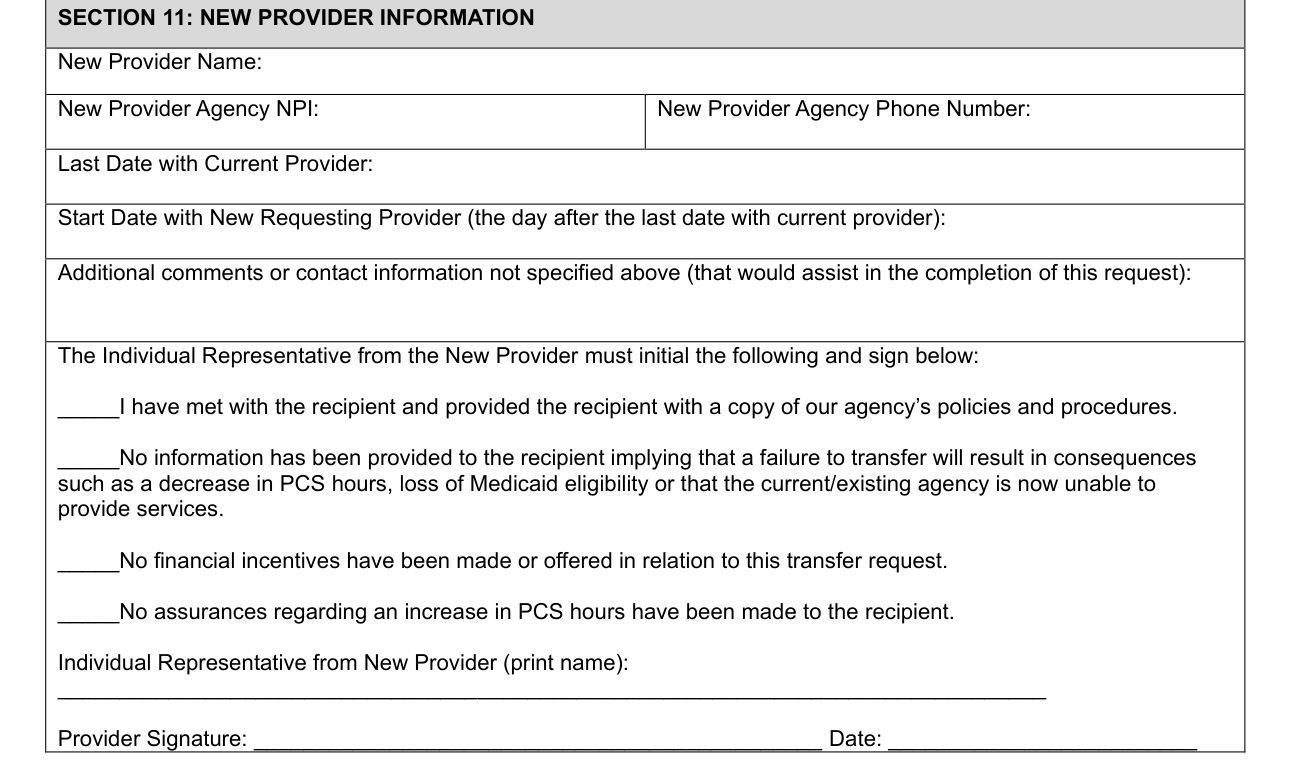
SECTION 11: NEW PROVIDER INFORMATION: enter the New Provider Name, New Provider Agency NPI, New Provider Agency Phone Number, Last Date with Current Provider, Start Date with New Requesting Provider (the day after the last date with current provider) and Additional comments or contact information not specified above (that would assist in the completion of this request).
The Individual Representative from the New Provider must initial and sign: enter Individual Representative from New Provider (print name).
More rules for Form FA-24
This referral/authorization is not a guarantee of payment.
Common questions about Form FA-24
Where do I file it?
Upload this request through the Provider Web Portal. Questions? Call: (800) 525-2395. For information on completing this form, see the instructions online at www.medicaid.nv.gov (select “Forms” from the “Providers” menu, then click on Form Number FA-24-I).
Sources
[1] Form FA-24 (07/16/2025), Nevada Medicaid and Check Up Authorization Request for Personal Care Services (PCS), Nevada Medicaid (the Official source link on this page).
