


FA-29 at a glance
What it is: The Nevada Medicaid and Nevada Check Up Prior Authorization Data Correction Form is to correct or modify non-clinical, administrative data on a previously submitted prior authorization request.
Where and when to file: Upload this form through the Provider Web Portal. Please allow up to 30 days for processing.
A filled-in FA-29 example: a provider corrects an admission date
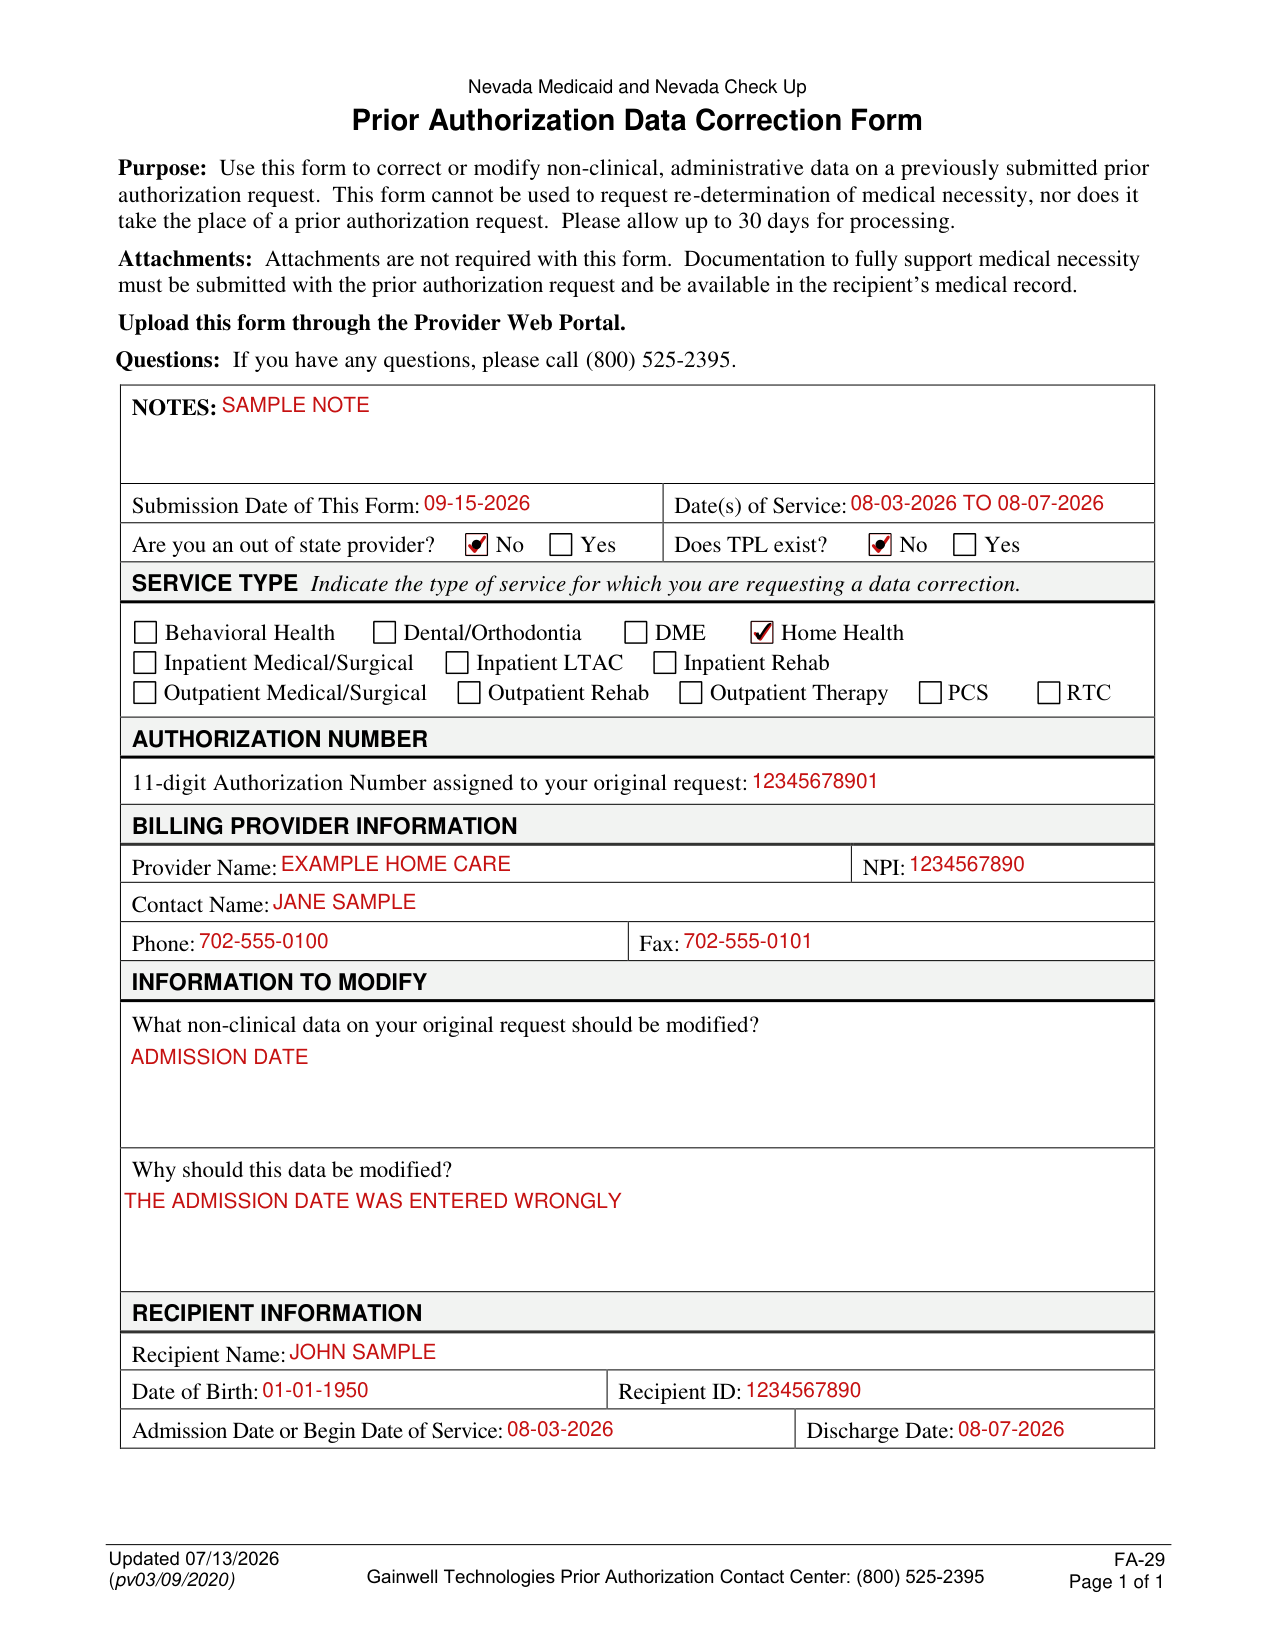
How to fill out FA-29, box by box
Submission date, dates of service, out of state provider and TPL

Enter the Submission Date of This Form and the Date(s) of Service.
Mark No or Yes for Are you an out of state provider? and for Does TPL exist?
Service type

Indicate the type of service for which you are requesting a data correction: Behavioral Health, Dental/Orthodontia, DME, Home Health, Inpatient Medical/Surgical, Inpatient LTAC, Inpatient Rehab, Outpatient Medical/Surgical, Outpatient Rehab, Outpatient Therapy, PCS or RTC.
Authorization number and billing provider information
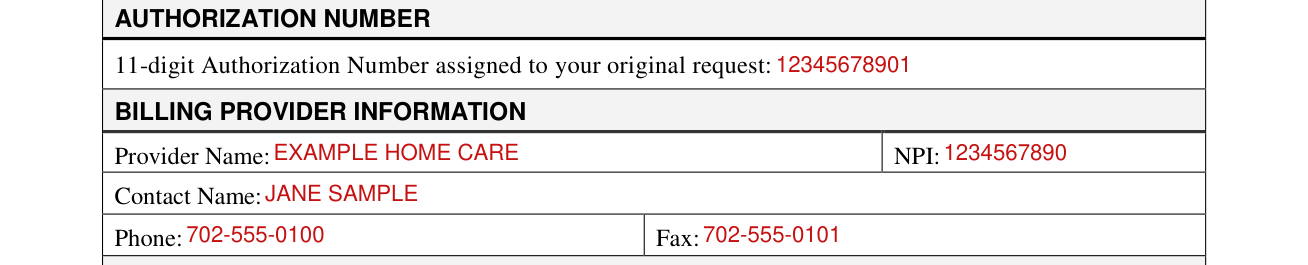
Enter the 11-digit Authorization Number assigned to your original request.
Under BILLING PROVIDER INFORMATION, enter the Provider Name, NPI, Contact Name, Phone and Fax.
Information to modify and recipient information
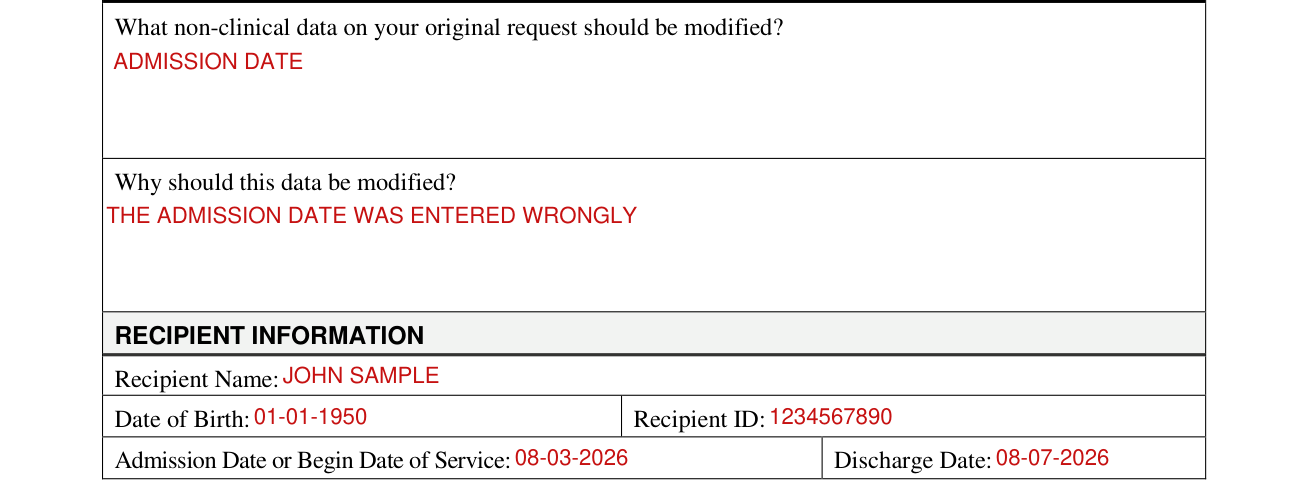
INFORMATION TO MODIFY: What non-clinical data on your original request should be modified? Why should this data be modified?
Under RECIPIENT INFORMATION, enter the Recipient Name, Date of Birth, Recipient ID, Admission Date or Begin Date of Service and Discharge Date.
More rules for FA-29
Attachments are not required with this form. Documentation to fully support medical necessity must be submitted with the prior authorization request and be available in the recipient's medical record.
If you have any questions, please call (800) 525-2395.
Common questions about FA-29
When is this form not the right one?
This form cannot be used to request re-determination of medical necessity, and it does not take the place of a prior authorization request.
Sources
[1] Form FA-29, Nevada Medicaid and Nevada Check Up Prior Authorization Data Correction Form, Nevada Medicaid (the Official source link on this page).