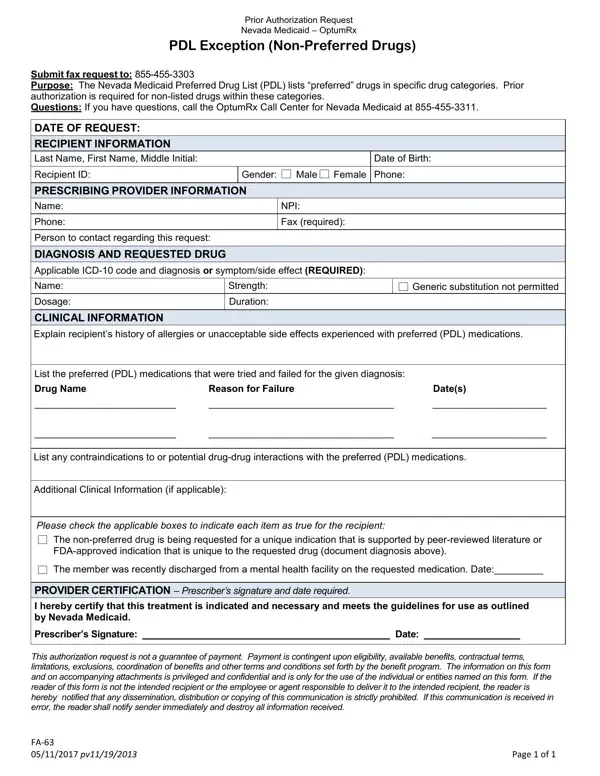
How to Fill Out Form FA-63

Form FA-63 at a glance

What it is: The Prior Authorization Request for Nevada Medicaid - OptumRx PDL Exception (Non-Preferred Drugs).

Who signs: PROVIDER CERTIFICATION - Prescriber's signature and date required.

A filled-in Form FA-63 example: a prescriber requests a non-preferred drug
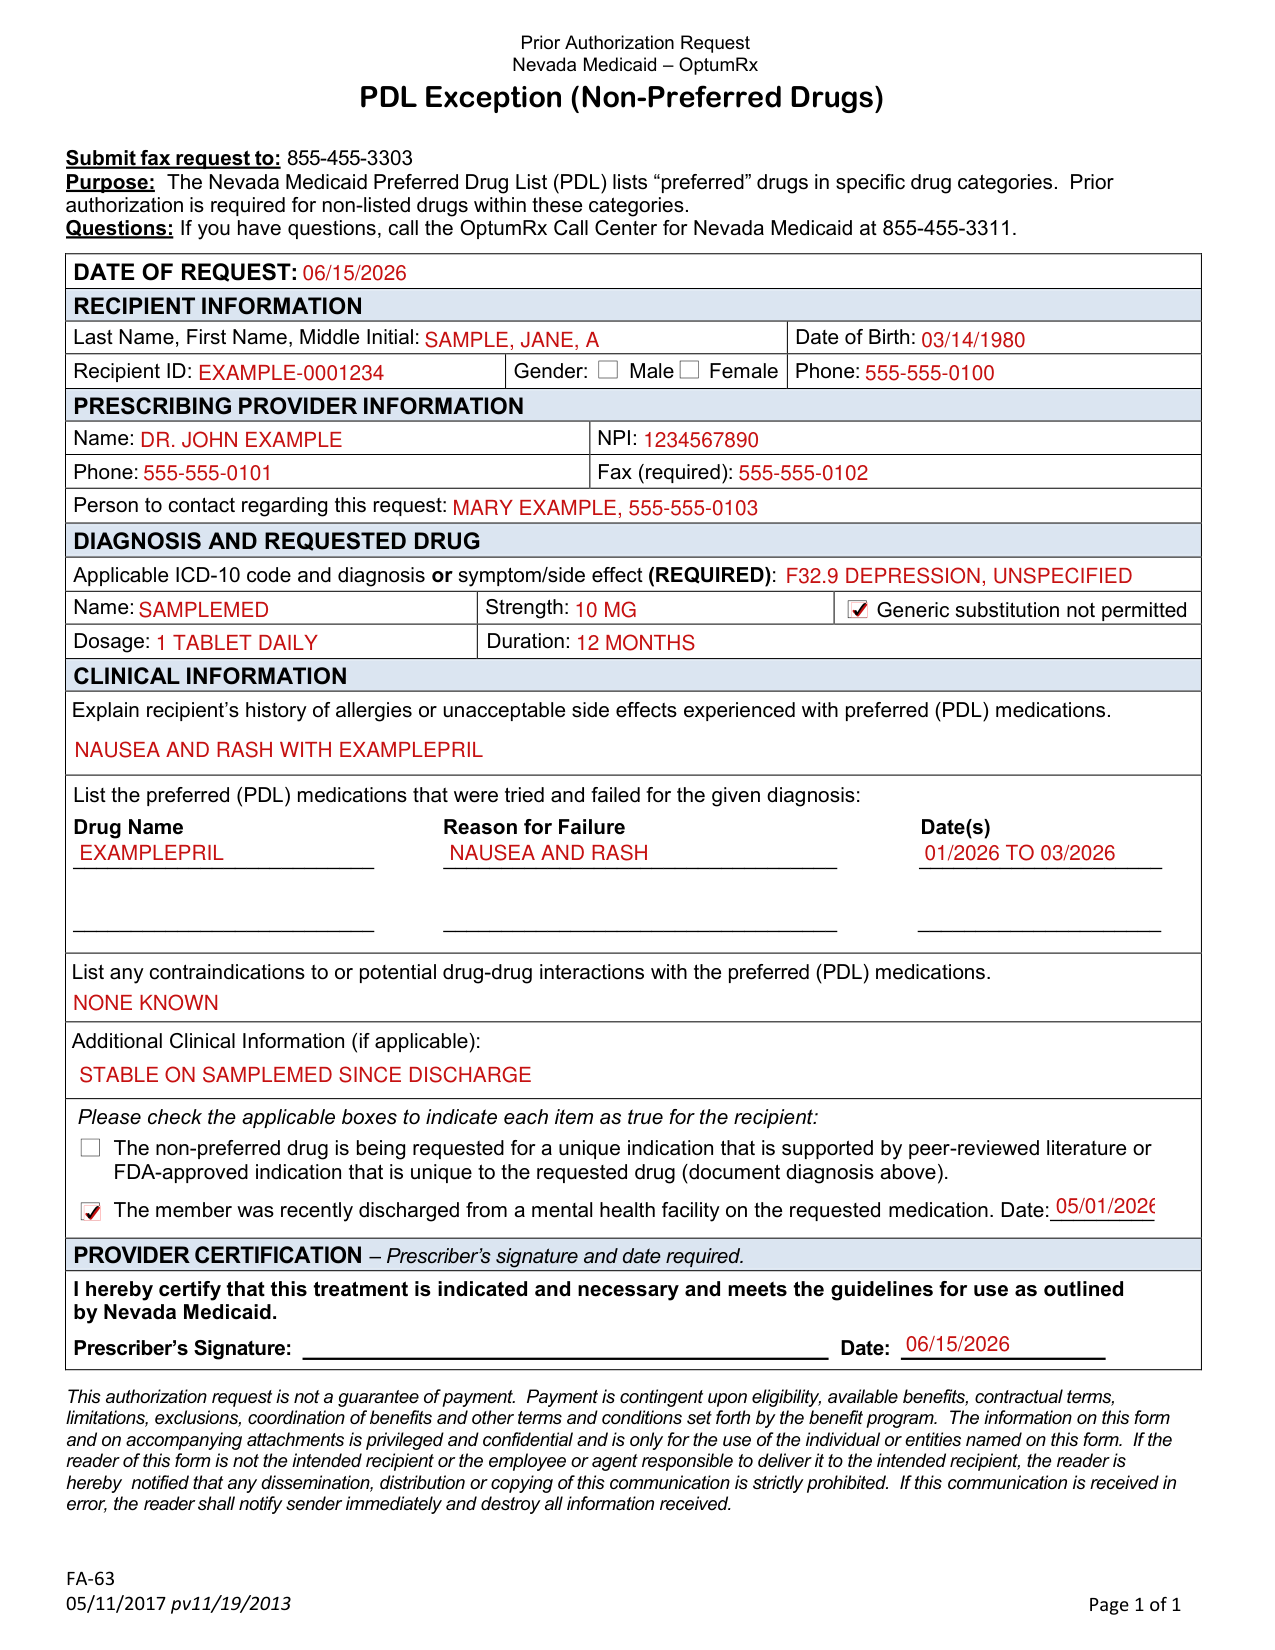
Form FA-63 example filled out, example: a prescriber requests a non-preferred drug
A prescriber submits this form to request a non-preferred drug for a Medicaid recipient. The recipient tried one preferred medication that failed, so one row of the table is filled. The picture shows page 1 and all its values are invented. The dose is one tablet daily for 12 months and generic substitution is not permitted. The recipient was discharged from a mental health facility on the requested medication on 05/01/2026. The unique indication box stays empty because the story gives no unique indication.

How to fill out Form FA-63, box by box

Date of request and recipient information
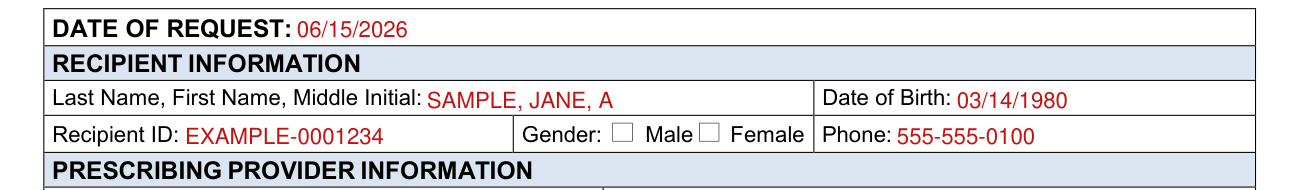
Form FA-63 example filled out, date of request and recipient information

Enter the DATE OF REQUEST, then under RECIPIENT INFORMATION the Last Name, First Name, Middle Initial, Date of Birth, Recipient ID, Gender (Male or Female) and Phone.

Prescribing provider information
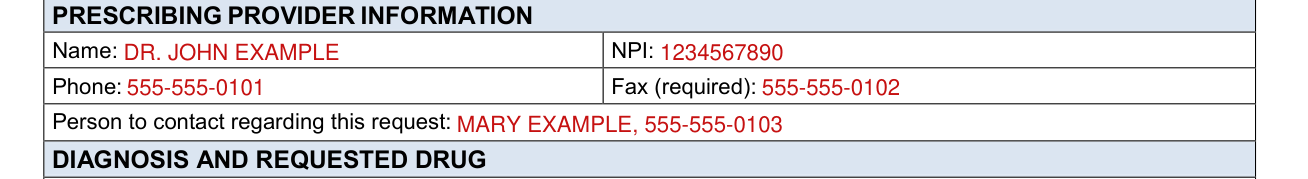
Form FA-63 example filled out, prescribing provider information

Under PRESCRIBING PROVIDER INFORMATION, enter the Name, NPI, Phone, Fax (required) and the Person to contact regarding this request.

Diagnosis and requested drug

Form FA-63 example filled out, diagnosis and requested drug

Under DIAGNOSIS AND REQUESTED DRUG, enter the Applicable ICD-10 code and diagnosis or symptom/side effect (REQUIRED).

Enter the Name, Strength, Dosage and Duration of the requested drug. Generic substitution not permitted is a check box.

Clinical information

Form FA-63 example filled out, clinical information

Under CLINICAL INFORMATION, explain the recipient's history of allergies or unacceptable side effects experienced with preferred (PDL) medications.

List the preferred (PDL) medications that were tried and failed for the given diagnosis, with the Drug Name, Reason for Failure and Date(s).

List any contraindications to or potential drug-drug interactions with the preferred (PDL) medications.

Enter any Additional Clinical Information (if applicable).

Applicable boxes for the recipient

Form FA-63 example filled out, applicable boxes for the recipient

Check the applicable boxes to indicate each item as true for the recipient: The non-preferred drug is being requested for a unique indication that is supported by peer-reviewed literature or FDA-approved indication that is unique to the requested drug.

Check The member was recently discharged from a mental health facility on the requested medication, and enter the Date.

Prescriber's signature and date

Form FA-63 example filled out, prescriber's signature and date

By signing, the prescriber certifies that this treatment is indicated and necessary and meets the guidelines for use as outlined by Nevada Medicaid. Enter the Prescriber's Signature and Date.

When prior authorization is required

Prior authorization is required for non-listed drugs within these categories

Submit fax request to: 855-455-3303. Purpose: The Nevada Medicaid Preferred Drug List (PDL) lists “preferred” drugs in specific drug categories. Prior authorization is required for non-listed drugs within these categories. Questions: If you have questions, call the OptumRx Call Center for Nevada Medicaid at 855-455-3311.

Sources

[1] Form FA-63, Prior Authorization Request, Nevada Medicaid (the Official source link on this page).

Form FA-63 Nevada Medicaid Prior Authorization Request PDF Details

The Nevada Medicaid Preferred Drug List (PDL) lists “preferred” drugs in specific drug categories.

Fax to: Submit fax request to: 855-455-3303.

Questions: If you have questions, call the OptumRx Call Center for Nevada Medicaid at 855-455-3311.

Required: Applicable ICD-10 code and diagnosis or symptom/side effect; Fax.

Tried and failed: Drug Name, Reason for Failure, Date(s).

Who signs: Prescriber's signature and date required.

Payment: This authorization request is not a guarantee of payment.

QuestionAnswer
Form NameForm FA-63 Nevada Medicaid Prior Authorization Request
Form Length1 pages
Fillable?No
Fillable fields0
Avg. time to fill out3 min
Other namesFA-63, Form FA-63, Nevada Medicaid FA-63, OptumRx PDL Exception
Official sourceForm FA-63, Prior Authorization Request, Nevada Medicaid